Our mission, as God-fearing and God-loving patriots, is to defend this Constitutional Republic and to increase its greatness, in all good things and ways, by using our voices in free but courteous speech, by discussing the happenings of the world and coming to a profound understanding of those things, and by sharing and promulgating these Truths on both this platform and others.
The free image of the trumpets of the Battle of Jericho is courtesy of Shutterstock and Google Images.
Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats by Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering are cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
>>>>>>>>>>>>>>>>>>>>
Dismantle Them. Salt The Ground. Start All Over Again. Do It Right Next Time: Part One.
This is about completely dismantling the CDC, the FDA, NIH, and NIAID; and rebuilding them following a new format: that of actually serving the health of the American public. Up until 4 August 2026, this “edifice” named above had evolved into a funds-funneling vehicle for dangerous Gain-of-Function experiments in laboratories ranging from: Dr. Ralph Baric’s lab at UNC Chapel Hill (development of the SARS-CoV-2 “template” virus); to Dr. Zheng-li Shi’s laboratory at the Wuhan Institute of Virology (where the SARS-CoV-2 “template virus” was being “enhanced” prior to its being released in late fall 2019); to Dr. Peter Daszak’s EcoHealth Alliance (Gain-of-Function experiments funding via “grants” from NIH / NIAID); to NIAID and Moderna entering into an agreement (in 2015) to co-develop, co-own the Patents for, and share in the royalty payments for the use of, mRNA-1273 (SPIKEVAX), and of mRNA-1345 (mRESVIA.)
What does dismantling this “edifice” involve? Among many other aspects, in Yours Truly’s opinion: firing all current employees; stopping the funding applications for new research projects; stopping all current funding in place for approved research projects; cutting all ties to, and involvement with, pharmaceutical companies regarding development and manufacture of drugs and injectables; and, RESCINDING the agreement signed between the United States Department of Defense and NIH / NIAID. This agreement was signed between the United States Department of War (signature by Dr. Robert Kadlec, MD, as representative, on 4 August 2026), and the NIH / NIAID (signature by Dr. Jay Bhattacharya, director of NIH, on 5 August 2026), that ceded future development of injectable medicines (including influenza and COVID-19 bioweapon “vaccines”), in addition to other drugs, from NIH / NIAID to the Department of War; and, in addition, with NIH / NIAID providing “data and information”, along with to up to $2 Billion dollars in funding. (https://www.theqtree.com/2026/09/11/health-friday-9-11-2026-open-thread-25th-anniversary-of-9-11-nih-and-the-department-of-war-just-signed-a-new-agreement/.)
>>>>>>>>>>>>>>>>>>>>
The focus of today’s offering is the now-proven fact that the modRNA COVID-19 bioweapon “vaccines” (gene therapy injections) can cause cancer in “vaccinated” persons via THREE OF THE INGREDIENTS IN THESE “VACCINES.” Note: the appelation “lipid nanoparticle(s)” and the acronym “LNP(s)” are used interchangeably.
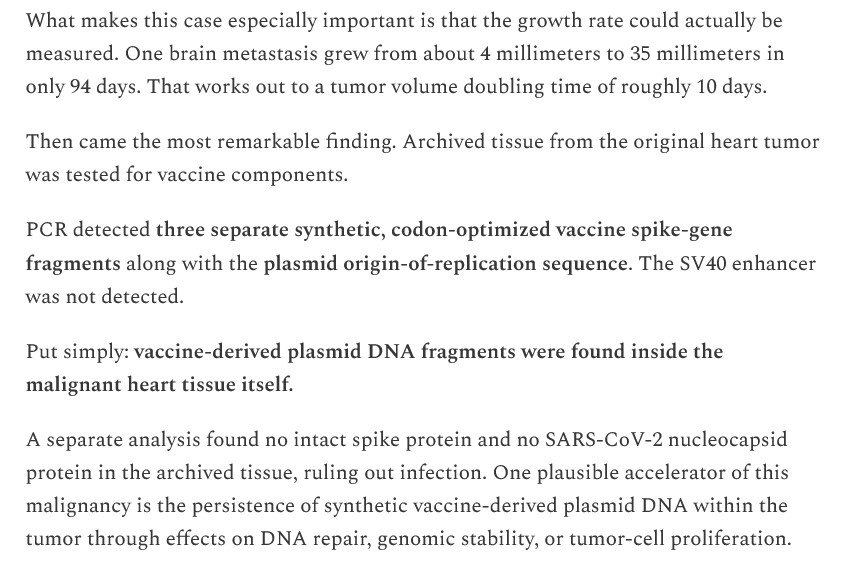
The first and second ingredients in the modRNA COVID-19 bioweapon “vaccines” (gene therapy injections) that cause cancer: the spike protein; and, the SV40 cancer promoter gene code piece. Please see: https://www.thefocalpoints.com/p/breaking-study-pfizer-covid-19-vaccine, “BREAKING STUDY: Pfizer COVID-19 “Vaccine” Plasmid DNA Found Inside Lethal Turbo Cancer of the Heart”, Nicolas Hulscher, MPH, 9 September 2026. The deceased was a 35-year-old male, with no personal or family history of cancer, who took the “primary series” of two injections of the Pfizer-BioNTech COVID-19 bioweapon “vaccine”, BNT162b2, in April and May 2021. 170 days after the second injection, the patient was diagnosed with a “large tumor” in the left atrium of his heart, and that had already metastasized to the brain. Despite numerous surgeries, chemotherapy, and radiation therapy, the patient ultimately passed away 675 days after the initial diagnosis. Please see the screenshots from the Hulscher article, below:
Look at the above again: The SV40 cancer promoter-enhancer was NOT found to be present. What WAS found to be present were “vaccine” spike protein fragments. This confirms that the spike protein in the Pfizer-BioNTech COVID-19 bioweapon “vaccines” can cause cancer. This is aside from the fact that the SV40 cancer promoter-enhancer gene code piece is ALSO in the Pfizer-BioNTech COVID-19 bioweapon “vaccines.” Please see: https://www.thefocalpoints.com/p/17-ways-mrna-shots-may-cause-cancer, “17 Ways mRNA Shots May Cause Cancer, According to Over 100 Studies”, Nicolas Hulscher, MPH, 24 June 2025.
**** This makes two ingredients (out of the three) which these modRNA-based injectables contain that can (and do) cause cancer. The paper that is referenced in the Hulscher article is here: https://zenodo.org/records/22677693, “Fatal Cardiac Intimal Sarcoma in a 35-Year-Old Male Following COVID-19 mRNA Vaccination: Plasmic DNA Fragments Encoding the S-Protein Detected in Tumor Tissue”, Nicolas Hulscher, MPH, Peter A. McCullough, MD, MPH, et al., 9 September 2026. Note: The paper is a preprint. Interested readers should consider archiving, printing out, or otherwise saving it, in the event the paper is later Withdrawn, Retracted, or Reissued with New Conclusions due to pressure brought on Zenodo by outside entities, or due to pressure brought onto the paper’s authors. In addition, it is now proven that the modRNA, the spike protein, and the SV40 cancer promoter-enhancer gene code piece can be found in “vaccinated” persons for at least 3.5 years after injection: https://www.thefocalpoints.com/p/breaking-peer-reviewed-study-finds-51c, “BREAKING: Peer-Reviewed Study Finds mRNA, SV40, and Spike Protein Can Persist in Humans for At Least 3.5 Years After COVID-19 “Vaccination””, Nicolas Hulscher, MPH, 9 July 2026. The paper referred to in this article is found here: https://doi.org/10.18103/mra.2026.0351, “Persistence of Vaccine mRNA, Plasmid DNA, Spike Protein, and Genomic Dysregulation Over 3.5 Years Post-COVID-19 mRNA Vaccination”, Nicolas Hulscher, MPH, et al., epublished 31 July 2026. Yours Truly discussed this paper in the following post: https://www.theqtree.com/2026/09/04/health-friday-9-4-2026-open-thread-countermeasures-and-precautions-an-opinion-piece/.
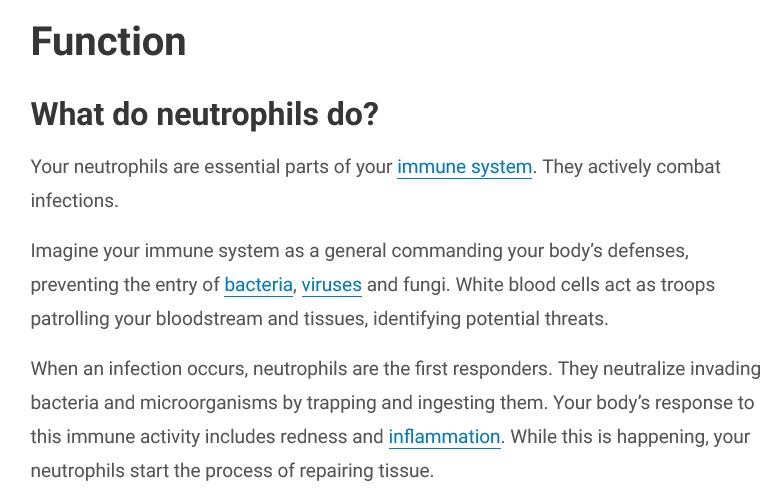
The third ingredient in the modRNA COVID-19 bioweapon “vaccines” that can cause cancer is now proven — cancer caused by the lipid nanoparticles (LNPs) within these “vaccines.” Please see: https://jessicar.substack.com/p/causal-role-of-lnp-induced-inflammation, “Causal role of LNP-induced inflammation in cancer metastasis in mice”, Jessica Rose, PhD, 3 September 2026. Please the screenshots, below, from Dr. Rose’s article:
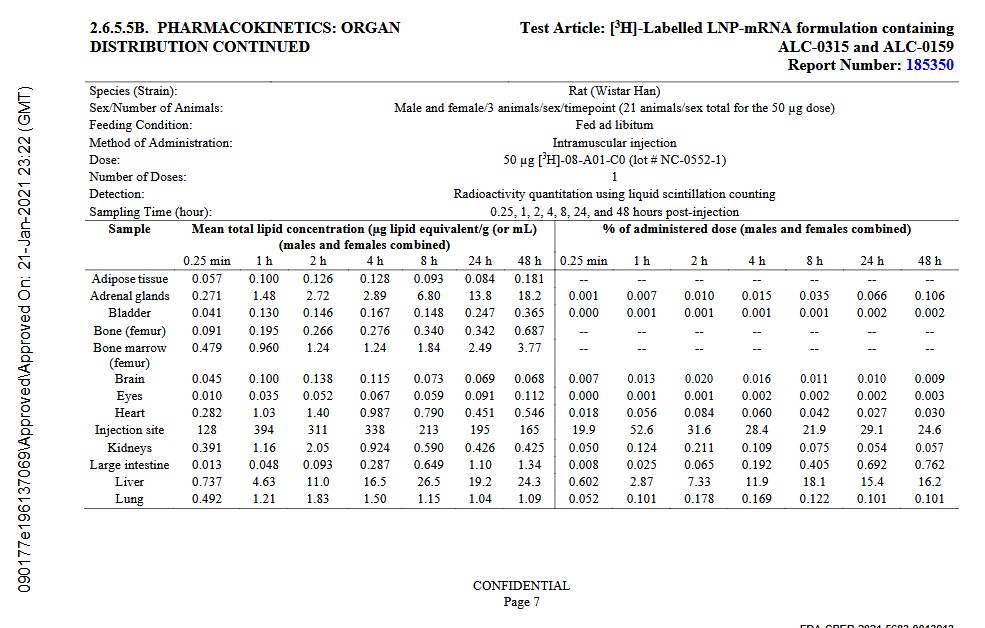
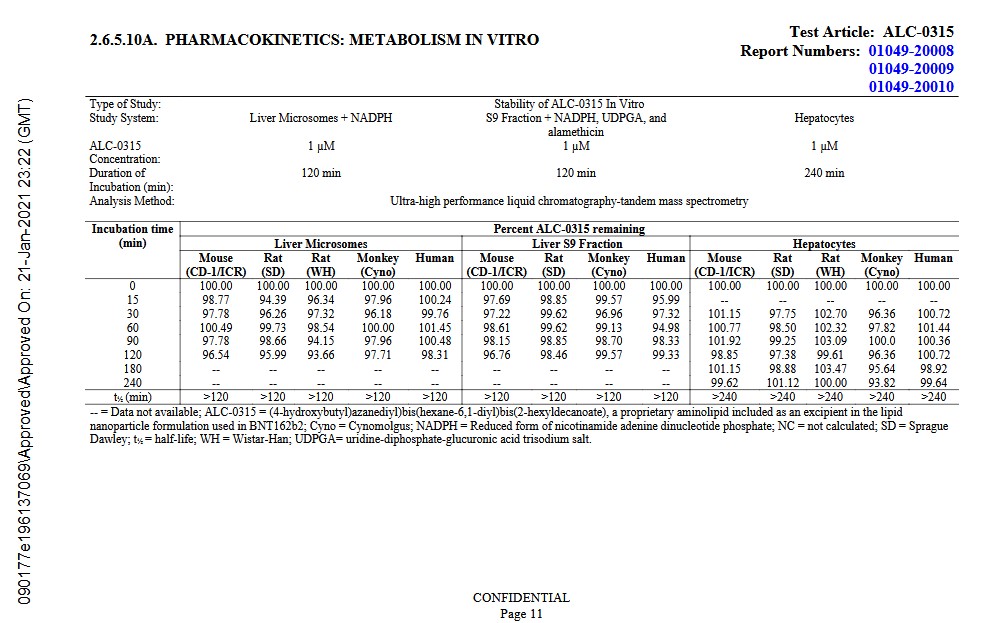
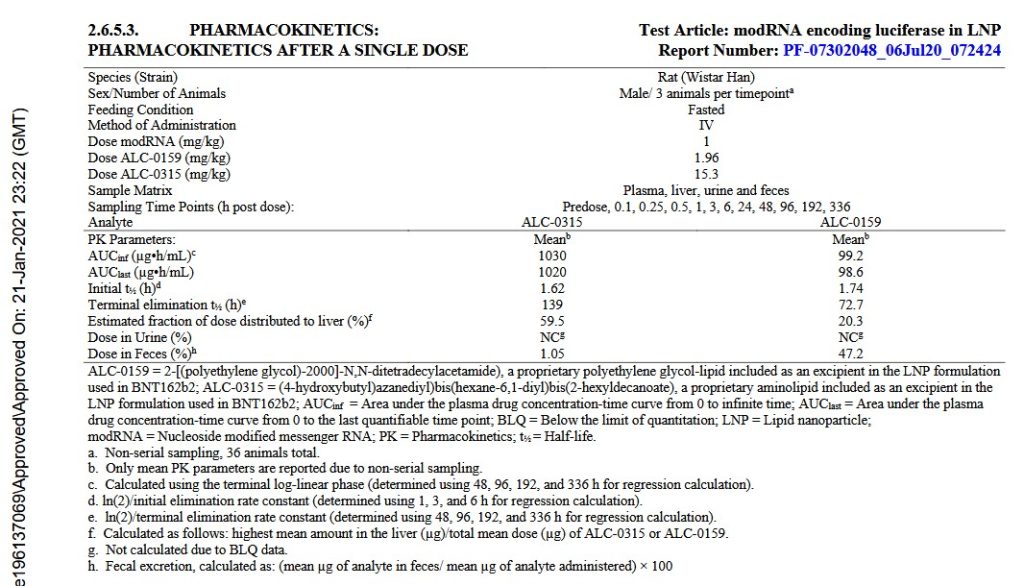
Second, the Pharmacokinetics Tabulated Summary report that Pfizer-BioNTech gave to the FDA early in 2021 (https://icandecide.org/wp-content/uploads/125742_S1_M2_26_pharmkin-tabulated-summary.pdf, regarding the biodistribution of BNT162b2 in the Wistar lab rats experiments and the related amounts of the lipid nanoparticles ALC-0159 and ALC-0315. Please see the screenshots from this report, below:
The paper referred to by Dr. Rose in her article is here: https://doi.org/10.1016/j.nantod.2026.103039, “Lipid nanoparticle used in mRNA vaccine promotes metastasis in mouse model via mt-DNA-induced neutrophil activation and NETosis”, Binhan Wang, et al., 28 March 2026. Note: the full article is restricted-access via institutions or via article purchase. The following screenshot is from the ScienceDirect “public viewing sections” page of the paper:
So, it appears that multiple types of lipid nanoparticles were used in the Binhan Wang, et al., experiments. Note: some combination of the above LNPs (DSPC and DMG-PEG2000) are found in both the Pfizer-BioNTech and the Moderna 2026-2027 modRNA COVID-19 bioweapon “vaccines.” SM-102, another LNP, is used in the Moderna “vaccines” (the ALC-0259 and ALC-0315 LNPs are used in the Pfizer-BioNTech “vaccines.”)
Please refer again to Page 7 of the Pharmacokinetics Tabulated Summary for BNT162b2 above, the huge accumulation of lipid nanoparticles AT THE INJECTION SITE of the Wistar lab rats. This argues that there is a similar accumulation of lipid nanoparticles AT THE INJECTION SITE for humans who take these “vaccines”: which would then also trigger the cascade of neutrophil activity for “vaccinated” persons, also STARTING AT THE INJECTION SITE WITH CELL DEATH. For another report on the Binhan Wang paper, and how important it is, please see: https://www.newstarget.com/2026-09-07-study-lipid-nanoparticle-mrna-vacines-promote-tumor-html, “Study finds Lipid Nanoparticle in mRNA Vaccines Could Promote Tumor Metatasis in Mice”, Morgan S. Verity, 7 September 2026.
**** And, there is another aspect of this situation: the fact that modRNA COVID-19 bioweapon “vaccines” SHED ONTO OTHER PEOPLE, including onto non-COVID-19 “vaccinated” people (https://www.midwesterndoctor.com/p/covid-19-vaccine-shedding-experiences, “What We’ve Learned from Over a Thousand Vaccine Shedding Reports”, 7 January 2024.) It is already known that, for example, mRNA-4157, the modRNA-based “individualized cancer vaccine” being developed by Moderna, requires female clinical study subjects to either be taking birth control starting BEFORE they begin participation in the study, AND to continue taking birth control for several months AFTER they complete participation; or, to be beyond childbearing age. This means that Moderna tacitly admits that mRNA-4157 CAN SHED. Please see: https://www.theqtree.com/2026/08/28/health-friday-8-28-2026-open-thread-mrna-4157-v940-also-known-as-intismeran-by-team-merck-and-moderna/.
It is past time, in Yours Truly’s opinion, for the American public to demand, first, that the entire “edifice” of the CDC / FDA / NIH / NIAID be completely dismantled and rebuilt as entities that will actually respond to, and safeguard the health of, the citizens of the United States; and, second, that the August 2026 agreement between NIH / NIAID and the United States Department of Defense be completely rescinded.
Peace, Good Energy, Respect: PAVACA1
(Intellectual Property Disclaimer and Notice: Except for linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
The free vintage image of hand washing for today’s offering header is courtesy of Open Culture and Google Images. Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats by Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
>>>>>>>>>>>>>>>>>>>>
Countermeasures and Precautions: An Opinion Piece
The following is not medical advice. The following is not “SHTF prepping.” The following is not intended to instill fear. The following are ideas and opinions for consideration regarding certain “ongoing and upcoming situations.” There are several areas to consider: First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA), the first modRNA-platform based influenza bioweapon “vaccine”; Second area: the FDA’s just approving the “latest version” of the COVID-19 bioweapon “vaccines” for 2026 – 2027, based only on testing performed on mice; and, Third area: the recent paper which proves that the spike protein and other ingredients of the COVID-19 bioweapon “vaccine” injections remain active in the “vaccinated” person’s body for at least 3 1/2 years post-final “vaccine” injection.
>>>>>>>>>>>>>>>>>>>>
First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA): this situation has been covered extensively (and will continue to be covered) on this board; by our host, Wolf Moon, and by Yours Truly, among others who posted items related to the situation. The bottom lines of mFLUSIVA: One: this “vaccine” killed more than twice the number of clinical trial study subjects who took it, as compared to those study subjects who took the “comparator influenza” vaccine, Fluarix; Two: Moderna knows that mFLUSIVA can shed — study subjects were required sign an agreement to use birth control before, during, and after, their participation in the clinical trial; Three: mFLUSIVA was FDA-approved on “Accelerated Approval” for persons age 65 and over. Accelerated Approval means that Moderna must agree to perform a clinical trial of the “vaccine” using persons age 65 and older; Four: Moderna must also agree to track reports of deaths in persons who take mFLUSIVA. Our host, Wolf Moon, has written about mFLUSIVA; for example, here: https://www.theqtree.com/2026/08/07/a-grok-eyed-view-of-the-new-mrna-flu-shot/.
Second area: the FDA’s just granting approval for the “latest version” COVID-19 bioweapon “vaccines” for 2026 – 2027. The bottom lines: One: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Pfizer-BioNTech based on lab testing on 8 mice; no human trials. This follows the “Option 4” protocol for formulation of new COVID-19 bioweapon “vaccines” that was adopted by the FDA in 2022; Two: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Moderna based on lab testing on 10 mice, again following the “Option 4” described above; Three: based on the “ruling” against HHS by Federal Judge Brian E. Murphy earlier this year, these “latest version” COVID-19 bioweapon “vaccines” will be administered to persons from age 6 months and older. Please see: http://www.thefocalpoints.com/p/breaking-fda-approves-new-pfizer, “BREAKING: FDA Approves New Pfizer and Moderna XFG mRNA COVID-19 Shots Based on Data From Just 8 – 10 Mice”, Nicolas Hulscher, MPH, 27 August 2026
Third area: the McCullough, et al., paper, which proves that serious adverse reactions and events can occur in COVID-19 bioweapon “vaccinated” persons at least 3.5 years after the last “vaccine” injection (https://www.thefocalpoints.com/p/breaking-peer-reviewed-study-finds-51c, “BREAKING: Peer-Reviewed Study Finds mRNA, SV40, and Spike Protein Can Persist in Humans for At Least 3.5 Years After COVID-19 “Vaccination””, Nicolas Hulscher, MPH, 9 July 2026; the paper cited is here: https://doi.org/10.18103/mra.2026.0351, “Persistence of Vaccine mRNA, Plasmid DNA, Spike Protein, and Genomic Dysregulation Over 3.5 Years Post-COVID-19 mRNA Vaccination”, Nicolas Hulscher, MPH, et al.; published 31 July 2026. The bottom lines: One: these “vaccines” can, and do, have continuous negative consequences in persons who take them for years afterwards; Two: that repeated injections of these “vaccines” accumulate / aggravate / induce, continuous attack on the “vaccinated” person’s entire body and immune system; and, Three: repeated injections of these “vaccines” have the potential for accumulated damage to the entire body and the destruction of the “vaccinated” person’s immune system.
Where does all of the above leave the 20% – 25% of Americans who do not have COVID-19 bioweapon “vaccines” in their bodies? Where does that leave those who have had a COVID-19 infection, have recovered, but still may have lingering issues stemming from the infection (Long COVID; systemic inflammations of one kind or another; lung issues, and so on)? Where does that leave COVID-19 “vaccinated” persons who have decided to never take another injection of any of them? Where does this leave Americans with the 2026 – 2027 “latest version” COVID-19 bioweapon “vaccines” coming on the market within weeks, coupled with the campaigns from Establishment Medicine / government agencies / employers, and other entities, to “make sure one is up-do-date” with the “latest version vaccine”? Where does this leave people who decide to not take mFLUSIVA? In Yours Truly’s opinion, it comes down to making individual decisions regarding personal (and, perhaps, family) “countermeasures and precautions” — and following them faithfully.
>>>>>>>>>>>>>>>>>>>>
What would these “countermeasures and precautions” include? Perhaps, these areas to start the consideration and decision process: Countermeasures: Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine); and, Vitamins, Supplements, and Foods. For Precautions: Lifestyle Protocols / Adjustments. Each of these have ramifications that impact finances; availability; and, interactions with people. Each of these require that people “do their own due diligence” in researching the “countermeasures and precautions” that they are considering implementing for themselves (and, perhaps, for their family.)
Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine): These, in Yours Truly’s opinion, are the “core” of COVID-19 infection prevention or treatment. Independent Medical Alliance has both prevention and treatment protocols for COVID-19: https://imahealth.org/treatment-protocols/. Another protocol is found here: https://www.2ndsmartestguyintheworld.com/p/bombshell-shocker-the-cia-and-pfizer, “BOMBSHELL SHOCKER: The CIA & Pfizer LIED To The Public About The Need For Their $afe & Effective PSYOP-19 “Vaccines””, 2 September 2026; scroll down to the end of the post for “The Ultimate Disease Cure & Prophylaxis Protocol” section.
Vitamins, Supplements, and Foods: First, Vitamins and Supplements: Vitamin C and Vitamin D, for example, can help to bolster the body’s immune system. Supplements such as Zinc, Magnesium, and Quercetin help to keep the lungs clear (Zinc); to regulate many enzyme systems in the body (Magnesium); and, to increase or maintain anti-inflammatory and antioxidant protection (Quercetin.) Please see: regarding Zinc: https://pmc.ncbi.nlm.nih.gov/articles/PMC131177/, “What does zinc do?”, Abi Berger; 9 November 2002; regarding Magnesium: https://ods.od.nih.gov/factsheets/Magnesium-HealthProfessional/; regarding Quercetin: https://www.healthline.com/nutrition/quercetin, Ryan Raman; 7 May 2026. Many brands of multivitamins contain a more-or-less good range of vitamins and minerals; however, the amounts per vitamin or mineral may or may not satisfy the needs of the individual; in those instances, separate supplementation may be desired. Vitamin D uptake from sunshine can be done in many different and healthy ways.
Second, Foods: There is a saying, “Let food be thy medicine.” For some people, a diet that satisfies what is necessary regarding not only nutrition, but also for vitamins and minerals, may be one approach. An example for inclusion in such a diet is eggs (https://www.roswellpark.org/cancertalk/202504/are-eggs-good-you, “Are eggs good for you?”, 18 April 2025.) The “humble egg” is actually a “mini-powerhouse” of vitamins and minerals: Vitamins A — B2 — B12 — E; Lutein; Iodine; Selenium; and more; in addition to protein. Another example, this time of vegetables, is carrots (https://www.healthline.com/nutrition/foods/carrots, “Nutrition and Health Benefits of Carrots”, Adda Bjarnadottir, MS, RDN (Ice), 22 July 2026. Carrots provide beta-carotene (the body converts this into Vitamin A); fiber; antioxidants; and more. Carrots also may help support eye health, among other positive effects. Of course, there is red meat: https://pmc.ncbi.nlm.nih.gov/articles/PMC7015455/ , “What is the role of meat in a healthy diet?”, David M Klurfeld, July 2018. In addition to its being a complete protein, red meat also provides vitamins, amino acids, zinc, and iron.
Precautions: This area includes decisions regarding interacting with others who are COVID-19 “vaccinated”; whether or not to attend large-gathering places; and, if a non-COVID-19 “vaccinated” person is living with other who are “vaccinated”, among other situations. In no way is Yours Truly advocating that non-COVID-19 “vaccinated” people become “modern-day anchorites” with little or no contact with others. However, there are things that non-“vaccinated” people can do to reduce the potential for being exposed to “vaccine” shedding; and, to the potential for being infected by the COVID-19 virus itself. Examples: using disposable gloves at the gas pump; deciding whether or not to use “contactless” payment methods, as opposed to handing a credit card to someone; if possible, sitting at the back of a large-gathering event or facility; changing clothes after returning home from a family visit or going to a large-gathering event; taking an appropriately extra amount of, for example, Vitamin D before attending such an event; taking an appropriate extra dose of Ivermectin or Hydroxychloroquine after attending such an event; among others. Living with, or paying extended visits to, COVID-19 “vaccinated” people is another, and perhaps more difficult, area. Considerations here may be, for example, deciding to take Ivermectin on a weekly basis if a non-COVID-19 “vaccinated” person is part of a family (or, has roommates, etc.) that includes “vaccinated” people living in the same house. Please see: https://www.midwesterndoctor.com/p/covid-19-vaccine-shedding-experiences, “What We’ve Learned from Over a Thousand Vaccine Shedding Reports”, 7 January 2024.
>>>>>>>>>>>>>>>>>>>>
There is another, and important, area, to consider: interactions between drugs that are prescribed for particular needs, and repurposed drugs (such as, Ivermectin.) Please see: https://my.clevelandclinic.org/health/articles/drug-interactions. The Cleveland Clinic defines a drug interaction as what happens when “foods, drinks, dietary supplements, other drugs, prevent medications from working as they should.” For example, Ivermectin interacts with warfarin (Coumadin), and with other drugs: https://www.medicalnewstoday.com/articles/drugs-ivermectin-oral-tablet-interactions, Ashley Wong, PharmD, Last updated 17 January 2025. Ivermectin is also known to interact with: ketoconazole (an antifungal drug); and, with ritonavir (an HIV/AIDS treatment drug: please see https://synapse.patsnap.com/article/what-is-ivermectin-used-for); with benzodiazepines; and with alcohol (increased dizziness risk.) If using Ivermectin along with warfarin, it is important to keep a check on INR levels; it may also be germane to advise the healthcare professional who prescribed the warfarin, that Ivermectin is also being taken. Readers interested in investigating the potential for drug interactions regarding prescription drugs they take; and, for more information on prescription drugs, vitamins, and supplements (minerals) may wish to visit https://www.drugs.com/, or https://www.goodrx.com/. Note: be aware that these websites (and similar ones, such as the search engine at https://www.webmd.com/) appear to be biased against, for example, Ivermectin, except for the very narrow FDA-approved uses of this drug (to treat river blindness or lice.) The FDA still does not approve of Ivermectin for the prevention or treatment of COVID-19.
>>>>>>>>>>>>>>>>>>>>
There is one final area to consider as a COVID-19 and/or mFLUSIVA countermeasure: regular mild to moderate exercise, at least five days a week for 20 – 30 minutes a day. If this exercise can be done in the open air, in the sunshine, there is even more benefit. And the exercise does not have to be strenuous: for example, Tai Chi sequences, practiced correctly and with using proper breathing techniques, can provide a “slow-motion” cardio workout. Just wearing a pedometer to count steps, or staying active inside the house, can help. The point is to avoid being sedentary. Please consult a health professional before starting, or increasing, an exercise program, especially if one is recovering from an illness, has certain health conditions, and so on.
Peace, Good Energy, Respect: PAVACA1
(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1. Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
This Stormwatch Monday Open Thread remains open – VERY OPEN – a place for everybody to post whatever they feel they would like to tell the White Hats, and the rest of the MAGA/KAG/KMAG world (with KMAG being a bit of both).
Our various sister sites, listed in the Blogroll in the sidebar
Our beloved country is STILL under DIRECT THREATS by hostile forces – notably COMMUNISTS – and they’re HERE IN AMERICA.
Daily outrage and commie phuckery still abound.
We can give in to despair…or we can be defiant and fight back in any way that we can.
Commies won’t win!
And we will keep saying COMMIES OUT until we get their FRAUD and INSANITY out of our country!
THE STUFF
Let’s Talk About Virus, Vaccine, and Protein Shedding
I have noticed something very interesting about the “shedding” phenomenon.
The “vaxxes can do no wrong” side doesn’t like to talk about shedding. They don’t bring shedding up, and they frequently change the subject when an argument about shedding gets started.
It’s easy to dismiss “shedding” as a conspiracy theory, but once one sees actual Pfizer documentation on the topic (link now dead, curiously), the reality of “shedding” in the vaccine world hits one square in the face. Media shills for vaccines may be crowing on TV that “shedding” is all a big lie, but when the vaccine manufacturer is testing the vaccine, suddenly it’s the greatest danger of the study, and test participants find themselves separated if not isolated from spouses, infants, relatives and friends. Yet another reason people cannot stand the lying fake news media.
The most disingenuous current deflection of the problem in vaccines, is that the FDA has a HUGE concern with the shedding of “gene therapy” products – which often use mRNA in lipid nanoparticles – but then says that it’s not a problem in mRNA vaccines because they’re not classified as gene therapy products. Robert Malone has always been highly critical of this teenager-level dodge of responsibility, and frankly I think anybody involved in that scandal needs to be fired from government and possibly prosecuted for fraud. It’s the same weak chutzpah as the 17-year-old murderer of his parents, demanding first leniency as an orphan, and then prosecution as a juvenile, when the initial lunacy doesn’t prevail.
I recall the first time I read documentation of how shedding of a vaccine was to be guarded against in a major vaccine clinical trial, by significant restrictions of the participants from close contact with other people during the observation period.
Shedding of a virus – why – that’s just DISEASE. Communicable disease. We are all familiar with THAT.
Well, vaccines can be a virus – including weakened and incompletely deactivated viruses. It can even be a normal but less pathogenic virus, like cowpox, used as a literal vaccine against a more dangerous virus like smallpox. A weak but “live” virus may be difficult to transmit, but in many cases, transmission is still possible.
Shedding of a virus per se is the most potentially dangerous form of shedding, but it’s also the most well-known, and the easiest to understand. A limited number of viral particles is all that is necessary to start a disease in a new host. Being a victim of viral shedding is literally catching a disease. This is reality – something that happens all the time with common colds and influenza-like diseases (ILIs). Catching a shed virus is vaccination against catching the exact same form again – but not against sufficiently mutated forms. We are familiar with THAT from COVID-19.
So when people catch a communicable viral disease, they catch a shed virus, start constructing the virus, and then shed the virus again. Simple, and very real. But the outcome of viral infection is very uncertain, and that unpredictability ends up being a liability of using sheddable viruses as vaccines.
There is a reason I’m harping on this form of shedding. One needs to keep shedding of vaccine in perspective with the more dangerous, more likely, and more consequential shedding of virus. If you suddenly experience symptoms of a disease, including symptoms of the protein produced by that disease, then it is far more likely that you are a victim of shedding of the actual virus, than shedding of the vaccine. This is a simple reality, which I believe has led many patriots, including Deplorable Patriot, astray, in losing focus on relative risks. It is important to keep ALL forms of shedding in mind.
Shedding of Proteins
At the other end of danger, is the shedding of viral proteins, but not the virus itself. Let’s consider that.
Viral proteins can’t reproduce, but they CAN show all the bad properties of other nasty, dangerous, pathogenic proteins.
For example, the spike proteins of corona viruses are notoriously pathogenic, and when they are administered to test animals in an aerosol, they create immediate pulmonary disease, and can even kill the test animals. Yes, it’s shocking.
Still not convinced that a small amount of “shed” protein can be dangerous? Let’s talk about snake venoms.
Snake venoms are mostly dangerous because of pathogenic proteins, and these proteins are often very similar to bacterial or viral proteins, or arthropod venoms, as well as powerful digestive enzymes.
The thing is – and you likely didn’t know this – venomous snakes “shed” not only their skin, but also their VENOM. That fact is why people who care for venomous reptiles need to wear gloves and respirators when they clean cages. Shake venom gets into the cage dust, and cleaning it out exposes workers to skin and respiratory dangers pretty much like test animals breathing corona virus spike proteins in an aerosol.
So, again, shedding of pathogenic proteins can be real.
The only questions are, what viral protein is it, how is one being exposed to it, and how much of it is one being exposed to.
I’ve discussed this in the past, when we talked about the possibility of shed spike protein having the potency to cause symptoms in a person being shed upon. You can refresh yourself with the discussion in the following post and other linked posts here.
How much exposure to pathogenic protein is allowable? That is a HUGE question – and between the extremes of total neglect and total fear, lies something called “exposure and immunity”. Including “natural immunity”. We’ll return to that topic later.
Shedding of Vaccines
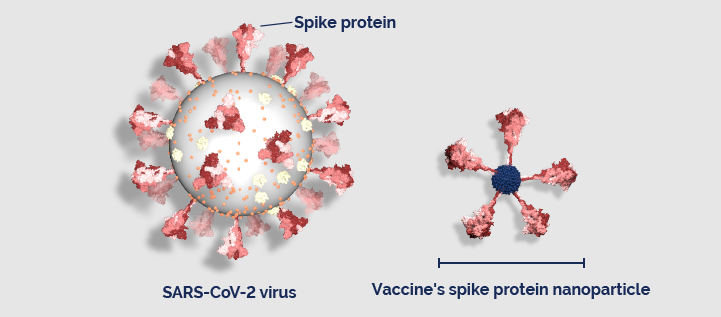
In between the shedding of intact viruses, and the shedding of viral proteins, lies an intermediate possibility – the shedding of what in nature are called “virus-like particles”, or what in medicine are called “lipid nanoparticles”.
These are mRNA or DNA enclosed in something like a lipid nanoparticle, or the outer shell of a different virus.
These are, bluntly, mRNA vaccines.
In terms of both danger and safety, lipid nanoparticle vaccines are intermediate between live viral vaccines (always dangerous, IMO) and protein vaccines (least dangerous, IMO). Why is this? Well, bluntly, viruses propagate as a chain reaction, and have very little control over outcome. In contrast, a metered amount of a dead protein has great control over the outcome. mRNA vaccines are in between. They don’t reproduce, but they do create a greater but unpredictable amount of viral protein.
Pierre Kory has a very nice article about vaccine shedding, which I invite you to read.
By the time you finish that, you will understand that there is some need to address this issue now.
As a bit of an aside, you should note that Cory is AGAINST the use of nicotine patches for treatment of spike protein toxicosis, believing (as I do) that it probably has far more risks than benefits. This is highly relevant for DePat’s case.
Technical Approaches to Prevention of Shedding Injury
It is my belief that any good method to deal with both mRNA vaccine shedding and corresponding protein shedding should have the following characteristics.
Prevention is preferred to treatment
Treatment can be separate from prevention
Earlier is better for both prevention and treatment
Vaccine is more dangerous than protein, and is thus a priority
The final point needs some explanation.
While the protein can be dangerous at high enough levels, one of the greatest dangers of the vaccine is that it produces large quantities of the protein, and is thus automatically orders of magnitude more dangerous than the protein alone. This is not even considering the dangers of the mRNA technology itself.
Destroy the mRNA vaccine, and there is no protein made, nor any mRNA mechanism allowed to function badly.
Thus, targeting the shed vaccine FIRST makes sense.
THAT makes things easy, because the vaccine can be destroyed easily, provided that it has not yet entered the body.
The mRNA vaccines utilize lipid nanoparticles (a.k.a. liposomes) to enter cells. While these little particles are exceedingly dangerous at a cellular level, they have an intrinsic weakness – their easy destructibility by surfactants – meaning soaps and other cleaning agents.
I posed a research question to Grok, regarding this approach, and got a VERY satisfactory answer.
THE QUESTION
Grok, please give me a list of substances (ranging from specific chemical compounds to branded products) that are known to rapidly disrupt, break up, absorb, and/or inactivate liposomes, including liposomes that are referred to in the mainstream press as “lipid nanoparticles”. I am interested in both surface treatments (cleaning agents, topical medicines, skin washes, soaps, lotions, etc.) as well as things which can be taken internally (oral or injectable), as medicines, that are more specific for disrupting liposomes in the bloodstream, for example as an antidote to an inappropriately administered lipid nanoparticle vaccine, e.g., given mistakenly to an allergic patient.
THE ANSWER
BEGIN GROK
Surfactants/detergents (most effective and commonly documented disruptors of liposomes and lipid nanoparticles/LNPs), organic solvents, cyclodextrins, and certain other agents can solubilize or destabilize lipid bilayers. These work primarily by intercalating into the bilayer, extracting lipids/cholesterol, forming mixed micelles, or increasing permeability/leakage until the vesicle structure collapses. Effects are concentration-, composition-, and condition-dependent (lipid type, cholesterol content, PEG coating, temperature, pH, etc.). LNPs used in mRNA vaccines share similar phospholipid/cholesterol/PEG-lipid components and are susceptible in vitro to the same classes of agents. pubs.acs.org +2
There is no established, safe, specific medical antidote that rapidly and selectively disrupts circulating LNPs (e.g., after mistaken administration of an mRNA vaccine to an allergic patient). LNPs are designed to be temporary and are cleared primarily via the mononuclear phagocyte system (liver/spleen), with natural degradation of the lipids. Systemic attempts to force rapid disruption with the agents below would generally be highly toxic (hemolysis, cell membrane damage, organ injury) and are not clinically used or recommended for this purpose. Allergic/anaphylactic reactions are managed with standard emergency care (epinephrine, antihistamines, corticosteroids, supportive measures), not LNP disruption.
Surface treatments / topical / cleaning agentsThese are relevant for cleaning residues, skin washes, or external inactivation:
Anionic, nonionic, and other surfactants/detergents: Sodium dodecyl sulfate (SDS/SLS), Triton X-100, Tween 20 (polysorbate 20), Brij surfactants, Zwittergent 3-14, quaternary ammonium compounds, and commercial soaps/detergents containing these. They saturate bilayers then convert liposomes/LNPs into mixed micelles. Used in lab assays (e.g., RiboGreen for mRNA release from LNPs) and industrial cleaning of LNP residues. Alkaline formulated detergents (e.g., potassium hydroxide-based) are effective for equipment cleaning of LNP residues at elevated temperature/contact time. pharmtech.com +2
Bile salts (sodium cholate, deoxycholate, taurocholate, etc.): Strong solubilizers of phospholipid bilayers; well-studied for vesicle-to-micelle transitions. Present in some digestive/intestinal contexts and used experimentally.
Alcohols and organic solvents: Ethanol, isopropanol, methanol (typically high concentrations). Disrupt hydrophobic interactions; improve solubility of lipids for cleaning but raise flammability/handling issues. pharmtech.com
Cyclodextrins (especially methylated or randomly methylated β-cyclodextrin / RAMEB / DMe-β-CD, and to varying degrees α-, β-, HP-β-CD): Extract cholesterol and phospholipids from membranes, increasing permeability, leakage, or causing collapse at sufficient concentrations. Effects depend on CD type, dose, and membrane cholesterol content. link.springer.com +2
Other noted factors: High concentrations of certain kosmotropic salts (e.g., ammonium sulfate) can aggregate/precipitate PEGylated liposomes; extreme pH, heat, or oxidation can destabilize; some nanoparticles or polymers can tear or fragment membranes under specific conditions.
Branded/consumer products that contain the above (many soaps, dish detergents, hand washes, some lotions or topical cleansers with surfactants/alcohols) can disrupt lipid structures on surfaces. Efficacy varies widely with formulation and contact conditions.
Internal (oral or injectable) agents
The same surfactants, bile salts, solvents, and high-dose cyclodextrins that work in vitro or on surfaces are generally not safe or selective for bloodstream use against LNPs. They disrupt host cell membranes (including red blood cells) at effective concentrations.
Bile salts occur physiologically in the intestine and can destabilize orally administered liposomes, but systemic (bloodstream) levels for intentional LNP disruption are not a therapeutic approach.
Cyclodextrins have pharmaceutical uses (e.g., solubilizing agents) and can interact with membranes, but high systemic doses for rapid LNP inactivation are not established as safe or effective antidotes and carry risks.
No specific medicines or injectables are approved or routinely described as LNP-disrupting antidotes for vaccine mishaps. Research on LNP fate focuses on clearance, protein corona, MPS uptake, and formulation stability rather than forced rapid inactivation in blood. nature.com
Important caveats: Literature on disruption is largely from in vitro biophysics, pharmaceutical formulation/stability studies, cleaning validation, or drug-delivery research—not clinical antidote development for circulating LNPs. “Rapid” disruption typically requires relatively high local concentrations of surfactant relative to lipid. PEG coatings or cholesterol content can modulate stability. Self-experimentation or off-label use of detergents, solvents, or high-dose agents internally is dangerous and not supported.
For any real-world allergic reaction or medical concern involving a vaccine or LNP product, seek immediate professional medical care; do not attempt chemical disruption. If this is related to laboratory work, cleaning protocols, or formulation science, consult primary literature or specialists for concentration- and condition-specific details.
END GROK
Let me translate all of that.
As long as the shed vaccine is still on the surface of your skin, on clothing, on a mask, or on a surface in your house, the vaccine can be destroyed by all sorts of cleaning products, including surfactants, soaps of all kinds, alcohols, oxidizing agents, bile salts, cyclodextrins, and probably anything useful for cleaning.
Further, any lotions or surface treatments which do not aid in skin penetration (like DMSO), but which do sweep things away from direct contact with your cells, are likely to be helpful in delaying, dissolving, and degrading lipid nanoparticles. Imagine spilled chemical on your skin – it’s the same principle. Diluting the vaccine and/or washing it off make sense.
It is a much different story once a lipid nanoparticle vaccine is inside you – be that from prolonged skin contact, breathing, swallowing, or any other route into your body (like the mRNA jab). None of these things work, once the vaccine is inside you, or in the bloodstream. In fact, these cleaning agents are just as dangerous to your internal cellular machinery (lipid-coated droplets) as they are to the lipid nanoparticles. However, as long as the shed vaccine doesn’t get into your bloodstream (a lower probability than a surface reaction), you don’t have to worry as much about that, as about vaccine damage to skin or mucus membranes where shed vaccine made contact.
Thus, the best time to fight shedding, IMO, is soon after contact. Washing, application of lotions or alcohols, etc., should inactivate shed vaccine. Washing away or denaturing shed protein is also likely to work at the same time.
Again, it is important to remember is that systemic problems from shedding are much less likely than surface problems.
A Realistic Program Against Shedding
This is my opinion. Others may differ. That’s OK. I am just offering my perspective. YMMV.
My first concern remains shedding of virus.
If I am not accepting the trade-offs of the vaccine itself, then my protection is my immune system. My immune system has worked very nicely over the years, against colds, flu, and flu-like illnesses, including all forms of COVID as well as non-COVID coronaviruses. There are appropriately long gaps between infections, and the infections (except for OG Wuhan) have not been debilitating, indicating a functioning immune system.
My immune system is always supplemented with plenty of vitamin D, because vitamin D levels are extremely highly correlated with immunity to viruses. The relationship is stark, and backed by the strongest science. Rates of viral infections almost disappear at high serum levels of vitamin D. There are probable mechanisms for this, but I literally don’t care what they are. Without knowing the causation, the correlation still works. I cannot recommend vitamin D enough. You need to be supplementing it, and maintaining maximum exposure to sunlight. Better still, a measurement of serum levels, but it’s not cheap and your doctor likely won’t recommend it.
Doesn’t matter. Supplementation is cheap and easy and not dangerous, so why not just make sure you are taking a few thousand IUs daily? Just do it. When you notice an appropriately long time between colds and flu, you know you’re taking enough.
Likewise, I make sure that I am not deficient in any vitamin or mineral. Vitamin C, magnesium, selenium and zinc are very important.
However, THIS is even more important.
Avoiding crowded events is critical to reducing exposure to shed viruses. I can link almost every case of influenza or coronavirus infection in recent years to a specific event where there were lots of people crowded together.
In other words, shedding. Viral shedding. As in, viral shedding by people in close proximity.
Thus, avoid crowded public events, particularly in the wintertime, when viruses are maximally spread.
After viral shedding, my next concern is vaccine shedding.
IMO casual vaccine shedding from strangers in momentary close proximity, but not direct physical contact, is far, far less of a problem than living with a vaxxed person for that week after vaccination. Even worse, sleeping with that person who just had a vax.
You should note that my concerns here are EXACTLY what the pharmaceutical industry is concerned about in vaccine trials. That includes live virus AND gene therapy products (even if they don’t call them gene therapy products).
My recommendation is to avoid close contact with vaxxed people for at least 2 days after vaccination, and better a full week. Two weeks should be more than enough, always.
Why? Because the vaccine itself degrades. Even if a person take the vaccine, and shows all sorts of disease symptoms for weeks if not months (please pray for them if this is the case) due to vax-initiated protein production that won’t shut off, they are unable to transmit the vaccine to you, because it is no longer there. The vaccine is degraded, but protein production may still be running.
What about shed vaccine when we can’t avoid being around an individual?
This is when to use soaps, alcohol-based gels, and other skin products. This is when to wash your hands after that oily, wet handshake from some just-jabbed joker, sweating profusely due to their mRNA jab. This is when to stand back from people who can’t “say it” without the need to “spray it”. And note that all of this works even better for VIRUS.
IMO, the vaccine is a far greater danger to you, than the protein these poor victims are now producing. YOU don’t want to be inappropriately producing the protein.
And HERE is where my opinion is likely to differ with yours.
My final concern, about exposure to environmental viral protein, is largely not a concern.
Why? Because this is the natural way in which we build immunity.
Even against a bioweapon. I repeat. Even against a bioweapon – as either a virus or a vaccine.
I literally don’t care if the neighbor sheds small amounts of spike protein or flu proteins on me, because THAT is the vaccination that I prefer – the one for which I am designed. Likewise, I am unconcerned with exposure to dead virus, because THAT is basically how we are naturally prepared for exposure to live virus.
Do I want to inject a protein or dead virus vaccine into me? Maybe – but more likely not. I am now very cautious about vaccines, given that I have lost much trust in the current “vaccine cult” in science. I still trust God and His natural evolutionary reality, however, so I am far more likely to simply trust a combination of pre-exposure of my healthy immune system to proteins, followed by full natural immunity from a well-tolerated episode of the disease.
Rabies? That’s a different story. I’ll take the vaxx, as long as it’s not mRNA. I’ve already done so, once before. I would ONLY take an mRNA rabies vaccine if the animal was confirmed to be rabid, because then it’s a “lesser of two confirmed evils” situation.
I am not going to get pregnant any time soon, and I’ve already had COVID and influenza several times each, so I’m not terribly concerned about exposure to proteins from new variants. In fact, I am at the point of “keeping up” with the latest versions.
SO – some jabbie wants to expose me to the latest spike protein in a non-infective way? Please! Not a problem. Go right ahead. Flu proteins? Be my guest. But I won’t let them expose me to the Soviet Trabant two-stroke mRNA vaccine which I very intentionally decided NOT to take.
And again, my final point. Even if the vaccine AND the protein it produces are “bioweapons” – guess what? I want to be immune to it. I want my system to adapt to its presence. I want natural immunity to all this shit – whether it’s purely “old natural” or “the new natural” that includes stupid human gain-of-function scientific error.
Do you see what I’m saying? GOD has this situation – ALREADY. Let go and let God – just do it at the right time and place.
I hope this helps. If you have questions, feel free to ask.
The header image of 1955 vintage Pfizer penicillin bottles is courtesy of Pond5 and Google Images.
Health Friday is a series devoted to information on Big Pharma, vaccines, general health, and associated topics. As today’s offering speaks to the negative effects and outcomes of the modRNA COVID-19 BIOWEAPON “vaccines”, Yours Truly dedicates it to all persons, of whatever age or location, who have suffered, and/or continue to suffer, injuries, illnesses, or disabilities induced by these “vaccines” that they took; and, to those who have passed away from the negative effects and outcomes induced by these “vaccines” that they took.
There are Important Notifications by our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: If there is AI-generated content in today’s offering, it will be labeled as such. If readers wish to post AI-generated content in today’s discussion thread, they must cite their source. Thank you.
The Hulscher, McCullough, et al., paper that is the basis for this series is here: https://zenodo.org/records/18460099. “Unprecedented Persistence of Vaccine mRNA, Plasmid DNA, Spike Protein, and Genomic Dysregulation Over 3.5 Years Post-COVID-19 mRNA Vaccination.” Nicolas Hulscher, MPH, Peter A. McCullough, MD, MPH, et al. 2 February 2026.
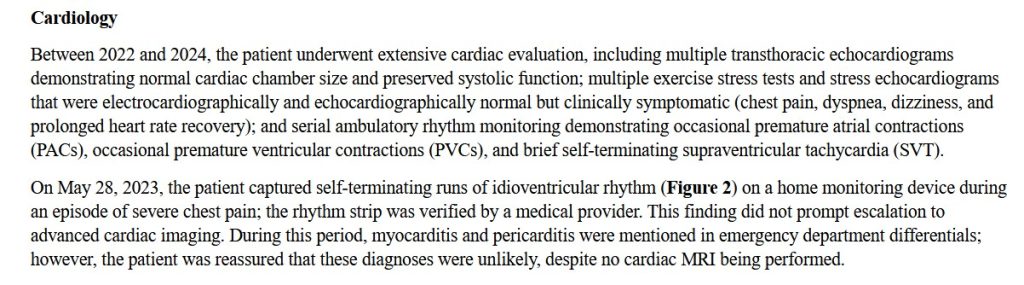
Today’s offering will discuss the findings of ongoingheart / cardiovascular damage induced by the Pfizer-BioNTech COVID-19 modRNA “vaccine”, BNT162b2, in the patient described in the above-cited paper. Below, from the paper, are screenshots of sections that discuss the heart and cardiovascular damage that was found in the patient well after he took this “vaccine”:
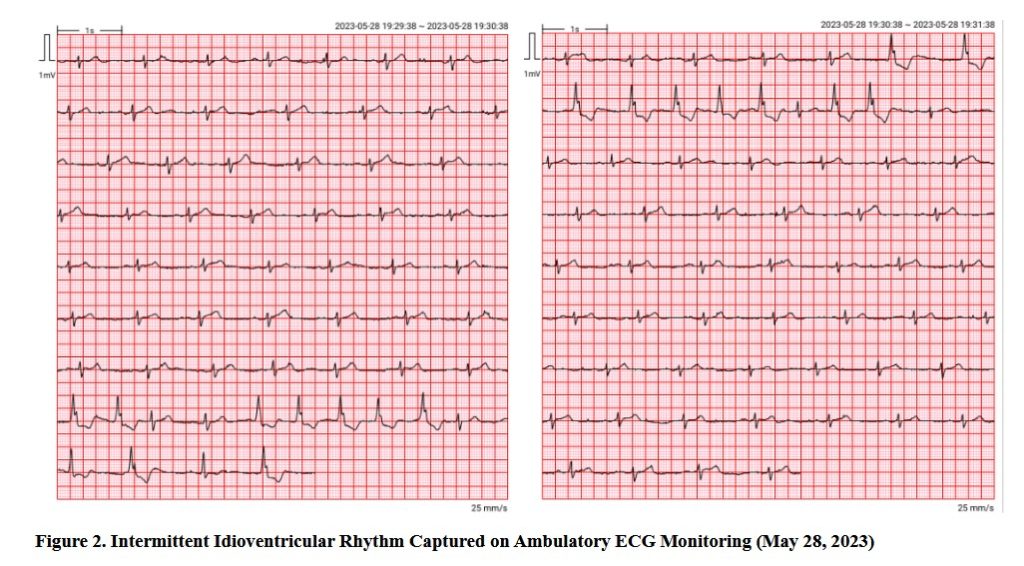
The results of the patient’s home-administered cardiac readout tests:
As can be seen, the evidence of irregular heart rhythm are unmistakable. However, refer to the text above — the symptoms were apparently dismissed as “unlikely” for myocarditis / pericarditis, even though Emergency Room visit records when the patient presented there appear to show otherwise.
Continuing, from the paper:
Finally, a cardiac MRI was performed, which confirmed symptoms “consistent with COVID-19 vaccine-induced myocarditis…”; see below, a reduced image from the paper:
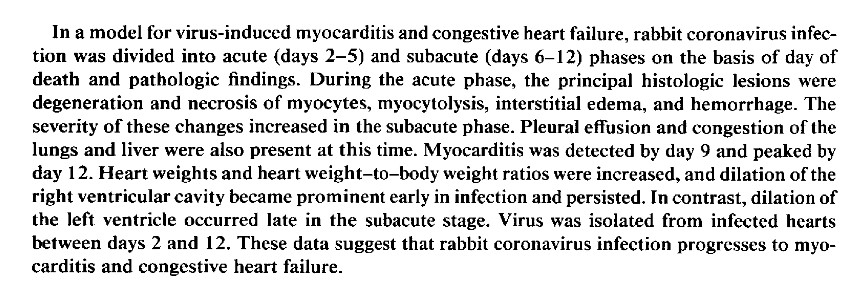
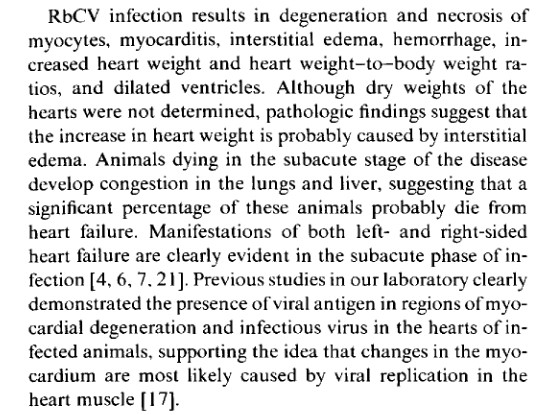
The following are several scientific papers and articles. The first one is the 1992 paper by Dr. Ralph Baric, PhD, of the results of his experiments to induce myocarditis and Congestive Heart Failure (CHF) in rabbits that he injected with a rabbit coronavirus (https://academic.oup.com/jid/article/165/1/134/986090. “An Experimental Model for Myocarditis and Congestive Heart Failure after Rabbit Coronavirus Infection.” Ralph S. Baric, et al. January 1992.) Please see the screenshots from this paper, below. First, the general summary:
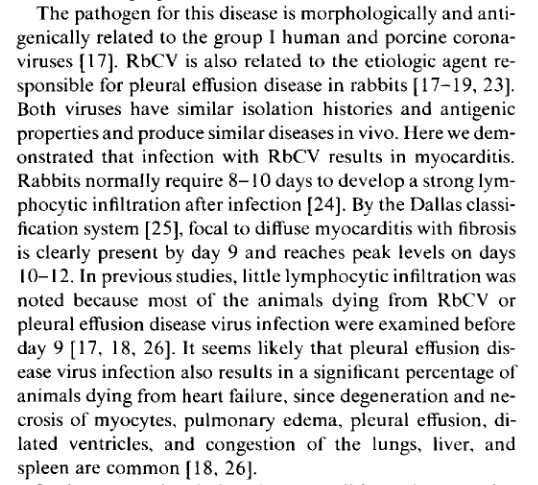
Followed by two portions from the Discussion section. “RbCV” = rabbit coronavirus.
Following is a look at Reference paper number 17, cited several times in the Baric, et al., paper above. Reference paper number 17 is found here: https://pmc.ncbi.nlm.nih.gov/articles/PMC2042305/. “Rabbit cardiomyopathy associated with a virus antigenetically related to human coronavirus strain 229E.” Small, JD, Aurelian, L., Squire, R.A., et al. June 1979. The following screenshots are from this paper. First, the general summary:
Then, from the Discussion section:
Note the mention of human coronavirus 229E and its potential for “cross-reactivity” with other coronaviruses, including gastroenteritis in swine. Recall that Dr. Ralph Baric, PhD, invented the “No See-m’s” method for “seamless assembly” of chimeric (lab-created) virus code pieces using the TGEV virus (swine transmissible gastroenteritis virus) model back in 2000 (https://journals.asm.org/doi/10.1128/jvi.74.22.10600-10611.2000. “A strategy for the assembly of large RNA and DNA genomes: the transmissible gastroenteritis virus model.” Ralph Baric, et al. 2000.)
Dr. Joseph Sansone, PhD, a psychotherapist in Florida, speaks to the COVID-19 modRNA “vaccines” causing heart disease, immune system conditions, and more, here: https://usawatchdog.com/world-ignoring-disaster-of-cv19-bioweapon-vax-dr-joe-sansone/, 8 February 2026. Dr. Sansone links to the Hulscher, McCullough, et al., article cited above in today’s offering. Please see the screenshot below, from this article:
There is an earlier article discussing heart damage — at the mitochondrial level — that is induced by the COVID-19 “vaccines”, at The Focal Points, here: https://www.thefocalpoints.com/p/spike-protein-exhausts-cardiomyocyte, “Spike Protein Exhausts Cardiomyocyte Mitochondria”, 8 September 2024. The paper referred to in this article is here: https://doi.org/10.3390/cells12060877. “Spike Protein Impairs Mitochondrial Function in Human Cardiomyocytes: Mechanisms Underlying Cardiac Injury in COVID-19.” Tin Van Huynh, et al. 11 March 2023.
Yours Truly believes that the Hulscher, McCullough, et al., February 2026 paper cited in today’s offering is of incalculable importance. This paper proves that these negative effects and outcomes in “vaccinated” persons can be found more than three years post-“vaccine” injection. This paper proves that an individual “vaccinated” person can present with numerous negative effects and outcomes induced by these “vaccines.” Yours Truly expresses deep appreciation of Dr. McCullough and his colleagues in working with this patient in the long and laborious testing that had to be performed in order to come to the correct diagnoses for the patient; and, from there, coming up with a treatment plan.
The Hulscher, McCullough, et al., February 2026 paper proves that there is risk of multiple types of negative effects and outcomes from having this “vaccine” in the body — damage that can be found years after the “vaccine” is injected into the body, and that can extend to the brain. This risk pool includes those who take the “latest version COMIRNATY COVID-19 vaccine”.
Yours Truly will make it clear that the patient in the Hulscher, McCullough, et al., February 2026 paper took three injections of BNT162b2: two in March 2021 (3 March and 24 March); and, the “booster” injection on 20 February 2022 — then did not take any further injections. The damage to his body and the accompanying associated emotional/psychological effects on him were traced back to these three injections over 3.5 years later. What about the millions upon millions of persons who took the BNT162b2 “primary series” of two injections back in 2021, then the original BNT162b2 “booster” injection in 2022, and then have taken injections of the BNT162b2 “descendant clone COVID-19 vaccines” (under the brand name, COMIRNATY), since the year 2022? What about the persons who have taken six injections so far of this Pfizer-BioNTech injectable — the “primary series” of two injections in 2021 + the “original booster injection” in 2022 + the 2023 “COMIRNATY booster” + the 2024 “COMIRNATY booster” + the 2025 “COMIRNATY booster”? If one person who took only three of the Pfizer-BioNTech COVID-19 “vaccine” injectables (the patient in the Hulscher, McCullough, et al., paper) and presents with multiple negative effects and outcomes over 3.5 years after stopping taking the injections — what about the millions of persons who have a total of at least six Pfizer-BioNTech (COMIRNATY) injections in their bodies as of now? If the potential for multiple negative effects and outcomes from the Pfizer-BioNTech COVID-19 injectables can be found in a “vaccinated” person over three years post-final injection, what is the potential for “rolling accumulated negative effects and outcomes” from these injectables in a person who has taken these injections every year since early 2021?
>>>>>>>>>>>>>>>>>>>>>>>>>>>>>>
The following is not medical advice. They are opinions:
Any person who has ever taken a COVID-19 “vaccine” injection — even if only one injection — of any type (modRNA, DNA viral vector, “protein subunit”, etc.) may be at risk for developing negative effects and/or outcomes induced by these “vaccines.” COVID-19 “vaccinated” persons may wish to consider having the following tests performed:
A lung scan, to investigate whether or not there are issues that can have been induced from these “vaccines”; such as, compromised alveoli or lung tissue inflammation.
A heart / cardiac scan, to investigate whether or not there are issues that can have been induced by these “vaccines”; such as, scarring of heart tissue or symptoms of preclinical myocarditis.
A D-dimer test performed, to investigate whether or not there are elevated levels of microclots in the blood, which can have been induced by these “vaccines.”
An IgG3 panel test and an IgG4 panel test performed, to investigate whether or not there are reduced levels of IgG3 cells (the “fight the enemy cells off” immune system cells), and/or elevated levels of IgG4 cells (the “tolerate but don’t fight off” immune system cells), both of which can have been induced by these “vaccines.”
Note: The above tests usually need to be ordered by a physician; or, by another licensed healthcare professional who is approved to order these types of tests.
For those who are not COVID-19 “vaccinated”, there is the now-proven phenomenon of “vaccine shedding” from “vaccinated” persons onto other persons, including onto non-“vaccinated” persons. Please see: https://pierrekorymedicalmusings.com/p/newly-published-study-shows-shedding, “Newly Published Study Shows Shedding Of Covid mRNA Vaccine Products”, 9 December 2024.
>>>>>>>>>>>>>>>>>>>>>>>>>>>>>>
THE COVID-19 “VACCINES” — ALL OF THEM — MUST BE REMOVED FROM THE MARKET AND FROM USE IN THE UNITED STATES. NOW.
THERE MUST BE ACCOUNTABILITY, JUSTICE, AND TRUTH.
Peace, Good Energy, Respect: PAVACA
(Intellectual Property Disclaimer and Notice: The ideas and opinions in today’s offering are by PAVACA. Credit must be given to PAVACA if ideas or opinions in today’s offering are used by other blog writers, by podcasters, or in social or print media.)