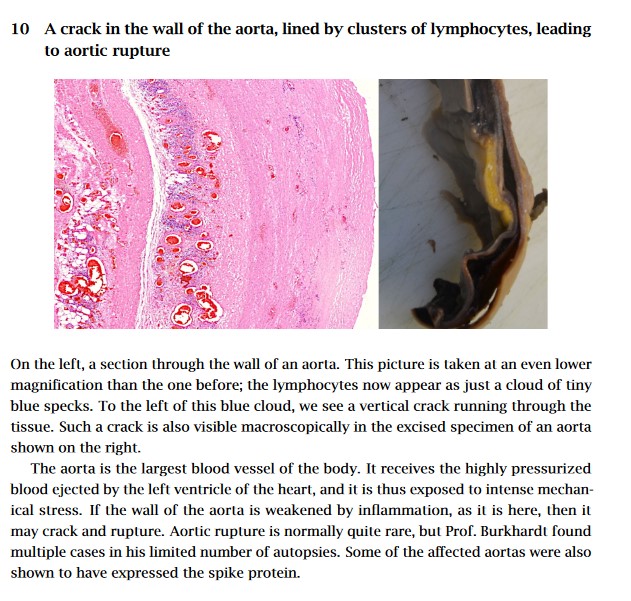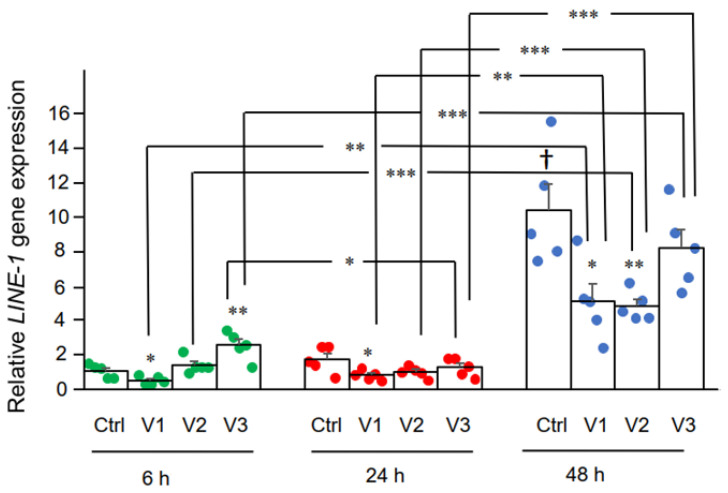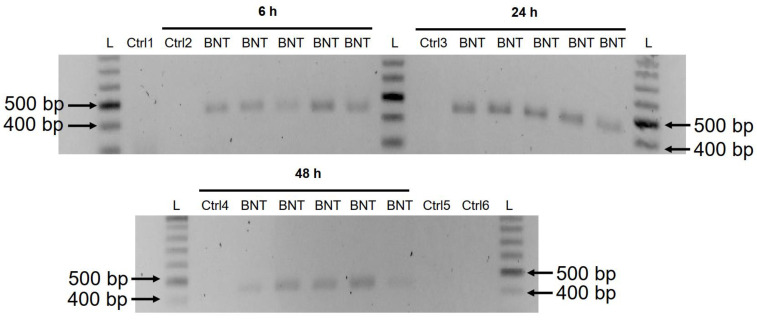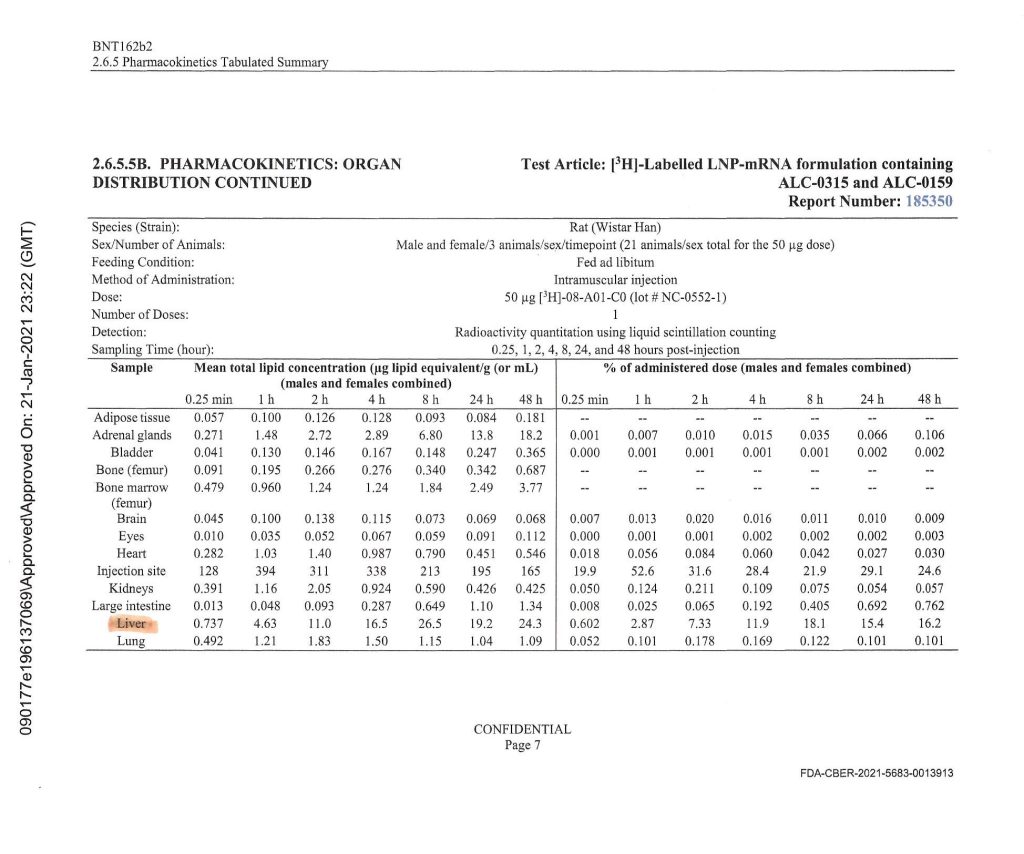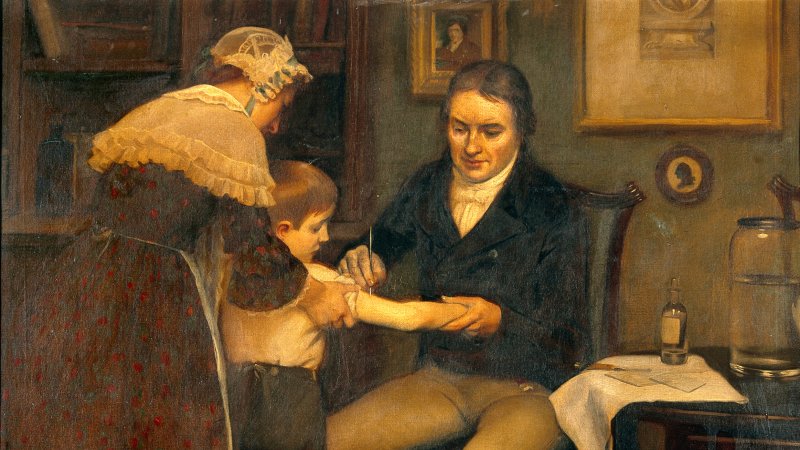
Health Friday Open Thread 9.20.2024: Double-Expose’ Edition

The above is a vintage image of Dr. Edward Jenner administering the first smallpox vaccination (inoculation) to James Phipps, 14 May 1796. Courtesy of www.sciencemuseum.org.uk/.

Today’s post, as it relates to the disaster of COVID-19 and the COVID-19 “vaccines”, is dedicated by Yours Truly in memory of her cousin Bill, who died “suddenly and unexpectedly” in September 2023. However, the discussion is not limited to what is presented here: it is an Open Thread.

There are two separate, although connected (Big Pharma), parts to today’s offering. Each part is of itself an expose’. This post is a long one, but important. Please, take a cup of coffee or tea; or, if it’s an appropriate time of the day, perhaps a “wee dram” of something like chilled D.O.M. Benedictine with a twist of lemon peel, and settle in for reading.

Readers already know the caveats regarding civil discussion on this board; of the alternate sites in case the main board is not accessible (here and here); and, that what Yours Truly presents on Health Friday is not medical advice, but opinions and/or hypotheses from ongoing research on COVID-19, Big Pharma, and other health topics.

“Quick, down-and-dirty summary” of today’s post:

One: Pfizer-BioNTech has begun a new enterprise, PfrizerForAllTM, which apparently seeks to completely circumvent / marginalize, in-person consumer contact with pharmacies; to “funnel” in-person consumer contact with healthcare practitioners to “Pfizer-affiliated” professionals; and, to “redirect” the dissemination of information about the COVID-19 “vaccines” to that provided by Pfizer-BioNTech.

Two: That the FDA approval of the very dangerous and deadly Smallpox “vaccine”, ACAM2000, for use also as a “prevention” for Mpox, is the result of a complex mixture of Big Pharma influence + FDA review of the Biologics License Applicaion for this use of ACAM2000 that is, in Yours Truly’s opinion, “a foregone conclusion despite serious reservations”, to say the least + Gain-of-Function experiments on the Mpox virus. There is also a potential tie-in to “an expanded biodefense role.”

Yours Truly has tried to avoid making today’s post read like a scientific paper; however, there is a lot of information that is relevant to each Expose’. Note: Mpox is now the “official” name for monkeypox.

Expose’ One: It appears that Pfizer-BioNTech is creating new ways to increase the company’s consumer operations (and, therefore, potential profit lines.) Pfizer-BioNTech has just launched PfizerForAllTM — a direct sell-to-consumer business that will provide online access to healthcare providers (online [virtual], or affiliated healthcare providers encounters [for example, to get a COVID-19 “vaccination”]); plus, “delivered to your door” prescription drugs and “easier access” to other company products, such as their COVID-19 “test kits.”

The story begins here: https://sashalatypova.substack.com/p/pfizers-vaccine-business-is-so-pfucked, 7 September 2024. From the blog article, below:

Pfizer-BioNTech filed a Trademark Application in May 2024 for this new PfizerForAllTM program https://endpts.com/pfizer-submits-trademark-application-that-suggests-it-could-be-launching-a-direct-to-patient-program/, 13 May 2024, by Nicole De Feudis. (One must be a subscriber in order to read the entire article.) It appears that the application was approved: the company officially launched the program on 27 August 2024 (from the article on www.businesswire.com/, Pfizer Launches PfizerForAllTM, a Digital Platform that Helps Simplify Access to Healthcare (www.pfizerforall.com/.) From the article:

In other words, in Yours Truly’s opinion, Pfizer-BioNTech, not happy with the company’s portfolio loss due to falling consumer acceptance of the modRNA COVID-19 “vaccines” offered, and due to the failure of the company’s clinical trial of its “combo” modRNA COVID-19 “vaccine” + influenza “vaccine”, a corporate decision was made to find a way to go straight to the consumer and make it “so easy” to get access to the “vaccines”, plus other Pfizer products. Translation: banish “vaccine” hesitancy / “vaccine” refusal, by doing what may be called “straight to the consumer medical psy-op.” Again, from the Latypova article:

Dr. Peter McCullough’s take on the Pfizer-BioNTech move is here: https://petermcculloughmd.substack.com/p/pfizer-launches-pfizerforall, 14 September 2024. Below is a portion of his article:

The lawsuit that Pfizer-BioNTech settled in 2009 was over the use of the company’s drug, Bextra, in “off-label” situations. The scope of the settlement is described here: www.justice.gov/, “Justice Department Announces Largest Health Care Fraud Settlement in Its History”, 1 November 2023. A portion of the announcement is below:

This lawsuit was the starting point for FDA changes to its “regulations” regarding the use of prescription drugs in “off-label” situations. The latest FDA changes are summarized here: www.sidley.com/en/insights/newsupdates/2023/11/fda-s-latest-off-label-guidance, 1 November 2023. It appears, in a nutshell, that drug manufacturers can be held responsible (liable) for “off-label” use of their products, even if they already comply with the “new” FDA “regulations.” (Think of this in light of the use of, for example, Ivermectin or Hydroxychloroquine to prevent or to treat COVID-19 — these uses, arguably, are “off-label” for these drugs.)

By the way, PfizerForAllTM is working with UpScript Health and Alto Pharmacy regarding access to healthcare services and filling prescriptions. Guess what? UpScript Health lists Pfizer as a “partner” on the company’s “About” page of their website: www.upscripthealth.com/about/. And, there’s more — Alto Pharmacy, the online prescription drug company, has a couple of interesting members on their Board of Advisors: Alex Azar (HHS head under then-President Trump); and, Dr. Ezekiel Emanuel (he who helped to write the “ObamaCare” bill; he who advocated for people to take their own lives at age 75 “to make room for the younger generation”, and more): www.alto.com/our-company. Dr. Emanuel is also involved with the Center for American Progress (Soros-connected: www.americanprogress.org/c3-our-supporters/); The Aspen Institute; and, he is Co-Director of the Healthcare Transformation Institute (HTI) at the University of Pennsylvania. Below is the Mission statement of HTI (https://hti.upenn.edu/mission/):

Note 1: the “objective” to transform the behavior of physicians and other healthcare providers. (Italics, mine.) Note 2: the “imagifashion” hyperlink, apparently, after getting past the “fake Latin language” on the main page, takes one to a clothing/accessories company in California: https://nilah.la-studioweb.com/contact-us/. (??)

Regarding Alto Pharmacy, please see here: www.fiercehealthcare.com/health-tech/track-soon-hit-1b-revenue-alto-pharmacy-tapped-amazon-exec-its-next-phase-growth, 17 August 2022. Here’s what one needs to know about the “mission” of Jamie Karraker and Matt Gemache-Asselin, the company’s co-founders:

This statement really frosts Yours Truly. My late father was a Registered Pharmacist for 57 years, who: kept his pharmacy very clean and neat (one was part of the crew that swept the floors and cleaned the display shelves starting when she was 10 years old); made it a point to know about all of his patients and to TALK with with then they came to have prescriptions filled or refilled; worked out deals with his suppliers to get extra samples of OTC products to give to his patients who had lost their steel mill jobs when the mills left Pittsburgh in the late 1970s-early 1980s, and, who paid for their prescriptions with his own money at times, etc., — finds the language, “…brick-and-mortar terrible experience…” in the above statement not only to be personally insulting to the memory of her father: but, also, degrading to those “brick-and-mortar” pharmacists who do their job to keep their stores clean and organized.

Expose’ Two: This regards the FDA just “approving” the “expanded use” of the dangerous and deadly Smallpox “vaccine”, ACAM2000, for the “prevention” of Monkeypox (now called “Mpox.”) The FDA issued this “approval” on 29 August 2024. The trail on this begins here: https://mole.substack.com/p/acam2000-package-insert-warning-death, 14 September 2024.

To gain more understanding of Smallpox and inoculation / vaccination against Smallpox, please see: www.sciencemuseum.org.uk/objects-and-stories/medicine/smallpox-and-story-vaccination. Both Smallpox (variola) and Mpox (mpox virus) are members of the genus Orthopoxvirus. Whereas, a disease condition that would equate to Smallpox goes at least as far back as to China around 3000BC, Mpox was first discovered in 1958 (all, per Wikipedia search.) Dr. Edward Jenner, an English physician, noticed that milkmaids were immune from Smallpox infection; he deduced that the Cowpox infections that they sustained had made them immune to the other type of infection. Dr. Jenner administered the first “inoculation” of Cowpox virus (to prevent Smallpox) to a child, James Phipps, on 14 May 1796. Another source of information is here: wwwnc.cdc.gov/travel/yellowbook/2024/infections-diseases/smallpox-and-other-orthopoxvirus-associated-infections. Further details are found here, in the article, Edward Jenner and the history of smallpox and vaccination, January 2005. A screenshot of a portion of this article is below:

About ACAM2000: it is manufactured by Emergent BioSolutions, headquartered in Gaithersburg, MD. The FDA approved ACAM2000 for use for the prevention of Smallpox in August, 2007. It contains vaccinia, a live virus ingredient used in modern Smallpox vaccines. The vaccinia used in ACAM2000 is a replicating version. The vaccine is cultured in a mixture of African Green Monkey kidney cells (sound familiar? — as in, perhaps, SV40 African Green Monkey cancer promoter gene splice that was found in the Pfizer-BioNTech modRNA COVID-19 “vaccine” by Dr. Kevin McKernan?). ACAM2000 was originally only intended for use to prevent Smallpox — until its use was “suddenly expanded” on 29 August 2024 by the FDA to include prevention of Mpox (more on that later in the post.) Since then, articles such as this one have appeared (https://childrenshealthdefense.org/defender/fda-acam2000-mpox-vaccine-warning-death-unvaccinated/, 17 September 2024, by Suzanne Burdick, Ph.D.; and, social media has been posting items like this one: https://x.com/toastontheside/status/1835921932841062412. This tweet references the FDA-issued handout for patients and/or caregivers regarding ACAM2000. The FDA handout is found here: www.fda.gov/media/75800/download. FDA handout documents for patients and/or caregivers are likely to have, in Yours Truly’s opinion, “sanitized” information and “pablum-like” assurances regarding the “safety and efficacy” of the drug or injectable. The FDA handout for ACAM2000, however, is different: when one reads the handout, one gets a distinct impression that this “vaccine” is highly dangerous. Below is a screenshot portion of the FDA patient/caregiver handout for ACAM2000:

Note that there is NO MENTION of the other FDA-approved Mpox vaccine, JYNNEOS, which is arguably “safer” for the patient (see further down in the presentation regarding JYNNEOS.)

The Fact Sheet for Healthcare Providers for ACAM2000 is here: www.fda.gov/media/75792/download. The document gives a much more comprehensive picture of the dangers of this “vaccine.” Yours Truly will highlight a few of the items in this document which show how dangerous and deadly this vaccine is, beginning with two images from page 1 of the Fact Sheet: the Black Box Warning; and, the Warnings and Precautions:

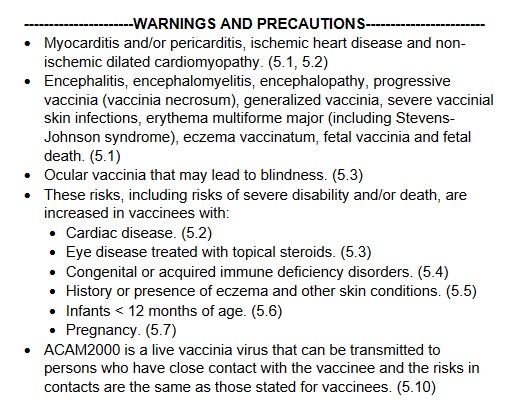
Remember, this dangerous and deadly “vaccine” is now approved for persons “at risk for Mpox”, in addition to persons at risk for Smallpox (this disease was eradicated in 1980.)

And, from Section 6 Adverse Reactions portion of the Fact Sheet for ACAM2000:

Continuing with Section 11 Description from the Fact Sheet for ACAM2000:

And, from Section 17 Patient Counseling Information of the Fact Sheet for ACAM2000, two portions:


Note several items from the above screenshots: One, that the “vaccine” must be given to the recipient via 15 separate jabs with a bifurcated needle; Two, there are MULTIPLE adverse reactions potential for persons taking this “vaccine”; Three, that persons who contract a Smallpox infection from a person “vaccinated” with ACAM2000 can die of the infection they contract; Four, that the ACAM2000-“vaccinated” person must stay away from pregnant women, household members, persons with eczema, etc., for a period of time after “vaccination”; among many other issues.

Yours Truly will again recall to the reader’s mind that ACAM2000 is now FDA-approved for PREVENTIVE USE among persons who are at risk for Mpox. From what Yours Truly has read about it, Mpox is, for all intents and purposes, likely to be a LESS-DANGEROUS form of Orthopoxvirus, compared to another form of the same Genus, variola (Smallpox virus.) [HOWEVER, see the presentation answering Question Two, further below in the post.] There is a vaccine that was previously FDA-APPROVED for the prevention of Mpox — JYNNEOS, manufactured by Bavarian-Nordic. This vaccine also uses the vaccinia virus as the foundation; but, JYNNEOS is cultured in a mixture of chicken embryo cells; and, although it also has live vaccinia, it is a NON-replicating version. JYNNEOS was also originally FDA-approved for the prevention of Smallpox. In Yours Truly’s opinion, even though JYNNEOS does indeed have potential for serious adverse reactions (for example, cardiac issues), this vaccine appears to be much less dangerous and deadly compared to ACAM2000. The FDA Fact Sheet for Healthcare Providers for JYNNEOS is here: www.fda.gov/131078/download.

Two questions arise immediately: First, what is about ACAM2000 that makes it so dangerous?; and, Second, why did the FDA suddenly approve the use of ACAM2000 for the prevention of Mpox in August 2024?

As to the first question: ACAM2000 is the “descendant Smallpox vaccine” from the older Dryvax Smallpox vaccine, which was manufactured by Wyeth. ACAM2000 replaced Dryvax in August 2007, after FDA approval. The Package Insert (archived version) for Dryvax is here: https://biotech.law.lsu.edu/blaw/bt/smallpox/dryvax_label.htm. Below are two screenshots from the Package Insert for Dryvax:


Note that the inoculation process for Dryvax consisted of 2 or 3 punctures for the initial (primary) vaccination; and that 15 punctures were used for revaccination. However, ACAM2000 requires 15 punctures for the initial vaccination. Why 15 punctures for the initial vaccination? It would appear, in Yours Truly’s opinion, that requiring 15 punctures for the initial vaccination with ACAM2000 exposes the patient to more of the ingredients of the vaccine (think the Moderna COVID-19 modRNA “vaccines” all having more than 3 times the “mcg payload” of lab-enhanced SARS-CoV-2 spike protein PER INJECTION, as compared to the “mcg payload” of the Pfizer-BioNTech modRNA COVID-19 “vaccines.” [Which is NOT to say that the Pfizer-BioNTech modRNA “vaccines” are somehow “safer” than those of Moderna. THEY ARE NOT.])

Yours Truly turns to section 8.1 of the FDA Fact Sheet for Healthcare Providers for ACAM2000 (link above.) This “vaccine” is particularly dangerous to pregnant women, to women who wish to become pregnant, and to a fetus carried by a pregnant woman (whether or not she is “vaccinated” with ACAM2000, since persons “vaccinated” with this product will “shed” ingredients [from the forming / formed pustule, or the scab from the pustule, etc.], onto other persons who come into contact with the “vaccinated” person.) Below is section 8.1:

It would also appear that there is inherent danger due to the fact that ACAM2000 uses a live, replicating vaccinia (another Orthopoxvirus that is “weaker” than variola [the Smallpox virus], and which is used to make modern-day Smallpox / Mpox vaccines), as compared to the live, NON-replicating vaccinia that is used the JYNNEOS Smallpox / Mpox vaccine. Once inoculated (vaccinated) with ACAM2000, the vaccinia produces a kind of “mini-infection” in the patient, affecting the area around the inoculation site, along with the lymph nodes in the same area. Vaccinia may also appear in the blood of the patient. There is also the issue of “self-inoculation” by the ACAM2000-“vaccinated” patient (from scratching or “picking at” the scab that forms after the “mini-infection” pustule forms on the skin, and also when this pustule begins to clear); and for other reasons — the FDA Fact Sheet section 17 Patient Counseling Information for ACAM2000 discusses this. In addition, there is the varying amount of vaccinia concentration that is produced in the patient after ACAM2000 inoculation; see below from section 11 Description of the FDA Fact Sheet for Healthcare Providers:

In other words, there are many areas about the ingredients and mechanisms of ACAM2000 that raise the risk of complications, including death, for the patient who takes this “vaccine”, for pregnant women and their fetuses, for women who wish to become pregnant, for persons who are immunocompromised, and for persons who are NOT “vaccinated” with ACAM2000, during the multiple “danger zone” weeks after ACAM2000 inoculation.

Turning to the second question, concerning the FDA approval in August 2024 for ACAM2000 to be used as an Mpox “vaccine”: this situation is complex. It involves Big Pharma, the WHO, and, what to Yours Truly “smells like” Gain-of-Function research, among other items.

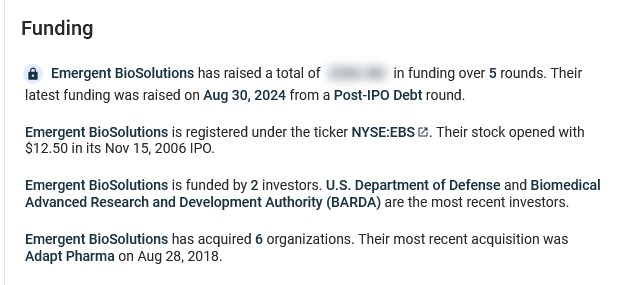
Yours Truly will begin with Emergent BioSolutions, the company that produces ACAM2000. Emergent BioSolutions, a “global enterprise” with headquarters in Gaithersburg, MD, was established in 1998. Its first project was to partner with the United States Defense Department to supply the Anthrax vaccine that was administered to members of the military (www.emergentbiosolutions.com/about-us/.) The current CEO of the company is Joseph C. Papa. Mr. Papa’s most-recent position was CEO of Bausch + Lomb, another large Big Pharma company. Mr. Papa, apparently, is a “mover and shaker” in the pharmaceutical industry. However, it is also apparent that Baush + Lomb was in financial trouble when he left it to become CEO of Emergent BioSolutions. In fact, Bausch + Lomb is “exploring” selling off some of its pharmaceutical assets, due to “significant debt load” (https://finance.yahoo.com/news/bausch-lomb-explores-sale-amid-112230409.html.) Perhaps, the company’s Post-IPO debt funding was not enough: www.crunchbase.com/organization/bausch-lomb/company_financials; scroll down to “Investors.” Mr. Papa has Bachelor’s and Doctorate degrees in Pharmacy; his career includes working with many Big Pharma companies (Novartis, Cardinal Health, and Watson Pharmaceuticals, among others.) Please see his entry in Wikipedia; and, here: https://waterstreet.com/people/papa-joseph. Water Street (Water Street Healthcare Partners) is an investment company that has a portfolio worth approximately $6Billion spread across healthcare services companies, medical diagnostics companies, and pharmaceutical/life sciences companies (https://waterstreet.com/companies.)

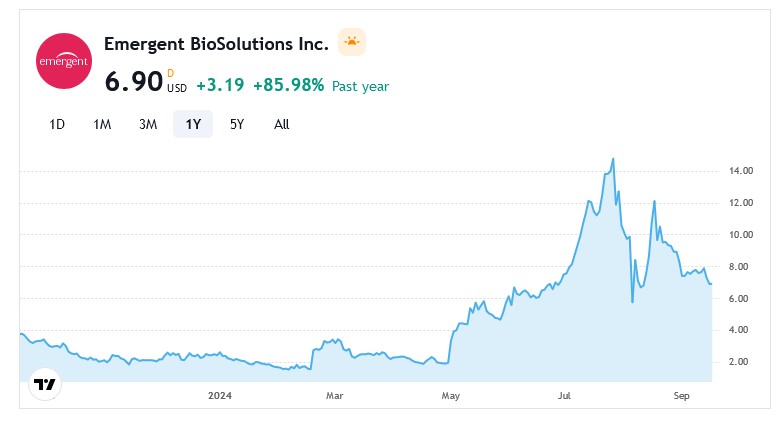
Mr. Papa was hired on 21 February 2024 by Emergent BioSolutions to facilitate the financial turnaround of the company. Below is a screenshot of the company’s financials from September 2023 to September 2024, via Crunchbase. It appears that Mr. Papa, a “mover and shaker” in the Big Pharma world, is working hard:
Also, via Crunchbase, a snapshot of Emergent BioSolution’s funders:
Which leads to this: https://investors.emergentbiosolutions.com/news-releases/news-release-details/emergent-biosolutions-acam2000r-smallpox-and-mpox-vaccinia, “Emergent BioSolutions’ ACAM2000R (Smallpox and Mpox (Vaccinia) Vaccine, Live) Receives U.S. FDA Approval for Mpox Indication; Public Health Mpox Outbreak Continues Across Africa and Other Regions”, 29 August 2024. The announcement follows this, from the WHO: www.who.int/news-room/questions-and-answers/item/mpox, 17 August 2024. A screenshot of a portion of article is below:

Which also follows the WHO declaration of an “Mpox Public Health Emergency” in Africa: https://investors.emergentbiosolutions.com/news-releases/news-release-details/emergent-biosolutions-responds-mpox-public-health-emergency, 19 August 2024.

It appears that now, Mpox is being “re-classified” as another, although serious, sexually-transmitted disease that can infect any sexually-active person; and, that Mpox has apparently “made the leap” from monkeys to other animals (rodents and even to domesticated dogs), and to between animals and humans. This leads to another aspect of the situation: Yours Truly’s suspicion that there have been / are ongoing, Gain-of-Function experiments on Mpox.

Here is the “fast and dirty” summary on Gain-of-Function experiments with Mpox:

One: Up until 22 August 2024, the FDA had only ONE approved “vaccine” for Mpox: JYNNEOS. However, on that same day, the FDA conducted a “review” of the BLA Application (Biologics License Application) for ACAM2000 to have approval as a “vaccine” for Mpox. This application was approved on 29 August 2024 (www.fda.gov/news-events/press-announcements/fda-roundup-august-30-2024.) Please see: www.fda.gov/media/181552/download for the BLA review. The FDA reviewers, apparently, had some “reservations” about ACAM2000 — see the screenshot below:

Despite the multiple reviewer comments regarding the BLA for ACAM2000, the FDA approved it anyway for Mpox “prevention.” In fact, look at THIS, from section 11.2 of the ACAM2000 BLA document, below:

Two, the Gain-of-Function issue regarding Mpox: First, the CDC connection:

The CDC has a”working relationship” with countries all over the world, including African countries: www.cdc.gov/global-health/about/index.html. The NIH has an entire department, the Fogarty International Center, part of the agency’s “global outreach.” Here is the agency’s link to the “Sub-Saharan African Region”: www.fic.nih.gov/WorldRegions/Pages/SubSaharanAfrica.aspx.

The “Fauci connection” related to his article regarding the role of the NIAID “…in preparing for an expanded “biodefense” role”, April 2022: www.ojp.gov/ncjrs/virtual-library/abstracts/expanded-biodefense-role-national-institutes-health. The NCJ Number is 194395. Below is the Abstract:

The CDC has an updated report on the incidence of Clade II infections of Mpox, an outbreak that originated in Central Africa (more on Clade II of Mpox further down in today’s post): www.cdc.gov/, “Clade II Mpox Outbreak Originating in Central Africa”, 13 September 2024. Per this article, there are no Clade I Mpox infections in the United States at this time; however, there are 2466 reported cases of Clade II Mpox infections, with 7 deaths. There are also, per the CDC report, cases of Clade II of Mpox literally all over the world at this time.

Here is an example of Gain-of-Function experiments with the Clade II of Mpox. This paper is about a study conducted at Kansas State University in which pigs were exposed to the Clade II of Mpox to see if they would get sick, and then take various blood and biological samples and test them. Sure enough, the pigs contracted Mpox. Please see: www.ncbi.nlm.nih.gov/pmc/articles/PMC11168330/, “Experimental inoculation of pigs with monkeypox virus results in productive infection and transmission to sentinels”, Emily Mantlo, et al., 7 May 2024. “Sentinels” were the pigs who were not injected with the Clade II Mpox, but were put in the same cages as those pigs who were. The “sentinel” pigs also came down with Mpox (in other words, animal-to-animal transmission of the virus.) Below are the Ethics Statement and the Funding Statement for this study:


Note that the study was conducted in BSL-3 labs at KSU; that tissue-processing was performed at CDC BSL-2 facilities; and, that, apparently, college students were working in the BSL-3 labs in the study. This indicates that Gain-of-Function experiments with the Clade II of Mpox were being performed; that lower-level biosafety labs were used; and, that college students were involved (how much close supervision was provided by KSU?)

Yours Truly now turns to the alarms being sounded regarding this Gain-of-Function research on Mpox, beginning here: www.science.org/content/article/house-republicans-fault-nih-for-evasive-answers-on-risky-monkeypox-virus-study, 11 June 2024. This is followed by: https://usrtk.org/risky-research/fauci-institute-hid-mpox-gain-of-function-plans/, 11 June 2024, by Emily Kopp. A screenshot from the USTRK article is below:

The link to the Congressional report is here.

So, Gain-of-Function experiments are being performed using the Mpox virus; experiments funded by the NIH. A very dangerous, deadly Smallpox “vaccine”, ACAM2000, was suddenly FDA-approved for the “prevention” of Mpox. The “definition” of who is “at risk” for an Mpox infection has been “expanded” to include all persons who are sexually active. The Clade II of Mpox (the one that is the subject of the Gain-of-Function experiments) is now infecting people all over the planet, including in the United States. And more. Cui bono? How many of the general public will line up for an injection of ACAM2000 because the CDC / FDA / AMA / Establishment Medicine, will issue a warning due to “increasing numbers of infections being reported of Mpox?” How many healthcare professionals will be “mandated” into taking ACAM2000 “to protect themselves and the patients they care for?” (Again, JYNNEOS was already approved for Mpox “vaccination”, and it is ** potentially ** a “safer” alternative “vaccine.”) How many more Gain-of-Function experiments will be conducted, not in facilities like the Wuhan Institute of Virology or the Baric Lab at UNC Chapel Hill — but at places like the BSL-3 Ag Lab at Kansas State University (a facility where, arguably, one would expect research on, say, equine viruses, not Clade II Mpox experiments on pigs)? How much more Gain-of-Function experimentation will be hidden and/or “obscured” from public knowledge, let alone from Congress?

Peace, Good Energy, Respect: PAVACA

Medicinal Cordials Open Thread: Health Friday 2024.09.13

The above image of vintage pharmacy bottles for medicinal cordials is courtesy of Wikipedia.

Today’s post is one of a series, Health Friday, related to Big Pharma, vaccines, general health, and associated topics. However, the discussion in these posts is not limited to what is presented: it is an Open Thread.

To begin, there are Important Wolf Moon Notifications, with a couple of extra items:

Free speech is practiced here. “Use it or lose it.”

The following are alternate Q Tree sites for certain circumstances:

The U Tree is for “argue it out” interactions.

The Rescue Thread at the U Tree: click on the “Featured” article.

The Third Site, in case the above two are not accessible.

Civil discussion is practiced here. The excellent and timely Rules of our late, good Wheatie prevail:

One: No food fights.

Two: No running with scissors.

Three: If you bring snacks, bring enough for everyone.

Please follow the added guidelines from our good Wolf Moon. Please do not give the modern-day version of Cato the Elder the opportunity to show “enmity” to the board.

The extra items:

What Yours Truly presents in this series, as in her previous blog posts for this board, is not medical advice — they are opinions and hypotheses based on her over 4 1/2 years (and continuing) of reading about, researching about, and writing about “all things COVID”, Big Pharma, and other health topics. Readers are encouraged to consult a healthcare practitioner regarding health concerns or conditions.

Today’s offering for Health Friday is one of a “slightly different path” — it regards Medicinal Cordials. It is a fascinating history that traces at least as far back to Italy during the 15th and 16th Centuries (the Renaissance period.) At that time, medicinal cordials were created and sold by apothecaries (what would now be called Pharmacists.) The craft spread quickly among western European countries (France, Spain, Germany, and England.) Medicinal cordials were originally used to “release” diseases from the body of the patient; to assist in the “renewal” of the diseased body, mind, and spirit; and, to “renew the natural heat” of the body. There were medicinal cordials that had flecks of gold. crushed pearls, or crushed coral added to them, as these items were thought to “assist” the mechanism of the drink. Medicinal cordials eventually “evolved” along two paths: One, into what became “patent medicines”; and, Two, into what are now called “digestifs” and non-medicinal cordials or liqueurs. A “separate” path of development produced a kind of “medicinal beer.” Some medicinal cordials had no alcoholic content at all; others had varying amounts of alcohol content. Some medicinal cordials were made from flowers and spices; others contained herbs and wood derivatives; still others were made of only from herbs and spices. They were (and, along with their modern-day versions of liqueurs, still are), distinct from “fortified wines”, such as Sherry or Vermouth; and, from certain other types of “alcohol + derived ingredient drinks”, such as Ouzo. There are “modern-day” types of “medicinal cordials” available: for example, https://texasmedicinals.com/, which produces and sells various cordials tinctures and elixirs made of flowers, herbs, and spices.

Certain orders of Roman Catholic monks were also involved in the making and providing of medicinal cordials. The famous cross between a medicinal cordial and a “digestif”, D.O.M. Benedictine, was first created by the Benedictine monks at the Abbey of Fecamp, France, in 1510. A French merchant, Alexandre Le Grand, found the original recipe in 1863 (it had been considered lost), and eventually recreated it as the drink sold today. Please see: https://wineanthology.com/1943-benedictine-dom-liqueur. The current product is no longer strictly a “medicinal cordial”, but is a liqueur. The exact ingredients are a secret, but the mixture is believed to contain hyssop, juniper, aloe, and cinnamon, among others. Please see: www.catalystplanet.com/travel-and-social-action-stories/2022/04/12/5-alcoholic-drinks-made-by-european-monks.

Then, there is Chartreuse, first created by the Carthusian monks of the Grande Chartreuse Monastery near Grenoble, France. A blend of distilled alcohol and 130 other ingredients (herbs and flowers among them), it is also no longer strictly a “medicinal cordial”, but a liqueur. (However, along with D.O.M. Benedictine, Chartreuse is still considered to have medicinal properties.) Chartreuse is available in “yellow” or “green” hues, which are different in their alcohol content. Please see: https://en.wikipedia.org/wiki/Chartreuse_(liqueur). There is also a version available, Chartreuse Vegetal, that is 138-Proof (www.luekensliquors.com/), search “Chartreuse Vegetal.” There are some websites that claim to have the ingredients of the recipe for Chartreuse; other websites have instructions on how to create a kind of “clone” of the recipe.

The Christian Brothers (originally, the De La Salle Christian Brothers), another Roman Catholic religious order of monks, began to grow and produce wines in the Martinez area of California around 1880. They expanded to include vineyards and wineries in the Napa Valley. They now produce altar wines for use in the Mass, and certain types of Brandy. They do not produce medicinal cordials or liqueurs. Please see: www.montlasallealtarwines.com/forms/MLS_History.pdf.

Drambuie, a whisky-based liqueur made in Scotland, is thought to have been created by “Bonnie Prince Charlie” (Prince Charles Edward Stewart) in 1745. A blend of malt whisky, honey, herbs, and spices, it was used as a medicinal cordial. The modern-day product is a Scottish whisky-based liqueur. Please see: www.thespruceeats.com/drambuie-liqeueur-profile-and-cocktals-760270.

Among other types of liqueurs, there are ones made of mostly flower or flower-herb bases. Some of these were originally used as “medicinal cordials.” Modern-day examples are: Vespetro (Italy); Becherovka Original (Czech Republic); St.-Germain Elder Flower Liqueur (France); and, American Elderberry Cordial (Missouri; no alcohol.)

And, yes, there is a kind of “medicinal beer” — Trappist beer, made by Trappist (Cistercian) monks. There are only a handful of Trappist monasteries that brew authentic Trappist beer or ale; they are governed by the International Trappist Association (ITA.) The recipe, a secret known only to a few of the monks, is thought to include herbs and spices. There is a “light” and a “dark” version of Trappist beer or ale (https://beerconnoisseur.com/articles/almighty-trappist-ale.) It is thought that the brew contains certain spices, such as cinnamon and coriander, in the mixture. For persons interested in making a “home-brew Trappist-style version” of the product, please see: https://beersmith.com/blog/2010/09/01/trappist-dubbel-and-tripel-recipes/.

However, there was a “darker side” to medicinal cordials — those that were used to quiet restless or ill babies and children. These were actually “patent medicines”; two such products were “Godfrey’s Cordial” and “Dalby’s Carminative.” They were used in England and the United States during the 18th and early 19th Centuries. The main ingredient of each of these “cordials” was opium — “Godfrey’s Cordial” had one ounce of opium for each two ounces of the product; “Dalby’s Carminative” contained 1/4 ounce of opium for each two ounces of the product. The number of babies and children who died from taking these products is not known. In addition, there was the original recipe for “Creme de Noyaux”, from Yvelines, France. This “cordial”, made from apricot or peach kernels, or cherry pits, could accumulate trace amounts of hydrogen cyanide (a poison.) The longer this “cordial” was kept in storage, the greater the potential for the hydrogen cyanide to accumulate and collect at the top of the bottle — an unsuspecting imbiber could be badly poisoned upon taking a glass of it. The recipe was re-formulated a few years ago by the Tempus Fugit company to remove all traces of the poison. (This formulation would appear to be the “safest” for Creme de Noyaux.)

There are sources online that can assist interested persons who wish to create cordials or liqueurs at home. One source is here: https://theherbalacademy.com/. Another source (which also has a history of medicinal cordials) is here: https://traditionalroots.org/wp-content/uploads/2015/05/Herbal-Cordials-and-Liqueurs-2_16.pdf, by Glen Nagel, ND (Naturopathic Doctor.) Here is an image of an Alembic Still, used to create home-made cordials or liqueurs (courtesy of Glen Nagel):

Interested persons should note that taking modern-day “versions” of medicinal cordials or liqueurs does not replace consulting a healthcare practitioner regarding health concerns; also, they should also investigate ingredients in home-made “medicinal cordials or liqueurs” to make sure none of them would interact with any prescription drugs, OTC drugs, and/or other herbals that the person is already taking. For example, the Gentian used in this home-made herbal “cordial” can interact with prescription drugs for high blood pressure, as Gentian is may lower blood pressure (www.webmd.com/vitamins/ai/ingredientmono-716/gentian, click on “Interactions.”)

Cordials glasses are usually small and hold no more than 2 to 4 ounces of the cordial. They are used to serve the drink at room temperature or chilled, and usually without other items mixed in. Some types of cordials glasses are also used to serve liqueurs. An example of vintage cranberry red cordials glasses is below, courtesy of https://rustedlove.com/:

Due to the varying alcohol content of cordials or liqueurs, and to their unique flavors, the modern-day versions of these products are often added to mixed drinks.

Ad Salutem Tuam!

Good Energy, Peace, Respect: PAVACA

Dear KMAG Health Friday Open Thread: The COVID-19 “Vaccines” Induce ME/CFS (Chronic Fatigue Syndrome): A Response to Steve Kirsch

The above vintage image of a tired woman is courtesy of QuoteGram, via Google Images.

Today’s Health Friday post, as it relates to COVID-19 and the COVID-19 “vaccines”, is dedicated to the memory of Yours Truly’s cousin Bill, who died “suddenly and unexpectedly” in September 2023. Health Friday is a series of offerings related to Big Pharma, vaccines, general health, and associated topics. However, the discussion is not limited to what is presented today: It is an Open Thread.

To begin, there are Important Wolf Moon Notifications, with a couple of extra items:

Free speech is practiced here: “Use it or lose it.”

The following are alternate Q Tree sites for certain circumstances:

The U Tree is for “argue it out” interactions.

The Rescue Thread at the U Tree: click on the Featured article there.

The Third site, in case the above two are not accessible.

Civil discussion is practiced here. The excellent and timely Rules of our late. good Wheatie prevail:

One: No food fights.

Two: No running with scissors.

Three: If you bring snacks, bring enough for everyone.

Please follow the Added Guidelines as expressed. Please do not give the modern-day version of Cato the Elder the opportunity to show “enmity” to the board.

The extra items:

What Yours Truly presents in this series, as in her previous blog posts for this board, is not medical advice — they are opinions and hypotheses based on her over 4 1/2 years (and continuing) of reading about, researching about, and writing about, “all things COVID”, Big Pharma, and other health topics. Readers are encouraged to consult a healthcare practitioner regarding health concerns or conditions.

Note: If any reader of today’s post is also a subscriber to Mr. Kirsch’s Substack (https://kirschsubstack.com/), it would be much appreciated if the link to this post could be sent to him. Thank you.

Dear Mr. Steve Kirsch:

Greetings. The writer of this post is a regular reader of your Substack site. Many thanks for all your efforts in exposing the truth about the COVID-19 “vaccines.” This is a response to your blog post of 30 August 2024, The COVID shots are fueling the rise of ME/CFS cases. While it is true that ME/CFS can present symptoms that are similar to that of “Long COVID”, I suspect that there may well be other items in play. To start, I am including an image of the VAERS chart that is in your blog post:

The incidence reports of CFS (ME/CFS) after taking COVID-19 “vaccines” far outstrips all of the other vaccines listed.

The Statement from the Paul-Ehrlich-Institut on “Post-Vac Syndrome” after COVID-19 Vaccination, regarding the PEI study mentioned in your post: www.pei.de/EN/newsroom/positions/covid-19-vaccines/statement-postvac.html, of 19 May 2023, has this (a portion of the screenshot):

I note that the Paul-Ehrlich-Institut is an agency of the German federal government. It is the equivalent to the FDA in the United States.

ME/CFS (Myalgic Encephalomyelitis / Chronic Fatigue Syndrome, also called Post Viral Fatigue Syndrome), is a medical condition that is difficult to diagnose and to treat: see Myalgic encephalomyelitis/chronic fatigue syndrome, per Wikipedia. For years, the condition has eluded efforts to isolate and identify elements that cause it; until fairly recently, only the presenting symptoms were recognized and treated: www.mayoclinic.org/diseases-conditions/chronic-fatigue-syndrome/symptoms-causes/syc-20360490; and, www.mayoclinic.org/diseases-conditions/chronic-fatigue-syndrome/diagnosis-treatment/drc-20360510. However, there have been recent discoveries that relate to one potential element in ME/CFS: mitochondrial dysfunction that interferes with a protein called WASF3. It appears that high levels of WASF3 can create what may be called a “cellular energy deficit”, which, in turn, can create fatigue. One example of the research on this is here: www.pnas.org/doi/10.1073/pnas.2302738120, WASF3 disrupts mitochondrial respiration and may mediate exercise intolerance in myalgic encephalomyelitis/chronic fatigue syndrome, Paul H. Hwang, et al., 14 August 2023. WASF3 is a component of the Human Chromosome 13: https://en.wikipedia.org/wiki/Category:Genes_on_human_chromosome_13, click on “Next Page” at the bottom of the A-U alphabetical list of proteins on the article.

ME/CFS conditions existed well before either the SARS-CoV-2 (COVID-19) virus itself, or the COVID-19 “vaccines” — per Wikipedia, Dr. Melvin Ramsay “published the first diagnostic criteria for ME” (Myalgic encephalomyelitis) in 1986. (Wikipedia search “history of ME/CFS”) However, cases of ME/CFS began to present in otherwise healthy people after they contracted a case of COVID-19 early on in the COVID-19 pandemic (before the COVID-19 “vaccines” were in use.) One such case is summarized here, in the Yale Medicine blog: Long COVID, ME/CFS and the Importance of Studying Infection-Associated Illnesses, 13 May 2024, by Osman Moneer. Below is a screenshot from the article:

Note: “Dr. Deborah F.” is not her real name.

There also may be a link between ME/CFS, Long COVID, and negative emotional-psychological outcomes: Infections, ME/CFS, Long COVID and Psychosis: Is There a Link?, 16 July 2023, by Cort Johnson. A screenshot from part of The Gist section of the article is below:

This opens up the question, What is in the COVID-19 virus itself, and therefore in the COVID-19 “vaccines”, that can induce ME/CFS (Post-viral Fatigue)? Yours Truly turns to the report that Pfizer-BioNTech gave to the FDA on 30 April 2021, regarding post-authorization Adverse Event Reports submitted to the company in people who took the first injection of the modRNA COVID-19 “vaccine” BNT162b2, between 12 December 2020 (the date on which the FDA granted the initial authorization for BNT162b2 to be used in the United States) and 28 February 2021. The report is here, via FOIA release: www.phmpt.org/wp-content/uploads/2022/04/reissue_5.3.6-postmarketing-experience.pdf. Page 30 of this report is the APPENDIX 1. LIST OF ADVERSE EVENTS OF SPECIAL INTEREST. This is a nine-page listing of over 1,200 serious Adverse Events that occurred in people who were “vaccinated” with BNT162b2 during the report period. Page one of this list has two types of damage to the mitochondria reported: “Alanine aminotransferase increased”; and, “Antimitochondrial antibody positive”. Page three lists “Chronic fatigue syndrome.” Page five lists “Immune-mediated encephalitis” and “Immune-mediated encephalopathy.” Page seven lists “Post viral fatigue syndrome.” In other words, at least six types of mitochondrial, neurological. or “body-wide” issues that are induced by modRNA COVID-19 “vaccines”, which can present in various forms, including CFS or ME/CFS.

There is also a link between the Epstein-Barr Virus (EBV) and the COVID-19 “vaccines.” EBV can be an “adjunct” presenting condition related to ME/CFS. Yours Truly found one paper, by Japanese researchers, on EBV presenting after “vaccination” with BNT162b2 (the Pfizer-BioNTech COVID-19 “vaccine”, [Epstein-Barr virus-associated lymphoproliferative disorders after BNT162b2 mRNA COVID-19 vaccination], from 2023. Only the Abstract is available in English. It is below:

It is now known that the COVID-19 “vaccines” (actually, gene therapy injections) do the following to the “vaccinated” person’s body:

Cross the Blood-Brain barrier (BBB); interfere with / damage / destroy mitochondrial elements and mechanisms; can induce negative effects / interfere with neurological elements and mechanisms; can induce onset of psychological issues, including psychosis; interfere with / damage or destroy, elements and mechanisms of the natural immune system (citations below.) These negative effects, in Yours Truly’s opinion, all have a bearing on the causation and presentation of COVID-19 “vaccine”-induced or aggravated ME/CFS. In order for these to occur, again in Yours Truly’s opinion, certain specific elements had to have been “inserted” into the lab-created SARS-CoV-2 (COVID-19) virus itself (and, by extension, into the lab-enhanced COVID-19 “vaccines”) to induce these types of damage. Perhaps it was a specific element that interacts with the WASF3 protein; perhaps it was a specific element that interacts with a component of the Epstein-Barr virus. Perhaps it was a specific element that interacts / interferes with other aspects of Human Chromosome 13. Perhaps it was all of these. I believe that ongoing research into the actual ingredients of the modRNA of the COVID-19 “vaccines” will eventually reveal the answers.

In addition, there are the following lipid nanoparticle (LNP) ingredients in the modRNA COVID-19 “vaccines”:

For the Pfizer-BioNTech “vaccines”: ALC-0159, ALC-0315, and PEG2000-DMG; for the Moderna “vaccines”: SM-102, ALC-0315, and PEG2000-DMG. All of these lipid nanoparticles are dangerous. All of them are to be used for research only, not for use in diagnosis or therapeutics for humans or for animals. All of them specifically “evade” the “vaccinated” person’s natural immune system’s “Are you a friend or a foe?” recognition and elimination mechanisms. They facilitate “access” of the ingredients and mechanisms of these modRNA COVID-19 “vaccines” to induce damage / destruction of the IgG3 “fight it off” immune system cells in the “vaccinated” person’s body; and, at the same time, to increase the amount of IgG4 “tolerate and never clear” immune system cells. This process is called the “Class Switch” done by the modRNA COVID-19 “vaccines.” (Citations below.)

In Summary: The COVID-19 virus itself can induce multiple negative medical effects on persons who contract an infection of the virus, including ME/CFS. The COVID-19 “vaccines”, which contain elements of the COVID-19 virus itself (in addition to other lab “enhancements” for these “vaccines”, such as the lipid nanoparticles), can therefore also induce multiple negative medical effects in persons who take these injectables, including ME/CFS. In addition, both the COVID-19 virus itself, and, by extension, the COVID-19 “vaccines”, can induce and/or aggravate negative psychological conditions. I believe that these “vaccines” need to be banned outright immediately and removed from the market across the world, until and unless such time they are completely reformulated and thoroughly tested (including testing by independent labs) for human safety, efficacy, toxicity, mutagenesis potential, and reproductive effects potential.

It is my opinion that: One, that all people, COVID-19 “vaccinated” or not, follow a personal program to acquire and maintain the highest degree of natural immune system health as possible; and, Two, that all people investigate any vaccine that is recommended (or “mandated”), then, to decide whether or not to take the injectable(s.)

Citations regarding the In Summary above, the lipid nanoparticles, and the “Class Switch”:

Lipid nanoparticles: ALC-0159: https://cdn.caymanchem.com/cdn/msds/34336m.pdf; ALC-0315: https://cdn.caymanchem.com/cdn/msds/34337m.pdf; SM-102: https://cdn.caymanchem.com/cdn/msds/33474m.pdf; PEG2000-DMG: https://cdn.caymanchem.com/cdn/msds/33945m.pdf. Please see Application of the Substance / the mixture on page one of these Safety Sheets.

Crossing the Blood-Brain Barrier: Adverse effects of COVID-19 mRNA vaccines: the spike hypothesis, Ioannis Trougakis, et al., 21 April 2022.

Mitochondrial damage: SARS-CoV-2 and the spike protein in endotheliopathy, Luca Perico, et al., 12 June 2023; and, www.theqtree.com/2023/10/28/the-covid-19-virus-and-the-modrna-covid-19-vaccines-induce-accelerated-aging/.

Neurological side effects: A review of neurological side effects of COVID-19 vaccination, Roya Hosseini and Nayere Askari, 25 February 2023. And, COVID-19 “vaccine”-induced psychosis: First Episode Psychosis Following the COVID-19 Vaccination – A Case Series. Tonka Borovina, et al., 18 May 2022.

The IgG3 – IgG4 “Class Switch”: IgG4, CD4s and why the LNP/mRNA platform should be prohibited, Jessica Rose, PhD, 14 August 2023.

Thank you for your time, Mr. Kirsch. Sincerely, with Peace, Good Energy, and Respect: PAVACA

Dear KMAG 2024.08.30 Health Friday Open Thread: The American Board of Internal Medicine Dictates “Toe the Line, Or Else”

The above image is courtesy of Board and Batten.

This post is part of Health Friday, a series of offerings related to Big Pharma, vaccines, general health, and associated topics. However, the discussion will not be limited to what is presented today; it is an Open Thread.

To begin, there are Important Wolf Moon Notifications, with a couple of extra items:

Free Speech is practiced here. “Use it or lose it.”

The following are alternate Q Tree sites for certain circumstances:

The U Tree is for “argue it out” interactions: https://utree.com.blog

The “Rescue Thread” at the U Tree: https://utree.home.blog and click on the “Featured” article.

The “third site”, in case the above two are not accessible: https://theqtree579486807.wordpress.com/

Civil discussion is practiced here. The excellent and timely Rules of our late, good Wheatie prevail:

One: No food fights.

Two: No running with scissors.

Three: If you bring snacks, bring enough for everyone.

Please follow the added guidelines as expressed here: www.theqtree.com/2019/01/01/dear-maga-open-topic-20190101/. Please do not give the modern-day version of Cato the Elder the opportunity to show “enmity” to the board.

The extra items:

What Yours Truly presents in this series, as in her previous blog posts for this board, is not medical advice — they are based on her over 4 1/2 years (and continuing) of reading about, researching about, and writing about “all things COVID”, Big Pharma, and other health topics. Readers are encouraged to please consult a healthcare practitioner regarding health concerns or conditions.

Today’s post in the Health Friday series regards the ongoing efforts by what Yours Truly calls Establishment Medicine to minimize, marginalize, and/or outright punish those healthcare professionals (especially physicians) who speak the truth about the COVID-19 virus itself and the COVID-19 “vaccines.”

For purposes of the post today, Yours Truly begins here: ABIM: “Follow the consensus, not the science. Saving lives is not a priority.”, from The Burning Platform, a post by Steve Kirsch. This details the American Board of Internal Medicine revoking the certifications of Dr. Pierre Kory and Dr. Paul Marik. The Washington Post and other media outlets gloated over this, trumpeting that the “medical disinformation spread” by these physicians (such as, that Ivermectin and Hydroxychloroquine can prevent and cure COVID-19 infections; and, that the modRNA COVID-19 “vaccines” are dangerous) was finished. Yours Truly’s presentation focuses on the ABIM decision regarding Dr. Kory.

Dr. Pierre Kory is a co-founder of COVID-19 Critical Care (FLCCC): https://covid19criticalcare.com/. He has been, and is, since the beginning of the disaster of COVID-19 and the COVID-19 “vaccines”, a leading voice in exposing the truth of this situation, along with being a champion of using Ivermectin and Hydroxychloroquine to prevent a COVID-19 infection and to treat COVID-19 infected patients. Until this month, Dr. Kory held three board certifications from the American Board of Internal Medicine — until this happened: The American Board of Internal Medicine Revoked All 3 of My Board Certifications, 17 August 2024. This is a big deal. Here’s why: By this action, the American Board of Internal Medicine (ABIM) removed Dr. Kory’s ability to have hospital privileges; it removed his ability to hold an academic position; and, it removed his ability to work in a medical clinic or other facility where other physicians hold ABIM certifications. Dr. Kory can still practice medicine in a private clinic where there no ABIM physicians; or, he can work independently in a clinic that he himself establishes. Below are three screenshots from Dr. Kory’s article:

Note the above third screenshot. To remove the ability of physicians to “think out of the box” will be, in Yours Truly’s opinion, to implement “one-size-fits-all Establishment Medicine.” And this is not all — this approach will (if it hasn’t already) spill over into the CMS (Medicare / Medicaid) system, making it almost impossible for persons covered under this system to find physicians who want to “think out of the box.”

The history of medical board certification in the United States began in 1917. A brief history can be found here: www.ncbi.nim.nih.gov/pmc/articles/PMC2394686/, “Professionalism and Accountability: The Role of Specialty Board Certification”, by Christine K. Cassell, MD, and Eric S. Holmhoe, MD, 2008. There are multiple entities that grant board certifications to physicians. Two of them are: the American Board of Medical Specialties (ABMS) www.abms.org/, which grants certifications in 40 specialties and 89 “sub-specialties”; and, the American Board of Internal Medicine (ABIM) www.abim.org/, which grants certifications in 14 specialties. In essence, board certification, which was at one time was an “add-on” to a physician’s already-established reputation and expertise is now a necessity — there is hardly a hospital, or a medical school, or a group practice that will consider hiring a physician who does not have a board certification, or is not working toward one. And, with the advent of “get board certified or forget about being hired”, comes what Yours Truly will call “the potential tyranny” of the granting entity over the physician who is board certified. There is continuing education and exams to renew the certifications; all of these cost money. There is “oversight” on the physician who obtains board certification — for example, are there any complaints from patients? Does the physician “spread misinformation” about things like the COVID-19 “vaccines” and/or “unapproved treatments” for COVID-19 infection? The granting entity can “charge” a physician who has board certification with “spreading misinformation” and/or “treating a patient with unapproved drugs”; the physician has to “defend” themself before the granting board in order to keep or to renew their certification(s). The granting entity has the sole power to either renew or to revoke the physician’s certification(s).

An opposite point of view on board certification is expressed here: Is Board Certification Overrated?, by Robert Anthony, 2010 (copyright 2010 by UBM). Below is a portion of the article:

On the other hand, here a screenshot from the ABMS article, About ABMS Board Certification:

Which appears, in Yours Truly’s opinion, to imply that a physician who is not board certified is somehow “lacking” in skills and knowledge and, perhaps, does not “meet a higher standard.”

Perhaps the most damning statement by Dr. Kory regarding the ABIM revoking his board credentials is this one, from his blog article referred to above:

Dr. Kory published a blog article in reply to the ABIM action against him: My Retaliation Against the American Board of Internal Medicine, 20 August 2024. Below is a screenshot from this article:

Read the above again. The ABIM has removed Dr. Kory’s ability to see patients in a hospital. He can’t participate in insurance plans — which means that any patient he sees in his own clinic must pay for all services, tests, and so on, out of pocket. This may include charges that would normally be covered by Medicare / Medicaid. He will have to carry less medical malpractice insurance. All of these can potentially mean that patients who need his services but cannot pay cash for them, are also potentially shut out from his services. His article above needs to be read: in it, he “exposes the underbelly” of the ABIM.

Dr. Meryl Nass (https://merylnass.substack.com/) also had her board certification revoked by the ABIM. The organization did not even bother to tell her that this was done: https://merylnass.substack.com/p/kory-and-marik-were-just-stripped, “Kory and Marik were just stripped of their specialty board certifications. So was I, but the ABIM never even bothered to tell me”, 14 August 2024. Dr. Nass also, in another blog post, reveals what may one item behind what the ABIM is doing — the organization apparently wants to replace the physicians whose certifications were revoked with medical doctors from foreign countries: https://merylnass.substack.com/p/after-stripping-doctors-of-their, “After stripping doctors of their credentials and making it impossible to practice ethical medicine, the ABIM wants to bring in foreign medical doctors as replacements”, 24 August 2024. Below is a JPG of the ABIM’s statement, shared by Dr. Nass from another physician:

To add another aspect to the discussion, Yours Truly believes there ** may ** be some involvement of the AMA (American Medical Association) in the revoking of board certifications: AMA adopts new policy aimed at addressing public health disinformation, 13 June 2022. Below is a screenshot from the press release:

Note the penultimate point regarding “specialty boards.” In Yours Truly’s opinion, the AMA is one of the bastions of what may be called “Establishment Medicine” (the others being entities such as: the CDC; the FDA; the medical schools of Harvard University, Stanford University, Cornell University, etc.)

Let’s say that a board-certified physician, “fully vaccinated and boosted” who “followed the science”, after watching “vaccinated and boosted” patients, colleagues, perhaps even family members, begin to present with “the doctors are baffled” medical issues; or, perhaps, a cancer that was in remission that has returned. Let’s say that this physician starts to feel a little uneasy regarding the modRNA COVID-19 “vaccines” and does a little research — perhaps, by reading a blog or two written by someone like Dr. Kory; perhaps, by reading some published scientific literature regarding “first onset of psychosis after SARS-CoV-2 vaccination” (there are multiple papers discussing this that can be found online.) Let’s say that this physician comes to the realization that the modRNA COVID-19 “vaccines” are not “safe and effective”, but instead are the opposite. Let’s say this physician has board-certification renewal coming up in a few months. And, to top it off, let’s say that this physician has a family to provide for, a mortgage to pay, and medical school debt to pay off. What is this physician to do? — without jeopardizing the job, the board certification, perhaps even the License to Practice Medicine? It is Yours Truly’s opinion that this kind of situation is starting to “bubble under the surface” of more than one physician currently in practice. It is not an easy situation to be in.

Where does this situation leave the patient? If the physician who discovers that the modRNA COVID-19 “vaccines” (actually, gene therapy and modification injections [the DNA of the “vaccinated” person is changed by the ingredients and mechanisms of these “vaccines”]) are ineffective and dangerous, but doesn’t / can’t say a word to the patient to not take them — doesn’t this violate the oath of “First, Do No Harm” that the physician swore upon receiving the degree of Doctor of Medicine? If the physician who finds out, for example, that Paxlovid has a high “rebound infection” percentage, but doesn’t / can’t say a word to the patient to not take this combo-drug but substitute, say, Hydroxychloroquine, Zinc, and Vitamin D to combat a COVID infection — doesn’t this silence put the patient at risk? One in Five Experience Rebound COVID After Antiviral Drug, New Study Shows, 13 November 2023. The article regarding the DNA change made by the modRNA COVID-19 “vaccines” is here: https://doctors4covidethics.com/wp-content/uploads/2022/08/causality-article. “Vascular and organ damage induced by mRNA vaccines: irrefutable proof of causality”, by Michael Palmer, MD, and Sucharit Bhakdi, MD, 18 August 2022. Slide 14 of this article is a graphic showing how the DNA of the COVID-19 “vaccinated” person is changed by the Pfizer-BioNTech modRNA COVID-19 “vaccine.”

How did the ABIM, the ABMS, and the other privately-run board certification granting entities in the United States come to have such power over the practice of medicine and over the physicians who obtain board certification? (There are literally dozens of these boards: www.americanboardcosmeticsurgery.org/so-what-does-physician-board-certification-actually-mean/, 7 February 2019.) To Yours Truly, it appears that they possibly used a combination of influence, lobbying, personal connections with medical schools, and other “tactics.” The result may well be an “authority” that these certification boards created and arrogated to themselves, in the name of “ensuring quality delivery of healthcare by qualified physicians.” While this may have been a true and worthy aspiration previously, it seems it has “evolved” into “Follow these dictates, or else.”

And, from there, where does this potentially go? If a physician is stripped of board certification(s), that physician can still practice medicine — unless their state medical licensing board (perhaps with the involvement of the AMA, please see above in today’s post) decides to “charge” the physician with “spreading disinformation to the public” in “violation” of the diktats of Establishment Medicine. The physician now faces the possibility of losing the License to Practice Medicine. The case of Dr. Carrie Madej, DO, comes to mind. (Doctors of Osteopathy are medical doctors who have somewhat different training from MDs, but who are recognized and licensed to practice medicine and write prescriptions.) She was brought up on similar “charges” by the medical licensing board of Georgia. After a protracted fight, Dr. Madej ultimately decided to surrender her License to Practice Medicine in 2023. (Recall that Dr. Madej was one of the first to demonstrate that the modRNA COVID-19 “vaccines” contain substances that appeared to be strange.)

And, from there, where does the potential for innovation in medicine go? If physicians (especially board-certified physicians) have to, in effect, constantly “look over their shoulder” and “toe the line” to Establishment Medicine, doesn’t this affect the potential to come up with new theories and to investigate them? — such as in, using drugs in “off-label” circumstances to help patients? — such as in, using Hydroxychloroquine to prevent or treat COVID-19 infection, instead of injecting a patient with a modRNA COVID-19 “vaccine” that changes that patient’s DNA and can also lead to the appearance of myocarditis or even to the death of the patient? Instead of hospitalized COVID-19 infected patients being put on ventilators and given Remdesivir, a drug that can kill the patient instead of helping the patient? Why Remdesivir Failed: Preclinical Assumptions Overestimate the Clinical Efficacy of Remdesivir for COVID-19 and Ebola, Victoria C. Yan and Florian L. Muller, 17 September 2021.

Yours Truly will say it is vitally important that all persons, COVID-19 “vaccinated” or not, to have and keep their natural immune system in the best condition possible; to become educated regarding any prescription medication that they take; and, to research any medical injectables that are recommended / required that they be given.

“For you shall know the truth, and the truth shall make you free.” John 8:32

Peace, Good Energy, Respect: PAVACA

Dear KMAG: 2024.08.23 Health Friday Open Thread: The modRNA COVID-19 “Vaccines” Induce IgG4-Related Disease

The above image of a physician performing a vaccination is courtesy of Google Images and The New York Times.

This post is the first of “Health Friday”, a new series of offerings related to Big Pharma, vaccines, general health, and related topics. It is an honor and privilege to contribute this series to the board. Since today’s post relates to COVID-19 and the COVID-19 “vaccines”, it is dedicated to the memory of Yours Truly’s cousin Bill, who “died suddenly and unexpectedly” in September 2023. However, the discussion will not be limited to what is presented today; it is an Open Thread.

To begin, there are Important Wolf Moon Notifications, with a couple of extra items:

Free Speech is practiced here. “Use it or lose it.”

The following are alternate Q Tree sites for certain circumstances:

The U Tree is for “argue it out” interactions: https://utree.home.blog

The “Rescue Thread” at the U Tree: https://utree.home.blog and click on the “Featured” article.

The “third site”, in case the above two are not accessible: https://theqtree579486807.wordpress.com/

Civil discussion is practiced here. The excellent and timely Rules of our late, good Wheatie prevail:

One: No food fights.

Two: No running with scissors.

Three: If you bring snacks, bring enough for everyone.

Please follow the added guidelines as expressed here: www.theqtree.com/2019/01/01/dear-maga-open-topic-20190101/. Please do not give the modern-day version of Cato the Elder the opportunity to show “enmity” to the board.

The extra items:

What Yours Truly writes in this series, as in her previous blog posts for this board, is not medical advice — they are opinions based on her over 4 1/2 years (and continuing) of reading about, researching about, and writing about “all things COVID”, Big Pharma, and other health topics. Readers are encouraged to please consult a healthcare practitioner regarding health concerns or conditions.

And now, to dive in. There is a lot to “unpack.”

The modRNA COVID-19 “vaccines” induce IgG4-related disease (IgG4-RD.) IgG4-related disease (IgG4-RD) is a term that covers multiple medical conditions, ranging from neurological to ocular to cardiovascular to respiratory to gastrointestinal to urogenital. Since it is a chronic inflammatory condition, there can be more than one location of an IgG4-RD associated ailment within the patient’s body. Please see: https://en.wikipedia.org/wiki/IgG4-related_disease, “IgG4-related disease”, which has a list of symptoms in reported cases of IgG4-RD, and a list of body area sites that can be affected by IgG4-RD. The first instance of what is now called IgG4-RD was discovered in 1892 by Johann von Mikulicz, who diagnosed an “inflammatory disease of the salivary glands” in a patient (this condition was later called Mikulicz’ disease.) In 2021, Hamano et al. found elevated IgG4 levels in patients with Autoimmune Pancreatitis (AIP.) Please see: https://ojrd.biomedicalcentral.com/articles/10.1186/s13023-014-0110-z, “IgG4-related disease: an orphan disease with many faces”, Herwig Pieringer, et al., 16 July 2014. It appears that an issue with obtaining a true diagnosis of an IgG4-related disease is that many of the presenting elements can “mimic” other conditions, such as cancer or non-Hodgkin’s lymphoma. In addition, IgG4-RD can simply not present symptoms at all, until the patient concludes that “something is going on here.” In terms of the presenting symptoms of an IgG4-RD disease, there are, among others: storiform fibrosis (“spindle-shaped” cells that can, with collagen fibers, form a “flowing arrangement”); and, eosinophilia (high elevation of a type of white blood cell [eosinophils] that supports the natural immune system.) Please see: https://academic.oup.com/mr/article/31/3/529/6300281, “The 2020 revised comprehensive diagnostic (RCD) criteria for IgG4-RD”, Hisamori Umehara, et al., 4 May 2021. (Note: the entire article is restricted access.) Below is a portion from “IgG4-Related Disease” from StatPearls – NCBI Bookshelf, an article by Sudheer Nambiar and Tony I. Oliver (www.ncbi.nlm.nih.gov/books/NBK499825):

There are some IgG4-RD conditions that may be genetically-based; one example is Autoimmune Pancreatitis (AIP.) Please see: https://pubmed.ncbi.nlm.nih.gov/31104539/, “Genetic analysis of IgG4-related disease”, Yuki Ishikawa and Chikashi Terao, 7 June 2020. (Note: again, the entire article is restricted-access.) On the other hand, another IgG4-RD condition, Autoimmune Lymphoproliferative Syndrome (ALPS) appears to strike children. In addition, IgG4-RD conditions can be “immune-mediated” (meaning, the body’s immune system response is either inappropriate or excessive); and/or “autoimmune” (meaning, the body’s immune system attacks healthy tissues in the body.)

Yours Truly will examine the presence of eosinophilia as an indicator of IgG4-RD. This is an important “marker.” And it ties into the modRNA COVID-19 “vaccines” — the COVID-19 “vaccinated” person’s natural immune system being damaged and/or destroyed by the ingredients and mechanisms of these “vaccines”; and, with repeated injections of these “vaccines” compounding this damage and/or destruction.

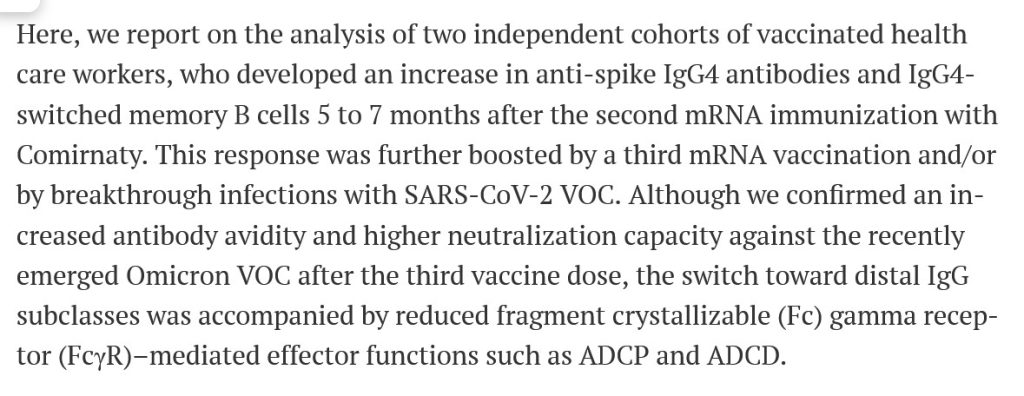
The first item is a blog article by Dr. Jessica Rose, PhD: https://jessicar.substack.com/p/igg4-related-disease-and-igg4-means, “IgG4-related disease (IgG4RD) means FIBROSIS and organ destruction”, 28 December 2022. It is now known that the modRNA COVID-19 “vaccines” induce a “class switch” in the COVID-19 “vaccinated” person’s natural immune system; this “class switch” is the damage and/or destruction of IgG3 immune system cells (these cells help to fight off infections and other enemies that “invade” the natural immune system), replacing IgG3 cells with increased numbers of IgG4 cells (these cells help to allow the body to “tolerate” assaults to the natural immune system.) Repeated injections of modRNA COVID-19 “vaccines” exacerbate this process: please see https://doi.org/10.1126/sciimmunol.ade2798, “Class switch toward non inflammatory, spike-specific IgG4 antibodies after repeated SARS-CoV-2 mRNA vaccination”, Irrgang P, et al., 22 December 2022. Notice the title: “non inflammatory”, “spike-specific”, “IgG4”, and “repeated SARS CoV-2 mRNA vaccination.” IgG4-RD conditions can present as non-inflammatory (the patient doesn’t notice anything wrong for some period of time, see above in today’s post); however, the IgG4 levels in the patient are high upon examination. Below is a portion of the Introduction of the above paper. Note: Comirnaty was the non-United States version of the Pfizer-BioNTech modRNA COVID-19 “vaccine” BNT162b2. Comirnaty and BNT162b2 are the same product. Note 2: the 2023-2024 Comirnaty modRNA COVID-19 “vaccine” was given full FDA approval for use in the United States on 23 September 2023 for persons age 12 above: www.pfizer.com/news/press-release/press-release-detail/pfizer-and-biontech-receive-us-fda-approval-2023-2024-covid; the version that the FDA authorized (the “2023-2024 Formula COVID-19 Vaccine” by the same company) was for persons age 6 months through 11 years of age (www.fda.gov/media/167211/download.)

Note that the IgG4 cell increase extended for months after the second injection of Comirnaty and was further increased after the third injection. This correlates to the original “two-injection Primary Series” plus the original “booster shot” of Comirnaty that millions of persons took between December 2020 and early 2022. This would also include, since the formulations were the same, of the “Primary Series” and the original “booster shot” of BNT162b2 that were taken by millions of persons in the United States from December 2020, until Comirnaty was given full FDA approval in the United States on 8 July 2022 for persons age 12 and older (at which point, BNT162b2 was “replaced” by Comirnaty except for use in persons age 6 months to 11 years; the FDA authorized the “Pfizer-BioNTech COVID-19 Vaccine” for this age group.) This “product name situation” may seem a little confusing: at bottom, it had to with removal of liability for the “vaccine” manufacturer. This will be discussed at a later date.) Note also that “VOC” means Variants of Concern (in other words, the Delta, the Omicron, the XBB.1.5 variants of the SARS-CoV-2 [COVID-19] virus, and so on.)

The second item is here: www.phmpt.org/wp-content/uploads/2022/04/reissue_5.3.6-postmarketing-experience.pdf, 5.3.6 CUMULATIVE ANALYSIS OF POST-AUTHORIZATION ADVERSE EVENT REPORTS OF PF-07302048 (BNT162B2) RECEIVED THROUGH 28-FEB-2021, given by Pfizer-BioNTech to the FDA on 30 April 2021. This report covers Adverse Event Reports that were submitted to the company between 11 December 2020 (the date on which the FDA in the United States granted the initial Emergency Use Authorization (EUA) for BNT162b2 to be used in the United States, 21 December 2020 (the date on which the EMA (European Medicines Agency) granted its initial EUA for BNT162b2 to be used in Europe / Scandinavia; and, 28 February 2021. The APPENDIX 1. LIST OF ADVERSE EVENTS OF SPECIAL INTEREST, which begins on Page 30 of this report, lists over 1,200 different types of medical adverse events that were reported to Pfizer-BioNTech from the worldwide EUA start dates above. On Page 3 and Page 4 of the APPENDIX 1. (Page 32 and Page 33 of the report), there are the following Adverse Events of Special Interest listed: Eosinopenia; Eosinophilic fasciitis; Eosinophilic granulomatosis with polyangiitis; Eosinophilic oesophagitis. On Page 5 of the APPENDIX 1. (Page 34) of the report, there is listed: Immunoglobulin G4 related disease. On Page 8 of the APPENDIX 1. (Page 37 of the report) there is listed: Sjogren’s syndrome (another type of IgG4-RD.) These are a few of the IgG4-RD types of reports that are listed in the APPENDIX 1. section. Thus, the FDA knew, on 30 April 2021, that BNT162b2 “vaccination” induces IgG4-related disease conditions. Yet, the FDA did nothing to stop the continuing rollout of BNT162b2.

A third item is here: https://mole.substack.com/cp/147758416, a 15 August 2024 cross-post from Lioness of Judah Ministry, “German Study Links Covid Shots to Surge in VITAL ORGAN DAMAGE among Children”. The study found that there was a large increase of organ damage induced by BNT162b2 in children in Germany ages 5 to 11 years old. The study is here: https://journals.lww.com/pidj/fulltext/9900/delayed_induction_of_noninflammatory_sars_cov_2.959.aspx, “Delayed Induction of Noninflammatory SARS-CoV-2 Spike-Specific IgG4 Antibodies Detected 1 Year After BNT162b2 Vaccination in Children”. Kobbe, Robin MD, et al., 30 July 2024. The IgG4 antibodies were detected after the second dose of BNT162b2 (in other words, after the “Primary Series” of two BNT162b2 injections was completed.)

And, a fourth item is here, related to COVID-19, the COVID-19 “vaccines” and autoimmune conditions: https://wmcresearch.substack.com/p/long-covid-is-an-autoimmune-disease, “Long COVID is an Autoimmune Disease: Injecting Mice with IgG from Long COVID Patients Induces Symptomology”, by Walter M Chesnut, 4 June 2024. Mr. Chesnut has long posited that the spike protein of the COVID-19 virus itself contains elements that attack the natural immune system of the body of a person infected with this virus; and that the COVID-19 virus itself can induce what is now called “Long COVID.” Yours Truly will add the opinion that the difference between “Long COVID” in a person who is “unvaccinated” against COVID-19, and “Long COVID” in a COVID-19 “vaccinated” person, is this: the natural immune system of the “unvaccinated” person still has the potential to not only fight off a COVID-19 infection, but also to mitigate or eliminate the chance that “Long COVID” may result from the infection; whereas, the natural immune system of the COVID-19 “vaccinated” person has been damaged (or worse), resulting in a much larger potential for “Long COVID” (both in presentation and in duration.)

Yours Truly believes that the COVID-19 virus itself, and the ingredients and mechanisms of the modRNA COVID-19 “vaccines” (one of these ingredients being a “lab-modified” form of the RNA of said virus), both attack the natural immune system of the body. The COVID-19 “vaccines” have been shown to damage and/or destroy the IgG3 cells of the body’s natural immune system (these cells help to fight off viruses, etc.), replacing these with increased amounts of IgG4 cells (“toleration facilitator” cells.) In Yours Truly’s opinion, one of the important details here is the targeting of HLA cells (human leukocyte antigen cells, a type of white blood cells) by the COVID-19 virus itself, and, by extension, the COVID-19 “vaccines.”

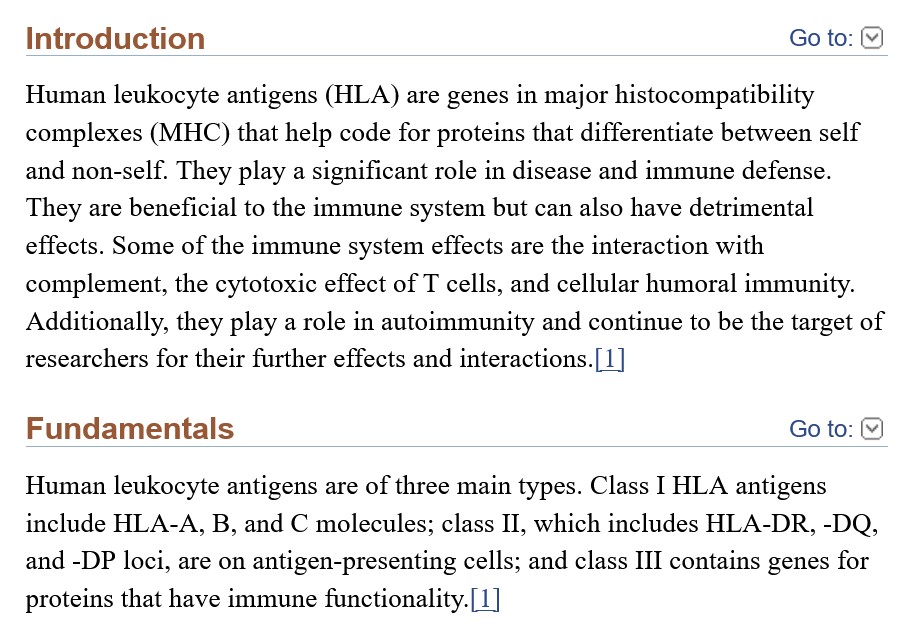
In the book Biochemistry, HLA Antigens by Helen Nordquist and Radia T. Jamil, www.ncbi.nlm.nih.gov/books/NBK546662/, there is the following:

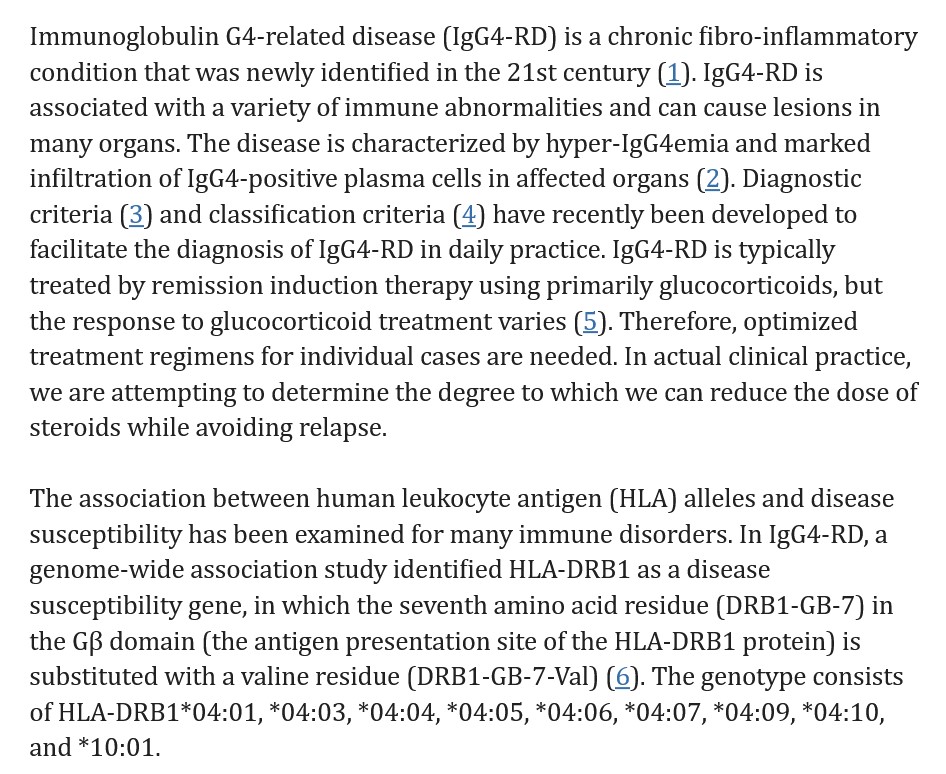
And, from this paper: www.ncbi.nlm.nih.gov/pmc/articles/PMC10864075, “HLA-DRB1 Is Associated with Therapeutic Responsiveness in IgG4-related disease”, Motohisa Yamamoto, et al., 23 May 2024:

Note that one of the most-recommended and used treatments for IgG4-RD conditions is glucocorticoids (steroids); and that cessation of treatment likely results in relapse of the condition. But, long-term use of glucocorticoids have risks, including high blood pressure and Cushing’s Disease. Please see: www.webmd.com/multiple-sclerosis/what-are-glucocorticoids.

Yours Truly will posit that the lab-created SARS-CoV-2 (COVID-19) virus itself, with the lab enhancements made to the mRNA of this virus to create the modRNA of the COVID-19 “vaccines” (such as the SV40 African Green Monkey cancer promoter gene piece in BNT162b2), plus the addition of dangerous lipid nanoparticles (ALC-0159 and ALC-0315 in BNT162b2 and its “descendant” COVID-19 “vaccines”; and, SM-102 in the Moderna mRNA-1273 modRNA COVID-19 “vaccines” and its “descendant” COVID-19 “vaccines”) and other ingredients in these “vaccines” — have been, and continue to be, designed to wreak as much havoc and damage on the human race as possible. This havoc and damage includes that done to the body’s natural immune system, its elements, mechanisms, and responses. Recall that the “descendant” modRNA COVID-19 “vaccines” use the original (lab-enhanced) SARS-COV-2 (COVID-19) virus modRNA that was present in the earlier versions of these “vaccines”, but in smaller amounts. Therefore, in one’s opinion, the potential exists for immune system damage in persons who take these “descendant” modRNA COVID-19 “vaccines.”

Until fairly recently, it was not known HOW, or the DETAILS behind WHY, the COVID-19 virus itself and the COVID-19 “vaccines” have such potential for havoc and damage — all that was beginning to present were, and are, the ADVERSE EFFECTS of the virus and especially of the “vaccines”: turbo-cancers; miscarriages; Bell’s Palsy; deaths; the Adverse Events of Special Interest listings of negative effects induced by BNT162b2 in the APPENDIX 1. cited above. It is now starting to become more clear as to what SPECIFIC elements likely used in the creation of both the SARS-CoV-2 virus itself, and in the development of the modRNA COVID-19 “vaccines.” Yours Truly will posit that one of these SPECIFIC elements is something that attacks and compromises at least one important component of the human body’s immune system: the antigen site of the human leukocyte protein DRB1 (HLA-DRB1.) It took time, effort, and large amounts of funding to investigate these SPECIFIC elements; to experiment with them to ascertain the damage that could be caused; then, to “insert” these elements into the SARS-CoV-2 virus itself, and, by extension, into the modRNA COVID-19 “vaccines.” And, as the passage of time obscures or obliterates “fingerprints” of the damage done by the COVID-19 “vaccines” in the “vaccinated” individual, the involvement of these “vaccines” may well become harder and harder to trace (even though the damage is continuing in the “vaccinated” person, since one of the mechanisms of said “vaccines” is to change the DNA of the person who takes them.) Below is Slide 14 from the Palmer, MD and Sucharit, MD, article regarding what the COVID-19 “vaccines” do to the “vaccinated” person’s body. Slide 14 shows how the Pfizer-BioNTech modRNA COVID-19 “vaccine” BNT162b2 changes the DNA of the “vaccinated” person:

The article is found here: https://doctors4covidethics.org/wp-content/uploads/2022/08/causality-article.pdf, “Vascular and organ damage induced by mRNA vaccines: irrefutable proof of causality”, by Michael Palmer, MD and Sucharit Bhakdi, MD, 18 August 2022.

Yours Truly will emphasize that it is of the utmost importance that all persons, COVID-19 “vaccinated” or not, have and maintain the highest degree possible of natural immune system health. A healthy diet is one of many ways to support and maintain a healthy natural immune system. Here is an article on this topic: www.medicalnewstoday.com/articles/322412, “The best foods for boosting your immune system”, by Lana Burgess, 10 July 2018. Among other ways to help the natural immune system are lifestyle changes, regular exercise, taking supplements, and addressing stress, as discussed here: www.healthline.com/nutrition/how-to-boost-immune-health, “9 Ways to Boost Your Body’s Natural Defenses”, by SaVanna Shoemaker, RDN, 1 April 2020. Yours Truly will add the opinion that avoiding unnecessary antibiotics and “certain injectables” are additional items to consider.

Peace, Good Energy, Respect: PAVACA
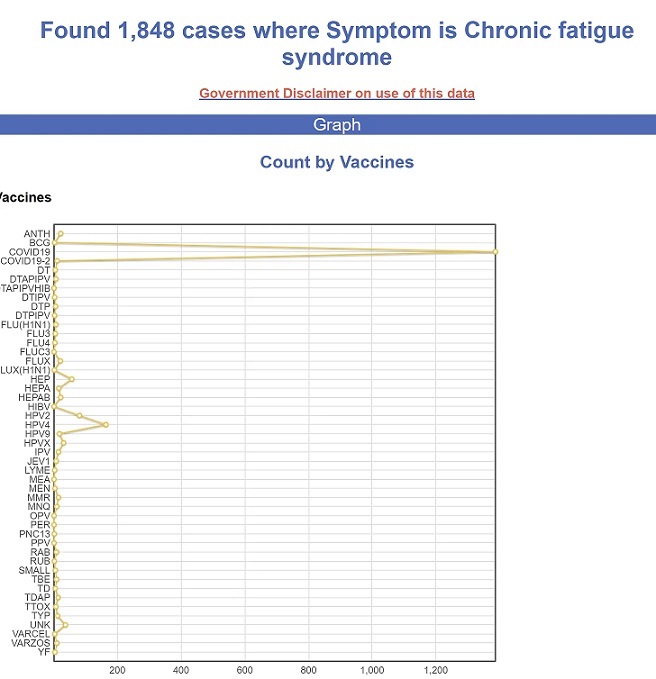
The HHS Gave the “Go-Ahead” to Use an H5N1″Vaccine”— But the AMA Just Issued New CPT Codes for an H5N8 “Vaccine”

The above image is of mass vaccination against smallpox in Paris in 1905. (Courtesy, Getty Images.)

Today’s post will trace what ** may be ** a “sleight-of-hand” that started out with Xavier Becerra, the Secretary of the United States government Department of Health and Human Services, giving the “Go-Ahead” for the use of the H5N1 Avian Influenza “vaccine”, AUDENZ, in anticipation of a potential “bird flu pandemic” in the United States; but, which since has been “transformed” into the American Medical Association just issuing new CPT codes for an Avian Influenza “vaccine” for a different strain, called H5N8. Meanwhile, the CDC / FDA / United States government, are all sending out warnings related to the H5N1 strain. Stay with Yours Truly, it gets even better — “Mais, mon Dieu!” — the twists and turns! This post is a kind of “snapshot” of the situation — it is an evolving issue.

For purposes of today’s post, the trail begins here: www.ernst.senate.gov/imo/media/doc/fowl_play_squeal.pdf, the letter that Sen. Jodi Ernst (R-Iowa) sent to USDA Secretary Tom Vilsack on 14 February 2024. In this letter, Sen. Ernst demands answers regarding United States government funding of what appears to be Gain-of-Function research experiments on Avian Influenza viruses; which experiments involve a scientist linked to the Chinese Communist Party. Yours Truly can find to date, no response from Sec. Vilsack to Sen. Ernst. A screenshot of Page 1 of her letter is below:

Yours Truly now turns to this: www.aha.org/news/headline/2024-07-23-hhs-broadens-emergency-declaration-facilitate-response-bird-flu-other-viruses-pandemic-potential, “HHS broadens emergency declaration to facilitate response to bird flu, other viruses with pandemic potential”, dated 23 July 2024, which “expanded” the 2013 amendment to the Federal Food, Drugs, and Cosmetics Act to now include “other viruses” that may have “pandemic potential.” The document, from HHS Secretary Xavier Becerra, specifically mentions three types of Avian Influenza strains: H1N1 (from 2009); H7N9 (from the 2013 amendment);, and H5N1 (from the 24 March 2024 USDA statement regarding H5N1 infections in dairy cows in Kansas and in Texas.) https://public-inspection.federalregister.com/2024-16247.pdf. Below is a screenshot from the AHA (American Hospital Association) press release:

And, for reference, here is the Congressional Research Service Legal Sidebar document related to what the HHS Secretary can “declare” under the PREP Act (including removing liability options), updated 21 July 2023: https://crsreports.congress.gov/product/pdf/LSB/LSB10730, “The PREP Act and COVID-19, Part 2: The PREP Act Declaration for COVID-19 Countermeasures.”

This was followed by a tweet from Robert Kennedy, Jr.: https://twitter.com/RobertKennedyJr/status/1816905031653675473, a screenshot of which follows:

Meanwhile, the USDA had already issued a press release regarding how dairy farmers can apply to receive expanded livestock assistance to compensate for milk production lost due to their cows infected with H5N1: www.usda.gov/media/press-releases/2024/06/27/usda-begin-accepting-applications-expanded-emergency-livestock, “USDA to Begin Accepting Applications for Expanded Emergency Livestock Assistance Program to Help Dairy Producers Offset Milk Loss Due to H5N1”, dated 27 June 2024.

Which was followed, in turn, by a CDC release regarding the government’s response to the current H5N1 Avian Influenza situation: www,cdc,gov/bird-flu/spotlights/h5n1-response-07262024.html; a screenshot from the release is below:

So, it would appear that the HHS gave the “go-ahead” for a kind of “EUA” regarding the use of the protein-subunit H5N1 “vaccine”, AUDENZ (a supply is already in the National Vaccine Stockpile); and, for the increased production of this “vaccine.” What follows is a “closer look” at AUDENZ. Yours Truly will begin with the FDA-issued Fact Sheet for healthcare providers for this “vaccine”: www.fda.gov/media/135020/download; three screenshots from the document are below. The first screenshot shows clearly that there was no Placebo group (Control/saline group) in at least two clinical trials for AUDENZ. The second screenshot shows clearly that no Toxicology studies were performed for AUDENZ. The third screenshot is Page 10 of the Fact Sheet.

Note this language in the first screenshot: “In both Studies 1 and 2, all SAEs appeared unrelated to study treatment.” This indicates at least two important details: One, that Serious Adverse Events (SAEs) did occur during at least two clinical trials of AUDENZ; and, Two, that these Serious Adverse Events were not considered to be related to the clinical trials for AUDENZ. This is the same type of language that Pfizer-BioNTech used regarding Serious Adverse Events that occurred during the (shortened and data-compromised) clinical trials for the company’s “flagship” COVID-19 modRNA “vaccine” BNT162b2. Note also that a “complete dose series” for AUDENZ is two separate doses of 0.5mL each, for all age groups age six months and up. AUDENZ uses an adjuvant (an ingredient that facilities the activities of the injectable) called MF59. MF59 is a squalene-based, oil-in-water adjuvant. The Safety Data Sheet for MF59 is here: https://file.medchemexpress.com/batch_PDF/HY-153206/MF59-SDS-MedChemExpress.pdf. The product is listed as “Not a hazardous product or mixture” in section 2.2 of this document. However, reading further down the same document, one finds all sorts of contradictory information in the sections on “First Aid Measures”, on “Handling and Storage”, on “Exposure Controls”, and more.

Note also the list of reported adverse events in section 6.2 of Page 10, above. These are same types of adverse events reactions to the Pfizer-BioNTech modRNA COVID-19 “vaccine”, BNT162b2, in the post-authorization report that this company gave to the FDA on 30 April 2021; and in reports to VAERS; and, which are listed within the FDA-issued Fact Sheet for Healthcare Providers for the “2023-2024 Formula COVID-19 Vaccine” by Pfizer-BioNTech (www.phmpt.org/wp-content/uploads/2022/04/reissue_5.3.6-postmarketing-experience.pdf; www.openvaers.com/; www.fda.gov/media/167211/download?attachment. Very troubling are the listings in section 6.2 of Page 10 above in the AUDENZ fact sheet for “convulsions”; “demyelination”; “encephalitis”; and, “Guillain-Barre’ syndrome.”

A blog post by Dr. Jessica Rose, PhD, on 27 June 2024, presents a summary of clinical trial for AUDENZ (NCT02839440), in which she proves that the fatality rate is 1/200 chances for AUDENZ: https://jessicar.substack.com/p/1200-chance-of-death-in-context-of, “1/200 chance of death in context of new bird flu injection – 5 times higher than placebo according to clinical trial.” NCT02839440 did have a Placebo control group, (Scroll down the blog post to the discussion of this clinical trial for AUDENZ.)

To date, Yours Truly can find no exact set of CPT Codes for AUDENZ. The closest item found is here: www.hhs.gov/guidance/document/flu-shot-coding-0; the listing is “Q2039 Influenza virus vaccination otherwise specified.”

AUDENZ is produced by CSL Seqirus, part of the much-larger CSL multinational drug company. Following is a JPG of the list of CSL offices and locations, sourced from: www.csl.com/:

The United States government awarded CSL Seqirus a contract to produce millions of doses of an Avian Influenza “vaccine” in May 2024: www.cslseqirus.us/news/csl-seqirus-announces-us-government-award-in-response-to-avian-influenza. The “vaccine” will be manufactured by the CSL Seqirus facility at Holly Springs, North Carolina. This facility was built in partnership with BARDA (Biomedical Advanced Research and Development Authority), a department of the United States government. The Avian Influenza “vaccine” that this facility will manufacture is “cell-based”, as opposed to “egg-based”; with a six-month “turnaround” for production: www.csl.com/we-are-csl/our-business-and-products/csl-seqirus/csl-seqirus-manufacturing-technologies. Below are two images from the article related to this facility:

Note that whatever Avian Influenza cell-based “vaccine” from the CSL Seqirus facility at Holly Springs will use the MF59 adjuvant. (By the way, MF59 is trademarked by Novartis AG, which was acquired by CSL.)

So far, it appears that the H5N1 strain of Avian Influenza is the one that the United States government is focused upon. However, here’s where the trail veers to another path.

Please refer back to the American Hospital Association press release above in today’s post. Note this language: “The amendment now applies to pandemic influenza A viruses and others with pandemic potential, such as the current H5N1 strain of bird flu…” (Italics, Yours Truly) In Yours Truly’s opinion, this is “a hole big enough to drive a truck through” — or, perhaps, another strain of Avian Influenza.

The following article beings to “lift the curtain” on what ** may ** really be going on — which, again in Yours Truly’s opinion, appears to be a kind of “sleight-of-hand”: www.naturalnews.com/2024-07-26-fda-grant-eua-mrna-bird-flu-vaccines.html, “Pandemic 2.0 ready to go: FDA to grant emergency use authorization (EUA) to mRNA bird flu shots, just like what happened with COVID“, by Ethan Huff. And, “right out of the gate”, the article begins with this:

But, wasn’t the “upcoming potential bird flu pandemic” supposed to be the H5N1 strain that the government is warning about? Where does the H5N8 strain come in? According to Wikipedia, the H5N8 strain of Avian Influenza is “is typically not associated with humans.” https://en.wikipedia.org/wiki/Influenza_A_virus_subtype_H5N8. Very few humans have contracted a case of H5N8; this virus strain predominates among wild birds. However, the mortality rate among wild birds infected with H5N8 is “at least 75%”, again according to the Wikipedia article above.

Now, turning to the American Medical Association’s issuing new CPT Codes for the use of an H5N8 “vaccine.” One media outlet that Yours Truly found has this: https://revcycleintelligence.com/news/ama-updates-cpt-code-set-for-avian-influenza-vaccines, dated 22 July 2024. Below is a screenshot from the article, with the new CPT codes:

Note that the American Medical Association owns the rights for the CPT codes. This means that the AMA gets a “royalty payment” every time a CPT code is used. The AMA notice regarding the CPT codes for H5N8 is here: www.ama-assn.org/press-center/press-releases/ama-announces-cpt-update-avian-influenza-vaccines, dated 19 July 2024. Below is a screenshot from the notice:

What’s going on here? The picture is, to say the least, somewhat “murky.” There are, however, a few potential clues. Among them is this: www.pennmedicine.org/news/news-releases/2024/may/penn-researchers-develop-experimental-mrna-avian-flu-vaccine, dated 23 May 2024. Note on the screenshot, below, from the article, the language regarding “a specific type of the H5N1 virus”; and, that animals other than wild birds were being used for the experiments:

Here is another clue, from 5 June 2024: www.idsociety.org/science-speaks-blog/u.s.-orders-4.8-million-doses-of-a-cell-based-adjuvanted-h5-vaccine-for-avian-flu-preparedness#/+/0/publishedDate_na_dt/desc/, by Daniel R. Lucey, MD, PhH, FIDSA. Below is a screenshot from this article:

Note the language regarding “pre-pandemic vaccine that is well-matched to the H5 of the currently circulating H5N1 strain,…” (bolding, Yours Truly)

A third clue is here: https://twitter.com/RenzTom/status/1816110256843264368; a screenshot of part of his tweet is below:

And, a fourth clue is here: https://clinicaltrials.gov/ct2/show/NCT05874713, a clinical trial that appears to be in the “wrapping-up” stages regarding testing an mRNA-based H5N8 “vaccine.” Below is a screenshot from the Clinical Trials webpage for this clinical trial:

Note the very low test subject enrollment (480 persons); the presence of the MF59 adjuvant in the H5N8 “vaccine” candidate used in the clinical trial; and, a “two-dose” series of “primary run” injections of the “vaccine” candidate, followed by a “booster shot” on Day 209 for the H5N8 “vaccine” candidate.

There are three other clinical trials of an H5N8 “vaccine” listed on the https://clinicaltrials.gov/ website: NCT02624219 (Completed); NCT05975840 (Active); and, NCT03014310 (Completed.) All of these clinical trials were/are Phase I or Phase I/II. None of them have a Placebo/saline control group. Each of them have fewer than 600 subjects (NCT02624219 had 275 test subjects.) Two of these three other clinical trials have the NIAID as the Sponsor.

What does all this mean? Is it possible that the current H5N1 “Avian Influenza infecting cattle, cows, and domesticated pets, in addition to poultry” situation, while it is indeed occurring, is also a sort of “Look, squirrel!” to distract from something that may be more dangerous?: from, perhaps, Gain-of-Function experiments on the H5N8 strain of the Avian Influenza (recall that this strain has a 75%+ mortality rate among the wild birds that it infects); plus, perhaps. the development of “vaccines” for this “perhaps-enhanced” H5N8 strain, which may include the millions of doses of an “Avian Influenza cell-based vaccine” that will be manufactured at the CSL Seqirus facility in North Carolina? In other words, “Pandemic 2.0”?

Good Energy, Peace, Respect: PAVACA

The 2024-2025 Formula COVID-19 “Vaccines”: Injection Dose #10

The above is a vintage image of mass vaccination. (Courtesy Google Images.)

This series on the disaster of the COVID-19 virus itself, and of the COVID-19 “vaccines”, is dedicated to the memory of Yours Truly’s cousin Bill, who “died suddenly and unexpectedly” in September 2023.

The origination of today’s post begins here: www.dossier.today/p/double-digits-biden-admin-tells-americans, “Double Digits: Biden Admin tells Americans that it’s soon time for their 10th Covid shot“, by Jordan Schachtel, 13 June 2024. (Mr. Schachtel wrote about the ninth COVID-19 “vaccine” injection here: www.dossier.today/p/dose-number-nine-cdc-panel-green, “Dose number NINE: CDC panel green lights yet another Covid mRNA shot“, 29 February 2024. The CDC recommended that persons over age 65 take another “booster shot” of either the Pfizer-BioNTech or of the Moderna “2023-2024 Formula COVID-19 Vaccine” of these manufacturers.) A person age 65 or older, if that person adhered to every CDC recommendation regarding taking a COVID-19 “vaccine” injection since December 2020 (when the FDA granted first Emergency Use Authorization (EUA) to Pfizer-BioNTech and to Moderna for these companies’ “flagship” modRNA COVID-19 “vaccines” (BNT162b2 by Pfizer-BioNTech; and, mRNA-1273 by Moderna), would have taken injection number nine starting on 28 February 2024.

Today’s post is long. There is a large amount of information to “unpack.” Stay with me here.

Below is an image from the FDA’s 13 June “updated” authorization announcement for the “2024-2025 Formula COVID-19 Vaccine”, the TENTH injection dose of the modRNA “vaccine” formula: www.fda.gov/vaccines-blood-biologics/updated-covid-19-vaccines-use-united-states-beginning-fall-2024.

Note the language regarding the “selection of a specific JN.1 lineage SARS-CoV-2 strain…” More about that later.

The trail behind the 5 June 2024 FDA announcement begins with the VRBPAC Briefing Document for the meeting held on 28 June 2022: www.fda.gov/media/159452/download, “FDA Briefing Document Vaccines and Related Biological Products Advisory Committee Meeting June 28, 2022.” It was at this meeting that the FDA “codified” the types of “strain composition recommendations” that the agency would use regarding “new versions” of COVID-19 “vaccines.” Yours Truly presents page 17, page 18, and page 19 of this document:

It appears that the FDA simply decided that it would be permissible for the agency to authorize a new COVID-19 “vaccine” strain composition along what, in Yours Truly’s opinion, may be called “very flexible” options. For example, the Pfizer-BioNTech XBB.1.5 COVID-19 “vaccine”, which was FDA authorized in the fall of 2023, had test results only from mouse testing prior to FDA authorization. Following are: The link to the Pfizer-BioNTech slide presentation about this “vaccine” to the CDC’s ACIP committee (Advisory Committee on Immunization Practices) meeting of 12 September 2023; and, an image of slide CC4 from this presentation. First, the presentation: www.cdc.gov/vaccines/acip/meetings/downloads/slides-2023-09-12/10-COVID-Modjarrad-508.pdf.

Second, slide CC-4 from the above presentation:

The XBB.1.5. Pfizer-BioNTech COVID-19 “vaccine” had only been given as a single injection to humans in the company’s clinical trial; a clinical trial which had only just begun prior to the ACIP meeting. Slide CC-5 of the presentation, the start of the company’s human trial of this “vaccine”, is below:

Slide CC-6 of the presentation has to do with the mouse studies of this “vaccine”, which were of longer duration.

Notwithstanding the above, the FDA authorized the use of the company’s XBB.1.5 COVID-19 “vaccine” on 11 September 2023 (in Yours Truly’s opinion, it appears that the ACIP meeting of 12 September 2023 was a “catch-up” formality.) It also appears (again, in Yours Truly’s opinion), that the FDA used a very loose interpretation of “Option 4” on page 18 of the FDA Briefing Document above in granting the EUA for this “vaccine”.

** Now, on to the latest “new version” of the COVID-19 “vaccines”, the “2024-2025 Formula COVID-19 Vaccines”, that the FDA authorized in June 2024.

The following linked items are important regarding background information related to this situation and to the FDA: First, the FDA document, stating that the agency would “align” its COVID-19 “vaccine” antigen composition to the recommendations of the World Health Organization’s TAG-CO-VAC recommendations: www.fda.gov/media/179139/download (the TAG-CO-VAC recommendation for the “2024-2025 Formula COVID-19 Vaccines” was to use the JN.1 strain); second, the FDA document regarding “considerations and recommendations” for the “2024-2025 Formula COVID-19 Vaccine” composition: www.fda.gov/media/179145/download; third, the FDA announcement of the 5 June meeting of its VRBPAC committee (Vaccines and Related Biological Products Advisory Committee.): www.fda.gov/advisory-committees/advisory-committee-calendar/vaccines-and-related-biological-products-advisory-committee-june-5-2024-meeting-announcement. From this last link, chick on “Event Materials” to see the slide presentations and other items that were discussed at this meeting.

Two important items from the “Event Materials” list: the FDA Briefing Document; and the VRBPAC roster for this meeting. First, the FDA Briefing Document: www.fda.gov/media/179003/download; and, second, the VRBPAC roster for this meeting: www.fda.gov/media/179225/download. The roster for the 5 June 2024 meeting has some “familiar” members and speakers: Paul Offit, MD; and Peter Marks, MD (director of CBER [Center for Biologics Evaluation the Research of the FDA]); and, among the “Temporary Voting Members”, are: Bruce Gellin, M.D., M. PH., the Chief of Global Public Health Strategy for the Rockefeller Foundation; and, Melinda Wharton, M.D., M. PH., Associate Director of Vaccine Policy of the CDC. (Italics mine)

The VRBPAC members voted unanimously to endorse the Pfizer-BioNTech, the Moderna, and the Novavax “2024-2025 Formula COVID-19 Vaccine” by these companies, based on the presentations of these companies’ representatives at the meeting. Yours Truly can find no registered human clinical trials performed in advance of the 5 June VRBPAC meeting by Pfizer-BioNTech, or by Moderna, or by Novavax, for any “2024-2025 Formula COVID-19 Vaccine”; that would indicate that any “clinical trials” were performed in these companies’ facilities on mice; and that any “human trials” were also performed in these companies’ facilities, prior to the meeting. The FDA then issued the agency’s original announcement of 7 June 2024: www.fda.gov/news-events/press-announcements/fda-roundup-june-7-2024; and, a screenshot from this announcement:

Note in particular “…the selection of a specific JN.1 lineage SARS-CoV-2 strain (e.g., JN.1. or KP.2) and expressed a strong preference for JN.1.” Here’s where it starts to “get interesting.”

First, on 12 April 2024 (well ahead of the 5 June VRBPAC meeting), Pfizer-BioNTech issues a statement regarding the company’s “taking reservations” for the coming “2024-2025 Formula COVID-19 Vaccine” (also, see the Pfizer-BioNTech presentation at the 5 June meeting, linked above): www.cvdvaccine-us.com/reservation. This is followed, after the meeting, by Moderna filing an application with the FDA for a “vaccine” to target the JN.1. COVID-19 strain (also, see the Moderna presentation at the 5 June meeting, linked above): https://investors.modernatx.com/news/news-details/2024/Moderna-Files-FDA-Application-for-the-JN.1-Targeting-COVID-19-Vaccine/default.aspx; then, Novavax files with the FDA for that company’s version (also, see the Novavax presentation at the 5 June meeting, linked above): https://ir.novavax.com/press-releases/2024-06-14-Novavax-Submits-Application-to-U-S-FDA-for-Updated-Protein-based-2024-2025-Formula-COVID-19-Vaccine.

But then, “something happens”, and the FDA suddenly makes a large “about-face” and switches its “2024-2025 Formula COVID-19 Vaccine” choice to the KP.2 strain on 13 June 2024: www.fda.gov/vaccines-blood-biologics/updated-covid-19-vaccines-use-united-states-beginning-fall-2024. This is the “second” announcement, which was cited at the beginning of today’s post.

What was it that happened? Part of the answer lies in the fact that the NIH and Moderna co-own the patents (and, therefore, share the royalties) for the Moderna “flagship” modRNA COVID-19 “vaccine”, mRNA-1273. This agreement would extend to “descendant clone COVID-19 vaccines” by Moderna. www.citizen.org/article/modernas-mrna-1273-vaccine-patent-landscape/. The NIH’s Dale and Betty Bumpers Vaccine Research Center (part of NIAID — which Dr. Anthony Fauci led from November 1984 until his retirement in December 2022) and Moderna co-developed mRNA-1273. https://covid19.nih.gov/news-and-stories/nih-vaccine-research-center; a screenshot from the article is below:

The other part of the answer is that Moderna was already developing a KP.2 strain COVID-19 “vaccine” for 2024-2025. This, and the FDA’s decision to shift away from the JN.1 strain to the KP.2 strain, are described in this post at Sasha Latypova’s blog: https://sashalatypova.substack.com/p/all-roads-lead-to-resilience, “All Roads lead to Resilience. FDA is removing competitors for the Pentagon & CIA’s baby…Moderna”, 23 June 2024.

The FDA’s “about-face” announcement regarding the switch from the JN.1 strain to the KP.2 strain was also covered here: www.contagionlive.com/view/fda-advises-manufacturers-to-consider-kp-2-strain-for-covid-19-vaccines, 14 June 2024, by Sophia Abene. Below is a screenshot from this article:

However, there’s yet another detail in play here, regarding the FDA’s switch, “based on evaluation of the most recent circulating strains of COVID-19”, from JN.1 to KP.2 — the CIA and the Pentagon. Here is a screenshot from Sasha Latypova’s Substack article:

Here is the report, linked from the Latypova blog article cited above, that describes the CIA-linked company, “National Resilience”, or “Resilience”, that manufactures the RNA for the Moderna modRNA line of COVID-19 Omicron “vaccines”: https://unlimitedhangout.com/2022/08/investigative-reports/rna-for-modernas-omicron-booster-manufactured-by-cia-linked-company/, by Whitney Webb, 17 August 2022. Below is a screenshot image from this blog article:

And here is story on this “interesting development”, from Resilience: www.businesswire.com/news/home/20210908005443/en/Resilience-to-Manufacture-mRNA-for-Moderna’s-COVID-19-Vaccine, 8 September 2021. Note that per this “multi-year contract”, Resilience manufactures the mRNA for the Moderna COVID-19 “vaccines” at this Canadian facility. Resilience was founded in 2020.

But wait, there’s more! Resilience lists multiple “partners”, such as the Mayo Clinic. The company also, apparently, has a “partnership” with the United States Army’s Joint Program Executive Office for Chemical, Biological, Radiological and Nuclear Defense https://resilience.com/learn/partnerships. Below is a screenshot from this website:

The website link in the screenshot above is broken. Here is the Army’s website on this: wwwt2.army.mil/T2-Laboratories/Designated-Laboratories/Joint-Program-Executive-Office-for-Chemical-Biological-Radiological-and-Nuclear-Defense/. Note: this link may or may not work. One will need to do a search for “Joint Program Executive Office for Chemical, Biological, Radiological and Nuclear Defense” to see links to this department of the United States Army. One such link: https://globalbiodefense.com/directory/name/joint-program-executive-office-for-chemical-biological-defense-jpeo-cbd/.

It appears, then, in Yours Truly’s opinion, that the FDA was perhaps “reminded” of the”details” regarding the NIH-Moderna co-ownership (and royalties – sharing) agreement related to Moderna’s modRNA COVID-19 “vaccines”; and, the role of the CIA-Pentagon-National Resilience (aka Resilience) in manufacturing the mRNA used in the Moderna COVID-19 Omicron “booster vaccines” — and the KP.2. strain is indeed a “descendant strain” in the Omicron lineage (as is the JN.1 strain.) Hence, the FDA’s 2024-2025 COVID-19 “vaccine” strain “sudden switch” announcement of 13 June 2024, only one week after the agency gave the nod to the JN.1 strain.

In Yours Truly’s opinion, it is statistically, medically, and ethically impossible for a new vaccine (let alone any COVID-19 “vaccine”) to be developed; tested (on lab animals, then on human subjects); the test data thoroughly collated and analyzed for “safety and efficacy” on both lab animals and on human subjects; then, which data is presented to the CDC / FDA for consideration; then, these agencies doing their own “due diligence” research; then, and only then, being granted an EUA by the FDA; then, and only then, manufactured for use in humans — in a time span of fewer than three to five years, let alone within a time span of only a few months. It appears, again in Yours Truly’s opinion, that the CDC and the FDA are playing “fast and loose” with the health and safety of the people who choose (or will be “mandated”) to take the “2024-2025 Formula COVID-19 Vaccine.” And, also, that “other entities” are in play here to perhaps “influence” decision making by these agencies.

All of above is in addition to the fact that the COVID-19 “vaccines” (actually, gene therapy injections) have caused, are causing, and will cause, multiple health issues, serious adverse reactions, and deaths, in those who are “vaccinated.” Just two of the most recent discoveries: One, the COVID-19 “vaccines” can cause brain damage, an article by Dr. William Makis: www.globalresearch.ca/brain-damage-covid-19-mrna-vaccines/5861012, “Brain Damage Caused by COVID-19 mRNA Vaccines”, 26 June 2024. Below is a screenshot from Dr. Makis’ article:

The second most recent discovery, that the COVID-19 “vaccines” reduce life expectancy (even in “all-cause” analysis) among COVID-19 “vaccinated” persons, by Dr. Peter A. McCullough: https://petermcculloughmd.substack.com/p/breaking-publication-a-critical-analysis, “BREAKING Publication — A Critical Analysis of All-Cause Deaths during COVID-19 Vaccination in an Italian Province”, 1 July 2024. The peer-reviewed paper is here: https://doi.org/10.3390/microorganisms12071343, “A Critical Analysis of All-Cause Deaths during COVID-19 Vaccination in an Italian Province”, Marco Alessandria, et al., published 30 June 2024. Below is a screenshot from the Conclusions section of this paper:

In Yours Truly’ opinion, it is apparent at “half a glance” that the COVID-19 “vaccines” (actually, gene therapy injections) must be completely withdrawn for human use until these products have been fully investigated, and then re-designed, before being re-introduced for human use; and, that there is no “co-ownership” or sharing of royalties between a government agency and a COVID-19 “vaccine” manufacturer; and, that there is no involvement of the United States military in the development or manufacture of such products.

Peace, Good Energy, Respect: PAVACA


The AMA EdHub: Window to “Establishment Medicine”

The above image is from the Textbook of Anatomy and Physiology, by Kimber, Gray, and Stackpole. Published by The Macmillan Company; eleventh edition, 1944. (Image courtesy of Laurel Leaf Farm.)

This post, part of a series on the disaster of COVID-19 and the COVID-19 “vaccines”, is dedicated to the memory of Yours Truly’s cousin Bill, who “died suddenly and unexpectedly” in September 2023. Today’s offering will speak to what might be called a “tangential” issue: the American Medical Association (the AMA.) Yours Truly will make it clear at the outset that today’s post is not to be construed as a “hit piece” on the AMA; also, that there are likely many members of the AMA who are not “beholden” to blindly accept everything that the AMA publishes. The point of today’s piece, in one’s opinion, is that the current AMA apparently sees itself as a sort of “arm” of “establishment medicine” (in other words, of the FDA and the CDC); in addition to becoming an organization that advocates what may be called “medico-political” viewpoints. First, before discussing the AMA Edhub, some items about the organization:

It is fair to posit that the American Medical Association (also referred to as the AMA) is the largest and most powerful medical doctor organization in the United States. The AMA has also become, arguably, the most powerful medical organization lobbyist in the United States House of Representatives and the United States Senate.

The American Medical Association was founded in 1847. In the year 2022, it had 271,660 members, and $493,147,829 in revenue (per Wikipedia: https://en.wikipedia.org/wiki/American_Medical_Association). Further information on the history of the organization is found here: www.ama-assn.org/about/ama-history. The AMA does not publish a membership directory as of the year 2021: https://myama.my.site.com/s/article/Does-the-AMA-have-a-member-directory, stating the following: “The privacy of our customers’ [presumably, this means “members'”] data is something we take very seriously.” On the other hand, the 2022 census of the Federation of State Medical Boards listed a total of 1,044,734 licensed physicians in the United States (www.fsmb.org/advocacy/news-releases/fsmb-physician-census-identifies—1044734-licensed-physicians-in-u.s/). This means that 26% (271,660) of the licensed physicians in the United States belong to the AMA. (Side note: members of the AMA have “exclusive discounts” towards purchasing new Mercedes-Benz and Volvo cars: www.ama-assn.org/member-benefits/personal-member-benefits-discounts/auto-transportation-discounts).

The American Medical Association is a “heavy-spender” lobbyist to the United States federal government, spending at least $15 million per year in this effort since 1998: www.influencewatch.org/non-profit/american-medical-association/ (this article also has a history of the AMA, the organization’s views on healthcare policies, and so forth); in the year 2022 alone, the AMA spent $21,060,000 on federal government lobbying, per Open Secrets: www.opensecrets.org. A screenshot of the Influence Watch report on the AMA is below. Note that the AMA owns the exclusive rights to the medical expenditure reimbursement codes system for Medicare and Medicaid (the CPT codes.) This entails the payments of “rights and royalties” to the AMA. For further information, please refer to: https://microwize.com/why-do-i-have-to-pay-a-fee-to-use-cpt-code/, 14 December 2022.

The AMA, as can be inferred from the above screenshot, is also involved with the FDA and the CDC. Two examples: the AMA’s lobbying efforts with these agencies regarding advocacy for COVID-19 programs of various types, along with other advocacy efforts: www.ama-assn.org/delivering-care/public-health/covid-19-amas-recent-and-ongoing-advocacy-efforts (1 June 2022 report); www.ama-assn.org/topics/coronavirus-vaccines; and, www.ama-assn.org/delivering-care/public-health/covid-19-2019-novel-coronavirus-resource-center-physicians (updated 17 April 2024.)

The AMA has a “membership dues schedule”, ranging from $20 for a 1-year medical student membership, through a $420 per year dues fee for a “Regular practice” physician who belongs to the AMA. And, there are other types of membership available (corporate and e-membership.) www.amanet.org/membership/. There are other types of corporate and institutional memberships available through the AMA Foundation, also called the “Roundtable.” (https://amafoundation.org/donors/corporate-donors/). A screenshot of the “Silver Level” corporate donor list to the AMA is below (the “Silver Level” requires a $30,000 contribution to the AMA Foundation, presumably paid each year by each donor company):

Two other areas of AMA effort are in physician Continuing Education and in publishing. Members of the AMA who are licensed medical doctors can fulfill their Continuing Education accreditation through courses offered by the organization. These courses are offered via various methods: www.ama-assn.org/topics/contuning-medical-education. The AMA also publishes a journal, known as JAMA (Journal of the American Medical Association): https://jamanetwork.com/. The website is open-access, and there are hundreds of peer-reviewed articles from thirteen different JAMA specialty journals available for public reading for several months after articles are published. As might be expected, the AMA advocates for what might be called “establishment medicine” — for example, championing FDA-authorized or FDA-approved treatments and drugs for COVID-19 infection.

Yours Truly will include part of the Abstract (below) of a recent paper published in JAMA, regarding people who mistrust “establishment medicine” (in other words, they may mistrust FDA-authorized or FDA-approved) treatments for COVID-19. This paper, in Yours Truly’s opinion, demonstrates the AMA’s official attitude towards those who question or refuse “establishment medicine” treatment of COVID1-19 and pursue other, alternative treatments — that these people are “being misled” by “misinformation” and may use that “misinformation” to avoid “health-promoting behaviors.” The paper is found here: https://jamanetwork.com/journals/jama-health-forum/fullarticle/2809985, “Misinformation, Trust, and Use of Ivermectin and Hydroxychloroquine for COVID-19”, Roy H. Perlis, MD, et al., published 29 September 2023. Dr. Perlis is Associate Editor of JAMA Network Open.

It appears that the AMA is “leading the charge” on “medico-political” topics, such as “climate change”, DEI (Diversity, Equity, and Inclusion), “equity of access to care” for illegal immigrants, “gender equity”, and more.

This leads to the AMA EdHub discussion.

The AMA EdHub website features online courses and Continuing Education (CME) fulfillment modules for physician members (https://edhub.ama-assn.org). These courses and modules are presented in various ways: webinars; video and/or audio courses; papers to be read; and so on. One does not have to be a member of the AMA in order to access and read many of the courses and modules; in fact, the AMA states that, “The AMA EdHub is open to anyone.” (https://education.ama-assn.org/help/, the “FAQ’s” section); interested persons simply open an account. However, only licensed physicians who belong to the AMA can fulfill their CME credits using the AMA EdHub. https:///edhub.ama-assn.org/pages/ama-cme, section “Target Audience“; and, www.ama-assn.org/member-benefits/personal-member-benefits-discounts/ama-ed-hub-member-benefits.

On other hand, the AMA EdHub provides a good “snapshot” of the current modes of thought in “establishment medicine”, as well as current trends in treatment and in the teaching of medical school students, among other topics. For example, there are CME modules and online courses related to DEI; to “anti-racism in medicine”; “equitable patient care”; and other what may be termed “medico-political” topics areas. Here is a link to one such example, a CME module: https://edhub.ama-assn.org/clinical-problem-solvers-antiracism-podcast/audio-player/18843339, “Episode 23 – Anti-Blackness, Anti-Fatness, and Food Shaming”, 9 January 2024. This somewhat over one hour audio module (with a Transcript that can be read) can be used, after the physician takes the Quiz, to earn one CME credit. The Learning Objectives listed for this module are: “1. Explain how anti-fatness and food shaming culture in the US is rooted in anti-Blackness 2. Describe the intersection of policing and the court systems with anti-fatness and food shaming 3. Identify ways to navigate clinical interactions with patients while respecting them and affirming their experiences with food and fatness.”

The AMA Edhub also has a department devoted to “health equity” — https://edhub.ama-assn.org/ama-center-health-equity. From the main page of the link: “Education from AMA Center for Health Equity AMA’s online education to empower individuals ad organizations, in healthcare and beyond, in advancing racial justice and equity.”

It appears that one area of particular emphasis in the AMA Center for Health Equity has to do with “gun violence prevention” — through “education” of medical students, practicing physicians, and patients — and working with the United States Congress. Here is a link to a recent video CME fulfillment presentation from the AMA Center for Health Equity: https://edhub.ama-assn.org/ama-center-health-equity/video-player/18867531, “Prioritizing Equity: Embracing Public Safety and Health for Improved Firearms Violence Prevention“, 2 April 2024. This video presentation has a Transcript that can be read. It appears, from reading the Transcript, that the AMA’s position on “gun violence prevention” goes beyond working through the criminal justice system. According to Dr. Megan Ranney, MD, one of the speakers interviewed on the video, “…it’s about separating someone from the potential to access a firearm at that moment of desperation, anger, impulsivity, hopelessness.” Dr. Ranney also states that, “…the amount of violence that youth are exposed to in urban neighborhoods far outstrips the amount of violence that people are exposed to in the military.” (Italics added)

The AMA EdHub has other areas of interest that offer online CME courses for AMA physician members, among them: promoting “race-conscious” admissions to higher education, including to medical schools: and, courses from The Fenway Institute, an organization that advocates for LGBTQIA+ and Transgender issues and persons. Here are links to examples of these AMA EdHub areas of interest: https://edhub.ama-assn.org/ama-center-health-equity/audio-player/18868328, 2 April 2024; “The SCOTUS Affirmative Action Ruling The Cost to the Physician Workforce and Historically Minoritized Communities (with a Transcript that can be read); and, https://edhub.ama-assn.org/fenway-institute-edu/video-player/18638799, 2 September 2021, “Affirming Care for People with Intersex Traits.”

In Yours Truly’s opinion, understanding the AMA EdHub is an important part in understanding how the AMA works to influence healthcare treatment practices, healthcare policies; and the United States Congress, through the AMA’s lobbying efforts.

Peace, Good Energy, Respect: PAVACA

The Elephant in the Room: Shedding of the COVID-19 Virus Itself and of the COVID-19 “Vaccines”

The above image is courtesy of Google Images.

This series on the COVID-19 virus and the COVID-19 “vaccines” is dedicated to the memory of Yours Truly’s cousin Bill, who “died suddenly and unexpectedly” in September 2023.

Human beings shed items from their bodies every day: hair (and dandruff); tears; nasal mucus when blowing the nose or in sneezing; saliva; urine and feces; dead skin cells; sweat — among other things. They also shed particles of viruses — for example, of the “common cold” virus. They shed particles of vaccines — for example, of the Zaire ebolavirus vaccine, ERVEBO (www.fda.gov/media/133748/download, the Package Insert for ERVEBO; please refer to section 12.3 Pharmacokinetics, subsection Shedding). Today’s post will discuss the shedding of the COVID-19 virus itself, and of the COVID-19 “vaccines” (including the “2023-2024 Formula COVID-19 Vaccines.”) For purposes of today’s presentation, the trail begins with some details about how the COVID-19 virus itself works. Note: the knowledge base of exactly what is contained in the mRNA and spike protein of the original Wuhan Hu1 SARS-CoV-2 (COVID-19) virus; and, exactly what is contained in the modRNA and the other elements within the COVID-19 “vaccines”, is an evolving situation.

The following article, published on www.statnews.com/ on 10 April 2020 (before any COVID-19 “vaccine” had been authorized or approved for use), is about how the SARS-CoV-2 virus itself enters into human cells via the ACE2 receptors www.statnews.com/2020/04/10/coronavirus-ace-2-receptor/, “The coronavirus sneaks into cells through a key receptor. Could targeting it lead to a treatment?”, by Kate Sheridan.) From the article: “In a healthy person, the ACE2 receptor chops up two forms of a protein called angiotensin to keep blood pressure stable, among other things. SARS and the novel coronavirus, however, use the receptors to infiltrate cells,…The virus can latch onto ACE2 and sneak inside, replicating itself inside the cell and then wreaking havoc throughout the body.” According to Wikipedia, ACE2 receptor cells, found in the intestines, kidney, testes, gallbladder, and heart, regulate blood pressure in the body. However, the SARS-CoV-2 spike protein damages the endothelium by “downregulating” the ACE2 receptor ability. The endothelium is a layer of cells lining the interior surfaces of blood vessels and of lymphatic vessels.

A paper in Nature was published on 10 May 2021 of a study of 31 SARS-CoV-2-infected patients in Italy. The data were collected between November 2019 (from seven healthy controls) and from 31 COVID-19 infected patients (hospitalized), prior to publication in May 2021. The treatments administered to the infected patients were Tocilizumab (an immunosuppressant drug), and Anakinra (a drug that treats Rheumatoid Arthritis), as no COVID-19 “vaccine” had yet been authorized or approved for use. The paper is found here: https://pubmed.ncbi.nlm.nih.gov/33972535/, “Identification and characterization of a SARS-CoV-2 specific CD8+T cell response with immunodominant features”; Pia Kvistborg, et al. (click on the DOI link for the full paper.) The authors of the paper were investigating the connection between the COVID-19 virus and its effects specifically on the CD8+ cells of the human body. What they found was quite interesting: the COVID-19 virus itself does indeed target many of the epitopes related to the CD8+ cells of the human immune system (an epitope is part of an antigen that is “recognized” by the immune system via antibodies, B cells, and T cells.)

Another paper, published on 31 July 2023, investigated the effects of the SARS-CoV-2 virus on the CD4 cells of the human body (https://doi.org/10.7554/eLife.84790, “SARS-CoV-2 uses CD4 to infect T helper lymphocytes”, Marcelo A. Mori, et al. Among the findings of this paper is that the SARS-CoV-2 virus attacks the ACE2 receptors of the CD4 lymphocyte cells.

Therefore, it was known as early as April 2020 that the SARS-CoV-2 (COVID-19) virus itself attacks and damages important cells and mechanisms of the body of an infected person. What about the COVID-19 “vaccines?” It may be assumed that, since the COVID-19 “vaccines” contain the mRNA and spike protein elements of the original Wuhan Hu1 virus, these same elements are also contained in the COVID-19 “vaccines” — in addition to lab-engineered modifications to the mRNA, plus lipid nanoparticles and certain excipients (for lists of the excipients, please see: https://doi.org/10.1016/j.jnma.2022.08.003, “Pfizer-BioNTech (BNT162b2), Moderna (mRNA-1273) COVID-19 vaccines and hypersensitivity reactions”, Hannah N. Haq, et al., published 29 October 2022.) In the “Trougakos, et al. paper” of 20 April 2022, it was presented that the COVID-19 “vaccines” bind the spike protein to the ACE2 receptors in the body and contribute to what the paper calls “vaccination-related AEs” (Adverse Events.) The paper is found here: https://doi.org/10.1016/j.molmed.2022.04.007, “Adverse effects of COVID-19 mRNA vaccines” the spike hypothesis”, Ioannis P. Trougakos, et al. Figure 1 from the paper, below, shows how the lipid nanoparticles (LNPs) in the COVID-19 “vaccines” move the spike protein and its modRNA around in the cell structure of the “vaccinated” person’s body. Note the “Furin cleavage-S1 shedding” on the figure:

Yours Truly now turns to “The Elephant in the Room” — the phenomena of shedding of the COVID-19 virus itself; and the shedding of elements of the COVID-19 “vaccines.” The first aspect, the shedding of the COVID-19 virus itself, is presented and discussed here: https://wmcresearch.substack.com/p/new-onset-autoantibodies-after-any, “New Onset Autoantibodies After Any Exposure to the Spike Protein of SARS-CoV-2”, by Walter M Chesnut. This article discusses, among other items, a paper published in February 2024, https://doi.org/10.1101/2024.02.15.24302857, “Prevalent and persistent new-onset autoantibodies in mild to severe COVID-19”, Peter Nilsson, et al. Yours Truly presents Figure 1 from this paper, an example of epitope mapping in neuro-COVID patients:

An autoantibody is an antibody made by the immune system that can attack one (or more) of the body’s own proteins; Graves’ Disease is an example of a condition induced by autoantibodies.

The Cleveland Clinic recognized, in 2022, that elements of the COVID-19 virus can be shed into the air: https://my.clevelandclinic.org/health/diseases/21214-coronavirus-covid-19, “Coronavirus, COVID-19”, dated 3 January 2022. In this article, people were warned away from “close contact” with COVID-19 infected persons. “Close contact”, in the article, was defined as, “…being within 6 feet of an infected person from a cumulative total of 15 minutes or more over a 24-hour period.” The article also states that the virus can be spread via “respiratory droplets released into the air when an infected person coughs, sneezes, talks, sings or breathes near you.” (Yours Truly is aware that the “stay 6 feet away rule” is arbitrary, considering that aerosols [sneezes, for example] travel a lot farther than six feet and also at quite high speeds.)

So, it is known that the COVID-19 virus itself can be shed by an infected person into the air, and by an infected person onto another person. What about the shedding of elements and particles of the COVID-19 “vaccines” by a “vaccinated” person? This aspect is fueling new research that is being studied, compiled, and published (again, another piece of the evolving knowledge base regarding the virus and the “vaccines.”) For purposes of today’s post, Yours Truly will present the current findings of two such researchers: Dr. Ana Mihalcea, MD, PhD; and Dr. Pierre Kory, MD, co-founder of COVID-19 Critical Care Alliance (FLCCC); a paper co-authored by Stephanie Seneff, PhD; and a paper co-authored Jessica Rose, PhD, and Peter A. McCullough, MD, et al.

Dr. Mihalcea has conducted several darkfield microscopic investigations into the shedding of COVID-19 “vaccine” elements and particles from “vaccinated” persons. One of her blog articles about her findings is here: https://anamihalceamdphd.substack.com/p/darkfield-live-blood-analysis-c19, “Darkfield Live Blood Analysis C19 Unvaccinated Blood. C19 Vax Shedding And Environmental Exposure Has Not Slowed Down”, published 23 January 2024. The image below is from her blood analysis of an “unvaccinated” person who was in close contact with a COVID-19 “vaccinated” person. Note the presence of unusual structures in this person’s blood:

Another of Dr. Mihalcea’s articles on her findings is here: https://anamihalceamdphd.substack.com/p/environmental-filaments-uv-light, “Flourescent Filaments Coming Out of C19 Vaccinated Individuals Skin Glowing Under UV Light: Darkfield Microscopy”, published 28 January 2024. This article discusses what appear to be filaments of luciferase that were “shed” from COVID-19 “vaccinated” persons onto their skin. For further reference regarding the presence of luciferase in the COVID-19 “vaccines,” please see: www.nature.com/articles/s41541-023-00751-6, “Effect of mRNA-LNP components of two globally-marketed COVID-19 vaccines on efficacy and stability”, Lizhou Zhang, et al. Section Results of this paper discusses the experiments with the firefly luciferase contained in the Pfizer-BioNTech COVID-19 “vaccine” LNP, ALC-0315, as compared to the firefly luciferase contained in the Moderna COVID-19 “vaccine” LNP, SM-102.

Dr. Pierre Kory is investigating the COVID-19 “vaccines” shedding phenomenon and is writing about it in his Substack. Here is his compendium post on the issue: https://pierrekorymedicalmusings.com/p/mrna-vaccine-shedding-of-spike-protein, “mRNA Vaccine Shedding Of Spike Protein: State Of the Scientific and Clinical Evidence”, published 20 February 2024. There is a searchable PDF of the report here: https://covid19criticalcare.com/wp-content/uploads/2024/02/Shedding-of-COVID-mRNA-Vaccines-A-review-of-evidence-2024-02-03.pdf. Yours Truly urges interested persons to read through this report, especially starting on Page 15, SUMMARY OBSERVATIONS OF OVER 1000 CLINICAL REPORTS OF SHEDDING; and continuing on Page 23, CLINICAL GUIDANCE. The entire report has many “clickable” underlined hyperlinks to documents, other reports, clinical trials, and so on. His COVID-19 “vaccines” shedding series begins here: https://pierrekorymedicalmusings.com/p/shedding-of-covid-mrna-vaccine-components, “”Shedding” of Covid mRNA Vaccine Components and Products From The Vaccinated to the Unvaccinated – Part 1″, published 1 November 2023 (there are links to the other eight parts of the series at the end of Part 1.)

Stephanie Seneff, PhD, and Greg Nigh published a paper in May 2021 on multiple possible “unintended consequences” of the COVID-19 “vaccines.” The paper is found here: International Journal of Vaccine Theory, Practice, and Research 2(1), May 10, 2021, pages 38 – 79, “Worse Than the Disease? Reviewing Some Possible Unintended Consequences of the mRNA Vaccines Against COVID-19.” Yours Truly presents part of page 62 of the paper:

Yours Truly now turns to the peer-reviewed paper published in Cureus on 24 January 2024, and which paper was suddenly retracted by Cureus on 26 February 2024: www.cureus.com/articles/203052-covid-19-mrna-vaccines-lessons-learned-from-the-registrational-trials-and-global-vaccination-campaign#1/, “COVID-19 mRNA Vaccines: Lessons Learned from the Registrational Trials and Global Vaccination Campaign”, M. Nathaniel Mead, Russ Wolfinger, Jessica Rose, Kris Denhaerynck, Steve Kirsch, Peter A. McCullough. (Cureus and its parent company, Springer / Nature have since been sued for $250 million in damages by Steve Kirsch on behalf of himself and the other co-authors of the paper, as it was not retracted by the authors themselves; nor was it retracted with their consent.) The paper presents and discusses the flawed, incomplete, and data-manipulated COVID-19 “vaccine” clinical trials. It also states the following, per the screenshot from the paper, below:

So, now it is known that both the COVID-19 virus itself, and elements of the COVID-19 “vaccines”, do shed. What are people, “vaccinated” and, especially, “unvaccinated” people, to do — stay away from others, including “vaccinated” friends and family? Go back to wearing the (mostly useless, except for certain healthcare settings, etc.) masks, the disposable gloves, the washing of clothes in hot water, etc.? Go back to “self-limiting” exposure to places like grocery stores, healthcare providers’ offices, and so on? Avoid all “unnecessary” travel? Are all people supposed to consider themselves to be COVID-19 “vaccinated,” either via injection or via shedding of COVID-19 “vaccine” elements by “vaccinated” persons?

The following is not professional medical or healthcare advice — they are only ideas and possible suggestions. In addition, since the investigation of COVID-19 virus shedding and COVID-19 “vaccines” shedding is an another evolving aspect of the entire situation, Yours Truly is not, and cautions against, “leaping to certain conclusions,” although ongoing research is uncovering important things; therefore, the following are presented as personal opinions for all people, “vaccinated” and “unvaccinated”, to consider:

It is important to make sure that one’s own general health and natural immune system are brought up to, and maintained, in the best shape possible: to avoid / prevent infection by the COVID-19 virus itself, and / or to be impacted by shedding of the COVID-19 virus from infected persons; and / or to be impacted by the shedding of COVID-19 “vaccines” elements by “vaccinated” persons. This could possibly include dietary changes, vitamins and supplements as needed, and so on. Note: Speak with a healthcare provider regarding possible interactions between certain supplements and any prescription drugs that a person may be taking: for example, Nattokinase can interact with prescription blood thinners or with aspirin.

It is important that regular mild to moderate exercise, especially walking, be undertaken for 30 minutes a day, at least five days of the week. This could also include activities such as gardening, Yoga, and so on.

It is important that techniques to reduce stress and eliminate unnecessary stressors be part of one’s life and practiced daily.

It is important to have and keep a positive connection to the Almighty God, or to whatever Benevolent Divine Force that one believes in.

It is important to follow a COVID-19 prevention / treatment / spike protein detox program — by COVID-19 “vaccinated” persons; by “unvaccinated” persons; and/or, by persons who have been infected by COVID-19 and have recovered — such as the programs outlined, for example, at COVID-19 Critical Care (FLCCC Alliance https://covid19criticalcare.com/); or, through working with a medical professional who believes in such a program; or, through working with a reputable Naturopathic Doctor, herbalist, Traditional Chinese Medicine or Ayurvedic Medicine practitioner.

It is important that COVID-19 “vaccinated” persons do their own due diligence regarding the dangers of the COVID-19 “vaccines”, and decide for themselves whether or not to continue taking them.

It may be prudent, if a person feels “coming down with” an illness, or doesn’t feel “up to par,” to politely decline attendance at activities or events that were previously planned, in order to stay home and take care of oneself, and/or to seek medical care.

For some further information on the truth about the COVID-19 virus itself, and about the COVID-19 “vaccines”, please see:

www.theqtree.com/2024/02/01/an-open-letter-to-medical-professionals-who-took-the-covid-19-vaccines/

www.theqtree.com/2023/12/14/pavacas-top-12-list-of-damages-the-covid-19-vaccines-can-do-to-the-recipient/

www.theqtree.com/2024/01/04/the-deagel-report-u-s-population-reduction-of-68-5-by-2025/

www.theqtree.com/2023/11/29/the-covid-19-vaccines-pave-the-way-for-turbo-cancers-and-a-note-on-the-virus-itself/

“Speak the truth in humility to all people.” (Sioux proverb)

“And you shall know the truth, and the truth shall make you free.” John 8:32 (NKJV)

Peace, Good Energy, Respect: PAVACA

An Open Letter to Medical Professionals Who Took the COVID-19 “Vaccines”

The above image is a photo from the article, “The new COVID boosters: What doctors and patients need to know”, published online by the Association of American Medical Colleges on 14 September 2023 (www.aamc.org/news/new-covid-boosters-what-doctors-and-patients-need-to-know).

This series of posts regarding the ongoing issues of COVID-19 and the COVID-19 “vaccines” is dedicated to the memory of Yours Truly’s cousin Bill, who passed away “suddenly and unexpectedly” in September 2023. Today’s post is addressed to medical professionals who had any COVID-19 “vaccines” (in reality, gene therapy injections) injected into their bodies since 11 December 2020. This post is not “accusatory” in nature: Yours Truly is curious. One will make it clear at the outset that there are vaccines and other injectables that are useful: For examples, the Rabies vaccine and the injectable form of Heparin. One will also make it clear that the following questions regarding the modRNA COVID-19 “vaccines” are not “tin-foil hat” or “conspiracy theory” in nature — all of them are based on the writings and researching of medical doctors and scientists who want to find out the truth about these particular “vaccines.” There are many other questions that must be asked; Yours Truly is presenting a few of the most important ones from a personal point of view in today’s post.

Dear COVID-19 “Vaccinated” Medical Professional:

With all due respect for your education and expertise, there now must be serious questions raised concerning the COVID-19 “vaccines” that were rushed into use in the United States and all over the world. These questions are especially important given the increasing numbers of reports of COVID-19 “vaccine”-induced injuries, illnesses, disabilities, and deaths, among those who have taken, and/or continue to take, these “vaccines.”

The first question that must be raised is: Are you aware that the FDA knew, back on 30 April 2021, that the modRNA COVID-19 “vaccine” by Pfizer-BioNTech, BNT162b2, is involved in the inducement of over 1,200 types of medical diseases and conditions? Here is the document that Pfizer-BioNTech gave to the FDA on that date: https://phmpt.org/document/5-3-6-postmarketing-experience.pdf, 5.3.6 CUMULATIVE ANALYSIS OF POST-AUTHORIZATION ADVERSE EVENT REPORTS OF PF-07302048 (BNT162B2) RECEIVED THROUGH 28-FEB-2021. Please see page 30 of this report, APPENDIX 1. LIST OF ADVERSE EVENTS OF SPECIAL INTEREST. The report is also found here: https://phmpt.org/document/5-3-6-postmarketing-experience.pdf. The document is FDA time-stamped 30 April 2021. Yours Truly will point out that this report covers only between 11 December 2020 (the date of the initial EUA granted by the FDA for BNT162b2 to be used in the United States) and 28 February 2021. The list of Adverse Events of Special Interest begins with 1p36 deletion syndrome; other diseases, disorders, and events mentioned include: Cardiac arrest; Cerebral thrombosis; Demyelination; Guillain-Barre syndrome; hepatic disorders; immune system disorders; pulmonary disorders; Myocarditis; neurological disorders; and, Pericarditis; among many others.

The second question that must be raised is: Are you aware that the modRNA COVID-19 “vaccines” made by Pfizer-BioNTech (these include BNT162b2; this company’s previous “booster” COVID-19 “vaccines”; and this company’s current “2023-2024 Formula COVID-19 Vaccine”) contain two dangerous lipid nanoparticles, ALC-0159 and ALC-0315, both of which are for research use only? Here are the Safety Data Sheets for these lipid nanoparticles: For ALC-0159: https://cdn.caymanchem.com/cdn/msds/34336m.pdf; and, for ALC-0315: https://cdn.caymanchem.com/cdn/msds/34337m.pdf. On page one of each of these Safety Data Sheets, there is the following language: “Application of the substance / the mixture This product is for research use – Not for human or veterinary diagnostic or therapeutic use.” In addition, are you aware that the modRNA COVID-19 “vaccines” made by Moderna (these include mRNA-1273; this company’s previous COVID-19 “booster vaccines”; and this company’s current “2023-2024 Formula COVID-19 Vaccine”) contain the dangerous lipid nanoparticle, SM-102, which is for research purposes only? Here is the Safety Data Sheet for this lipid nanoparticle: https://cdn.caymanchem.com/cdn/msds/33474m.pdf. On page one of this Safety Data Sheet, there is the exact same language in the section “Application of the substance / the mixture” as is listed for ALC-0159 and for ALC-0315 in their respective Safety Data Sheets: “This product is for research use – Not for human or veterinary diagnostic or therapeutic use.” (As an aside, ALC-0149 and ALC-0315 are described only by their chemical component names in the FDA-issued Fact Sheet for the Pfizer-BioNTech “2023-2024 Formula COVID-19 Vaccine”: www.fda.gov/media/167211/download; please see under section 11 DESCRIPTION. However, ALC-0159 and ALC-0315 are called by their proper names in the FDA document, www.fda.gov/media/172019/download, Emergency use Authorization (EUA) for an Unapproved Product Review Memorandum, dated 23 June 2023, section 7.1 Chemistry Manufacturing and Control (CMC) Information.)

The third question that must be raised is: Are you aware that the COVID-19 “vaccines” can, and do, “shed” components of these products from “vaccinated” persons to un-“vaccinated” persons? Dr. Pierre Kory has an extensive series of articles on his blog relating to this phenomenon: https://pierrekorymedicalmusings.com/; please see Part One of this series: https://medicalmusings.com/p/shedding-of-covid-mrna-vaccine-components, published 1 November 2023.

The fourth question that must be asked is: Are you aware that the COVID-19 “vaccines” can, and do, damage the blood vessels, heart tissue, and lung tissue, of persons who have these “vaccines” in their bodies? Please refer to: https://doctors4covidethics.org/wp-content/uploads/2022/08/causality-article.pdf, “Vascular and organ damage induced by mRNA vaccines: irrefutable proof of causality”, Michael Palmer, MD, and Sucharit Bhakdi, MD. Yours Truly presents page nine of this paper, which is self-explanatory:

The fifth question that must be asked is: Are you aware that the modRNA Pfizer-BioNTech COVID-19 “vaccine”, BNT162b2, changes the DNA of the LINE-1 Human Liver7 cell line? Please refer to: https://doi.org/10.3390/cimb44030073, “Intracellular Reverse Transcription of Pfizer BioNTech COVID-19 mRNA Vaccine BNT162b2 In Vitro in Human Liver Cell Line”, Yang De Marinis, et al. Yours Truly presents two images from this paper: The first, of DNA expression induced in BNT162b2-treated Human Liver7 cells in LINE-1; the second, of DNA amplicons induced by BNT162b2-treated Human Liver7 cells in LINE-1.

Also, please refer to this document, given by Pfizer-BioNTech to the FDA on 21 January 2021 and FDA time-stamped on that date, which can be found here: https://icandecide.org/wp-content/uploads/2022/03/125742_S1_M2_26_pharmkin-tabulated-summary.pdf, BNT162b2 2.6.5 Pharmacokinetics Tabulated Summary, regarding BNT162b2. Yours Truly present page seven of this report:

Notice the heavy accumulation of BNT162b2 in the livers of the Wistar lab rats that were used in this experiment conducted by Pfizer-BioNTech. This was the same BNT162b2 Pfizer-BioNTech modRNA COVID-19 “vaccine” that was later injected into human patients (with ingredients amounts calibrated for human use.)

Yours Truly will note that the CDC changed the definitions of “vaccine” and “vaccination” in 2021, after the rollout of the COVID-19 “vaccines” (gene therapy injections.) One suspects that this was done to “shoe-horn in” these products under the aegis of “vaccines.” Please refer to: www.johnlocke.org/the-cdc-changed-its-definitions-of-vaccine-and-vaccination-and-keeps-changing-its-definition-of-fully-vaccinated/. However, the FDA states clearly, on page four of the Fact Sheet for Healthcare Providers for the administration of the “2023-2024 Formula COVID-19 Vaccine” by Pfizer-BioNTech, that this product is to prevent coronavirus disease (COVID-19), not to “protect against serious illness from COVID-19”, as the CDC states. Please refer to: www.fda.gov/media/167211/download, page four, under section 1 EMERGENCY USE AUTHORIZATION; and to www.cdc.gov/coronavirus/2019-ncov/vaccines/stay-up-to-date.html under What You Need to Know.

Finally, there is this paper, published on 24 January 2024: https://doi.org/10.7759/cureus.52876, “COVID-19 mRNA Vaccines: Lessons Learned from the Registrational Trials and Global Vaccination Campaign”, M. Nathaniel Mead, Peter A. McCullough, et al. Yours Truly presents part of the Abstract of this paper:

Yours Truly sincerely asks that COVID-19 “vaccinated” medical professionals make every effort to investigate these “vaccines”, and to understand the very real risks and dangers of putting them into the human body. For further information, please see: www.theqtree.com/2024/01/04/the-deagel-report-u-s-population-reduction-of-68-5-by-2025/.

Sincerely, with Good Energy, Peace, and Respect, PAVACA
PAVACA: BFA (2), Carnegie-Mellon University; MA, Duquesne University. Reading and writing about COVID-19 and the COVID-19 “vaccines” since March 2020. Also interested in Pharmacy and in the impacts of Big Pharma. General Editor of Imagination-Building: The Memoirs of John Douglas Forbes (1910 – 2018), First Professor of the Darden School of the University of Virginia, available at www.amazon.com/, www.barnesandnoble.com/, and www.authorhouse.com/.