Health Friday 9.4.2026 Open Thread: Countermeasures and Precautions: An Opinion Piece

The free vintage image of hand washing for today’s offering header is courtesy of Open Culture and Google Images. Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats by Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.

>>>>>>>>>>>>>>>>>>>>

Countermeasures and Precautions: An Opinion Piece

The following is not medical advice. The following is not “SHTF prepping.” The following is not intended to instill fear. The following are ideas and opinions for consideration regarding certain “ongoing and upcoming situations.” There are several areas to consider: First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA), the first modRNA-platform based influenza bioweapon “vaccine”; Second area: the FDA’s just approving the “latest version” of the COVID-19 bioweapon “vaccines” for 2026 – 2027, based only on testing performed on mice; and, Third area: the recent paper which proves that the spike protein and other ingredients of the COVID-19 bioweapon “vaccine” injections remain active in the “vaccinated” person’s body for at least 3 1/2 years post-final “vaccine” injection.

>>>>>>>>>>>>>>>>>>>>

First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA): this situation has been covered extensively (and will continue to be covered) on this board; by our host, Wolf Moon, and by Yours Truly, among others who posted items related to the situation. The bottom lines of mFLUSIVA: One: this “vaccine” killed more than twice the number of clinical trial study subjects who took it, as compared to those study subjects who took the “comparator influenza” vaccine, Fluarix; Two: Moderna knows that mFLUSIVA can shed — study subjects were required sign an agreement to use birth control before, during, and after, their participation in the clinical trial; Three: mFLUSIVA was FDA-approved on “Accelerated Approval” for persons age 65 and over. Accelerated Approval means that Moderna must agree to perform a clinical trial of the “vaccine” using persons age 65 and older; Four: Moderna must also agree to track reports of deaths in persons who take mFLUSIVA. Our host, Wolf Moon, has written about mFLUSIVA; for example, here: https://www.theqtree.com/2026/08/07/a-grok-eyed-view-of-the-new-mrna-flu-shot/.

Second area: the FDA’s just granting approval for the “latest version” COVID-19 bioweapon “vaccines” for 2026 – 2027. The bottom lines: One: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Pfizer-BioNTech based on lab testing on 8 mice; no human trials. This follows the “Option 4” protocol for formulation of new COVID-19 bioweapon “vaccines” that was adopted by the FDA in 2022; Two: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Moderna based on lab testing on 10 mice, again following the “Option 4” described above; Three: based on the “ruling” against HHS by Federal Judge Brian E. Murphy earlier this year, these “latest version” COVID-19 bioweapon “vaccines” will be administered to persons from age 6 months and older. Please see: http://www.thefocalpoints.com/p/breaking-fda-approves-new-pfizer, “BREAKING: FDA Approves New Pfizer and Moderna XFG mRNA COVID-19 Shots Based on Data From Just 8 – 10 Mice”, Nicolas Hulscher, MPH, 27 August 2026

Third area: the McCullough, et al., paper, which proves that serious adverse reactions and events can occur in COVID-19 bioweapon “vaccinated” persons at least 3.5 years after the last “vaccine” injection (https://www.thefocalpoints.com/p/breaking-peer-reviewed-study-finds-51c, “BREAKING: Peer-Reviewed Study Finds mRNA, SV40, and Spike Protein Can Persist in Humans for At Least 3.5 Years After COVID-19 “Vaccination””, Nicolas Hulscher, MPH, 9 July 2026; the paper cited is here: https://doi.org/10.18103/mra.2026.0351, “Persistence of Vaccine mRNA, Plasmid DNA, Spike Protein, and Genomic Dysregulation Over 3.5 Years Post-COVID-19 mRNA Vaccination”, Nicolas Hulscher, MPH, et al.; published 31 July 2026. The bottom lines: One: these “vaccines” can, and do, have continuous negative consequences in persons who take them for years afterwards; Two: that repeated injections of these “vaccines” accumulate / aggravate / induce, continuous attack on the “vaccinated” person’s entire body and immune system; and, Three: repeated injections of these “vaccines” have the potential for accumulated damage to the entire body and the destruction of the “vaccinated” person’s immune system.

>>>>>>>>>>>>>>>>>>>>

It is estimated that about 77.1% of the population of the United States has taken at least one injection of a modRNA-based COVID-19 bioweapon “vaccine” (https://dig.abclocal.go.com/ccg/interactives/us-vaccine-tracker/vax_us_cdc.html, “U.S. COVID-19 vaccine map by state”. It is estimated that 135.6 million persons in the United States took an influenza “vaccine” in the 2025 – 2026 season (https://www.cdc.gov/fluvaxview/dashboard/index.html.) It is unknown how many will be take mFLUSIVA; however, there are physicians actively promoting this injectable. In fact, mFLUSIVA is being promoted as the “replacement” influenza vaccine for persons age 50 and older (https://epicenter.nyc.com/what-to-know-about-the-new-mrna-flu-vaccine-for-those-over-50/, Ambar Castillo, 13 August 2026.

>>>>>>>>>>>>>>>>>>>>

Where does all of the above leave the 20% – 25% of Americans who do not have COVID-19 bioweapon “vaccines” in their bodies? Where does that leave those who have had a COVID-19 infection, have recovered, but still may have lingering issues stemming from the infection (Long COVID; systemic inflammations of one kind or another; lung issues, and so on)? Where does that leave COVID-19 “vaccinated” persons who have decided to never take another injection of any of them? Where does this leave Americans with the 2026 – 2027 “latest version” COVID-19 bioweapon “vaccines” coming on the market within weeks, coupled with the campaigns from Establishment Medicine / government agencies / employers, and other entities, to “make sure one is up-do-date” with the “latest version vaccine”? Where does this leave people who decide to not take mFLUSIVA? In Yours Truly’s opinion, it comes down to making individual decisions regarding personal (and, perhaps, family) “countermeasures and precautions” — and following them faithfully.

>>>>>>>>>>>>>>>>>>>>

What would these “countermeasures and precautions” include? Perhaps, these areas to start the consideration and decision process: Countermeasures: Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine); and, Vitamins, Supplements, and Foods. For Precautions: Lifestyle Protocols / Adjustments. Each of these have ramifications that impact finances; availability; and, interactions with people. Each of these require that people “do their own due diligence” in researching the “countermeasures and precautions” that they are considering implementing for themselves (and, perhaps, for their family.)

Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine): These, in Yours Truly’s opinion, are the “core” of COVID-19 infection prevention or treatment. Independent Medical Alliance has both prevention and treatment protocols for COVID-19: https://imahealth.org/treatment-protocols/. Another protocol is found here: https://www.2ndsmartestguyintheworld.com/p/bombshell-shocker-the-cia-and-pfizer, “BOMBSHELL SHOCKER: The CIA & Pfizer LIED To The Public About The Need For Their $afe & Effective PSYOP-19 “Vaccines””, 2 September 2026; scroll down to the end of the post for “The Ultimate Disease Cure & Prophylaxis Protocol” section.

Vitamins, Supplements, and Foods: First, Vitamins and Supplements: Vitamin C and Vitamin D, for example, can help to bolster the body’s immune system. Supplements such as Zinc, Magnesium, and Quercetin help to keep the lungs clear (Zinc); to regulate many enzyme systems in the body (Magnesium); and, to increase or maintain anti-inflammatory and antioxidant protection (Quercetin.) Please see: regarding Zinc: https://pmc.ncbi.nlm.nih.gov/articles/PMC131177/, “What does zinc do?”, Abi Berger; 9 November 2002; regarding Magnesium: https://ods.od.nih.gov/factsheets/Magnesium-HealthProfessional/; regarding Quercetin: https://www.healthline.com/nutrition/quercetin, Ryan Raman; 7 May 2026. Many brands of multivitamins contain a more-or-less good range of vitamins and minerals; however, the amounts per vitamin or mineral may or may not satisfy the needs of the individual; in those instances, separate supplementation may be desired. Vitamin D uptake from sunshine can be done in many different and healthy ways.

Second, Foods: There is a saying, “Let food be thy medicine.” For some people, a diet that satisfies what is necessary regarding not only nutrition, but also for vitamins and minerals, may be one approach. An example for inclusion in such a diet is eggs (https://www.roswellpark.org/cancertalk/202504/are-eggs-good-you, “Are eggs good for you?”, 18 April 2025.) The “humble egg” is actually a “mini-powerhouse” of vitamins and minerals: Vitamins A — B2 — B12 — E; Lutein; Iodine; Selenium; and more; in addition to protein. Another example, this time of vegetables, is carrots (https://www.healthline.com/nutrition/foods/carrots, “Nutrition and Health Benefits of Carrots”, Adda Bjarnadottir, MS, RDN (Ice), 22 July 2026. Carrots provide beta-carotene (the body converts this into Vitamin A); fiber; antioxidants; and more. Carrots also may help support eye health, among other positive effects. Of course, there is red meat: https://pmc.ncbi.nlm.nih.gov/articles/PMC7015455/ , “What is the role of meat in a healthy diet?”, David M Klurfeld, July 2018. In addition to its being a complete protein, red meat also provides vitamins, amino acids, zinc, and iron.

Precautions: This area includes decisions regarding interacting with others who are COVID-19 “vaccinated”; whether or not to attend large-gathering places; and, if a non-COVID-19 “vaccinated” person is living with other who are “vaccinated”, among other situations. In no way is Yours Truly advocating that non-COVID-19 “vaccinated” people become “modern-day anchorites” with little or no contact with others. However, there are things that non-“vaccinated” people can do to reduce the potential for being exposed to “vaccine” shedding; and, to the potential for being infected by the COVID-19 virus itself. Examples: using disposable gloves at the gas pump; deciding whether or not to use “contactless” payment methods, as opposed to handing a credit card to someone; if possible, sitting at the back of a large-gathering event or facility; changing clothes after returning home from a family visit or going to a large-gathering event; taking an appropriately extra amount of, for example, Vitamin D before attending such an event; taking an appropriate extra dose of Ivermectin or Hydroxychloroquine after attending such an event; among others. Living with, or paying extended visits to, COVID-19 “vaccinated” people is another, and perhaps more difficult, area. Considerations here may be, for example, deciding to take Ivermectin on a weekly basis if a non-COVID-19 “vaccinated” person is part of a family (or, has roommates, etc.) that includes “vaccinated” people living in the same house. Please see: https://www.midwesterndoctor.com/p/covid-19-vaccine-shedding-experiences, “What We’ve Learned from Over a Thousand Vaccine Shedding Reports”, 7 January 2024.

>>>>>>>>>>>>>>>>>>>>

There is another, and important, area, to consider: interactions between drugs that are prescribed for particular needs, and repurposed drugs (such as, Ivermectin.) Please see: https://my.clevelandclinic.org/health/articles/drug-interactions. The Cleveland Clinic defines a drug interaction as what happens when “foods, drinks, dietary supplements, other drugs, prevent medications from working as they should.” For example, Ivermectin interacts with warfarin (Coumadin), and with other drugs: https://www.medicalnewstoday.com/articles/drugs-ivermectin-oral-tablet-interactions, Ashley Wong, PharmD, Last updated 17 January 2025. Ivermectin is also known to interact with: ketoconazole (an antifungal drug); and, with ritonavir (an HIV/AIDS treatment drug: please see https://synapse.patsnap.com/article/what-is-ivermectin-used-for); with benzodiazepines; and with alcohol (increased dizziness risk.) If using Ivermectin along with warfarin, it is important to keep a check on INR levels; it may also be germane to advise the healthcare professional who prescribed the warfarin, that Ivermectin is also being taken. Readers interested in investigating the potential for drug interactions regarding prescription drugs they take; and, for more information on prescription drugs, vitamins, and supplements (minerals) may wish to visit https://www.drugs.com/, or https://www.goodrx.com/. Note: be aware that these websites (and similar ones, such as the search engine at https://www.webmd.com/) appear to be biased against, for example, Ivermectin, except for the very narrow FDA-approved uses of this drug (to treat river blindness or lice.) The FDA still does not approve of Ivermectin for the prevention or treatment of COVID-19.

>>>>>>>>>>>>>>>>>>>>

There is one final area to consider as a COVID-19 and/or mFLUSIVA countermeasure: regular mild to moderate exercise, at least five days a week for 20 – 30 minutes a day. If this exercise can be done in the open air, in the sunshine, there is even more benefit. And the exercise does not have to be strenuous: for example, Tai Chi sequences, practiced correctly and with using proper breathing techniques, can provide a “slow-motion” cardio workout. Just wearing a pedometer to count steps, or staying active inside the house, can help. The point is to avoid being sedentary. Please consult a health professional before starting, or increasing, an exercise program, especially if one is recovering from an illness, has certain health conditions, and so on.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1. Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)


Health Friday 8.28.2026 Open Thread: mRNA-4157 / V940, Also Known As Intismeran, by Team Merck and Moderna

The free image of a vintage laboratory for today’s offering header is courtesy of stockcake and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you. Special Note regarding today’s offering: it is long. There are exhibits. Yours Truly is taking a blowtorch to the entire situation regarding mRNA-4157 (Intismeran) + KEYTRUDA©. Thank you.

The general summary: Moderna’s “on-demand cancer vaccine”, mRNA-4157, takes the concept of modRNA to a new, and potentially dangerous, level. There are no published results for the most-recent clinical trial for this “vaccine”, NCT05933577; Moderna states it will release the “topline results” of this study “at a medical meeting.” The results of the previous clinical trial for mRNA-4157, NCT03897881, were not “stellar”, to say the least. The 2020 Patent for mRNA-4157, WO2020097291, discussed below, states that this “cancer vaccine” is apparently to be primarily used as a preventative measure in healthy persons, with the “option” to also use it for a treatment of diagnosed cancer in persons. mRNA-4157 is formulated using potentially multiple types of lipid nanoparticles. mRNA-4157 is formulated using potentially multiple types of uracil RNA destroyers, chief among them, the N1-methylpseudouridine already in use in the company’s COVID-19 bioweapon “vaccines.” Moderna has partnered with Merck, Sharp and Dohme, in the development and clinical trials for mRNA-4157. These two companies have a 50/50 partnership agreement in place. Moderna has also borrowed $1.5 Billion dollars from Ares Capital Corporation for more funding.

>>>>>>>>>>>>>>>>>>>>

Merck, Sharp and Dohme has teamed up with Moderna to lab-create a new type of modRNA-based “vaccine”; this one, they claim, based on blood samples taken from the patient himself/herself. The result is a “combination” of modRNA created, so it is claimed, from blood samples taken from patients with melanoma, a skin cancer that can be fatal; and into which samples certain other elements are mixed. The resulting product is called Intismeran Autogene (also called Intismeran.) This product is used in conjuction with an already-approved drug used in cancer treatment, called KEYTRUDA©. The patient is injected with Intismeran “cancer vaccine” mixture, while at the same time, undergoing treatment with KEYTRUDA© (with the patient having begun with KEYTRUDA© before the Intismeran is added; then, both are used.)

>>>>>>>>>>>>>>>>>>>>

Yours Truly begins here, with the Merck announcement of the Phase 3 clinical trial “positive topline results” for Intismeran + KEYTRUDA© (NCT05933577: https://www.merck.com/news/merck-and-moderna-announce-phase-3-interpath-001-trial-of-intismeran-autogene-plus-keytruda-met-endpoints-of-recurrence-free-survival-rfs-and-distant-metastasis-free-survival-dmfs-in-patient/, “Merck and Moderna Announce Phase 3 INTerpath-001 Trial of Intismeran Autogene Plus KEYTRUDA© Met Endpoints of Recurrence-Free Survival (RFS) and Distant Metastasis-Free Survival (DMFS) in Patients With Completely Resected Stage IIB – IV Melanoma”, 19 August 2026. Please see the screenshots from this article, below. Note: For purposes of today’s offering, Yours Truly will use the terms KEYTRUDA©, pembrolizumab, and pembro interchangeably, as all three terms describe the same drug. Similarly, mRNA-4157 and Intismeran will be used interchangeably. Also, Yours Truly is not in any way, dismissing or minimizing the use of pembrolizumab alone in treating cancer; this drug has worked well for many patients. What Yours Truly is interested in is what appears to be the use of pembrolizumab as an “adjunct”, so to speak, to mRNA-4157.

However, no results have been published for Phase 3 of NCT0593577 — more on that below. Here is the announcement by Moderna, covered in BioPharmaDive: https://www.biopharmadive.com/news/moderna-merck-cancer-vaccine-landmark-result-melanoma/828238/, “Moderna and Merck cancer vaccine returns ‘landmark’ result in melanoma”, Jonathan Gardner, 19 August 2026. Please see the screenshot, below:

So, Team Merck and Moderna have no plans to release these “topline results” of NCT05933577 to the general public — but, instead, “intend” to release these “topline results” at a “medical meeting.” How “interesting.”

Which is followed by this, courtesy of our good TradeBait2, from Just The News: https://justthenews.com/politics-policy/science-press-release-moderna-cashes-mrna-cancer-vaccine-while-hiding-trial, “Science by press release: Moderna cashes in on mRNA cancer vaccine without publishing trial results”, Greg Piper, 23 August 2026.

Is Team Merck and Moderna hiding something about the “landmark result” of the Phase 3 clinical trial of mRNA-4157 (Intismeran) + KEYTRUDA©? Is it, perhaps, because this “landmark result” is really NO BETTER than those of the PREVIOUS clinical trial for this “cancer vaccine combo treatment”, NCT03897881? The truth is: the results of NCT03897881 are, so to speak, “less than landmark.” Please see: https://cancertherapyadvisor.com/reports/adding-intismeran-pembrolizumab-survival-melanoma/, “Adding Intismeran to Pembolizumab Boosts Survival in Advanced Resected Melanoma”, Liam Andrew Davenport, MA (Hons), 25 June 2026. This article reports on the 2026 annual meeting ot ASCO (American Society of Clinical Oncology.) The presenter of the results for NCT03897881 was Matteo S. Carlino, MBBS, PhD. Below are several screenshots: two from the meeting report; then, one of the Results section of the paper on NCT03897881 that was written by Dr. Carlino:

Look at what Dr. Carlino states: non-significant improvement in the study subjects who were taking mRNA-4157 + pembro; and, more risk of Grade 3 or higher adverse events in study subjects who were taking mRNA-4157 + pembro. Grade 3 adverse events “are serious” and interfere with the person’s ability to do normal activities such as, eating (https://dipg.org/treatment/clinical-trials/side-effects/, “Side Effects in Clinical Trials.”)

Look at the Results section above: less than 50% RFS risk reduction for mRNA-4157 + pembro compared to pembro use alone; SEVEN study patients died after taking the mRNA-4157 + pembro, and SEVEN patients died after taking pembro alone: in other words, no reduction of risk of death from the mRNA-4157 + pembro “conbo drug treatment.” The website for NCT03897881 are here: https://clinicaltrials.gov/study/NCT03897881. In the “Reseacher View” details of this clinical trial, the only results are those in the two scientific papers that are cited; there is nothing in the “Results Posted” section on the clinical trial “Overview” webpage.

BUT, despite this set of results for NCT03897881, the FDA granted “breakthrough therapy designation” for the mRNA-4157 + pembrolizumab “combo cancer vaccine treatment”: https://www.onclive.com/view/fda-grants-breakthrough-therapy-designation-to-mrna-4157-v940-plus-pembrolizumab-in-high-risk-melanoma, Chris Ryan, 23 February 2023. Not a bad “return on investment” for Moderna on this one — even though the results of the NCT03897881 clinical trial appear to be “less than stellar.” A perfect example, in Yours Truly’s opinion, of how Big Pharma controls the FDA.

>>>>>>>>>>>>>>>>>>>>

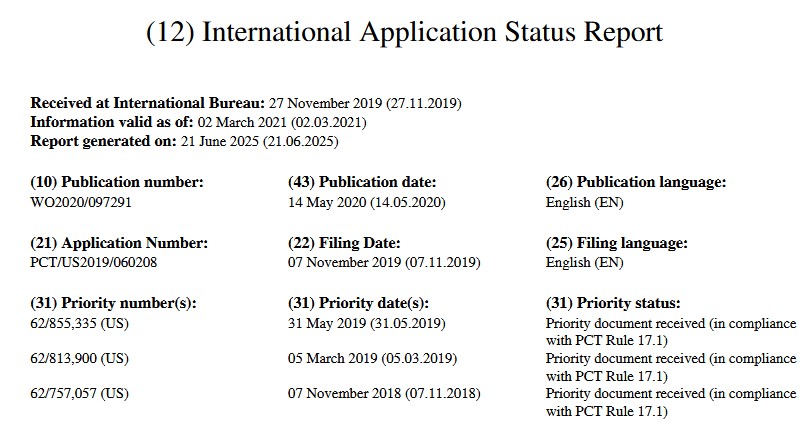
Yours Truly now turns to a major “source document” for mRNA-4157: the Patent for this “cancer vaccine”, found here: https://patentscope.wipo.int/search/en/WO2020097291, “RNA Cancer Vaccines”, publication date 14 May 2020; the Applicant is: ModernaTX, Inc., 200 Technology Square, Cambridge MA 02139. The following exhibits are from the Patent document; summaries are by Yours Truly. To begin: first, the Publication page; then, second, a portion of the Status Report page:

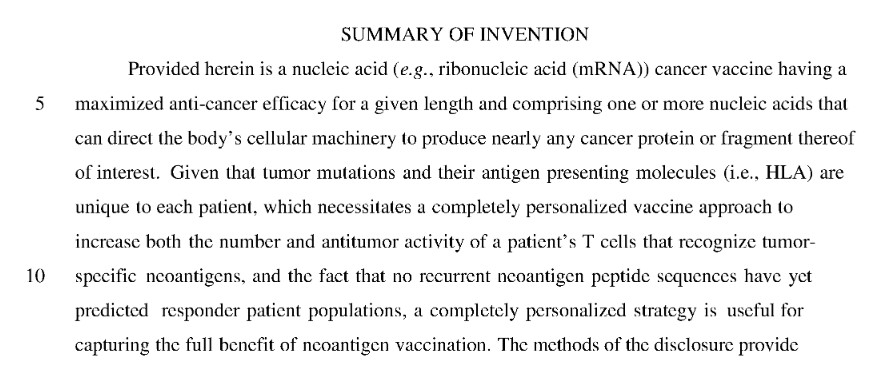
From the Summary of Invention, page 2: first, lines 5 – 11; then, lines 22 – 29. Notice that the “invention” is intended to stimulate the body to produce cancer proteins or parts thereof. This appears to be the “autogene” part of the “invention.” Notice also that the “invention” is to be administered multiple times to the patient. Notice also that mRNA-4157 can contain one or more mRNAs, each with one or more ORFs (Open Reading Frames):

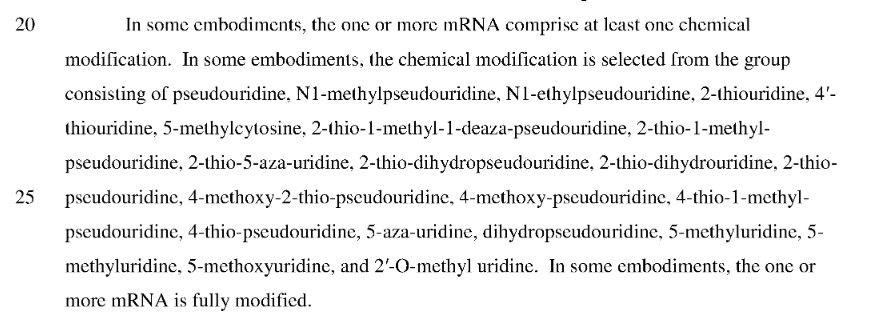
Page 4, lines 20 – 28: the Patent’s inventors waste no time in making sure that N1-methylpseudouridine, among other uracil (RNA) destroyers (“modifiers”) can be used in mRNA-4157:

**** Page 5, lines 15 – 17: the basic mechanism of mRNA-4157 — to “provoke” a “memory immune response” in the patient’s body. Shades of the “immune memory response” that is supposedly “taught” to the body of the person who takes Moderna’s COVID-19 bioweapon “vaccines” SPIKEVAX or mNEXSPIKE, perhaps?:

**** Page 5, lines 25 – 27: It appears that either cancer tumor DNA, or blood sample DNA, from the patient, can be used to lab-generate the peptide epitopes in mRNA-4157:

Page 6, lines 21 – 22: the “checkpoint inhibitor” in the “cancer vaccine” treatment is KEYTRUDA© (pembrolizumab.)

**** Page 17, lines 20 – 24: mutations; look at the mention of frameshifting. A tacit admission that mRNA-4157, as do the modRNA COVID-19 bioweapon “vaccines”, induce frameshifting in the body:

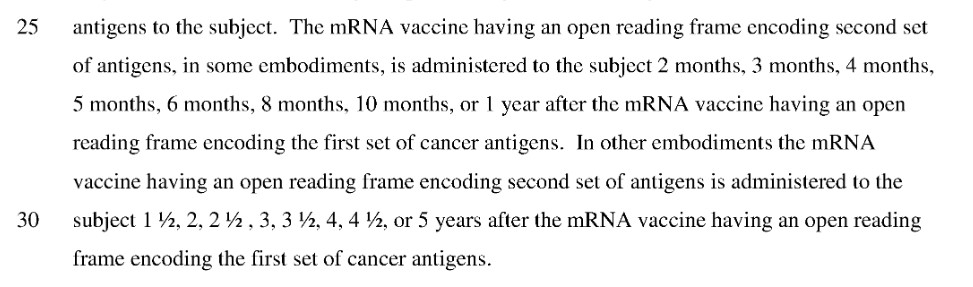
Page 31, lines 25 – 31: Depending on the ORF (Open Reading Frame) used, the treatment with mRNA-4157 can go on for up to 5 years:

There is extensive mention in the Patent of the use of N1-methylpseudouridine to completely replace (“uniformly modify” or “fully modify” are the terms used in the Patent) the uracil RNA of Uridine in the patient’s body. Example: please see Page 42, lines 8 – 14.

**** Methods of Treatment section: Page 67, lines 5 – 14: It appears that, in reality, mRNA-4157 is to be used as PROPHYLACTIC PROTECTION from cancer. Look at the language, “It may be reasonable” to use the “vaccine” ALSO as a treatment for a person who already has cancer. Also — Page 68, lines 30 – 31, and Page 69, lines 1 – 6: the mRNA-4157 “cancer vaccine” can ALSO be used in HEALTHY PERSONS as a “primer” and/or as a “booster shot”:

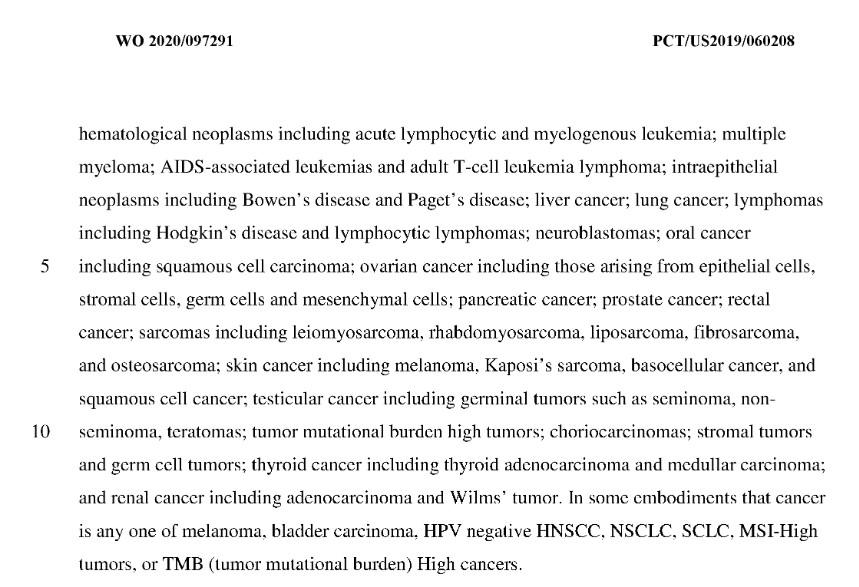
**** Page 70, lines 28 – 31, through Page 71, lines 1 – 14: the list of cancers that the Patent claims can be treated by mRNA-4157. This list includes dozens of types of cancer. The list from Page 71 is below:

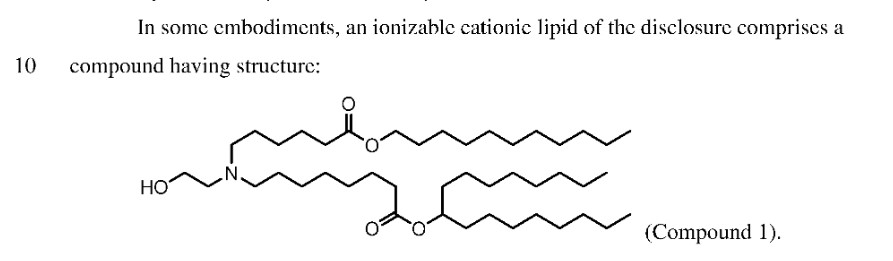
Page 82 through Page 90: Discussion and description of the “Formula (1)”, aka “Compound 1” (which appears to be at least one of the mRNA-4157 “formulas” that is being used in the clinical trials); discussion and description of “Formula 1A”; discussion and description of “Formula II.”

Page 91, lines 9 – 11: What looks like the chemical schema of the lipid nanoparticle SM-102 being used in the “Compound 1” of mRNA-4157:

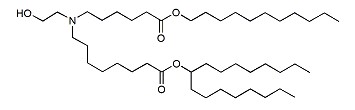
Which looks suspiciously like CAS# 2089251-47-6, “SM-102” available from Broadpharm (https://broadpharm.com/search?search_query=2089251-47-6):

Or, that Moderna modified the “backbone” of the SM-102 lipid nanoparticle that is used in the company’s COVID-19 modRNA bioweapon “vaccines” for use in mRNA-4157.

**** Page 105: Phase 1 clinical trial for mRNA-4157 + pembro, “Combination arm” results. “Compound 1” (“C1” — see above in the Patent presentation) was used. Table 6, included on Page 105, indicates that, of the 20 advanced metatastic / advanced cancer patients in the study, 8 then presented with Progressive Disease. This appears to mean an almost 50% risk of presenting with progressive cancer while taking mRNA-4157 + pembro. The results of this 2019 Phase 1 clinical trial (https://clinicaltrials.gov/study/NCT03739931) are summarized here: https://ascopubs.org/doi/10.1200/JGO.2019.5.suppli.93. From the Abstract of this paper, the Results section, which equates to the Table 6 on Page 105 of the Patent:

**** Team Merck and Moderna KNOW that mRNA-4157 CAN SHED. Please see: https://clinicaltrials.gov/study/03739931, the “Researcher View”; scroll down to the subsection “Exclusion Criteria”. BOTH male and female study subjects in this Phase 1 clinical trial had to agree TO USE BIRTH CONTROL:

The above is not an exhaustive analysis of the cited Patent for mRNA-4157. In fact, there are multiple other Patents listed for mRNA-4157, per Page 30 of the above cited Patent. What the exhibits and summaries of the above cited Patent do indicate, however, are:

That Moderna is using the “framework” of their COVID-19 modRNA bioweapon “vaccines” to move on to the next step: the lab-creation of “on-demand” cancer treatment “vaccines” that would be tailored to the individual patient, and lab-created from various types of samples from the patient;

That Moderna is potentially including MULTIPLE TYPES of lipid nanoparticles in the potential “compositions” of the “cancer vaccines” that the company is using mRNA-4157 as the “template” for;

That Moderna is taking the concept of “modRNA” to a different — and, in Yours Truly’s opinion, a potentially dangerous level, absent YEARS of intense research and clinical trials — “modRNA” that is lab-created using an “automated one-demand” process from the cells of an individual person (blood; tumor; urine; sweat; saliva, etc.);

That Moderna is making the claim that a “cancer treatment vaccine” lab-created from the patient’s own DNA can be, almost literally, be produced “on the spot” for near-real time, “instant’ treatment use; and has built an entire “automated facility” to produce this “vaccine”;

That it appears Moderna intends for mRNA-4157 to be used in healthy persons as a PREVENTATIVE “vaccine” for cancer, in addition to the product being used to treat persons who ALREADY HAVE cancer; and,

That Moderna appears to be using persons who already have cancer as “human lab rats” to see if mRNA-4157 has any real benefit as a cancer treatment;

That Moderna may be using these “human lab rats” in mRNA-4157 clinical trials as “proof” of “If cancer can be cured with a modRNA “vaccine”, and cancer being something that people never want to have: then, taking mRNA-4157 as a cancer preventative can erase cancer from humankind.”

>>>>>>>>>>>>>>>>>>>>

Yours Truly now turns to another type of “source document” regarding mRNA-4157 (Intismeran): the Moderna SEC filing of 31 December 2025 (Securities and Exchange Commission document.) The SEC filing is found here: https://www.sec.gov/Archives/degar/data/1682852/000168285226000033/mrna-20251231.htm.

Page 10: the “surface properties” regarding the lipid nanoparticle (LNP) platform systems.

**** Page 19: the mRNA-4157 “Intismeran autogene” targets the CD4 and CD8 cells of the body (shades of the attack on the CD4 and CD8 cells that occurs from the modRNA COVID-19 bioweapon “vaccines.”) Also: Moderna will share 50% with Merck regarding the costs, profits and losses worldwide for mRNA-4157. Please see the screenshot, below, from Page 19 of the SEC filing:

Page 22: Moderna has built an entire “dedicated” facility in Marlborough, MA, devoted solely for the lab-creation and processing of mRNA-4157.

**** Page 26, section THIRD-PARTY STRATEGIC ALLIANCES: Merck has paid Moderna a total of $450 million in research and development costs for mRNA-4157. This is pursuant to a third-party strategic alliance agreement that was signed by Moderna and Merck in January 2015, for the development, approval, and marketing of “cancer vaccines.” (Recall that Moderna also has a STILL-EXISTING third-party strategic alliance agreement with NIAID regarding the development, approval, and marketing of mSPIKEVAX and mNEXSPIKE. Moderna is paying royalty payments for NIAID for every dose of these “vaccines.” This particular third-party strategic alliance agreement began in 2015, with Moderna and NIAID agreeing to co-develop and co-own the Patent for mRNA-1273. This is discussed in the SEC filing of 31 December 2025, on Page 31) Please see the screenshot below, regarding mRNA-4157 and Merck:

**** Page 43 et seq., Item 1A. Risk Factors section of the Moderna SEC filing of 31 December 2025: the following, from Page 44: “The commercial success of our products depends on the degree of market acceptance by physicians, patients, third-party payors and others in the medical community.” From Page 46: “If we cannot obtain, or are delayed in obtaining, regulatory approvals and advisory committee recommendations, we will be unable to effectively commercialize, or be delayed in commercializing, our product candidates.” In Yours Truly’s opinion, Moderna is stating that its products are “successful” if they have “market acceptance”; and, that Moderna needs to have swift regulatory approval of its products to get them on the market as soon as possible.

**** Page 144, Exhibit 10.7 (title hyperlinked): Moderna borrowed $1.5 Billion dollars from Ares Capital Corporation on 19 November 2025. The lender(s), of course, will be looking for a “full return” of the loan. Please see below:

>>>>>>>>>>>>>>>>>>>>

Yours Truly turns to one more aspect of modRNA “vaccines”: the potential that they will shed onto other people. This phenomenon is likely, as most vaccines can shed, at least for a limited time; however, in the case of the modRNA “vaccines” (and this now includes modRNA “cancer vaccines”, such as mRNA-4157), the potential for “vaccine” shedding is ALSO brought to a new, and possibly very dangerous, level. If a modRNA COVID-19 bioweapon “vaccine” can shed, what about the potential for an “individualized cancer vaccine” to ALSO shed? For more information regarding COVID-19 “vaccine” shedding, please see: https://www.thefocalpoints.com/p/inadvertent-exposure-to-pharmacologically, “Inadvertent Exposure to Pharmacologically Designed Lipid Nanoparticles Via Bodily Tissues: Biologic Plausibility and Potential Consequences”, Peter A. McCullough, MD, MPH, 3 March 2024. The three types of exposure are: “vaccine” biodistribution within the body of the “vaccinated” person; Two, via “secondary exposure” (skin-to-skin contact, sexual intercourse, bodily fluids, etc.); and, Three, via contaminated blood in blood transfusions. The paper referred to in the McCullough article, of the same title as his article, is here: https://doi.org/10.20944/preprints202402.1267.v1, T.J. Halma, Jessica Rose, Peter A. McCullough; 22 February 2024.

>>>>>>>>>>>>>>>>>>>>

Gentle reader, does one see how the game is played by Moderna? In November 2015, Moderna and NIAID signed a CONFIDENTIAL DISCLOSURE AGREEMENT regarding development of injectable drugs. NIAID (NIH) would pay Moderna as part of this “collaborative” agreement. Amendment No. 5, of April 2019, is the first mention of mRNA technology being co-developed by Moderna and NIAID; Amendment No. 6, of February 2020, extends this “collaboration.” In addition to these, Moderna and NIAID signed a COOPERATIVE RESEARCH AND DEVELOPMENT AGREEMENT (“CRADA”) in August 2016. The above documents are found here: https://www.documentcloud.org/doceuments/6935295-NIH-Moderna-Condifential-Agreements/.

So, Step One is in place: Moderna and the US government agree to co-develop, co-own, and share royalty payments for certain vaccines, including mRNA-based bioweapon “vaccines.” Step Two: between April 2019 and November 2020, the “collaborators” work on the lab-creation of mRNA-1273. Step Three: the COVID-19 disaster begins, late fall of 2019. Step Four: the FDA grants the initial EUA for mRNA-1273 on 11 December 2020. Step Five: millions of Americans are gaslighted, coerced, or “mandated” to take COVID-19 bioweapon “vaccines” — such as, mRNA-1273 and its “descendant clone vaccines.” Step Six: hundreds of types of serious adverse reactions and adverse effects begin to present. These adverse effects include cancer.

Meanwhile, Moderna and Merck, in January 2016, sign an agreement to “collaborate” on the lab-creation of an modRNA-based “cancer vaccine”, (which would eventually be called mRNA-4157 (Intismeran)), and get this injectable to the clinical trials stage. Moderna and Merck agree to share 50 / 50 the costs, profits, and losses regarding this “cancer vaccine.” The Patent for mRNA-4157, described above, specifically states that mRNA-4157 is to be used as a preventative for cancer, with the “option” for it to also be used as a cancer treatment (with another cancer drug as an “adjunct”; in the case of mRNA-4175, it is pembrolizumab.) Moderna has several “bases” covered at the same time: create a “vaccine” that can (and does) induce cancer in the body; then treat that cancer with another modRNA-based “vaccine” (mRNA-4157) that is coupled with pembrolizumab; while, at the same time, keeping mRNA-4157 “under wraps”, so to speak, in the Patent for this “cancer vaccine”, for future use as a preventative for cancer.

Moderna is already moving along in the mRNA-4157 trajectory. There are two other clinical trials using this “cancer vaccine”: NCT06307431, for persons with renal cell carcinoma; and, NCT06961006, for persons with advanced melanoma. The clinical trials cited in today’s offering were / are sponsored either by Moderna or by Merck.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items above that are available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions from today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 8.21.2026 Open Thread: NIH, NIAID, US Army Fund the Creation of an Avian Influenza Vaccine with Plague-Derived Adjuvant

The free vintage image for today’s offering header of Scène de la peste de 1720 by Michel Serre, of the Great Plague of Marseille, is courtesy of Google Images. For more information about the Great Plague of Marseille, please see: https://www.sciendirect.com/science/article/pii/S0755498222000318, “History of the plague of 1720 – 1722, in Marseille”, Michel Signoli, et al.; September 2022. For more information about the Black Death (Black Plague) in Europe, 1347 – 1351, please see: https://www.britannica.com/event/Black-Death. Note that the article on the Britannica website mentions the fact that the strain of Yersinia pestis (Y. pestis) that caused the Black Death plague in Europe is the ancestral strain of all other plague events since then.

The word “plague” generate images of the Black Death (Black Plague, the Bubonic Plague) that swept through Europe in the mid-1300s. Of thousands of dead people on the streets. Of entire families wiped out in a few days. Of the cries of “Bring out your dead.” And the Black Death is only one example of how devastating the plague can be. There have been numerous other incidents of plague attack, such as the 1720 – 1722 event that struck Marseille, France. Today’s offering discusses a “new aspect” of the plague — of a certain element of it being used as a “vaccine” ingredient. For purposes of today’s offering, Yersinia pestis and Y. pestis are used interchangeably.

>>>>>>>>>>>>>>>>>>>>

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.

>>>>>>>>>>>>>>>>>>>>

There has been concern and discussion regarding the use of certain “adjuvants” in injected drugs (examples: the Hepatitis B “vaccine” uses an aluminum-based adjuvant; certain influenza “vaccines” still use mercury-based adjuvants (thimerosal.) https://www.cdc.gov/vaccine-safety/about/adjuvants.html defines an adjuvant as: “An adjuvant is an ingredient used in some vaccines that helps create a stronger immune response in people receiving the vaccine.” For more information regarding the use of aluminum as an adjuvant, please see: https://www.chop.edu/vaccine-education-center/vaccine-safety/vaccine-ingredients/aluminum. For more information regarding the use of mercury as an adjuvant, please see: https://www.chop.edu/vaccine-education-center/vaccine-safety/vaccine-ingredients/thimerosal. Both of these articles are by Children’s Hospital of Philadelphia.

However, there are other types of adjuvants that are either now in use, or are being studied for use, in injectable drugs. One such use being studied is the subject of today’s offering: an Avian Influenza “vaccine” adjuvant derived from the Yersinia pestis bacterium (the Black Death, the Black Plague, and also known as the Bubonic Plague.) To repeat: an Avian Influenza “vaccine” adjuvant derived from the Yersinia pestis bacterium (the Black Death, the Black Plague, and also known as the the Bubonic Plague.) Yours Truly begins here, with an article by Jon Fleetwood: https://jonfleetwood.substack.com/p/hhs-funds-chimeric-bird-flu-pandemic, “HHS Funds Chimeric Pandemic Bird Flu Vaccine Made With Engineered Plague Derivative BECC470s: Journal ‘mSphere'”, 13 August 2026. Please see the screenshots from this article, below:

The paper referred to in the Fleetwood article is here: https://journals.asm.org/doi/10.1126/msphere.00171-26, “Optimizing an avian influenza vaccine using a novel Bacterial Enzymatic Combinatorial Chemistry (BECC) TLR4 adjuvant”, Robert K. Ernst, et al.; 10 July 2026. The research was funded primarily via HHS-NIH-NIAID-BAA2017/HHSN272201800043C; via other HHS-NIH-NIAID grants; and, the Center for Vaccine Development and Global Health (University of Maryland School of Medicine.) The work of one co-author, Devon Riley, was funded via the United States Army Long-Term Health and Education Training Program.

>>>>>>>>>>>>>>>>>>>>

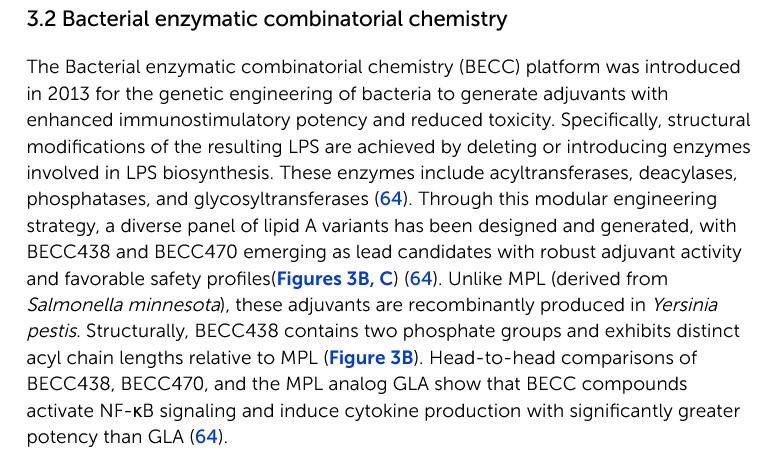
What is BECC470? Please see: https://www.fromtiersin.org/journals/immunology/articles/10.3389/fimmu.2026.187218/full, “Licensed and investigational TLR4 agonists as vaccine adjuvants: Structural basis, clinical progress, and future directions”; Jiasheng Zhou, et al.; 16 July 2026. Note that, except for one co-author of this paper (who is associated with the Communist Chinese version of the CDC), all other co-authors are associated with research institutes in Wuhan, Communist China. A screenshot of section 3.2 of this paper, which describes BECC (Bacterial Enzymatic Combinatorial Chemistry) is below. There are two versions of BECC470: BECC470b (the biological form of the Y. pestis element in the adjuvant); and, BECC470s (the lab-created synthetic form of the Y. pestis element in the adjuvant):

BECC438, BECC470b, and BECC470s are all derived from the lipid A in Y. pestis.

It appears that there are three separate publications of the Robert K. Ernst, et al., paper: the 10 July 2026 paper in the ASM Journals, cited above; another publication, a day later in July 2026, in journal Vaccines (https://www.sciencedirect.com/science/article/pii/S02644-10X26005839), “BECC-adjuvanted hemagglutinin influenza vaccine promotes enhanced immunogenicity and protective efficacy”, Robert K. Ernst, et al.; 11 July 2026; and, a Biorxiv preprint version, published in March 2026 (https://www.biorxiv.org/content/early/2026/03/05/2026.03.03.709477.full.pdf, “Optimizing an avian influenza vaccine using a novel Bacterial Enzymatic Combinatorial Chemistry (BECC) TLR4 adjuvant”, Robert K. Ernst, et al.; 5 March 2026. All three of these publications appear to have same parameters: One, that Gain-of-Function experiments were performed with multiple strains of Avian Influenza and then injected into the lab mice; Two, there is no direct mention that BECC438, or BECC470b, or BECC470s, are derived from the lipid A of Y. pestis; and, Three, that BECC adjuvants are “superior” to the other types of adjuvants currently in influenza “vaccines.”

>>>>>>>>>>>>>>>>>>>>

Back to the article by Jon Fleetwood. Something caught Yours Truly’s eye: It appears that the lipid A portion of a certain strain of Y. pestis, called KIM6+, is the one that was chosen to lab-create BECC470b, which was then chemically engineered to create BECC470s. Please see below:

Yours Truly did some digging into KIM6+. The 2023 paper, which also has Robert K. Ernst as co-author, is here: https://www.cell.com/action/showPdf?pii=S2405-8440(23)05327-6, “Physiochemical characterization of biological and synthetic forms of two lipid A-based TLR4 agonists”, Robert K. Ernst, et al.; available online 8 July 2023. Another paper, from 2021, by Bland, et al., discusses the KIM6+ strain of Y. pestis and its infectivity: https://journals.plos.org/plospathogens/article?id=10.1371/journal.ppat.1009995, “Acquisition of Yersinia murine toxin enabled Yersinia pestis to expand the range of mammalian hosts that sustain flea-borne plague”, David M. Bland, et al.; 14 Octocer 2021. Please see below, from the Results section of this paper:

It appears that the KIM6+ strain of Y. pestis is one that has about 50% more capability to infect. And it is the KIM6+ strain that was chosen to lab-create BECC470b; and then to have that chemically engineered to lab-synthesize BECC470s — both of which can be used as vaccine adjuvants.

>>>>>>>>>>>>>>>>>>>>

Robert K. Ernst holds at least two US Patents related to the use of KIM6+-derived Y. pestis lipid A constructs that can be used as adjuvants in vaccines: US10358667B2, 7 January 2016, “Adjusted expiration” of 19 March 2034: and, US11124815B2, 21 September 2021, “Adjusted expiration” of 7 March 2034. Both Patents have the same Title (“Immunotherapeutic Potential of Modified Lipooligosacchardies/Lipid A”); the same Inventors (Robert K. Ernst, et al.); and the same Licenses and Options (Licensed to TollereBio Corporation [Robert K. Ernst], Optioned to Virtici, LLC.)

Reading through US10358667B2, one finds, for example, that a BSL-2 biosafety laboratory level is, apparently, sufficient to work with the KIM6+ lipid A of Y. pestis, and to lab-create BECC470 adjuvants from this bacterium; that BOTH the “biological version” of BECC470 (BECC470b) and the “synthetic version” of BECC470 (BECC470s) can be used as vaccine adjuvants; and, that the BECC470 vaccine adjuvants, per the Patent, section VIII. Use of Exemplary Lipooligosaccharide/Lipid A-based Mimetic Compositions: “…is [sic] useful for…” the following vaccines, among others, listed in the Patent:

measles, mumps, rubella (think MMR);

polio;

plague;

chickenpox;

HPV;

Hepatitis B (think newborn “vaccination” with this one);

pertussis;

tetanus;

and, shigella (Shingles)

And, in fact, Dr. Ernst is at work creating a shigella “vaccine” that includes BECC-engineered adjuvants: https://www.sciencedirect.com/science/pii/S0264410X25000763, “BECC-engineered live-attenuated Shigella vaccine candidates display reduced endotoxicity with robust immunogenicity in mice”, Robert K. Ernst, et al.; 19 March 2025. This paper appears, in Yours Truly’s opinion, to “dance around” actually mentioning the apparent use of Y. pestis-derived elements in the Gain-of-Function shigella “vaccine” that was administered to lab mice (administered using various methods, including intramuscular injection and gastric injection.) The paper does list various Patents that are “related” to the paper, including both US10358667B2 and US11124815B2 (discussed above in today’s offering.) The paper also lists the 2018 Ernst, et al., paper regarding the use of Y. pestis-derived BECC438 in a vaccine administered to mice: https://www.sciencedirect.com/science/article/abs/pii/S0264410X18307680, “A lipid A-based TLR4 mimetic effectively adjuvants a Yersinia pestis rF-V1 subunit vaccine in a murine challenge model”, Robert K. Ernst, et al.; 27 June 2018.

In Yours Truly’s opinion, this entire situation raises important questions, among them: One: Why is the United States government (via HHS / NIH / NIAID), and the United States Army, funding research into using any element of the plague bacterium in a drug of any type, let alone a drug that can be injected? Two: How is it possible that a BSL-2 level laboratory can be considered to have sufficient biosafety to work with any element of the plague bacterium? Three: Why was KIM6+, apparently one of the most deadly and infective lipid A elements of Y. pestis, used to lab-create BECC470b and BECC470s? And, Four: Is it possible to completely “de-nature” the deadly effects of any element of Y. pestis sufficiently for such element to be used as an adjuvant in vaccines?

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 8.14.2026 Open Thread: The Female Fertility and Pregnancy Killers in US9884895B2, the SARS-CoV-2 “Template Virus” Patented by Dr. Ralph Baric, PhD

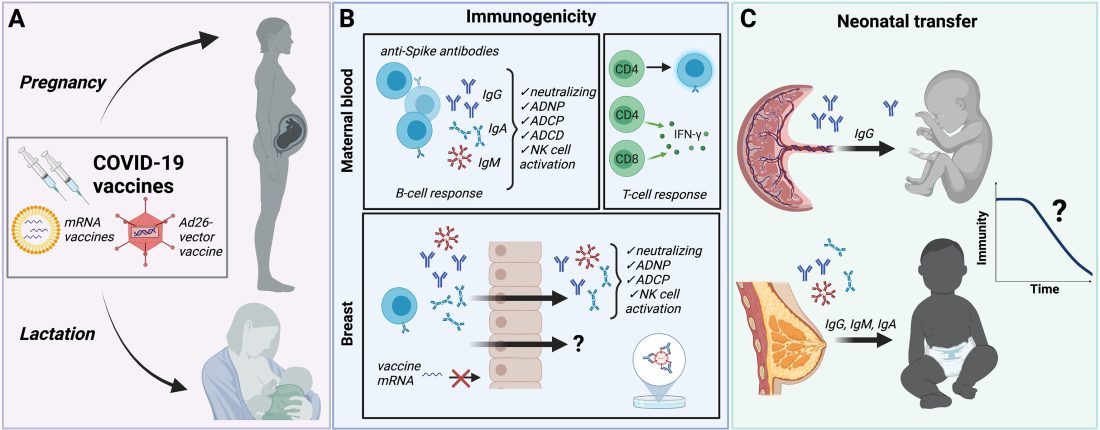
The graphic above, which is also the header for today’s offering, is Fig. 1 from: https://www.frontiersin.org/journals/cellular-and-infection-microbiology/articles/10.3389/fcimb.2021.735394/full, “COVID-19 Vaccination in Pregnancy and Lactation: Current Research and Gaps in Understanding”, Lydia L. Shook, et al.; 15 September 2021. With thanks to the authors of this paper.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.

>>>>>>>>>>>>>>>>>>>>

Please see: https://www.2ndsmartestguyintheworld.com/p/bombshell-faucis-private-textx-admit, “BOMBSHELL: FAUCI’S PRIVATE TEXTS Admit “Theoretical Miscarriages for Pregnant Women From PSYOP-19 “Vaccine””, 11 August 2026. Please see the linked article, https://www.2ndsmartestguyintheworld.com/p/confidential-pfizer-documents-confirm, “Confidential Pfizer Documents confirm 82 – 97% of COVID Vaccinated Pregnant Women sadly lost their Baby during Trial”, 15 August 2022. Please also see: https://www.theburningplatform.com/2026.08/12/fauci-knew-covid-jab-was-dangerous-for-pregnant-women/, Martin Armstrong, 12 August 2026. Another article is here: https://www.thefocalpoints.com/p/faucis-miscarriage-of-public-health. “Fauci’s Miscarriage of Public Health Led to Actual Fetal Loss in Thousands of Pregnant Women”, Peter A. McCullough, MD, MPH (text summary and embedded video interview with Dr. McCullough.) There are links to other articles; to scientific papers; to charts and graphics, within each of the other cited URLs. An example of the items found in the links above is this one, a screenshot from the Martin Armstrong article. The paper by Dr. Tom Shimabukuro, the “federal study” of April 2021, is discussed further down in today’s offering:

In Yours Truly’s opinion: Dr. Anthony Fauci; Dr. Rochelle Walensky; and, Dr. Vivek Murthy — all knew what they were doing in privately recognizing to each other that the modRNA COVID-19 bioweapon “vaccines” were dangerous to pregnant women; to the child they were carrying; and, that these “vaccines” could cause the death of the fetus in a “vaccinated” pregnant woman: while, at the same time, each of them were stating that these same “vaccines” were “safe and effective”, and that they would not pose harm to a pregnant woman or to her unborn child. There is no excuse for, no “qualifying explanation” for, no running away from, the fact that the lies these three physicians spread resulted in the miscarriage — the stillbirth — the death inside the womb, of thousands of babies due to the their expectant mothers getting COVID-19 “vaccinated.” The miscarriages — stillbirths — deaths of these children are on their hands.

The Shimabukuro, et al., paper of April 2021, attempted to gloss over the dangers of the COVID-19 bioweapon “vaccines” to pregnant women (https://nejm.org/doi/full/10.1056/NEJMoa2104983, “Preliminary Findings of mRNA Covid-19 Vaccine Safety in Pregnant Persons”, Tom Shimabukuro, et al; April 2021. At the time this paper was published, Dr. Shimabukuro was the director of the Immunization Safety Office of the CDC. Please see the screenshot of the “Results” section of the Abstract from the original April 2021 paper; followed by the screenshot of the “Correction” version of the same “Results” that was published on 8 September 2021:

However, neither the original Shimabukuro, et al., paper, nor the “corrected” paper, apparently mention the fact that, of the 3958 reported pregnancies in COVID-19 bioweapon “vaccinated” women (“pregnant persons”), only 827 pregnancies were “completed.” Which leaves 3,131 reported pregnancies that were NOT “completed” in these “vaccinated” women; in other words, about a 79.2% non-completed pregnancy rate in these “vaccinated” women — not the 12.6% negative pregnancy outcomes rate stated in the paper.

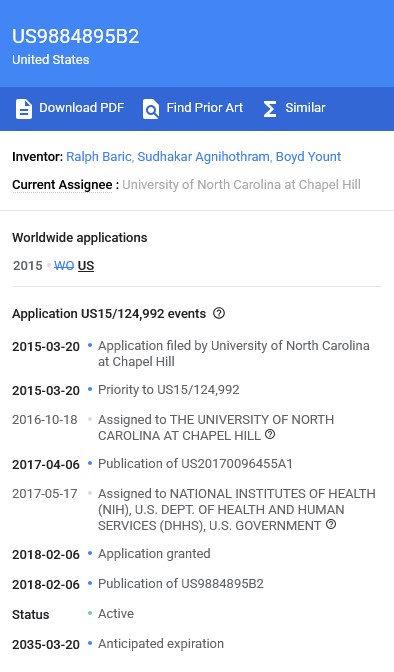
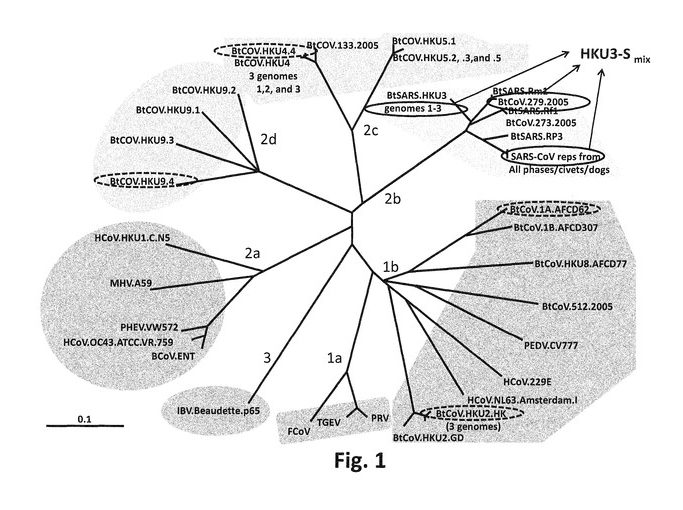
Yours Truly now turns to US9884859B2, the Patent granted in October 2015 to Dr. Ralph Baric, PhD, of the University of North Carolina, Chapel Hill, for his “invention” of the “template virus” for SARS-CoV-2. The following screenshots, below, are from this Patent: the Title and Dates Summary; the Figure 1; the paragraph from the Detailed Description of the Invention regarding the use of subgroup 1a-type viruses in the “invention”; the citations from the Patent for viruses used in the subgroup 1a section on the Figure 1 “virus tree chart”

Look at the phrase from the paragraph regarding subgroup 1a viruses that can be used in Dr. Baric’s “invention”: “…, as well as any other subgroup 1a coronavirus now known (e.g., as can be found in the GenBank (R) Database or later identified, and any combination thereof.” This means that ANY subgroup 1a-type of coronavirus can be used in the SARS-CoV-2 “template virus” that Dr. Baric “invented.” How does this tie into the miscarriages, the stillbirths, the live births of infants who are weak / low weight, and so on, to expectant mothers who were “vaccinated” with a COVID-19 bioweapon “vaccine”? First: Yours Truly believes that Dr. Ralph Baric shared information contained in US9884895B2 with Dr. Zheng-li Shi of the Wuhan Institute of Virology (as she was working on various coronaviruses, including SARS-CoV); and/or, he shared samples of certain subgroup 1a viruses with Dr. Shi. Second: Yours Truly believes that US9884895B2 was the “template virus” for SARS-CoV-2 “foundation” that ultimately became the “modRNA” (aka “mRNA”) used in the COVID-19 bioweapon “vaccines.” Regarding the citation in the Patent above, about Porcine Respiratory and Reproductive Virus (also called Porcine Reproductive and Respiratory Syndrome), please see the following screenshot from this website: https://www.merckvetmanual.com/generalized-conditions/porcine-reproductive-and-respiratory-sundrome/porcine-reproductive-and-respiratory-syndrome:

Regarding the Figure 1 of the Patent, please refer to the “1a” portion of the “virus tree.” There are three viruses listed: FCoV (Feline coronavirus); TGEV (Transmissible Gastroenteritis virus [swine]);, and, PRV (Pseudorabies virus [swine].) Please see the screenshot about PRV, below, from this website: https://merckvetmanual.com/nervous-system/pseudorabies/pseudorabies-in-pigs:

Why was Dr. Baric including at least two viruses that cause reproductive failure in swine in his Patented “template virus” for SARS-CoV-2 “invention” — Porcine Reproductive and Respiratory Virus (PRRV, aka PRRS); and, Pseudorabies virus (PRV)? Why was Pseudorabies virus (PRV) the only one listed on Fig. 1 from the Patent US9884895B2, unless this entire “virus tree” graphic is only listing examples of the various subgroup viruses that could be utilized in Dr. Baric’s Patent “template virus” for SARS-CoV-2 “invention”?

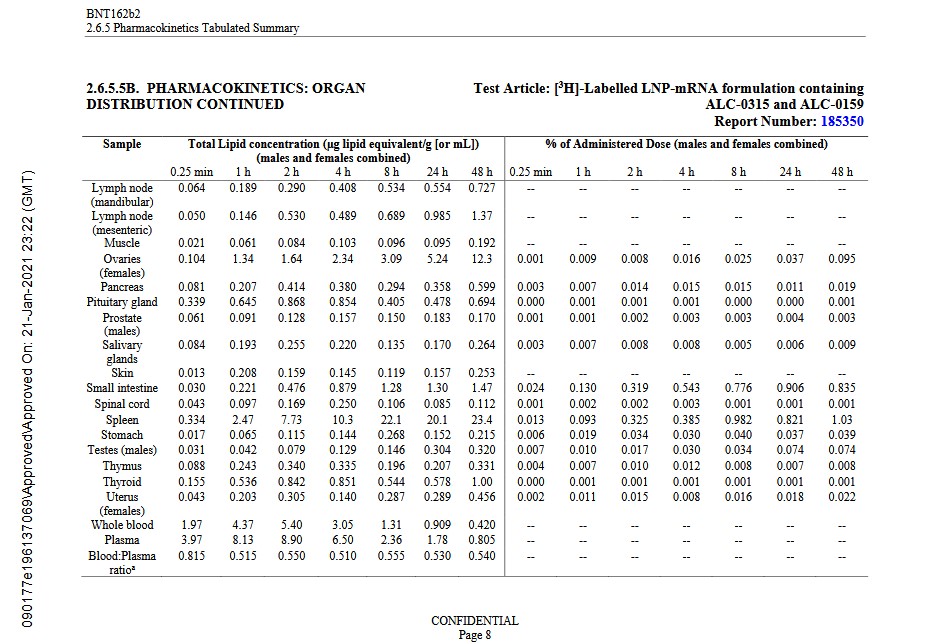
Yours Truly turns to one final item: Page 8 of the Pharmacokinetics Tabulated Summary report on BNT162b2 (COMIRNATY) given to the FDA by Pfizer-BioNTech in 2021 (https://icandecide.org/wp-content/uploads/2022/03/125742_S1_M2_26_pharmkin-tabulated-summary.pdf. Look at the BNT162b2 accumulations (assisted by the ALC-0159 and ALC-0315 lipid nanoparticles in this “vaccine”) in the Ovaries (12.3) and in the Uterus (0.456) in the Wistar lab rats.) [Note: this is aside from the fact that the COVID-19 bioweapon virus itself, as “invented” by Dr. Baric, has these two female fertility and pregnancy killers included in it — meaning that a female of childbearing age could, in theory, become infected with the virus itself, recover, but potentially have problems in terms of conception, carrying the fetus through pregnancy, and delivering a healthy child. The difference here, in Yours Truly’s opinion, is that if the female is non-COVID-19 bioweapon “vaccinated”, that person still has a relatively intact natural immune system to help fight off the virus itself and its negative effects. A “vaccinated” female’s natural immune system is damaged or destroyed by the COVID-19 bioweapon “vaccines” that she took. The mechanism of these “vaccines” is to induce a constant state of “fake COVID-19 virus infection” in the “vaccinated” persons’ body. In addition, the lipid nanoparticles ALC-0159 and ALC-0315 (in the Pfizer-BioNTech “vaccines”); and, the SM-102 (in the Moderna “vaccines”) move the ingredients of these injectables into every cell in the “vaccinated” person’s body.)] Page 8 is below:

Now, tie these accumulations in with the information above regarding the inclusion of at least two types of swine virus that cause reproductive failure (PRRV, aka PRRS; and, PRV) into Dr. Baric’s “template virus” Patent for SARS-CoV-2, US9884895B2. To Yours Truly, the combination of these inclusions; plus, the documented accumulations in the ovaries and the uteruses of the Wistar lab rats injected with BNT162b2 (COMIRNATY); and which version, by the way, was the same version for which the FDA granted the initial EUA for use in the United States on 11 December 2020, and which version is still the “foundational version” still used in all “descendant versions” of COMIRNATY since then; plus, the documented reports of miscarriages — stillbirths — live births with weak and/or low weight infants, involving pregnant females who were injected with modRNA COVID-19 bioweapon “vaccines”: all add to up something that is not a “coincidence.” It is, instead, a situation that cannot be ignored or minimized. It is, instead, a situation that must be fully investigated by the highest levels of government. In Yours Truly’s opinion: Pfizer-BioNTech; Moderna; and, Novavax, MUST be compelled to disclose the EXACT ingredients of the modRNA in their respective COVID-19 bioweapon “vaccines”, the AMOUNTS of these ingredients, and the EXACT formulations of their respective COVID-19 bioweapon “vaccines.” In addition, the above manufacturers MUST be compelled to disclose any and all communications with Dr. Baric regarding US9884895B2, and the use of any of the information in that Patent in their respective COVID-19 bioweapon “vaccines” formulations and manufacture.

THE USE OF ANY COVID-19 BIOWEAPON “VACCINE” ON PREGNANT FEMALES, AND ON FEMALES OF CHILDBEARING AGE, MUST STOP IMMEDIATELY.

Peace, Good Energy, Respect: PAVACA

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 8.7.2026 Open Thread: More on US9884895B2, Dr. Ralph Baric’s Patented “Template Virus” for SARS-CoV-2: Part One

The free image of the word Patent for today’s offering header is courtesy of Vecteezy and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.

Special Note: the appellation viral biological weapon (VBW)© as a more accurate description of the SARS-CoV-2 “virus” (COVID-19 “virus”) is copyrighted by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.)

>>>>>>>>>>>>>>>>>>>>

Yours Truly has written regarding the “invention” by Dr. Ralph Baric, PhD, the now-retired head of the Baric Lab at the Gillings School of Global Public Health at the University of North Carolina, Chapel Hill, of the “template virus” for SARS-CoV-2 (the COVID-19 “virus”), here: https://www.theqtree.com/2026/01/09/health-friday-1-9-2026-open-thread-the-baric-files-part-four-ecohealth-alliance-wuhan-institute-of-virology-dr-zheng-li-shi-the-template-virus/. This “invention” by Dr. Baric was almost totally funded through grants issued from the National Institutes of Health (NIH) via its National Allergy and Infectious Diseases (NIAID) division (Dr. Anthony Fauci, MD, NIAID Director from 1984 until his retirement in 2022.) This particular Health Friday series will focus on certain items in US9884895B2. Today’s offering is not intended to be a science lecture: it is to illustrate a certain aspect of the research journey of the “Master Designer” of SARS-CoV-2: Dr. Ralph Baric, PhD.

>>>>>>>>>>>>>>>>>>>>

The SARS-CoV-2 “virus” (COVID-19 “virus”) is actually a lab-created viral biological weapon (VLBW)©. It is nothing ever found in nature: it is a lab-created construct. This lab-created “virus” is a construct of gene code pieces from multiple animal coronaviruses, among them: RaTG13 bat coronavirus (which may also be a lab-created coronavirus; see the Bostickson and Ghannam paper link, below in today’s offering); SHC014 bat coronavirus; WIV1 bat coronavirus; VEEV (Venezuela Equine Encephalitis Virus); MP789 Pangolin coronavirus; and, TGEV (swine gastroenteritis virus.) The gene code pieces of the SHC014 bat coronavirus, the WIV1 bat coronavirus, the VEEV, and the TGEV — among dozens of other types of coronaviruses, including the MERS virus (Middle Eastern Respiratory Syndrome virus) — were spliced into Gain-of-Function viruses that Dr. Baric was experimenting with, to create his “invention” of the “template virus” for SARS-CoS-2, and for which Dr. Baric applied for a Patent in March 2015. It is this writer’s belief that Dr. Baric transmitted information related to the “invention” of US9884895B2, along with other items, to Dr. Zheng-li Shi of the Wuhan Institute of Virology (where she was already working on a SARS-type lab-created virus), in order for Dr. Shi to complete further “enhancement” of the “template virus” that Dr. Baric had lab-created. Yours Truly further believes that Dr. Baric and Dr. Shi had been in collaboration regarding this SARS-type virus “enhancement” since 2013, if not earlier. What is now known is that Dr. Shi did further “enhance” the SARS-type virus that she had been working on with more, and more lethal, coronaviruses: the MP789 Pangolin coronavirus; the 7896 bat coronavirus; and, perhaps others. In the case of the 7896 bat coronavirus, there was a concerted effort by the Communist Chinese version of the CDC to cover up the use of this particular coronavirus. Please see: https://www.researchgate.net/publication/350515493_2_INVESTIGATION_OF_RaTG13_AND_THE_7896_CLADE, William Bostick and Yvette Ghannam, 2021; and, https://usrtk.org/wp-content/uploads/2021/10/Latinne-et-al-3.pdf, the Accession Listing for MN312322, the 7896 bat coronavirus, at NCBI, as an inclusion into the SARs-CoV-2 “virus.” This Accession is on Page 77 (of 576) of File #3 of the section “Latinne at al. (2020) and the National Center for Biotechnology Information (NCBI)”, found here: https://usrtk.org/covid-19-origins/foi-documents-on-origins-of-sars-cov-2-risks-of-gain-of-function-research-and-biosafety-labs/. Yours Truly believes that, since Dr. Shi was undoubtedly taught by Dr. Baric about how to use his other “invention”, the “No-see-um” invisible gene-splicing method for Gain-of-Function experiments (https://journals.asm.org/doi/10.1128/jvi.76.21.11065-11078.2002, “Systematic Assembly of a Full-Length Infectious cDNA of Mouse Hepatitis Virus Strain 59”, B. Yount, M.R. Dennison, S.R.Weiss, R.S. Baric; November 2002), this method was used to insert the above-mentioned MP789 Pangolin coronavirus, the 7896 bat coronavirus, and likely other gene codes from other types of coronaviruses, into the SARS-type virus that Dr. Shi was already working on. Yours Truly believes that this (likely not-quite-“finished” enhanced SARS-CoV-2 (COVID-19) “virus” — this lab-created viral biological weapon (VBW)© was released into the world from the Wuhan Institute of Virology lab in late 2019. An aside: the 7896 bat coronavirus which is also included in the SARS-CoV-2 “virus” (listed as a clade of the HKU2 Rhinolophus bat coronavirus) as Accession Number MN312322 (see above links) — attacks the lungs and has a 50% death rate in humans (Bostickson and Ghannam, 2021, cited above.)

>>>>>>>>>>>>>>>>>>>>

Yours Truly turns to the NCBI PubChem entry for the breakdown of what appears to be the “main elements” that Dr. Ralph Baric included in his “invention” of the SARS-CoV-2 “virus” (COVID-19 “virus”) “template virus”, which Patent application was filed in March 2015. The PubChem entry is here: https://pubchem.ncbi.nlm.nih.gov/patent/US-9884895-B2, “Methods and compositions for chimeric coronavirus spike proteins”, Ralph Baric, Boyd Yount, Sudhakar Agnihothram. The hyperlinked list of elements, chemical compositions, and so forth, is on the right side of this page. Yours Truly clicked on the section “Linked Genes”, and found a gene numbered 5970, called “RELA — RELA proto-oncogene, NF-kB subuit (human).” Below is a screenshot from section 9 “Linked Genes”:

Yours Truly clicked on the 5970 hyperlink. This led to another page, https://pubchem.ncbi.nlm.nih.gov/gene/5970. Please see the screenshot, below, of the Title and Summary of this gene:

**** Notice the multiple types cancers this gene, 5970, is involved in the establishment of: ductal carcinoma in situ; lung cancer; lymphoma; renal cell carcinoma; multiple other types of carcinoma; cervical carcinoma in situ. This gene is also involved in the establishment of other types of diseases, including diseases of the prostate. Why was Dr. Ralph Baric splicing gene 5970 into his “invention” of the SARS-CoV-2 “Template virus”?

Yours Truly then clicked on the section 9 “Cell Lines” hyperlink on the 5970 gene page. This took one to: https://pubchem.ncbi.nlm.nih.gov/gene/5970#section=Cell-Lines, and then clicked on the “COV18” hyperlink. From there, one then clicked on subsection 4, “Diseases.” Please see the screenshot, below, of subsection 4:

That’s correct — High grade ovarian serous adenocarcinoma. Which, again, raises the question: Why was Dr. Ralph Baric inserting gene code pieces from gene 5970, which has multiple connections to potentially causing cancer in the human body, into his SARS-CoV-2 “template virus invention”, US9884895B2? And gene 5970 is only one of dozens of genes that had code pieces inserted into various “permutations” of this “invention”, US9884895B2. Which also means, in Yours Truly’s opinion, that the SARS-CoV-2 “virus” (actually, a viral biological weapon (VBL), see above) can also have the potential to cause cancers of various types in persons who become infected with this viral biological weapon (VBL.)

Yours Truly then went to Page 8 of the BNT162b2 Pharmacokinetics Tabulated Summary report that Pfizer-BioNTech gave to the FDA on 21 January 2021 (https://icandecide.org/wp-content/uploads/2022/03/125742_S1_M2_26_pharmkin-tabulated-summary.pdf.) Please see the screenshot of Page 8, below:

Look at the BNT162b2 accumulation (assisted by the lipid nanoparticles ALC-0159 and ALC-0315 in BNT162b2) in the OVARIES of the Wistar lab rats 48 hours post-injection: 12.3.

>>>>>>>>>>>>>>>>>>>>

What is a “proto-oncogene?” Please see the screenshots, below, from this article: https://www.nature.com/scritable/topicpage/proto-oncogenes-to-oncogenes-to-cancer-883/, Heidi Chial, PhD, 2008:

Yours Truly then went back to gene 5970, RELA — RELA proto-oncogene, NF-kB, subunit (human), and did some more digging. I found this: https://www.uniprot.org/uniprotkb/A0A087x0W8/variant-viewer. There are 448 variants of this gene. Many are listed as “Variant of uncertain significance.” However, for example, Variant 372 causes “Mucocutaneous ulceration, chronic”, and is also listed as “Pathogenic.” Another example: Variant 264 causes “RELA-related disorder” and is also listed as a “Variant of uncertain significance.”

>>>>>>>>>>>>>>>>>>>>

All of the foregoing in today’s offering is not to incite a “frisson” of “this is too much information and it’s too detailed.”

All of the foregoing in today’s offering is, instead, to illustrate the “layered permutations” of just ONE of the elements contained in Dr. Ralph Baric’s “template virus” for SARs-CoV-2, which he Patented as US9884895B2 in October 2015 — about a month before he and Dr. Zheng-li Shi (which whom Dr. Baric was working since at least 2013, if not earlier) published their “Bait Circulating Coronavirus” paper of November 2015.

All of foregoing in today’s offering is, instead, to illustrate the fact that the SARS-CoV-2 “virus” itself (which is actually a viral biological weapon (VBW)©) has the potential (either from gene 5970, or from other proto-oncogenes that may be included in the “invention” by Dr. Baric) to cause cancer. This is entirely aside from the fact that the modRNA COVID-19 bioweapon “vaccines” can, and do, cause cancer de novo; and/or the aggravation of previous cancer that was under treatment prior to COVID-19; and/or the re-establishment of cancer that was in remission prior to COVID-19 — in “vaccinated” persons.

Dr. Ralph Baric, PhD, does not have a “pre-emptive pardon” from the “President Biden auto-pen.” Dr. Ralph Baric’s Gain-of-Function experiments, which ultimately resulted in the Patent US9884895B2, Dr. Baric’s “invention” of the SARS-CoV-2 “template virus”, in 2015, were funded by Dr. Anthony Fauci of the NIAID as far back as the mid-1980s. Dr. Baric has close ties with the Wuhan Institute of Virology and with the United States Defense Department. It is time for Dr. Baric to be brought to account for his activities. Dr. Baric needs to answer questions, under oath, such as: What information, if any, was shared with Pfizer-BioNTech (PfizerUSA), and/or with Moderna, from Patent US9884895B2? What information, if any, was shared with Pfizer-BioNTech (PfizerUSA), and/or with Moderna, regarding the possible inclusion of proto-oncogenes listed in Patent US9884895B2 into these companies’ modRNA COVID-19 bioweapon “vaccines”? What information, if any, was shared with DARPA, BARDA, NIAID, or any other United States government entity, from Patent US9884895B2?

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet in today’s offering, the ideas and/or opinions above are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 7.31.2026 Open Thread: Dr. Fauci and the Hearing

The free image of a Senate hearing is courtesy of https://www.senate.gov/ and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated content in today’s offering will be cited as such. If readers wish to post AI-generated items to today’s discussion thread, they must cite their source. Thank you.

Special Note for today’s offering: In no way is the content of this post to be construed as diagnosis (medical, legal, or otherwise) of Dr. Anthony Fauci. Yours Truly presents her ideas and opinions only. Thank you.

>>>>>>>>>>>>>>>>>>>>

Dr. Anthony Fauci, retired Director of the National Institute of Allergy and Infectious Diseases division (NIAID) of the National Institutes of Health (NIH), both of the United States Health and Human Services Department (HHS) of the federal government, went to Capitol Hill on Wednesday 29 July 2026, to testify to a Senate committee hearing chaired by Sen. Dr. Rand Paul (R-KY.) The video of the hearing is here: https://www.hsgac.senate.gov/hearings/testimony-of-anthony-fauci/. Yours Truly commented on this hearing, both while it was in session, and afterwards, here: https://www.theqtree.com/2026/07/29/kmag-daily-thread-20260729-data-centers/. After Dr. Fauci read his “opening statement” to the committee, he spent the rest of the hearing refusing to answer any any questions posed to him by committee hearing members, citing the Fifth Amendment to the United States Constitution. Dr. Fauci invoked the Fifth Amendment a total of one hundred and eleven times during the hearing in response to questions from committee hearing members. After closing statements were made by various committee hearing members, Sen. Dr. Paul stated that he would seek a vote regarding Contempt of Congress by Dr. Fauci next week, and then adjourned the hearing.

There was extensive media coverage of the committee hearing, and of Dr. Fauci’s repeated refusals to answer questions posed to him by committee hearing members by his invoking of the Fifth Amendment. This coverage either praises Dr. Fauci, or excoriates him. Yours Truly will, instead, focus on three concepts: Fraudulent activity / Lying; Manipulation / Control; and, Mindset (Narcissism, among other aspects.) Some of these aspects appear to present in combination (examples: Lying and Control; Fraudulent Activity and Narcissism.)

Sen. Dr. Rand Paul (R-KY) released multiple entries made by Dr. Anthony Fauci in his “personal diary”, a diary that Dr. Fauci wrote on computers owned by the Federal government. Multiple entries on this “personal diary” conflict with, or contradict, statements made by Dr. Fauci in public, including in sworn testimony before Congress. The “personal diary” entries by Dr. Fauci are here: https://www.paul.senate.gov/wp-content/uploads/2026/07/2026.07.26_Tonys-Diary-Package.pdf.

Fraudulent Activity / Lying:

Dr. Fauci “fraudulently claimed” that Ivermectin did not work to prevent or cure COVID-19:

Dr. Fauci lying regarding his “not knowing the authors of the “Proximal Origin” paper”:

Lying and Control:

Please see: https://www.2ndsmartestguyintheworld.com/p/psyop-19-coverup-dr-faucis-testimony, “PSYOP-19 COVERUP: Dr. Fauci’s Testimony Preview: Conning President Trump, Lying About Lockdowns, Malignant Narcissism, Epstein, Bill Gates, Fatality Rate Fraud, Hydroxychloroquine Suppression & More”, 27 July 2026.

Control:

Dr. Fauci suffered a pulmonary infarction in July 2021, several months after he took the Moderna modRNA COVID-19 bioweapon “vaccine” (mRNA-1273.) He was treated for this incident. He kept this situation out of public knowledge — when he needed to, in Yours Truly’s opinion, gone public with the situation as an illustration of the dangers of this “vaccine.” Please see: https://kirschsubstack.com/p/tony-fauci-was-vaccine-injured, 30 July 2026. Please see the screenshot of the Summary of Mr. Kirsch’s article, below:

Fraudulent activity, Control, Narcissism:

Sen. Josh Hawley (R-MO) detailing, in the Senate hearing on 29 July, how Dr. Fauci used government time, government resources, and government employees to assist in his being awarded honors; some of which awards included money:

Mindset:

Yours Truly presents these: One: https://www.medicalnewstoday.com/articles/sociopath-vs-narcissist, “Sociopath vs. narcissist: What is the difference?”, Amy Murnan, medically reviewed by Lori Lawrenz, PsyD, 30 October 2024. Please see the screenshot from this article, below:

And, Two: https://www.psychologytoday.com/us/basics/psychopathy/, reviewed by Kaja Perina, 24 October 2025. Please see the screenshot from this article, below:

Yours Truly will provide two examples of Dr. Fauci’s mindset, which, in this writer’s opinion, may present as “socio–narcissism verging on possible psychopathy”: First, his experiments on AIDS-infected babies and young children (some of whom were orphans) in New York state. Please see this article, by our good Aubergine, from 2022: https://www.theqtree.com/2022/01/03/who-or-what-killed-all-of-these-children-the-world-deserves-to-know/. There is this link in her article, proving that these experiments did occur, and that babies and children died: https://www.thegatewaypundit.com/2021/12/rfk-jr-reporter-found-monument-dead-orphans-tortured-killed-monster-fauci-video/, 20 December 2021.

Second, the experiments on beagle puppies, in which their vocal cords were cut before the dogs were placed in cages to be exposed to sandflies (which would eat them alive): experiments which were allegedly funded through Dr. Fauci: https://insiderpaper.com/fauci-dog-beagles-funding-cage-sandflies/, “Fauci under fire for ‘dog experiments’ in which beagles were kept in cages to be eaten by hungry sandflies {UPDATE: Agency responds]”, Brendan Taylor, 26 October 2021. Please see the screenshot from this article, below, which was the “response” from NIAID on this situation:

In Yours Truly’s opinion, Dr. Anthony Fauci is not a person “who has lost his way”, according to Dr. Peter A. McCullough (https://www.thefocalpoints.com/p/breaking-guilt-ridden-anthony-fauci, “BREAKING — Guilt-Ridden Anthony Fauci Pleads the Fifth Amendment 111 Times”, 29 July 2026. Dr. Anthony Fauci chose his path. In Yours Truly’s opinion, Dr. Fauci is not “guilt-ridden”: in fact, something quite different: he presents as a person who shows, by his words and deeds, that he has no concept of guilt, no concept of personal responsibility, and no concept of either empathy or compassion.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items that are available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinion in today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 7.24.2026 Open Thread: HHS Still Funding Gain-of-Function Experiments: on the Avian Influenza Virus; on HIV: and, with the Wuhan Institute of Virology

The free vintage image of a scientist working in a laboratory for today’s header is courtesy of Adobe Stock and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie;, and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.

>>>>>>>>>>>>>>>>>>>>

HHS is Still Funding Gain-of-Function Experiments on the Avian Influenza Virus

Yours Truly begins here: https://jonfleetwood.substack.com/p/hhs-funds-experiments-determining, “HHS Funds Experiments Determining How to Make H5 Influenza More Pathogenic: Journal ‘Science'”, 1 July 2026. Please see the screenshot from this article, below:

The paper cited in the Fleetwood article is here: https://doi.org/10.1126/science.adr6632, “Polymerase trapping as the mechanism of H5 highly pathogenic avian influenza virus genes”; Mathis Funk, et al.; 12 March 2026. This paper was Received on 11 July 2024; Resubmitted on 17 July 2025; Accepted on 21 November 2025; and, Published in print on 12 March 2026. This paper was funded, in part, by NIH / NIAID grants: HHSN2722014-00008C; 75N93201C00014; and, 1R01AI177487. These grants were awarded to Ron A.M. Fouchier and to Mathilde Richard. Dr. Richard and Dr. Fouchier work at Erasmus Medical Center, Rotterdam, The Netherlands. This raises important questions: One: Why was / is NIH-NIAID funding research performed at a university outside of the United States?; and, Two: Why was / is NIH-NIAID continuing to fund research into making the H5 Avian Influenza virus more dangerous and deadly? Please see the screenshots, below, from the AAAS website (https://www.science.org/, American Association for the Advancement of Science) for this paper:

Then, after Gain-of-Function experiments are performed by Funk, et al., with the furin cleavage site of the H5 Avian Influenza virus, they apparently concluded that this virus can become more pathological. Please see the screenshot, below, from the AAAS website for this paper:

The NIH-NIAID grants for this paper were also solicited by Mathis Funk, the lead author of the paper, who was associated with Erasmus University. Mr. Funk passed away on 28 November 2024, at the age of 34. The paper mentions his passing with the statement that he “left the world too soon.”

Yours Truly did some more digging on the NIH-NIAID 1R01AI177487 grant listed above. In addition to the original grant, Dr. Mathilde Richard was also awarded a “sub-grant”, 1R01AI177487-01, on 1 August 2023, with a “Project end date” of 31 July 2028. Please see: https://reporter.nih.gov/search/qKxmt58hnkKa7rYIA1rSKg/projects. The NIH-NIAID employee who is the “Contact” for this grant is Brooke Allison Bozick, PhD. She is listed as “Program officer, Influenza and Rhinovirus Pathogen Biology and Clinical Research” at https://www.niaid.nih.gov/about/respiratory-disease-branch-contacts. Ms. Bozick has been an employee of HHS (NIH – NIAID) since at least 2019, including work involving CEIRR (Centers of Excellence for Influenza Research and Response [NIAID].) This raises the question: Why is NIH – NIAID funding the Gain-of-Function work of Dr. Richard all the way up to 31 July 2028?

Yours Truly did some more digging on the HHSSN27220140008C grant listed above. This grant been active since at least 2016. In fact, this grant ALSO funded Gain-of-Function research at the (infamous) Dr. Yoshihiro Kawaoka lab for research into Avian Influenza at the University of Wisconsin-Madison: https://wisc.edu/h7n9-influenza-is-both-lethal-and-transmissible-in-animal-model-for-flu/, Kelly April Tyrrell, 19 April 2017. The mention of the HHSN grant is at the end of the article.

Yours Truly did some more digging on the NIH-NIAID 75N93021C00014 grant listed above. This grant has been active since at least 2021. In fact, this grant ALSO funded Gain-of-Function research on Avian Influenza at the Kawaoka lab at the University of Wisconsin; at the University of Tokyo; and, at Cairo University, Egypt. Please see: https://doi.org/10.1016/j.ebiom.2025.105842, “Susceptibility and shedding in Mx1 and Mx1- female mice experimentally infected with dairy cattle A(H5N1) influenza viruses”, Asim Biswas, et al.; Published 8 July 2025.

>>>>>>>>>>>>>>>>>>>>

Now, to another item: it appears that HHS, via NIH-NIAID, is still funding Gain-of-Function research involving personnel connected with the Wuhan Institute of Virology (WIV.) Yes, WIV — where Dr. Zheng-li Shi took the samples of the “enhanced with SHC014 bat coronvirus lab-created SARS-CoV-2 virus “template” that was “invented” and Patented by Dr. Ralph Baric, PhD, at his lab at UNC Chapel Hill: for the purpose of FURTHER ENHANCING this “template virus” in order to make MORE PATHOGENIC AND MORE LETHAL. Which SARS-CoV-2 virus was released into the world in late 2019, presumably, as a “lab leak”; and, presumably, before the virus was “finished” via the “enhancement process” at WIV. However, nobody knows for sure whether or not the SARS-CoV-2 virus (that became known as COVID-19) was “finished”, or if it was “still in the finishing process” when it was released. The HHS grants involved are: K08AI183990 (NIH-NIAID; granted in 2024 to the University of Washington, to John K. Bui); R01AI174304 (NIH-NIAID; granted in 2023 to the University of Washington, to Andre Michael Lieber); and, R01HL130040 (HL-NHLBI-NIH-HHS; granted in 2019, with continuing funding, to the University of Washington, to Andre Michael Lieber.)

The paper that was Epublished on 13 March 2026, funded by these grants, is here: https://doi.org/10.1016/j.ymthe.2026.03.018, “In vitro and in vivo base editing of CCR5 in hematopoeitic stem cells confers HIV-1 resistance”, Anna K. Anderson, Chang Li, et al. Chang Li is affiliated with the Wuhan Institute of Virology. Please see the screenshot of the Abstract from this paper, below:

And, from the paper, the affiliation of Chang Li with the Wuhan Institute of Virology, from the Affiliations and Notes drop-down section:

This raises the question: Why is this research, while worthy and can produce significant positive results, has anyone from the Wuhan Institute of Virology involved?

In summary: the United States government, via HHS (NIH-NIAID) is still using taxpayer money to fund Gain-of-Function research on the Avian Influenza virus in The Netherlands, in Japan, and in Egypt; and, to fund Gain-of-Function research on elements of the Human Immunodeficiency Virus (HIV) that involves personnel from the Wuhan Institute of Virology. None of this is acceptable.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 7.17.2026 Open Thread: ER-100: SV40 Injected Into the Eyes to “Reverse Aging”, Part Two of Two

The free vintage image for the header of today’s offering is courtesy of ClipArt and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health,, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats by Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items will be cited as such in today’s offering. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you. Note: As with Part One, today’s offering is not to be viewed as a “hit piece” on Dr. Sinclair, nor as a denigration on his work. This series is simply focused on aspects of one part of his work.

Part One of this series is here: https://www.theqtree.com/2026/07/10/health-friday-7-10-2026-open-thread-er-100-sv40-injected-into-the-eyes-to-reverse-aging-part-one/. Today’s offering is Part Two of two. There are several areas to cover.

First area: continuation of the presentation of WO/2020069373, the Patent (second Patent) template for ER-100, an “invention” by Dr. David Sinclair, PhD, of Harvard University, et al. The Patent is here: https://patentscope.wipo.net/search/en/WO2020069373. The Title of the Patent is: “WO2020069373 — CELLULAR REPROGRAMMING TO REVERSE AGING AND PROMOTE ORGAN AND TISSUE REGENERATION.”

Section 00542 and Section 00543: “TRE-human OSK – SV40 (SEQ ID NO. 105)” — the gene sequence.

Section 00544 and Section 00545: “EFS-human OSK-SV40 (SEQ ID No: 106)” — the gene sequence.

Section “Additional Embodiments”: there are 151 listings of additional embodiments (combinations) of the ER-100 template: Sections numbered 00578 through 00730.

The following are from the PDF of the Patent.

FIG. 3: circle schematic (vector map) showing the SV40 position. Please see below:

FIG. 7C: schematic of optic nerve crush performed on the lab mice to simulate an eye injury as part of the experiments to lab-create the ER-100 template. Please see the image, below:

FIG. 8A: image of “Regeneration Potential”. Please see below:

Second area: The initial (first) Patent regarding ER-100, also an “invention” of Dr. David A. Sinclair, et al. This patent is found here: https://patentscope.wipo.int/search/en/detail.jsf?docID=WO2020069339&_cid=P22-MRGI4D-39697-1. The Title of this Patent it: “MUTANT REVERSE TETRACYCLINE TRANSACTIVATORS FOR EXPRESSION OF GENES.” The International Filing Date for this Patent was 27 September 2019; the Publication Date was 2 April 2020. Inventors: Sinclair, David, A., et al. Patent Applicants: the President and Fellows of Harvard College, 17 Quincy St., Cambridge, MA, 02138.

The following are short summaries of some of the Claims listed in this Patent:

Claim Number 10: listing of SV40.

Claim Number 22 and Claim Number 23: “SV40-derived terminator sequence.”

Claim Number 30 “Pharmaceutical composition”, followed by Claim Number 33 (includes viruses and AAV); Claim Number 34 (includes SV40); Claim Number 44 (methods) — Claim Number 44 lists doxycyline as “promoting expression of the first transgene.”

Claim Number 45, Claim Number 46, Claim Number 47: 1st and 2nd engineered nucleic elements present in a virus.

**** Claim Number 48: “…wherein the method comprises withdrawing tetracycline.”

**** Claim Number 49: “therapeutically effective amount of [a]-[b] or [a]-[c] are administered to a subject in need thereof.” This refers back to Claim 1 of the Patent above, in which [a]-[b] = the G72 and the G12 positions in the rtTA3 of the composition (SEQ ID NO:11); and, [a]-[c] = the G12 and the F67 positions in the rtTA3 (SEQ ID NO:11.)

FIG. 8B: schematic of SV40 sequence added to TRE3G and presence of ftTA4 element. Please see below:

FIG. 9: circle schematic (vector map) of the “mutant” tetracycline (doxycycline) in the ER-100 composition at position 1000. Please see below (Yours Truly rotated the image which is in the Patent):

FIG. 13: circle schematic (vector map) of SV40 relative to promoter / terminator / editing sequences in the ER-100 composition. Please see below (Yours Truly rotated the image which is in the Patent):

Third area: the Clinical Trial (in recruiting) for ER-100: https://clinicaltrials.gov/study/NCT07290244, “Evaluating ER-100 for Safety in People with Glaucoma or Non-Arteritic Anterior Ischemic Optic Neuropathy (Optic Nerve Conditions.)” Study Start (Actual): 2026-03-02; Primary Completion (Estimated): 2027-05; Study Completion (Estimated): 2032-03; Enrollment (Estimated): 18; Phase: Phase 1. Yours Truly will be discussing items from the “Researcher View” of this clinical trial.

From the “Outcome Measures (Primary)” section: it appears that study subjects will take an 8-week course (56 days) of doxycycline, which is called an “Activation Period.” There are numerous tests that study subjects will take during this “Activation Period”, such as, “Safety Laboratory Tests”, blood tests of various types, etc.; “Changes in Baseline Intraocular Pressure” tests; “Changes in Visual Acuity” tests; among other tests. These tests will be repeated on Day 112 of the study.

From the “Outcome Measures (Secondary)” section: it appears that study subjects have “secondary measures” testing performed during the 56-day doxycycline “Activation Period”, and also repeated on Day 112 of the study, such as: “Change in Baseline in Humphrey Visual Field (HVF) Test Results”; Retinal Nerve Thickness tests; ER-100 viral shedding tests; tests to determine if ER-100 viral DNA has appeared in the aqueous humor of the eye; among others. Study subjects will be followed “for up to 5 years to monitor long-term health and vision outcomes.”

From the “Detailed Description” section: NCT07290244 will have two “study cohorts.” Within each cohort, a “sentinel” study subject will receive an initial dose of ER-100 in an eye. From there, various tests will be performed to investigate whether this dose was tolerated; if it was, the dose will be “approved” by “Data Safety Monitoring Board”, and the other study subjects in the same cohort will receive that dose of ER-100. It appears that increase, or reduction, of the ER-100 dose will also be under the aegis approval of this board.

From the “Intervention” section: this describes the makeup of ER-100. At no point in this section is there any mention of SV40: only the other three “Yamanaka factors” are mentioned (OCT-4; SOX-2; KLF-4.) There is no mention of SV40 being used to “swap out” the fourth “Yamanaka factor” (c-Myc.) Were the study subjects informed that there would be SV40 in the ER-100 dose that would be injected into their eye? https://www.lifebiosciences.com/life-biosciences-announces-first-patient-dosed-in-phase-1-trial-of-er-100-for-optic-neuropathies/, 9 June 2026.

Fourth area: the 2020 paper by David A. Sinclair, et al., the “template” for ER-100: https://ophed.com/system/files/2020/09/s41586-020-2975-4_SMALL.pdf, “Reprogramming to recover youthful epigenetic information and restore vision”, David A. Sinclair, et al.; 2 December 2020.

From the section, “Reset of ageing signatures rather than identity”, the following quotation: “Our first goal was to find a way to reset the epigenome without erasing cell identity. Among the genes expressing the Yamanka factors, Myc is an oncogene that reduces the lifespan of mice (20) and is not required for the initiation of cellular reprogramming (21). We therefore excluded MYC from out experiments…” Based on this, Yours Truly asks this question: If it is true that Myc is an oncogene, and that for this reason, it was excluded from the Sinclair experiments: then why was a known potential cancer promoter element — SV40 — included in the template formulation (composition) for ER-100? Please see below, again from the paper, in the Methods section, subsection “Production of adeno-associated viruses“:

Another quotation from the section cited above: “Next we tested the long-term safety of ectopically expressing OSK in vivo. To deliver and control OSK expression in mice, we engineered a dual adeno-associated virus (AAV) system under the tight control of a tetracycline response element (TRE) promoter (Fig. 1a).”

Referring back to the second Patent for the ER-100 template (WO/2020/069373, presented in Part One of this series), found here: https://patentscope.wipo.net/search/en/WO2020069373, from the Description:

Section 0047: AAV (adeno-associated viruses) may be used in compositions of ER-100. So can any of the recombinant viruses (herpes virus; vaccinia virus; alphavirus; and so on — “alone or in combination.”

Section 00221: list of recombinant viruses.

**** Section 00222 and Table 1.: list of recombinant AAV virus types; Table 1. is the list of AAV serotypes. AAV2 and AAV9 were the serotypes most used in the mice experiments for the December 2020 paper. AAV9 serotypes cross the Blood-Brain Barrier (https://en.wikipedia.org/wiki/Adeno_associated_virus.)

**** Section 00239, Section 00240, Table 2.: OSK (the Yamanaka Factors OCT-4, SOX-2, KFL-4) “…may be activated…in combination with activating an enhancer of reprogramming and/or inhibiting a barrier of reprogramming.” This sentence is highly significant, in light of the Table 2. Non-limiting strategies to enhance reprogramming. One of the “barriers to reprogramming” that would be inhibited is the p53 protein — the very protein that is the “master control” element in the human body to detect and suppress cancer cells. (https://www.thefocalpoints.com/p/breaking-our-censored-study-showing, Nicolas Hulscher, MPH, 19 December 2025; https://www.theqtree.com/author/pavaca1/, search “p53”.)

All of above is aside from the fact that Dr. Sinclair and his co-authors apparently had no issues with simulating eye injury effects in lab mice by crushing the optic nerve of the mice (under anesthesia); and, with simulating glaucoma effects in lab mice by injecting large amounts of microbeads into the eyes of the mice. After which, the mice were evaluated, then eventually euthanized for autopsy. Yours Truly will call these lab mice “Sinclair’s mice” (recall the phenomenon of “Fauci’s beagles” in the NIH-funded experiments with beagle puppies and sand flies: please see https://bfp.org/, the Beagle Freedom Project.)

Yours Truly is not making a case against therapeutic efforts that MAY BE helpful or conclusive in slowing down, stopping, or even reversing, medical conditions such as, certain eye diseases (whether or not these eye diseases are relating to the aging process): therapeutic efforts that MAY work. However, one also believes that therapeutic efforts which include inhibiting the body’s ability to detect and suppress cancer cells (such as, ER-100 containing elements that would inhibit the p53 cancer cell detector / suppressor protein); along with adding a known potential cancer promoter element (SV40) — is not the way to go. Similarly, why would a therapeutic effort need to include potentially using a recombinant virus (such as, ER-100 containing elements of, for example, the herpes virus [see Part One of this series])? If one is reading the December 2020 paper and the Patent WO/2020/069373 for the ER-100 template correctly; and the September 2019 Patent WO/2020/069339 for the “Mutant Reverse Tetracycline Transactivators” correctly — it appears that a tetracycline (doxycycline) is first added into, then removed from, the composition of ER-100, thus requiring a course of doxycyline to be taken by the patient (or, in the case of NCT07290244, the study subjects) to “activate” the “transgenes” in the composition. What happens after the 56-day course of doxycycline that the Clinical Trial NCT07290244 study subjects will take, in order to “activate” the ER-100 in the body? Does the ER-100 just keep working “on its own” inside the body after this course of doxycyline is completed? What happens if the ER-100 stops working, either during the clinical trial, or during the 5-year-follow period? What about the 5-year-long follow timeframe for the NCT07290244 study subjects in general?: Is this out of an “abundance of caution?” Or, is it, so to speak, to use the study subjects as a kind of “long-term human lab mouse study group since actual mice don’t live for 5 years” situation? Is it reasonable to ask: What recourse do the NCT07290244 study subjects have in the event that a serious adverse event occurs to them, either during the study period, or afterwards?

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)

Health Friday 7.10.2026 Open Thread: ER-100: SV40 Injected Into the Eyes to “Reverse Aging”, Part One of Two

The free image of an eye for the header of today’s offering is courtesy of ClipArt and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank You.

ER-100: SV40 Injected into the Eyes to “Reverse Aging”: Part One of Two

There is a certain tenured PhD professor in genetics at Harvard University. His name is David A. Sinclair. He is a native of Australia. Dr. Sinclair, and his lab at Harvard, specialize in the study of what ages human beings. He also studies methods and ways to slow down, or even to stop, this aging process. He is the holder of numerous Patents in this regard. Please see: https://sinclair.hms.harvard.edu/people/david-sinclair. Dr. Sinclair is also the co-founder of a company called Life Biosciences. The company’s statement: “At Life Biosciences, we are on a mission to reverse age-related disease” (https://www.lifebiosciences.com/about-us/about-life-sciences/.) Today’s offering is not to be viewed in any way as a “hit piece” on Dr. Sinclair, or to denigrate his work: instead, it is to present another take on a certain project that he is working on.

Dr. Sinclair believes that he can reverse aging of the human eye (and also, by extension, the mechanisms of human eyesight.) He has been doing research on this subject since before the year 2020. This current year, 2026, Dr. Sinclair, via Life Biosciences, secured $80 Million dollars in funding to put his theories and research into action (https://allsci.com/news/funding/life-biosciences-secures-usd-80-million-series-d-to-advance-er-100-gene-therapy/, 9 April 2026.) The drug that would be used to reverse the aging of the human eye is called ER-100. It is injected into the eyes. ER-100 is immediately hailed as a “breakthrough” drug: including by the alternative COVID-19 treatment entity, Independent Medical Alliance (https://sashalatypova.substack.com/p/dr-ryan-cole-and-independent-medical, “Dr. Ryan Cole and Independent Medical Alliance are now promoting an “immortality elixir” containing and known carcinogen, synthetic SV40!”, 26 June 2026.) Also, in January 2026, Life Biosciences secured an FDA clearance for the drug’s IND application for ER-100 (https://www.lifebiosciences.com/life-biosciences-announces-fda-clearance-of-ind-application-for-er-100-in-optic-neuropathies/, 28 January 2026. IND = Investigational New Drug.) Perhaps predictably, this announcement was heralded as a kind of “turning point” for the FDA: https://lifespan.io/life-bios-trial-is-the-fda-warming-to-rejuvenation/, “Life Bio’s Trial: Is the FDA Warming to Rejuvenation?”, Steve Hill, 8 April 2026.

However — the Life Biosciences press release, cited above, mentions only three of the four “Yamanaka factors” that ER-100 would be be utilizing. This is not a small point. And this is where the story gets interesting.

Dr. Shinya Yamanaka (https://en.wikipedia.org/wiki/Shinya_Yamanaka) discovered proteins, called Transcription Factors, which regulate / control “…the rate of transcription of genetic information from DNA to messenger RNA [mRNA], by binding to DNA sequences” (https://en.wikipedia.org/wiki/Transcription_factor.) Dr. Yamanaka reduced the original number of Transcription Factors from twenty-four down to four: OCT-4; SOX-2; KLF-4; and, c-Myc. It is the c-Myc transcription factor that can “go rogue”, so to speak, and foster the growth of cancer cells: https://www.nature.com/articles/nrc904, “c-MYC: more than just a matter of life and death”, Stella Pelengaris, et al. A screenshot of the Abstract of this article is below:

What is SV40 — the element that has been proven to be in both the Pfizer-BioNTech and in the Moderna modRNA COVID-19 bioweapon “vaccines”? Please see:https://doi.org/10.1093/jnci/91.2.119, “Cell and Molecular Biology of Simian Virus 40: Implications for Human Infections and Disease”, Janet S. Butel, John A. Lednicky; 20 January 1999. Following is a quotation from the Abstract of this paper: “Simian virus 40 (SV40), a polymavirus of rhesus macaque origin, was discovered in 1960 as a contaminent of polio vaccines that were distributed to millions of people from 1955 to early 1963. SV40 is a potent DNA tumor virus that induces tumors in rodents and transforms many types of cells in culture, including those of human origin.” (Bolding mine.)

Why is Yours Truly including a mention of SV40 here? Because SV40 is contained in ER-100. It is the “swapped-out” protein for the fourth Yamanaka Factor, c-Myc, discussed above. The following screenshot, below, is from the Latypova article on ER-100: a screenshot from the 2020 published paper by Dr. David Sinclair, et al. (which will be further discussed in Part Two.) It is also, in Yours Truly’s opinion, the reason why the Life Biosciences press release, cited above, mentions only three of the Yamanaka Factors — it is possible that the company does not want the public to know that SV40, a cancer-causing element, is contained in the drug: especially in light of the fact that more people are starting to realize that SV40 is in the modRNA COVID-19 bioweapon “vaccines” that they have in their bodies:

In other words: the poly(A) “signal” used in the modified AAV-TRE-OSK element in ER-100 is the SV40 poly(A) “signal.” AAV is “adeno-associated virus vector” element; TRE is the tetracycline-derived element; OSK is the acronym for the three Yamanaka Factors OCT-4, SOX-2, and KLF-4 elements. Thus far, then, ER-100 is comprised of AAV (with the SV40 poly(A) tail) + TRE + OSK-4 + SOX-2 + KLF-4. But this is not the entire story. Yours Truly now turns to the Patent “template” for ER-100, which was “invented” by Dr. David A. Sinclair, et al., Patent Number WO2020/069373, filed on 27 September 2019.

The Patent information for WO2020/069373 is found here: https://patentscope.wipo.net/search/en/WO2020069373. The Patent was filed using an international listing, as opposed to a US Patent listing. The International Filing Date was 27 September 2019. The Publication Date was 2 April 2020. The applicamts for the Patent were the President and Fellows of Harvard College, 17 Quincy St., Cambridge, MA, 02138. The funding for the research leading to the Patent was provided through NIAID grants R01AG019719, and R01DK100263. The Title of the Patent is: “1.WO2020069373 – CELLULAR REPROGRAMMING TO REVERSE AGING AND PROMOTE ORGAN AND TISSUE REGENERATION.” The following are Yours Truly’s summaries of some of the listings in the Description of the Patent:

Section 0002: Lists the NIAID grants that funded the “invention.”

Section 0018: mention of SV40: an “expression vector”, also as a “constitutive promoter.”

Section 0019: SV40 amounts used in the composition of the “invention.” These amounts range from AT LEAST 70%, up to 100% “in certain embodiments.”

Section 0033: the “invention” will contain a tetracycline (example: doxycyline.)

Section 0034: the “invention” may include TRE (a Tetracycline Reverse Element (a promoter.))

Section 0035: areas of the body where the “invention” can be used. Examples: eye; ear; nose; mouth; bone; breast; lung; pancreas; cardiac muscle; liver; skin; heart; intestine; testis; ovary.

**** Section 0047: the “compositions” of the “invention” may include “any of the recombinant viruses” (e.g. alphavirus; vaccinia virus; herpes virus; AAV; etc.)

Section 0074: types of ocular diseases the “invention” can be used for.

Section 00109: description of the Gain-of-Function techniques used to produce the “invention.” Section 00100 and Section 00111 further describe the Gain-of-Function techniques used.

Section 00133: the “invention” can also use a “tetracycline-controlled transactivator” called MUTANT REVERSE TETRACYCLINE.

Section 00200: the “invention” will use a nanoparticle called NANOPLASMID. (For more information on NANOPLASMID, please see: https://www.aldevron.com/custom-manufacturing/nanoplasmid/faq.)

Section 00263: start of listings of the “engineered nucleic acids”, “engineered cells”, “engineered proteins”, and “chemical agents” that the “invention” will use to induce “expression” of the OCT-4, KFL-4, and/or the SOX-2 factors cells.

Section 00294: start of discussion and listings of the various cationic lipids that the “invention” will use in “certain embodiments.” Examples: Lipofectin (DOTMA + DOPE); DOTMA separately; DOSPA; DDAB, etc.

Now, from the above, thus far, ER-100 is comprised of: AAV (with the SV40 poly(A) tail) + TRE (Tetracycline Reverse Element promoter) + OSK-4 + SOX-2 + KFL-4 + possibly “any of the recombinant viruses (Section 0047) + a MUTANT REVERSE TETRACYCLINE TRANSACTIVATOR FOR EXPRESSION OF GENES (Section 00133) + NANOPLASMID (Section 00200) + a cationic lipid (Section 00294.)

It also appears, in Yours Truly’s opinion, that ER-100 for use to “reverse aging in the eye” may be only the first application of Dr. Sinclair’s “invention.” It appears that the “certain embodiments” of his “invention” can potentially be used to “reverse the aging” of many areas and organs of the human body.

To be continued in Part Two.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Disclaimer and Notice: Except for the linked URLs and other items in today’s offering that are available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
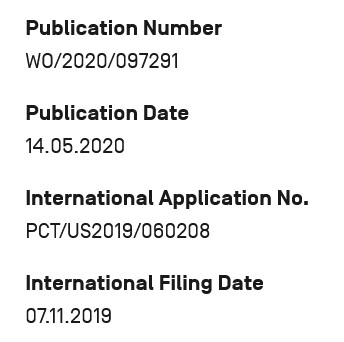
Health Friday 7.3.2026 Open Thread: Health Freedom: An Opinion Piece

The word cloud image of Good Health for today’s offering header is courtesy of Dreamstime and Google Images.

Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited. If readers wish to post AI-generated items in today’s discussion thread, the must cite their source. Thank you.

Health Freedom

Guard Your Health Freedom: The federal government will not do this for you, or for your family. Nor will the American Medical Association, the American Academy of Pediatrics, or the Federal Judiciary. In fact, the federal government (via the Department of Health and Human Services (HHS), the United States military’s biological weapons development and procurement divisions (DARPA and military research labs), and both the House of Representatives and the Senate (funding these activities) are doing all they can to continue the imposition of the COVID-19 bioweapon “vaccines” (gene-therapy injections) on the citizens of the United States of America.

Example: https://jonfleetwood.substack.com/p/hhs-awards-moderna-314-million-for, “HHS Awards Moderna $314 Million for Adult and Pediatric COVID-19 Vaccines: SAM.gov”, 28 June 2026. These awards were granted to Moderna through the CDC Office of Acquisition Services. The awards contracts were granted on 3 June 2026. The awards numbers and amounts are:

Pediatric: Award Number 75D30126D21000 for $285,044,250.

Adult: Award Number 75D30126D21003 for $29,183,000.

Example: https://jonfleetwood.substack.com/p/cdc-awards-pfizer-12-billion-for, “CDC Awards Pfizer $1.2 Billion for More COVID Vaccines: SAM.gov”, 11 June 2026. These awards were granted to Pfizer (PfizerUSA / Pfizer-BioNTech) through the CDC Office of Acquisition Services. The awards contracts were granted on 3 June 2026. The awards numbers and amounts are:

Pediatric: Award Number 75D3012621001 for $735,720,598.

Adult: Award Number 75D30126D21004 for $505, 272, 000.

The CDC Office of Acquisition Services is located at 1600 Clifton Rd., Atlanta, GA, 30333. The most current (as of 20 June 2024) organization chart for the CDC’s Office of Financial Resources (of which the Office of Acquisition Services is part) is listed here: https://www.cdc.gov/about/media/pdfs/ofr-org-chart.pdf. There are NO EMPLOYEE NAMES associated with ANY of the offices listed on this chart. None of the awards contracts listed above have any contract details, other than the date of the awards, the company name that is the awardee, and the contract number. These awards are examples of how the current HHS is operating. So much for “oversight” and “transparency” in the current HHS. Who exactly signed the awards documents for HHS? Who signed the acceptance documents at Pfizer (PfizerUSA / Pfizer-BioNTech) and at Moderna? Did HHS Sec. Kennedy, Jr., know about these awards in advance and signed off on them? Was he told after the fact and then signed off on them? A screenshot of one of the “information pages” for one of these awards is below. My apologies for the length of the screenshot — one has to see this to believe it:

Who is Jariya Taylor, the “Primary Point of Contact” for this award? Apparently, via Internet search, this person is a “Procurement Officer” with the CDC Office of Acquisition Services. Who is Chad Turner, the “Alternative Point of Contact” for this award? Apparently, via Internet search, this person is also a “Procurement Officer” with the CDC Office of Acquisition Services. How long have they worked for the CDC? What are their qualifications to be “Procurement Officers”? Are these employees the exact ones who signed the awards documents for HHS / CDC for the Pfizer (PfizerUSA / Pfizer-BioNTech) and the Moderna awards? Why does the award state, “Inactive” at the top of the document? What happened to the money? Who at Pfizer (PfizerUSA / Pfizer-BioNTech) “solicited” this award? Or, did the CDC, via Jariya Taylor and Chad Turner, reach out to the company to “be aware of an opportunity (award)”? Does the reader see how the game is played between Big Pharma, the CDC — and all using taxpayer monies?

Another point: How do the CDC awards to Moderna for their 2026-2027 modRNA COVID-19 bioweapon “vaccines” (gene-therapy injections) square with THIS story?: https://www.cidrap.umn.edu/misc-emerging-topics/moderna-chief-company-won-t-invest-new-late-stage-vaccine-trials, “Moderna chief: Company won’t invest in new late-stage vaccine trials”, Stephanie Soucheray, MA, 26 January 2026. Moderna CEO, Stephane Bancel, made these remarks at the WEF summit in Davos in January. Direct quotation from the article, from Mr. Bancel: “You cannot make a return on investment if you don’t have access to the U.S. market.” Direct quotation from the article: “He [Mr. Bancel] said the vaccine market in the United States is much smaller as more anti-vaccine guidelines have become the norm.” If that is so, then WHY did the CDC “create the opportunity” to award Moderna $314 Million to develop and market the company’s 2026 – 2027 modRNA COVID-19 bioweapon “vaccines” (gene-therapy injections)?

Example: HHS Sec. Robert F. Kennedy, Jr., wrote and issued a “new” charter for the CDC’s ACIP panel (Advisory Committee on Immunization Practices) in April 2026. This was after Federal Brian E. Murphy disbanded the former ACIP panel, every recommendation made by this panel from June 2025 to March 2026, and re-instituted the old CDC Childhood and Adolescent Immunization Schedule that has a total of 72 “vaccine” injections to be administered to children age 0 up to age 18. HHS Sec. Kennedy, Jr., is an attorney. However, it appears that he was not either informed of, or paying attention to, the minutiae of drawing up federal regulations. The result is that the “new” ACIP charter was quietly withdrawn in May 2026 (https://www.medpagetoday.com/infectiousdisease/vaccines/121349, “HHS Withdraws New Rules for CDC Vaccine Panel”, Terrence Rudd, 19 May 2026); and, replaced it with yet another “new” ACIP panel charter (https://www.cidrap.umn.edu/childhood-vaccines/new-acip-charter-could-allow-rfk-jr-further-restrict-vaccine-access-critics-say, Liz Szabo, MA, 26 June 2026.)

Meanwhile, the re-instituted old CDC Childhood and Adolescent “vaccination” schedule — the one that “recommends” 72 total “vaccine” injections in children age 0 to age 18 — is here: https://www.cdc.gov/vaccines/hcp/imz-schedules/child-adolescent-age.html. There is a mealy-mouthed “we’re sorry, but we have to do this because a Federal Judge ordered us to” CDC “excuse” on this webpage, above the immunization schedule hyperlink. And, recalling that it was the American Academy of Pediatrics (AAP) which sued HHS and won, via the “ruling” of Federal Judge Brian E. Murphy in March 2026 — take a look at the current CDC VFC Vaccine Price List: https://www.cdc.gov/vaccines-for-children/pdfs/2026/06/Pediatric-VFC-Vaccine-Price-List-06-16-2026.pdf. Pediatricians who inject children with the “vaccines” on the VFC List will get compensated according to the Price List (via the billing codes they send to the patients’ insurance company, and/or to CMS.) The ruling by Judge Murphy is discussed here: https://www.risehealth.org/insights-articles/federal-judge-stops-hhs-cdc-vaccine-policy-overhaul/, Ilene MacDonald, 17 March 2026. The “Recommended Immunization Schedule” for children and adolescents that was issued by the American Academy of Pediatrics (which closely “mirrors” the old CDC immunization schedule) is here: https://downloads.aap.org/AAP/PDF/AAP-Immunization-Schedule.pdf.

The American Medical Association (AMA) has championed the development and use of the COVID-19 bioweapon “vaccines” since early 2021. The AMA is the most powerful medical organization lobby in both houses of Congress. The AMA devotes entire sections of its “guidance” to physicians to “combating misinformation” about these “vaccines” (in other words, fighting the spread of the real truth of the dangers and deadliness of these “vaccines”; training physicians on how to “convince” the “vaccine-hesitant” patient to agreeing to have these “vaccines” injected into them; and so on.) Two examples of AMA publications on these topics: https://www.ama-assn.org/public-health/infectious-diseases/covid-19-vaccines-guide-physicians (scroll down to the “Read now” link and click); and, https://www.ama-assn.org/topics/vaccines-vaccinations-immunizations.

And, more corroboration that Big Pharma and the federal government are intent on poisoning Americans with “vaccines” (especially American children): https://www.2ndsmartestguyintheworld.com/p/democide-update-if-all-vaccines-are, “DEMOCIDE UPDATE: If ALL Vaccines are Unsafe and Ineffective, Then Why Are They Being Foisted on Humanity?”, 28 June 2026.

>>>>>>>>>>>>>>>>>>>>

The following is not intended to blame persons who were gaslighted, coerced, or “mandated” into taking the COVID-19 bioweapon “vaccines” (gene-therapy injections.) A multi-level, planned, extremely sophisticated, orchestrated program was implemented by governments and official entities all over the world, to ensure that the maximum number of persons on Earth would be injected with these “vaccines.” Please see: https://www.theqtree.com/2025/01/31/health-friday-1-31-2025-open-thread-hhs-gaslighting-and-propaganda-to-increase-vaccines-uptake/. However, the evidence is now a Tsunami of information proving that these “vaccines” (gene-therapy injections) are dangerous and deadly. Only one example: the rising incidence of “turbo cancer” among COVID-19 “vaccinated” persons:

Yours Truly thanks Brave and Free for this link.

>>>>>>>>>>>>>>>>>>>>

If a reader of today’s offering is a COVID-19 “vaccinated” medical professional / licensed healthcare provider: Stop “recommending”, let alone administering, these gene-therapy injections. Stop taking these “vaccines” yourself. Stop your family from taking them. Recognize that all COVID-19 “vaccinated” persons (including “vaccinated” medical professionals / healthcare providers) have had their natural immune system damaged or even destroyed by the ingredients and mechanisms of these “vaccines” (https://www.thefocalpoints.com/, by Dr. Peter A. McCullough, MD, MPH; search “immune system”; https://jessicar.substack.com/, by Dr. Jessica Rose, PhD; search “class switch.”) Read the post-authorization report from Pfizer-BioNTech that the company gave to the FDA in early 2021 regarding the reports of over 1,200 medical conditions, diseases, and serious negative side effects (including death) in persons who were injected with BNT162b2 (FDA approved under the name COMIRNATY): https://phmpt.org/wp-content/uploads/2021/11/5.3.6-postmarketing-experience.pdf, date-stamped by the FDA on 30 April 2021. Have the courage to put yourself, COVID-19 “vaccinated” family, and COVID-19 “vaccinated” patients, on a protocol to try and mitigate / reduce the damage that the spike protein in these injections have already done to the body. One example of protocols to search: https://www.twc.health; The Wellness Company, Dr. Peter A. McCullough, MD, MPH. Another example: https://imahealth.org/treatment-protocols/ (the Independent Medical Alliance website.) Other entities also provide COVID-19 spike protein detox items: search “COVID-19 spike protein detox protocol” on the Internet. There are certain foods that can assist in spike protein detoxification: for examples of these foods, and also for natural spike protein detox advice, please see: https://drwillcole.com/spike-protein-detox-functional-medicine/; and, https://www.417integrativemedicine.com/articles/the-role-of-nutrition-and-detoxification-in-spike-protein-removal. Note: Yours Truly is not endorsing any particular COVID-19 spike protein detox / removal protocol; I am merely listing some ideas for interested readers to search for themselves. The point is to find ways to safely detox/or remove the spike protein from the body; or, at the least, to minimize the spike protein’s negative effects.

If a reader of today’s offering who is not a medical professional, or a healthcare provider, but who is COVID-19 “vaccinated”: Stop taking the injections. Do not allow your family to be COVID-19 “vaccinated.” Recognize that the spike protein in these injections already in the body have damaged or destroyed the natural immune system; have damaged the heart muscle / cardiovascular system, and the lungs; have altered the DNA in the LINE1 liver cells; have crossed the Blood-Brain Barrier and damaged both the physical (Central Nervous System) and the psychological (learning, memory, and emotional control) mechanisms of the brain. Please see above for information regarding getting on a spike protein detox protocol. The same applies to COVID-19 “vaccinated” family members. For more information about the damage that these injections have done, please visit the links above; and, also, https://doctors4covidethics.org/wp-content/uploads/2022/08/causality-article.pdf, “Vascular and organ damage induced by mRNA vaccines: irrefutable proof of causality”, Michael Palmer, MD, and Sucharit Bhakdi, MD; https://www.theqtree.com/author/pavaca/ (search “LINE1”; “Blood-Brain Barrier”; and, “neurological.”)

For those who are not COVID-19 “vaccinated” (and also in those who are “vaccinated”), there is the potential for “shedding” from these “vaccines” from those who are “vaccinated”, onto other persons. Yours Truly has not advocated, nor is advocating, that the non-“vaccinated” live like “anchorites in the desert”: this is simply not possible. However, there is justifiable room for being cautious. It is up to the individual to determine what “being cautious” means. Having a healthy natural immune system is important. Taking care of health issues when they arise is important. Following a healthy diet and exercise program is important. Having Ivermectin and/or Hydroxycholorquine — Vitamin D — Quercetin — Zinc — among other items — on hand, and using them, is important. Please see: https://www.midwesterndoctor.com/p/covid-19-vaccine-shedding-experiences, 7 June 2024.

>>>>>>>>>>>>>>>>>>>>

Good health is Health Freedom. The ability to decide what constitutes good health, and what to do to support and maintain good health, is Health Freedom. There are times when choosing this freedom comes with a price. The individual gets to decide if that price is worth paying. But how is this freedom affected when health is compromised? What if a person has a condition that negatively affects movement, or the heart, or the lungs, or the eyesight, or the emotional/psychological region — then what? In Yours Truly’s opinion, based on personal experience, the “then what?” becomes finding a balance between doing all one can to ameliorate / support the compromised area(s) — perhaps even finding ways to cure these, if that is a possibility; and strengthening the areas which are not compromised. One believes that a healthy natural immune system is an important key to the whole: along with inner determination, and a positive connection with a Higher Power / Supreme Being.

As the United States of America begins celebrations for the 250th anniversary of her founding, please, consider Health Freedom becoming a part of one’s life.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for linked URLs and other items in today’s offering that are available on the Internet, the ideas and/or opinions of today’s offering are by PAVACA (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions of today’s offering are used by other blog writers; by podcasters; or in print or social media.)