Our mission, as God-fearing and God-loving patriots, is to defend this Constitutional Republic and to increase its greatness, in all good things and ways, by using our voices in free but courteous speech, by discussing the happenings of the world and coming to a profound understanding of those things, and by sharing and promulgating these Truths on both this platform and others.
We have created this site as a place for people to openly express their thoughts and opinions. This is a place where honest but civil discussion of all topics is encouraged. This particular thread is – for the moment – TRUST THE PLAN Thursday. You are welcome to say what you think, in a civil and courteous manner that loves your neighbor. Free speech matters! Courteous speech makes it happen.
Please label all AI-generated content as being such, unless it is patently obvious (e.g., humorous AI images). It is important that we as individuals not begin to pretend that socially derived artificial intelligence is actually our own, as this form of stealthy social information averaging and feedback would be one more pretense and deception between people, in service of stupid Marxist socialism, and of those who wish to substitute their communally protected lies for actual truth.
You are you. AI is AI. Keep your identity. Don’t “Borg Out” on us!
And yes, it’s THURSDAY…again.
That was stolen from Wheatie.
Let’s steal her rules, too.
No food fights.
No running with scissors.
If you bring snacks, bring enough for everyone.
Other rules may be derivable from these, and that conjecture is left for discussion.
Amy Acton seems like an enigma – until you realize that there are two Amy Actons.
One of them is the real Amy Acton. Who I will call Real Amy Acton. She’s likable, but in a ditzy, scatter-brained, and often cringey way. There is absolutely no way that this person should have been a Director of Health. She could never, ever, be the governor of a state.
The other Amy Acton – who I will call Imaginary Amy Acton – is a mirage – a creation. She’s not very likable, but she is competent. She obeys Democrat policy, because she is the creation of professional Democrats. On paper, she sounds quite different from the real Amy Acton, because she’s not the real Amy Acton. She’s like a Soviet consensus on what Amy Acton is supposed to think and believe.
It’s no wonder the Democrats in Ohio are not allowing either Amy Acton to debate Vivek Ramaswamy.
I would like to show you some select insights into this lady, that will help you understand.
Let’s start with a recent X post by Dr. Acton – or Lockdown Amy as she is known, that I find both attractive and a bit out of touch. This is Real Amy Acton.
We weren’t messing around today at The Scioto Ribber.
At first glance, I really liked these images. She’s like a neighbor, going out and eating at some restaurant and posting a tweet about it. That’s very real. It’s very likable. If she wasn’t running for office, I’d think “Hey! That’s Amy Acton, that doctor lady from Columbus!”
I find it interesting that there’s nobody around, and I think that says a lot about her campaign. I think the Democrats may not be thinking she can win, or even planning on winning. I think perhaps they’re grooming her for head of HHS, or CDC, or something like that, should the Demon Donkeys ever get back in the White House.
Next point – while I think it’s awesome that Dr. Acton is having a MONSTROUS steak (I have not had one like that in years), I don’t see that image as being politically wise right now – unless she’s desperate for some carnivore crossover votes that she’s surely not going to get, IMO. Indeed, that picture drew lots of criticism on her timeline, although it’s hard to know how much of that criticism is real, and how much is just AI bots going after her. I see the “same but opposite” on all the GOP timelines.
But what is Imaginary Dr. Amy Acton like?
Well, politically, there are some problems.
Ohio here is what Amy Acton will not tell us out loud.
Amy Acton supports:
⯈Abortion ( even up to 9 months ) ⯈Sanctuary cities ⯈Illegal invaders ⯈Entitlements for illegals ⯈Higher taxes to pay for entitlements to illegals ⯈Cuts in police ⯈Shutting Ohio down ⯈Forcing… pic.twitter.com/dtYjFNATsm
Ohio here is what Amy Acton will not tell us out loud.
Amy Acton supports:
⯈Abortion ( even up to 9 months ) ⯈Sanctuary cities ⯈Illegal invaders ⯈Entitlements for illegals ⯈Higher taxes to pay for entitlements to illegals ⯈Cuts in police ⯈Shutting Ohio down ⯈Forcing more vaccines on Ohioans ( especially children) ⯈Not allowing ICE to operate in Ohio ⯈Allowing lunatic liberal protesters to take over Ohio cities
Amy Acton is running on two things. Brown man is bad. ( Which is racist ) and she will somehow make things less expensive ( for generational entitlement freeloaders ).
She is 100% for socialism not free choice.
NO VOTE AMY ACTON
SO – yeah – Imaginary Amy Acton – the one who would actually be in charge of Ohio – is pretty left-wing, despite some serious efforts to pass her off as moderate right now.
I started looking more deeply into Acton’s background, especially back in her “COVID czarina” days, and what I found is both laughable and disturbing.
Two videos. The first was the New York Slimes singing her praises in early 2020, as the “pandemic” was just getting started. Here is the thumbnail (not an active video).
OMG, it is SO CRINGE! SO VERY CRINGE!!!
You get Real Amy Acton talking, but you get the Times pretending they are talking to Imaginary Amy Acton. This is how they sell one to the public, to install the other in office.
Amy Acton even SOUNDS like Kamala Harris. Just listen.
Amy Acton has been a PROJECT of the left from day one. But now, after the fall of both COVID communism and Kamala Harris, Real Amy Acton is clearly not fit for the job. She was never fit for her earlier job, either.
But it gets worse. Much worse.
Imagine CRINGE SQUARED.
Imagine a video of an event CELEBRATING the first video.
Imagine an event – a lecture given by Real Dr. Acton – celebrating Imaginary Dr. Acton’s “success” as the popularly evicted COVID czarina.
Imagine Amy at her absolute CRINGIEST, WOKEST, and DIZZIEST. Yes. She’s ten times more out to lunch than in any modern video.
Yes, it’s THAT BAD. Although it is fun and entertaining, like talking to a tipsy female doctor in a bar.
I kid you not.
There is a “transcript” which is actually an essay derived from the second video. The essay is clearly a re-write of Real Amy Acton’s speech by somebody else, to make her sound like Imaginary Amy Acton. It’s hard to tell that they’re even related.
Both of these videos are mind-boggling reminders of just how psychotic the COVID years were. And Amy Acton – both of them – was fully riding along with all that dubious psychosis. All the psychosis that was dubious then, and is horrifying now.
These videos are gold mines of cringey error, bad science, dictatorial hubris, talking down to the public, cargo-cult hero-worship, wishful remembrance, and all the rest. I hope to give both videos their own threads in the future, before the election, but you are welcome to dig in now.
So what’s the verdict?
Real Amy Acton may be a nice person and a good neighbor. Stripped of her goofy politics, she seems like a very typical, very likable, Ohio mom. Real Amy’s a bit more entertaining than most, either because of (1) alcohol, (2) xanax, or (3) naturally dizzy mentality. Provided that Real Amy Acton doesn’t drive drunk, she would be welcome in almost any neighborhood in Ohio. She does not strike me as a bad person.
But that is not why we have governors. We have governors to make difficult choices correctly – to do the right things, and to not do the wrong things. And Real Amy Acton is NOT governor material.
But neither is Imaginary Amy Acton – the competent leftist.
Imaginary Amy Acton is what we would get – and it would be even worse than those brutal COVID days.
We have to get that word out. Ohio doesn’t need the trouble it would have, if Amy Acton – any version of her – was Governor.
The free vintage image of hand washing for today’s offering header is courtesy of Open Culture and Google Images. Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats by Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
>>>>>>>>>>>>>>>>>>>>
Countermeasures and Precautions: An Opinion Piece
The following is not medical advice. The following is not “SHTF prepping.” The following is not intended to instill fear. The following are ideas and opinions for consideration regarding certain “ongoing and upcoming situations.” There are several areas to consider: First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA), the first modRNA-platform based influenza bioweapon “vaccine”; Second area: the FDA’s just approving the “latest version” of the COVID-19 bioweapon “vaccines” for 2026 – 2027, based only on testing performed on mice; and, Third area: the recent paper which proves that the spike protein and other ingredients of the COVID-19 bioweapon “vaccine” injections remain active in the “vaccinated” person’s body for at least 3 1/2 years post-final “vaccine” injection.
>>>>>>>>>>>>>>>>>>>>
First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA): this situation has been covered extensively (and will continue to be covered) on this board; by our host, Wolf Moon, and by Yours Truly, among others who posted items related to the situation. The bottom lines of mFLUSIVA: One: this “vaccine” killed more than twice the number of clinical trial study subjects who took it, as compared to those study subjects who took the “comparator influenza” vaccine, Fluarix; Two: Moderna knows that mFLUSIVA can shed — study subjects were required sign an agreement to use birth control before, during, and after, their participation in the clinical trial; Three: mFLUSIVA was FDA-approved on “Accelerated Approval” for persons age 65 and over. Accelerated Approval means that Moderna must agree to perform a clinical trial of the “vaccine” using persons age 65 and older; Four: Moderna must also agree to track reports of deaths in persons who take mFLUSIVA. Our host, Wolf Moon, has written about mFLUSIVA; for example, here: https://www.theqtree.com/2026/08/07/a-grok-eyed-view-of-the-new-mrna-flu-shot/.
Second area: the FDA’s just granting approval for the “latest version” COVID-19 bioweapon “vaccines” for 2026 – 2027. The bottom lines: One: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Pfizer-BioNTech based on lab testing on 8 mice; no human trials. This follows the “Option 4” protocol for formulation of new COVID-19 bioweapon “vaccines” that was adopted by the FDA in 2022; Two: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Moderna based on lab testing on 10 mice, again following the “Option 4” described above; Three: based on the “ruling” against HHS by Federal Judge Brian E. Murphy earlier this year, these “latest version” COVID-19 bioweapon “vaccines” will be administered to persons from age 6 months and older. Please see: http://www.thefocalpoints.com/p/breaking-fda-approves-new-pfizer, “BREAKING: FDA Approves New Pfizer and Moderna XFG mRNA COVID-19 Shots Based on Data From Just 8 – 10 Mice”, Nicolas Hulscher, MPH, 27 August 2026
Third area: the McCullough, et al., paper, which proves that serious adverse reactions and events can occur in COVID-19 bioweapon “vaccinated” persons at least 3.5 years after the last “vaccine” injection (https://www.thefocalpoints.com/p/breaking-peer-reviewed-study-finds-51c, “BREAKING: Peer-Reviewed Study Finds mRNA, SV40, and Spike Protein Can Persist in Humans for At Least 3.5 Years After COVID-19 “Vaccination””, Nicolas Hulscher, MPH, 9 July 2026; the paper cited is here: https://doi.org/10.18103/mra.2026.0351, “Persistence of Vaccine mRNA, Plasmid DNA, Spike Protein, and Genomic Dysregulation Over 3.5 Years Post-COVID-19 mRNA Vaccination”, Nicolas Hulscher, MPH, et al.; published 31 July 2026. The bottom lines: One: these “vaccines” can, and do, have continuous negative consequences in persons who take them for years afterwards; Two: that repeated injections of these “vaccines” accumulate / aggravate / induce, continuous attack on the “vaccinated” person’s entire body and immune system; and, Three: repeated injections of these “vaccines” have the potential for accumulated damage to the entire body and the destruction of the “vaccinated” person’s immune system.
Where does all of the above leave the 20% – 25% of Americans who do not have COVID-19 bioweapon “vaccines” in their bodies? Where does that leave those who have had a COVID-19 infection, have recovered, but still may have lingering issues stemming from the infection (Long COVID; systemic inflammations of one kind or another; lung issues, and so on)? Where does that leave COVID-19 “vaccinated” persons who have decided to never take another injection of any of them? Where does this leave Americans with the 2026 – 2027 “latest version” COVID-19 bioweapon “vaccines” coming on the market within weeks, coupled with the campaigns from Establishment Medicine / government agencies / employers, and other entities, to “make sure one is up-do-date” with the “latest version vaccine”? Where does this leave people who decide to not take mFLUSIVA? In Yours Truly’s opinion, it comes down to making individual decisions regarding personal (and, perhaps, family) “countermeasures and precautions” — and following them faithfully.
>>>>>>>>>>>>>>>>>>>>
What would these “countermeasures and precautions” include? Perhaps, these areas to start the consideration and decision process: Countermeasures: Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine); and, Vitamins, Supplements, and Foods. For Precautions: Lifestyle Protocols / Adjustments. Each of these have ramifications that impact finances; availability; and, interactions with people. Each of these require that people “do their own due diligence” in researching the “countermeasures and precautions” that they are considering implementing for themselves (and, perhaps, for their family.)
Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine): These, in Yours Truly’s opinion, are the “core” of COVID-19 infection prevention or treatment. Independent Medical Alliance has both prevention and treatment protocols for COVID-19: https://imahealth.org/treatment-protocols/. Another protocol is found here: https://www.2ndsmartestguyintheworld.com/p/bombshell-shocker-the-cia-and-pfizer, “BOMBSHELL SHOCKER: The CIA & Pfizer LIED To The Public About The Need For Their $afe & Effective PSYOP-19 “Vaccines””, 2 September 2026; scroll down to the end of the post for “The Ultimate Disease Cure & Prophylaxis Protocol” section.
Vitamins, Supplements, and Foods: First, Vitamins and Supplements: Vitamin C and Vitamin D, for example, can help to bolster the body’s immune system. Supplements such as Zinc, Magnesium, and Quercetin help to keep the lungs clear (Zinc); to regulate many enzyme systems in the body (Magnesium); and, to increase or maintain anti-inflammatory and antioxidant protection (Quercetin.) Please see: regarding Zinc: https://pmc.ncbi.nlm.nih.gov/articles/PMC131177/, “What does zinc do?”, Abi Berger; 9 November 2002; regarding Magnesium: https://ods.od.nih.gov/factsheets/Magnesium-HealthProfessional/; regarding Quercetin: https://www.healthline.com/nutrition/quercetin, Ryan Raman; 7 May 2026. Many brands of multivitamins contain a more-or-less good range of vitamins and minerals; however, the amounts per vitamin or mineral may or may not satisfy the needs of the individual; in those instances, separate supplementation may be desired. Vitamin D uptake from sunshine can be done in many different and healthy ways.
Second, Foods: There is a saying, “Let food be thy medicine.” For some people, a diet that satisfies what is necessary regarding not only nutrition, but also for vitamins and minerals, may be one approach. An example for inclusion in such a diet is eggs (https://www.roswellpark.org/cancertalk/202504/are-eggs-good-you, “Are eggs good for you?”, 18 April 2025.) The “humble egg” is actually a “mini-powerhouse” of vitamins and minerals: Vitamins A — B2 — B12 — E; Lutein; Iodine; Selenium; and more; in addition to protein. Another example, this time of vegetables, is carrots (https://www.healthline.com/nutrition/foods/carrots, “Nutrition and Health Benefits of Carrots”, Adda Bjarnadottir, MS, RDN (Ice), 22 July 2026. Carrots provide beta-carotene (the body converts this into Vitamin A); fiber; antioxidants; and more. Carrots also may help support eye health, among other positive effects. Of course, there is red meat: https://pmc.ncbi.nlm.nih.gov/articles/PMC7015455/ , “What is the role of meat in a healthy diet?”, David M Klurfeld, July 2018. In addition to its being a complete protein, red meat also provides vitamins, amino acids, zinc, and iron.
Precautions: This area includes decisions regarding interacting with others who are COVID-19 “vaccinated”; whether or not to attend large-gathering places; and, if a non-COVID-19 “vaccinated” person is living with other who are “vaccinated”, among other situations. In no way is Yours Truly advocating that non-COVID-19 “vaccinated” people become “modern-day anchorites” with little or no contact with others. However, there are things that non-“vaccinated” people can do to reduce the potential for being exposed to “vaccine” shedding; and, to the potential for being infected by the COVID-19 virus itself. Examples: using disposable gloves at the gas pump; deciding whether or not to use “contactless” payment methods, as opposed to handing a credit card to someone; if possible, sitting at the back of a large-gathering event or facility; changing clothes after returning home from a family visit or going to a large-gathering event; taking an appropriately extra amount of, for example, Vitamin D before attending such an event; taking an appropriate extra dose of Ivermectin or Hydroxychloroquine after attending such an event; among others. Living with, or paying extended visits to, COVID-19 “vaccinated” people is another, and perhaps more difficult, area. Considerations here may be, for example, deciding to take Ivermectin on a weekly basis if a non-COVID-19 “vaccinated” person is part of a family (or, has roommates, etc.) that includes “vaccinated” people living in the same house. Please see: https://www.midwesterndoctor.com/p/covid-19-vaccine-shedding-experiences, “What We’ve Learned from Over a Thousand Vaccine Shedding Reports”, 7 January 2024.
>>>>>>>>>>>>>>>>>>>>
There is another, and important, area, to consider: interactions between drugs that are prescribed for particular needs, and repurposed drugs (such as, Ivermectin.) Please see: https://my.clevelandclinic.org/health/articles/drug-interactions. The Cleveland Clinic defines a drug interaction as what happens when “foods, drinks, dietary supplements, other drugs, prevent medications from working as they should.” For example, Ivermectin interacts with warfarin (Coumadin), and with other drugs: https://www.medicalnewstoday.com/articles/drugs-ivermectin-oral-tablet-interactions, Ashley Wong, PharmD, Last updated 17 January 2025. Ivermectin is also known to interact with: ketoconazole (an antifungal drug); and, with ritonavir (an HIV/AIDS treatment drug: please see https://synapse.patsnap.com/article/what-is-ivermectin-used-for); with benzodiazepines; and with alcohol (increased dizziness risk.) If using Ivermectin along with warfarin, it is important to keep a check on INR levels; it may also be germane to advise the healthcare professional who prescribed the warfarin, that Ivermectin is also being taken. Readers interested in investigating the potential for drug interactions regarding prescription drugs they take; and, for more information on prescription drugs, vitamins, and supplements (minerals) may wish to visit https://www.drugs.com/, or https://www.goodrx.com/. Note: be aware that these websites (and similar ones, such as the search engine at https://www.webmd.com/) appear to be biased against, for example, Ivermectin, except for the very narrow FDA-approved uses of this drug (to treat river blindness or lice.) The FDA still does not approve of Ivermectin for the prevention or treatment of COVID-19.
>>>>>>>>>>>>>>>>>>>>
There is one final area to consider as a COVID-19 and/or mFLUSIVA countermeasure: regular mild to moderate exercise, at least five days a week for 20 – 30 minutes a day. If this exercise can be done in the open air, in the sunshine, there is even more benefit. And the exercise does not have to be strenuous: for example, Tai Chi sequences, practiced correctly and with using proper breathing techniques, can provide a “slow-motion” cardio workout. Just wearing a pedometer to count steps, or staying active inside the house, can help. The point is to avoid being sedentary. Please consult a health professional before starting, or increasing, an exercise program, especially if one is recovering from an illness, has certain health conditions, and so on.
Peace, Good Energy, Respect: PAVACA1
(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1. Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
I will be hitting VERY HARD on the topic of mRNA vaccines in general, and the mRNA flu shot mFlusiva in particular, over the next few weeks.
I will be refreshing your memories to get you all back into FIGHTING SHAPE.
To begin with, I strongly suggest watching this 1 HOUR movie about mRNA vaccines. The main reason is that it will AWAKEN your dormant memories of the world under COVID. Automatic brain boost for our purposes.
I also think it is very important to see interviews with actual vaccine-injured people.
This movie will show you the reality of vaccine injury.
Thank you for your attention to this matter.
W
THE MOVIE:
Chapters:
00:00 Intro 02:53 Surgeon Joel Wallskog’s health issues 06:21 Operation Warp Speed initiative 06:38 Former CDC Director on mRNA vaccines 07:35 Regulators’ safety assessment 08:09 Calls to pause mRNA vaccines 09:32 mRNA researcher Robert Malone 12:56 Pathologist Ryan Cole on COVID vaccination 14:14 Cardiologist Aseem Malhotra on heart health 14:37 Cardiologist Peter McCullough on side effects 17:28 Scientist Jessica Rose on vaccine concerns 18:41 Critical care specialist Paul Marik on patient community 21:17 Explaining mRNA 23:45 How mRNA vaccines work 27:06 Spike protein and possible effects 30:57 Pathologist Arne Burkhardt’s biopsy findings 32:49 Health agencies’ safety stance 33:38 Vaccination in pregnancy and children 34:22 Artist Jessica Sutta’s health issues 39:03 Future uses of mRNA technology 42:55 Tobie Vergara’s health issues 45:12 History of mRNA vaccines 46:44 Modified mRNA technology 48:40 mRNA research status in 2017 49:07 Toxicity concerns in 2017 49:33 Progress in mRNA technology 49:50 mRNA vaccines during the pandemic 55:41 Support for post-vaccination syndrome 57:06 Doctors offering assistance Sources, studies, timecodes: https://docs.google.com/spreadsheets/…
The free image of the word Patent for today’s offering header is courtesy of Vecteezy and Google Images.
Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
Yours Truly has written regarding the “invention” by Dr. Ralph Baric, PhD, the now-retired head of the Baric Lab at the Gillings School of Global Public Health at the University of North Carolina, Chapel Hill, of the “template virus” for SARS-CoV-2 (the COVID-19 “virus”), here: https://www.theqtree.com/2026/01/09/health-friday-1-9-2026-open-thread-the-baric-files-part-four-ecohealth-alliance-wuhan-institute-of-virology-dr-zheng-li-shi-the-template-virus/. This “invention” by Dr. Baric was almost totally funded through grants issued from the National Institutes of Health (NIH) via its National Allergy and Infectious Diseases (NIAID) division (Dr. Anthony Fauci, MD, NIAID Director from 1984 until his retirement in 2022.) This particular Health Friday series will focus on certain items in US9884895B2. Today’s offering is not intended to be a science lecture: it is to illustrate a certain aspect of the research journey of the “Master Designer” of SARS-CoV-2: Dr. Ralph Baric, PhD.
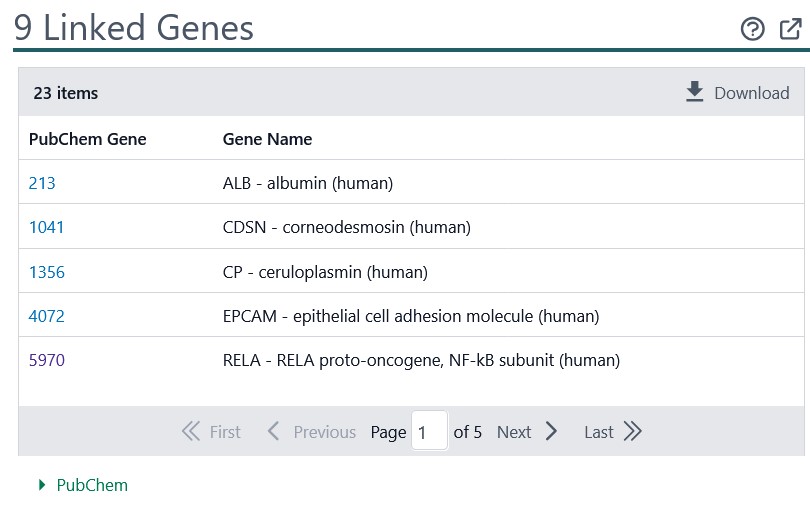
Yours Truly turns to the NCBI PubChem entry for the breakdown of what appears to be the “main elements” that Dr. Ralph Baric included in his “invention” of the SARS-CoV-2 “virus” (COVID-19 “virus”) “template virus”, which Patent application was filed in March 2015. The PubChem entry is here: https://pubchem.ncbi.nlm.nih.gov/patent/US-9884895-B2, “Methods and compositions for chimeric coronavirus spike proteins”, Ralph Baric, Boyd Yount, Sudhakar Agnihothram. The hyperlinked list of elements, chemical compositions, and so forth, is on the right side of this page. Yours Truly clicked on the section “Linked Genes”, and found a gene numbered 5970, called “RELA — RELA proto-oncogene, NF-kB subuit (human).” Below is a screenshot from section 9 “Linked Genes”:
Yours Truly clicked on the 5970 hyperlink. This led to another page, https://pubchem.ncbi.nlm.nih.gov/gene/5970. Please see the screenshot, below, of the Title and Summary of this gene:
**** Notice the multiple types cancers this gene, 5970, is involved in the establishment of: ductal carcinoma in situ; lung cancer; lymphoma; renal cell carcinoma; multiple other types of carcinoma; cervical carcinoma in situ. This gene is also involved in the establishment of other types of diseases, including diseases of the prostate. Why was Dr. Ralph Baric splicing gene 5970 into his “invention” of the SARS-CoV-2 “Template virus”?
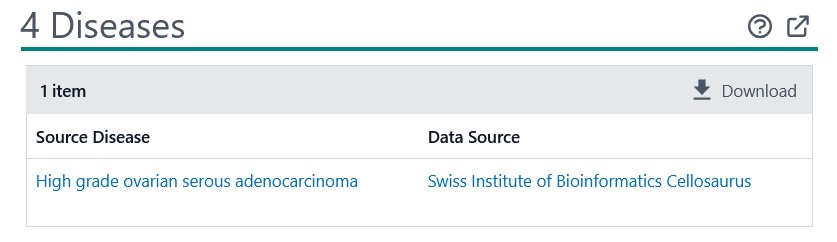
Yours Truly then clicked on the section 9 “Cell Lines” hyperlink on the 5970 gene page. This took one to: https://pubchem.ncbi.nlm.nih.gov/gene/5970#section=Cell-Lines, and then clicked on the “COV18” hyperlink. From there, one then clicked on subsection 4, “Diseases.” Please see the screenshot, below, of subsection 4:
That’s correct — High grade ovarian serous adenocarcinoma. Which, again, raises the question: Why was Dr. Ralph Baric inserting gene code pieces from gene 5970, which has multiple connections to potentially causing cancer in the human body, into his SARS-CoV-2 “template virus invention”, US9884895B2? And gene 5970 is only one of dozens of genes that had code pieces inserted into various “permutations” of this “invention”, US9884895B2. Which also means, in Yours Truly’s opinion, that the SARS-CoV-2 “virus” (actually, a viral biological weapon (VBL), see above) can also have the potential to cause cancers of various types in persons who become infected with this viral biological weapon (VBL.)
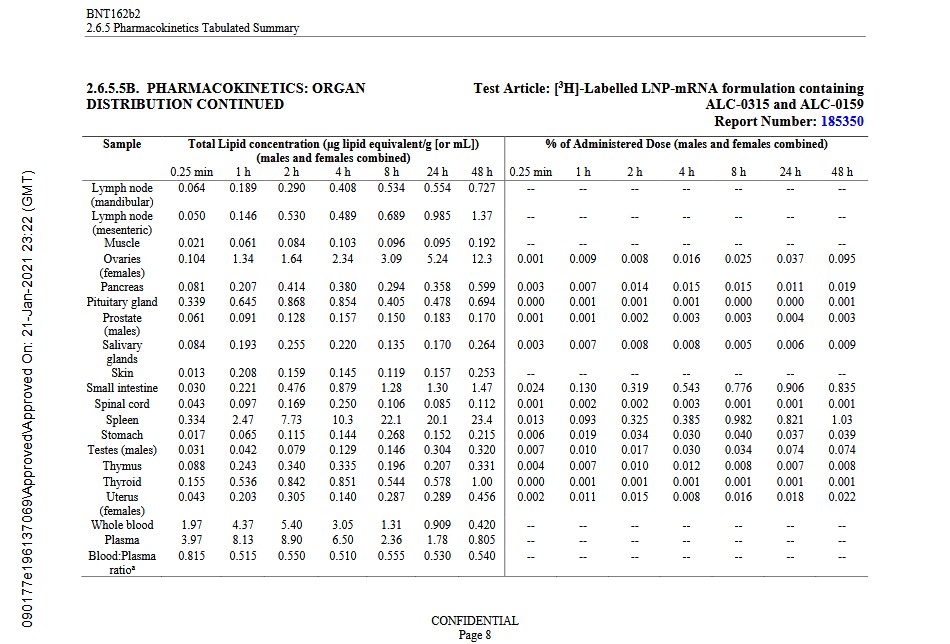
Look at the BNT162b2 accumulation (assisted by the lipid nanoparticles ALC-0159 and ALC-0315 in BNT162b2) in the OVARIES of the Wistar lab rats 48 hours post-injection: 12.3.
Yours Truly then went back to gene 5970, RELA — RELA proto-oncogene, NF-kB, subunit (human), and did some more digging. I found this: https://www.uniprot.org/uniprotkb/A0A087x0W8/variant-viewer. There are 448 variants of this gene. Many are listed as “Variant of uncertain significance.” However, for example, Variant 372 causes “Mucocutaneous ulceration, chronic”, and is also listed as “Pathogenic.” Another example: Variant 264 causes “RELA-related disorder” and is also listed as a “Variant of uncertain significance.”
>>>>>>>>>>>>>>>>>>>>
All of the foregoing in today’s offering is not to incite a “frisson” of “this is too much information and it’s too detailed.”
All of the foregoing in today’s offering is, instead, to illustrate the “layered permutations” of just ONE of the elements contained in Dr. Ralph Baric’s “template virus” for SARs-CoV-2, which he Patented as US9884895B2 in October 2015 — about a month before he and Dr. Zheng-li Shi (which whom Dr. Baric was working since at least 2013, if not earlier) published their “Bait Circulating Coronavirus” paper of November 2015.
Dr. Ralph Baric, PhD, does not have a “pre-emptive pardon” from the “President Biden auto-pen.” Dr. Ralph Baric’s Gain-of-Function experiments, which ultimately resulted in the Patent US9884895B2, Dr. Baric’s “invention” of the SARS-CoV-2 “template virus”, in 2015, were funded by Dr. Anthony Fauci of the NIAID as far back as the mid-1980s. Dr. Baric has close ties with the Wuhan Institute of Virology and with the United States Defense Department. It is time for Dr. Baric to be brought to account for his activities. Dr. Baric needs to answer questions, under oath, such as: What information, if any, was shared with Pfizer-BioNTech (PfizerUSA), and/or with Moderna, from Patent US9884895B2? What information, if any, was shared with Pfizer-BioNTech (PfizerUSA), and/or with Moderna, regarding the possible inclusion of proto-oncogenes listed in Patent US9884895B2 into these companies’ modRNA COVID-19 bioweapon “vaccines”? What information, if any, was shared with DARPA, BARDA, NIAID, or any other United States government entity, from Patent US9884895B2?
Peace, Good Energy, Respect: PAVACA1
(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet in today’s offering, the ideas and/or opinions above are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
The header image of Justice for today’s offering is courtesy of Mammoth Memory Art and Google Images.
Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
It is time — in fact, is it past time — to bring Dr. Ralph Baric, PhD, to account. His activities must be be swept under the rug, now that the University of North Carolina, Chapel Hill, has forced him to retire in June of this year.
Yours Truly brings the following as “preliminaries”: https://merylnass.substack.com/p/today-ralph-baric-was-forcibly-retired, “Today, Ralph Baric was forcibly retired. Let’s examine his career and his central role in the COVID disaster”, Meryl Nass, MD, 12 May 2026. Dr. Nass, who lives in Maine, was suspended from her License to Practice Medicine in 2023 by the Maine Board of Licensure in Medicine — for prescribing Ivermectin to treat COVID-19. https://merylnass.substack.com/p/dr-meryl-nass-on-professional-cancellation, 20 December 2023. Her License to Practice Medicine was “License Suspension for Discipline”, with “Suspended Until: Open End Date.” This means that Dr. Nass (a physician with over 40 years’ experience) cannot practice medicine in Maine until she admits “wrongdoing” to the Licensure board; that she takes “re-education” courses; that she agrees to have her work monitored; and, that she “shows remorse” — all of which she refuses to do. Her case is a prime example of what Establishment Medicine will do to punish licensed physicians who dare to treat COVID-19 with repurposed drugs (such as, Ivermectin.)
Why are the above important? They illustrate the breadth and depth of Establishment Medicine and of media “cancellation” / censorship of those who dare to tell the truth about the COVID-19 bioweapon “vaccines”, and of those who dare to treat COVID-19 with prescription drugs / therapeutics that are not on the “FDA-approved” list.
Why are the above important? They illustrate one aspect of the myriad “ripple effects” of the results of the work of one scientist — Dr. Ralph Baric, PhD, (being forcibly retired in June 2026) of the University of North Carolina, Chapel Hill: the scientist who was the Master Designer of the SARS-CoV-2 virus. The scientist who invented the “No See’m” method for hiding insertions / changes in virus gene codes in order to lab-create “new virus gene codes” of spliced-in or deleted code pieces. The scientist who taught multiple other scientists how to lab-create coronaviruses via his “Synthetic Genomics” paper that was published in 2006. The scientist who obtained the Patent for his “invention” of the SARS-CoV-2 virus template — Patent Number US9884895B2 — in March 2015: which Patent was obtained months before Dr. Baric (with Dr. Zheng-li Shi) published the infamous “Circulating Bat Coronavirus” paper in November 2015. The scientist who was a prime “acolyte” of Dr. Anthony Fauci in working on lab-created coronaviruses — with NIH/NIAID grants money from Dr. Fauci that began in the mid-1980s. The scientist who had deep ties with the Wuhan Institute of Virology and Dr. Shi. The scientist who had deep ties with Dr. Peter Daszak and EcoHealth Alliance. Yours Truly’s Health Friday six part series, The Baric Files, discusses the above, and traces Dr. Baric’s research journey (https://www.theqtree.com/author/pavaca; search “The Baric Files.”) One of the recurring themes of The Baric Files is the repeated Gain-of-Function experiments that Dr. Baric performed, literally over decades (beginning in the mid-1980s), related to animal coronaviruses. The March 2020 Patent for his “invention” of the SARS-CoV-2 virus template, the November 2020 “Circulating Bat Coronaviruses” paper, and other items, reflect the Gain-of-Function approach in his research. Keep this mind when reading onward:
In Yours Truly’ opinion: It appears that Dr. Ralph Baric, PhD, was involved in continuing Gain-of-Function research on coronaviruses, even after the general pause on that type of research in the United States was implemented in 2014. It also appears that Dr. Ralph Baric, PhD, engaged in continuing Gain-of-Function research as described in the DEFUSE proposal made by Dr. Peter Daszak (with Dr. Baric as a co-contributer) in 2018 to the United States military, which proposal was turned down. And, in both circumstances, it appears that Dr. Baric misled officials regarding the nature of the work that he was continuing to perform (Gain-of-Function experiments.)
>>>>>>>>>>>>>>>>>>>>
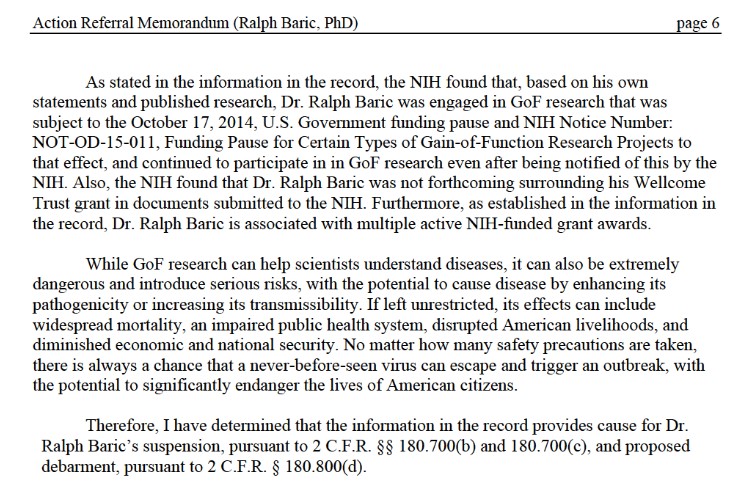
On (or, perhaps, before) 6 May 2026, an HHS Action Referral Memorandum, Notice of Suspension and Proposed Debarment of Ralph Baric, PhD, was sent to Dr. Baric via email and by Certified Mail – Return Receipt Requested. There appears to be no actual “sent date” listed on the HHS document; it can be assumed that it was sent between 15 April 2026 (the date of the NIH ROI evidence items list in the document), and 6 May 2026; link is below. The Notice was signed by HHS employee Jennifer D. Johnson, Suspension and Debarment Official and Deputy Assistant Secretary of Acquisitions: https://www.science.org/cms/asset/8669-dc85-416d-bc3a-f4600-bd2cc70/hhssuspensionandproposeddebarmentofralphbaricphd_05.06.2026_r.pdf. Apparently, Dr. Baric furnished a copy of the Notice to the American Association for the Advancement of Science (AAAS.) Two screenshots from the final page of the Notice are below:
Dr. Baric stated that he would fight the HHS Notice: https://bioethics.com/archives/102651, “Virologist accused to starting COVID-19 will fight U.S. ban on funding”, 12 May 2026.
But, something else happened: Dr. Baric was apparently summarily “retired” from the Gillings School of Global Public Health of the University of North Carolina Chapel Hill on 12 May 2026. The action was done under the aegis of Dr. Nancy Messonnier, MD, (Dean of the Gillings School since 2022); and a message was emailed to Gillings School faculty and staff on 12 May. https://www.theassemblync.com/news/education/higher-education/unc-coronavirus-researcher-ralph-baric-retires/, Karie Dean, 12 May 2026. His “retirement” is official as of 1 June 2026. (Yes, it’s that Dr. Nancy Messonnier, MD: sister of Rod Rosenstein. She was the “chief architect” of the COVID-19 bioweapon “vaccine” rollout and imposition campaign. https://sph.unc.edu/adv_profile/nancy-messonnier-md/.)
So it’s official now. Ralph Baric, perhaps the world’s most famous coronavirologist (or infamous, depending on who you ask) has retired.
"Nancy Messonnier, dean of the Gillings School of Global Public Health, and Maria Gallo, chair of the school’s epidemiology department, made…
So, despite the accolades about Dr. Baric by Dr. Messonnier and Maria Gallo in the email above as reported in The Assembly, why does the full tweet above have the phrase, “Messonnier and Gallo’s message did not cite a reason for Baric’s retirement.”?
**** However, several other things also took place prior to the HHS Notice going to Dr. Baric on 6 May 2026:
**** Per the Carolina Journal article cited above, Lee H. Roberts, the Chancellor of the University of North Carolina Chapel Hill, is still refusing to fully cooperate with demands to release the withheld 5,205 remaining documents related to Dr. Baric’s activities in the origins of COVID-19. Why?
**** Why does it feel as if Dr. Nancy Messonnier, MD, Dean of the Gillings School of Global Public Health at the University of North Carolina Chapel Hill, “threw Dr. Ralph Baric, PhD, under the bus” and summarily “retired” him on 12 May 2026? It is almost impossible that Dr. Messonnier had not heard of Dr. Baric or of his Gain-of-Function experiments on coronaviruses prior to becoming Dean; or, if not before taking the job, then certainly, at some point after her becoming Dean. Why did she suddenly “retire” him?
**** What aboutDr. Boyd Yount, PhD, and Dr. Sudhakar Agnihothram, PhD, the CO-INVENTORS of the 2015 SARS-CoV-2 virus “template” Patent along with Dr. Ralph Baric, Patent Number US9884895B2? Dr. Yount is still employed by the Gillings School of Global Public Health at the University of North Carolina Chapel Hill (https://sph.unc.edu/adv_profile/boyd-yount-jr/.) Dr. Agnihothram left UNC and has been working at the FDA since at least 2021 — in the CBER division (Center for Biologics Evaluation and Research): https://www.linkedin.com/in/sudhakar-agnihothram-8195309. Why aren’t these two co-inventors being investigated for their activities alongside Dr. Baric? Why is Dr. Sudhakar Agnihothram, PhD, serving as a speaker at CBER conferences and meetings?: https://www.fda.gov/media/186566/download; scroll down the page to “FDA CBER PARTICIPANTS.” Surely, the FDA knows that Dr. Agnihothrom would likely be biased towards approving COVID-19 bioweapon “vaccines.”
Dr. Ralph Baric, PhD; and his co-inventors of the SARS-CoV-2 virus “template” Patent US9884895B2, must all be investigated. Thoroughly. And held to account. Their “invention” was undoubtedly used by Dr. Zheng-li Shi at the Wuhan Institute of Virology, starting in late November 2015, in her experiments to further develop the SARS-CoV-2 virus. This was the (potentially “unfinished”) virus that was “somehow leaked” from her lab at the WIV in the late fall of 2019, and which was subsequently named “COVID-19”: https://www.theqtree.com/2026/01/09/health-friday-1-9-2026-open-thread-the-baric-files-part-four-ecohealth-alliance-wuhan-institute-of-technology-dr-zheng-li-shi-the-template-virus/. Dr. Baric used the bat coronavirus SHC014, which Dr. Shi was working on at her lab at WIV, and samples of which virus she sent to him, in his SARS-CoV-2 virus “template” Patent, US9884895B2. Please see below, from the Detailed Description of the Invention section of the Patent (the SHC014 virus labelled “WiV1 S”):
>>>>>>>>>>>>>>>>>>>>
Why is Dr. Ralph Baric, PhD, in particular, still being “protected” for his activities in lab-creating the COVID-19 virus “template”? What is contained in the 5,205 pages of documents that the University of North Carolina still refuses to release? Does the University of North Carolina believe that, by apparently forcing Dr. Baric into retirement, the school has “shut the door” on further investigation into his activities?
DR. RALPH BARIC, PhD, MUST BE BROUGHT TO ACCOUNT, ALONG WITH HIS SARS-CoV-2 VIRUS “TEMPLATE” CO-INVENTORS.
Peace, Good Energy, Respect: PAVACA
(Intellectual Property Disclaimer and Notice: Except for linked URLs and other items available on the internet, the ideas and/or opinions of today’s offering are by PAVACA. Credit must be given to PAVACA for ideas and/or opinions of today’s offering that are used by other blog writers, by podcasters, or in print or social media.)
The header image of drawings for a Patent application is courtesy of Getty Images, ThoughtCo, and Google Images.
Health Friday is a series devoted to information about Big Pharma, general health, and associated topics. As today’s offering speaks to the disaster of COVID-19, Yours Truly dedicates it to all persons, of whatever age or location, who have suffered health issues from to an infection of the COVID-19 virus itself; or, from the negative effects of the COVID-19 “vaccines” that they have in their bodies; or, who have passed away from complications due to an infection of the COVID-19 virus itself, or from complications due to the negative effects of the COVID-19 “vaccines” they had in their bodies.
There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s offering for AI-generated content. To the best of her knowledge and belief, there is none, except for AI-generated images and/or text within linked URLs. If readers wish to post AI-generated content to today’s discussion thread, they must cite their source. Thank you.
Yours Truly wishes one and all a Happy New Year 2026.
Special Note regarding today’s offering: In no way is the following, or The Baric Files in general in the Health Friday posts, to be construed as a “character assassination”, or as an “indictment”, or as any other type of attack or smear on the Ralph Baric, PhD, of the UNC Gillings School of Global Public Health of the University of North Carolina, Chapel Hill, or of his lab at the university. The linked scientific papers, images therefrom, and other information about Dr. Baric (such as, his Curriculum Vitae [1]) are all available on the internet. The ideas and conclusions of today’s offering are by Yours Truly. There is a plethora of information related to Dr. Baric; Yours Truly will focus on a few of them in each part of The Baric Files.
The Baric Files, Part Three: Patents; Dr. Anthony Fauci
Patents:
Ralph S. Baric, PhD, owns 25 to 30 Patents (depending on whether one is looking at, for example, https://justia.com/patents/, or at https://patents.google.com/, or at NIH RePorter at https://report.nih.gov/) related to items he found or created during his research journey into coronaviruses and/or his Gain-of-Function experiments. What is definite, however, is that our old friend, NIH grant AI23946 (also called AI023946) figures in at least three of these Patents: Patent Number 6593111; Patent Number 7279327; and, Patent Number 7618802 — all of which are associated with his lab the UNC Gillings School of Global Public Health at the University of North Carolina Chapel Hill.
Patent Number 6593111 is titled, “Directional assembly of large viral genomes and chromosomes.”
Patent Number 7279327 is titled, “Methods of Producing Recombinant Coronaviruses.”
Patent Number 7618802 is titled, “Methods and compositions for infectious cDNA of SARS coronavirus.”
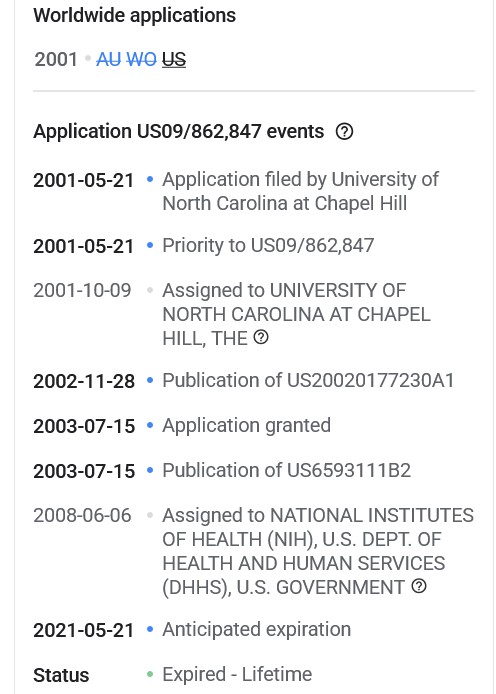
Yours Truly will focus on Patent Number 6593111 [2], the timeline of which Patent begins on 5 May 2001. The NIH grant AI023946 has been “extended” several times; in this Patent, it is called “AI023946-08“, and the Patent Number has been changed to “US6593111B2.” By now, Dr. Baric’s research journey has taken him to experimenting with coronaviruses that infect pigs: in particular, the TGE virus (Transmissible Gastroenteritis virus, also called Transmissible Gastroenteritis Coronavirus [TGEV].) The following screenshots are from the Patent document. The screenshots are, in order: the Abstract; the Events summary; the first paragraph of the Summary of the Invention section; from the Detailed Description of the Preferred Embodiments discussion section; and, Fig. 1a and Fig. 2 from the images in the Patent document:
Note, in the screenshot above, the mention of “vaccines and expression vectors”; and, the sentence, “The vectors may be targeted to other species by, for example, replacing the S glycoprotein gene.” This paragraph, in Yours Truly’s’ opinion, begins the eventual “tie-into evolution” of the SARS-CoV-2 virus.In other words — Gain-of-Function research and application.
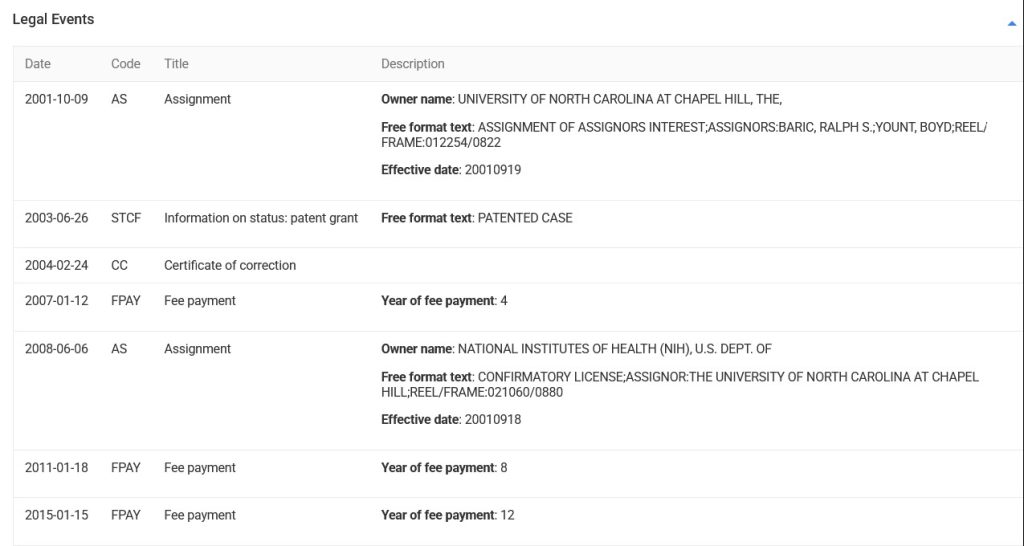
However, there is another item in Patent Number US6593111B2 that is interesting: the list of Legal Events near the end of the document. A screenshot of this list is below:
Note that UNC (Baric lab) “transferred” the ownership of the Patent to the NIH in 2008. Note also that on 18 January 2011, someone at NIH must have sent the Patent Fee payment that would be good for eight years. A Fee payment for a Patent is a “Patent Maintenance Fee” that “preserve a patent.” [3] Note also, that on 15 January 2015, someone at NIH must have sent the Patent Fee payment that would good for twelve years (thus theoretically preserving the Patent until January 2027.) However, on the Events Summary list for Patent Number US6593111B2 (in the images above), it lists the Patent as Status Expired – Lifetime. This brings up some questions: To what person at NIH was Patent US6593111 transferred to in 2008? The NIH Director in June 2008 was Elias Zerhouni, MD [4]. When he left the NIH, who did he designate to take over NIH ownership of the Patent? Is Patent US6593111B2 still in force, even though it is listed as “Status Expired – Lifetime?” Is it still in force, but under a different name?
>>>>>>>>>>>>>>>>>>>>>>>>>>>>>>
Anthony Fauci, MD, Director of NIAID1984 – 2022:
It can be assumed that Dr. Ralph Baric, PhD, had been on the “radar” of Dr. Anthony Fauci, MD, Director of the NIAID division (National Institute of Allergy and Infectious Diseases division) of the National Institutes of Health (NIH) since at least 1984, if not before (Dr. Fauci had joined NIH in 1968, shortly after completing his medical Residency.) This “being on his radar” situation, in Yours Truly’s opinion, would have included, at the least, what may be called a “bowing acquaintance” with Dr. Baric through NIAID funding applications and grants dispersements reports.
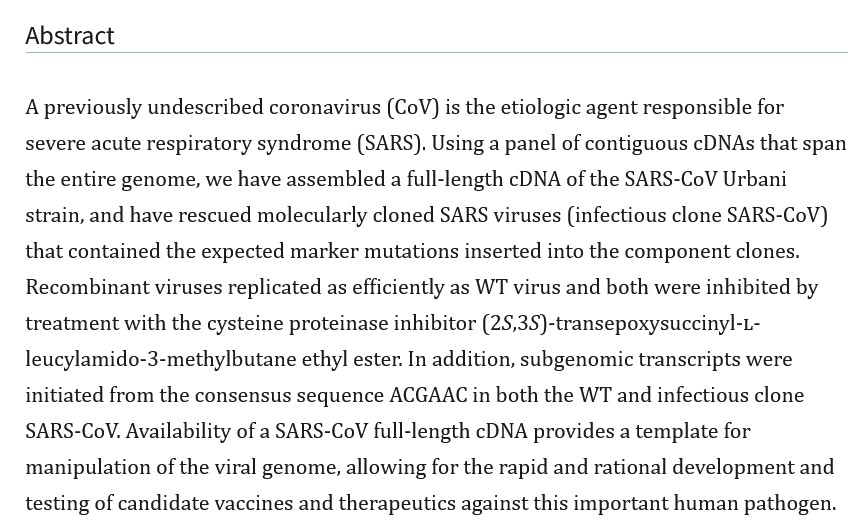
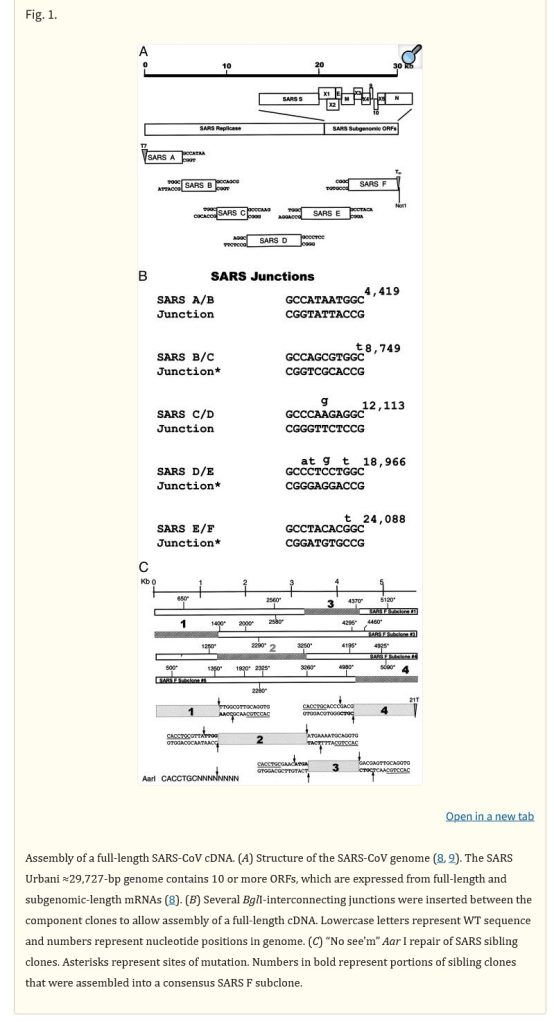
In fact, NIH / NIAID (and, it can be assumed, within the knowledge of Dr. Anthony Fauci), was funding Dr. Barics’s Gain-of-Function research on coronaviruses as far back as at least the year 2003 [5]. The 2003 paper not only describes what can only be called Gain-of-Function experiments with SARS coronaviruses; it also describes the Baric-invented “No see ‘m” procedure for covering up gene code insertions in the lab-creation of SARS coronavirus “clone” viruses. Please see the screenshots from this paper, below. Note that our old friend, NIH grant AI23946, was involved in the funding of the 2003 paper. Below are: the Abstract, the Figure 1., and, the Acknowledgements sections from this paper:
Note that one of the co-authors of the 2003 paper is Thomas M. Geisbert, of the the United States Army Medical Research Institute of Infectious Diseases (also known as USAMRIID, located at Fort Detrick, Maryland.)
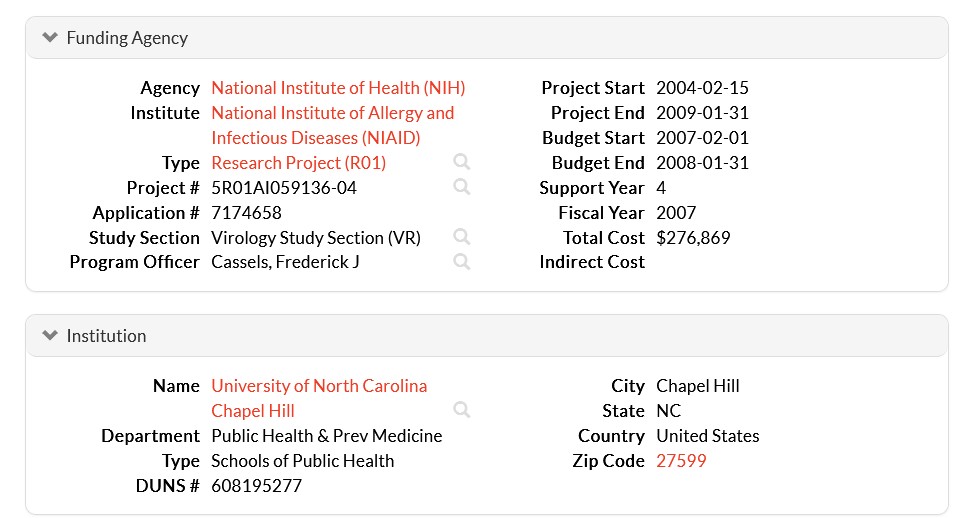
Another example of NIH / NIAID / Dr. Anthony Fauci funding Gain-of-Function research by Dr. Baric is NIH grant R01AI059136-04, from 2004 [6]. Please see the screenshots from the documents on this grant, below: of the Title for the grant; the Abstract; the Funding Agency; and, the receiving Institution:
Dr. Fauci has denied ever knowing Dr. Baric. However, there is evidence to the opposite: Please see the screenshots, below, from a February 2023 U.S. Right to Know article by Emily Kopp [7]:
A screenshot of a photo from the Emily Kopp article:
The official work calendar for Dr. Anthony Fauci was released via FOIA from Open The Books [8]. The calendar shows that Dr. Fauci met with Dr. Baric in February 2020. A screenshot from the article in Open The Books on this situation is below:
An article by Sainath Suryanarayanan in U.S. Right to Know related to Dr. Baric’s emails early in the COVID-19 pandemic [9]. These emails were either from Dr. Baric, or were sent to him as part of a group email from various institutions and/or government agencies and/or from medical professionals in these institutions or agencies. In these emails, the “code name” for the burgeoning COVID-19 virus infection situation in the United States was “Red Dawn Responding, Start 16 March.” The emails were released through a public records request.
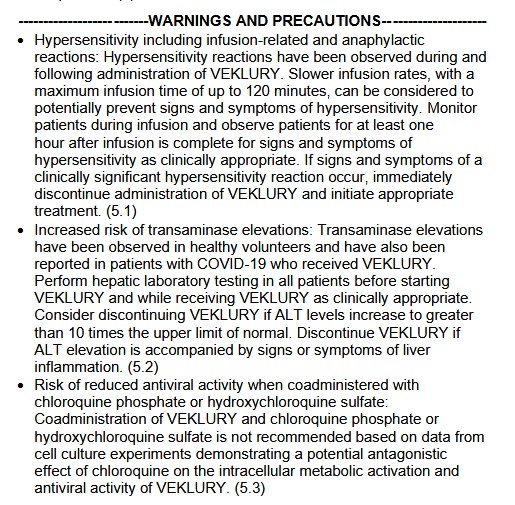
By the way, Dr. Baric and his lab at the University of North Carolina Chapel Hill worked with Gilead Sciences to create remdesivir (Veklury), a COVID-19 treatment drug that can have a mortality rate of 50%, and also can cause kidney damage [10] [11] [12] [13]. Please see the screenshots below; the first, from the University of North Carolina article about the creation of remdesivir; the others are also items regarding this drug:
Please see Reference [10].
VekluryPackage Insert,Warnings and Precautions:
Please see Reference [11].
Please see Reference [12].
World Health Organization (WHO) advisory against usingVeklury (remdesivir):
Please see Reference [13].
>>>>>>>>>>>>>>>>>>>>>>>>>>>>>>
It is apparent that by at least the year 2003, Dr. Baric’s research journey was shifting to methods and applications for the cloning of coronaviruses, including his invention of the “No see ‘m” method of covering up insertions into coronavirus gene code pieces in the lab-creation of the cloning of coronaviruses to make such insertions “un-traceable.”
To be continued in The Baric Files:Part Four.
>>>>>>>>>>>>>>>>>>>>>>>>>>>>>>
ALL COVID-19 “VACCINES” MUST BE REMOVED FROM THE MARKET AND FROM USE IN THE UNITED STATES. NOW.
ALL GAIN-OF-FUNCTION RESEARCH ACTIVITIES IN THE UNITED STATES MUST BE STOPPED AND DE-FUNDED. NOW.
THERE. MUST. BE. ACCOUNTABILITY.
THERE. MUST. BE. JUSTICE.
THERE. MUST. BE. TRUTH.
Peace, Good Energy, Respect: PAVACA
(Intellectual Property Notice and Disclaimer: With the exception of published scientific papers, news articles, and other items available on the internet, the ideas and conclusions of today’s offering are by PAVACA. Proper credit must be given to PAVACA if the ideas and conclusions in today’s offering are used by other blog writers, podcasters, in social media, or in print media.)
[5]: “Reverse genetics with a full-length infectious cDNA of severe acute respiratory syndrome coronavirus.” https://www.pnas.org/cgi/doi/10.1073/pnas.1735582100. Ralph S. Baric, Thomas Geisbert, et al. 29 August 2003.
The above image (also the header image) of a vintage Rolodex in today’s offering is courtesy of Google Images.
Health Friday is a series devoted to Big Pharma, vaccines, general health, and associated topics. As today’s offering speaks to the disaster of COVID-19, Yours Truly dedicates it to all persons, of whatever age or location, who have passed away from either the negative effects of a COVID-19 virus infection; or, from the negative effects of the COVID-19 “vaccines” that they had in their body.
There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s offering for AI-generated content. To the best of her knowledge and belief, there is none, except perhaps for AI-generated images within linked URLs. If readers wish to post AI-generated content in today’s discussion thread, they must cite their source. Thank you.
Vaccines, Amen, by Attorney Aaron Siri. Attorney Siri is involved with https://phmpt.org/ (Public Health and Medical Professionals for Transparency, one of the organizations that have forced the release of thousands of documents on the modRNA COVID-19 “vaccines” via FOIA lawsuits.)
The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex, by John Leake and Peter A. McCullough, MD, MPH. Mr Leake and Dr. McCullough are involved with https://www.thefocalpoints.com/, a website that focuses on, among other topics, disseminating the real truth about the COVID-19 “vaccines”, the role of Bio Pharma in promoting the modRNA COVID-19 “vaccines”, and more.
Information Compendium sitesrelated to COVID-19:
From Children’s Health Defense: https://www.covidindex.science/, via Dr. Brian Hooker, PhD, Chief Scientific Officer of CHD. This is a searchable index of thousands of items.
Preventing Cancer: The ROOT Protocols. https://doi.org/10.71189/JIM/2025/V01N04A02, by Paul Marik, MD, and Justus Hope, MD. Both of these medical doctors are involved with Independent Medical Alliance https://imahealth.org/ (formerly FLCCC.) Interested readers must register with the Journal of Independent Medicine (the journal of Independent Medical Alliance) in order to view the entire paper. A story on The ROOT Protocols is here: https://imahealth.substack.com/cp/178752784, 12 November 2025.
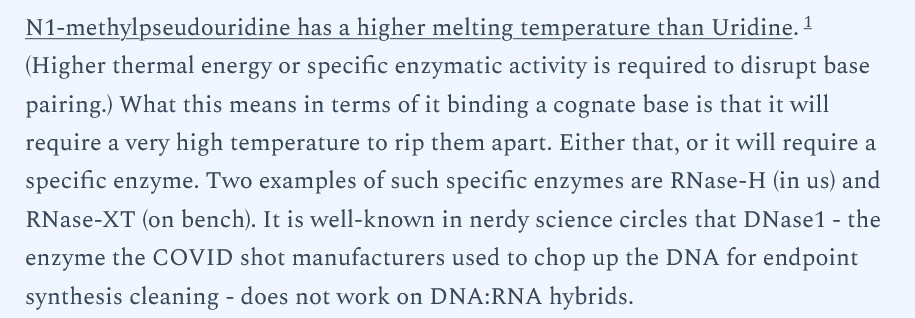
Dr. Jessica Rose and Dr. Kevin McKernan have just finished a new project which reveals the truth behind the inclusion of N1-Methylpseudouridine, in both the Pfizer-BioNTech and the Moderna modRNA COVID-19 “vaccines”; and, of the inclusion of a gene code piece from the African Green Monkey cancer promoter, SV40, in the Pfizer-BioNTech modRNA COVID-19 “vaccines”: https://jessicar.substack.com/p/we-know-exactly-how-and-why-the-dna. “We now exactly how and why the DNA is in the Moderna and Pfizer vials”, 15 November 2025. Please see the screenshots from this article, below;
Three:
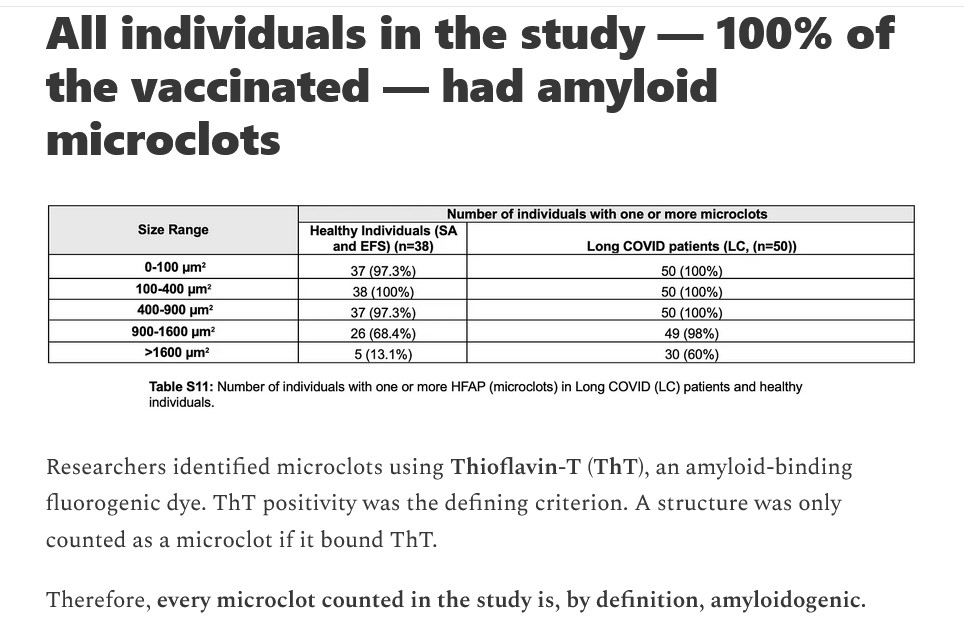
A new study, by Alain R. Thierry, et al., reveals that 100% of COVID-19 “vaccinated” persons have microclots in their blood; and, that COVID-19 “vaccinated” persons who present with symptoms of “Long COVID” also have microclots: https://www.thefocalpoints.com/p/breaking-study-anomalous-amyloid, “Breaking Study: Anomalous Amyloid Microclots Found in 100% of the COVID-19 Vaccinated”, Nicolas Hulscher, 17 November 2025. Please see the screenshots from this article, below:
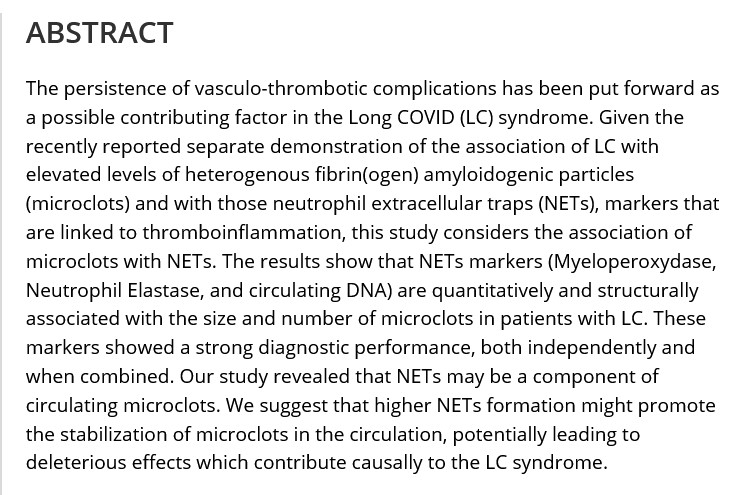
The scientific paper referred to in the Hulscher article is here: https://doi.org/10.1002/jmv.70613, “Circulating Microclots Are Structurally Associated With Neutraphil Extracurricular Traps and Their Amounts Are Elevated in Long COVID Patients”, Alain R. Thierry, et al., 2 October 2025. Note the use of the word, “circulating.” This means that the microclots in the blood of the COVID-19 “vaccinated” persons are moving around inside the body. The Abstract from this paper is below:
The COVID-19 “vaccines” — all of them — if, for no other reason, must be immediately removed from use, from the market, and removed from any immunization schedule (especially the Immunization Schedules of the CDC), because of the evidence presented in the Thierry, et al., paper regarding circulating microclots in the blood of COVID-19 “vaccinated” persons, and in the blood of COVID-19 “vaccinated” persons who present with symptoms of “Long COVID.” There is no other acceptable option at this point.
THERE. MUST. BE. ACCOUNTABILITY.
THERE. MUST. BE. JUSTICE.
THERE. MUST. BE. TRUTH.
Peace, Good Energy, Respect: PAVACA
(Intellectual Property Notice: With the exception of cited published scientific papers and publicly-available blogs and other websites, the ideas and conclusions in today’s post are by PAVACA. Proper credit must be given to PAVACA if other blog writers, podcasters, social media posts, or print media, use the ideas or conclusions in today’s post.)
The free header stock image of a nursing home is courtesy of Vecteezy and Google Images.
Health Friday is a series devoted to Big Pharma, vaccines, general health, and associated topics.
There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s offering for AI-generated content. To the best of her knowledge and belief, there is none, except possibly that which is contained in URL links in today’s post. If readers wish to add AI-generated content to today’s discussion thread, they must cite their source. Thank you.
Please take a moment and remember our good GA/FL (Georgia Sibyl Swink Smith), who passed away on 8 October 2025. The time, energy, and ingenunity that GA/FL invested into decades of taking care of her late daughter, “Sally Q” Smith, after the latter’s diagnosis of Friedreich’s Ataxia at the age of 14, was amazing and inspiring. Sally Q passed away from the effects of this condition on 10 May 2025. Georgia was a devout Christian. May she and her daughter rest in eternal Peace. GA/FL will be sorely missed.
Yours Truly comes from a birth family that, on both sides, had a horror of having to go into “a home” (“a home” was “code” for a nursing home or care facility.) Grandparents, aunts, uncles — even one’s own father — vigorously preferred to remain at home, no matter what, and stay away from congregate living of any kind. Only as a last resort, did my maternal grandmother have to go to live at a nursing home. I think she had a premonition that she would not “come out alive” from the facility. She was correct. My own brother was discharged from the hospital to a nursing home, but that, too, was under “last resort” circumstances; he, also, did not “come out alive” from the facility. In both the cases of my maternal grandmother and of my brother, there were extremely serious medical conditions which excluded their ever living at their own homes again.
Nursing homes and care / rehabilitation facilities in the United States are inspected by the state health agencies where these are located. CMS (Medicare / Medicaid) will step in if a nursing home or care facility fails to meet state inspection standards, or if complaints are filed with either the state health department or CMS regarding a nursing home or care / rehabilitation facility. Please see: https://www.cms.gov/medicare/health-safety-standards/enforcement/nursing-home-enforcement, last updated 21 April 2025.
Nursing homes and care / rehabilitation facilities in the United States were especially negatively affected by the COVID-19 disaster. During the “lockdown” period, these places became off-limits to family and friends of the residents / patients. Untold numbers of these residents / patients died alone. Untold numbers of residents / patients were injected with the modRNA COVID-19 “vaccines”, whether they consented to this or not. According to data complied by the CDC, residents / patients of these facilities had increased risk of death if they were “vaccinated” against COVID-19: https://kirschsubstack.com/p/cdc-nursing-home-data-the-vaccine, “CDC Nursing Home Data: The vaccine increased the risk of the elderly dying from COVID”, Steve Kirsch, 5 September 2023. Please see the screenshots from this article, below:
The AMA (American Medical Association), on the other hand, made it clear, also in 2023, that deaths among the COVID-19 “vaccinated” simply underscored the “need” for persons to get a COVID-19 “vaccine booster shot”: https://www.ama-assn.org/public-health/infectious-diseases/why-covid-19-deaths-among-vaccinated-show-boosters-matter, Cynthia Cos, et al., 7 March 2023. Please see the screenshots from this article, below, in which Dr. Elaine Choi (a member of the AMA) is “explaining” why COVID-19 “vaccine booster shots” are a good thing, even though “vaccinated” persons were then dying from COVID:
Currently, the AMA, among other professional medical organizations, is speaking out regarding what they term the “new restrictions against COVID-19 vaccination” that were put into place by HHS Sec. Robert F. Kennedy, Jr., earlier this year. One example of such “speaking out” is here: https://www.chiefhealthexecutive.com/view/defending-vaccines-ama-nursing-leaders-speak-out, Ron Southwick, 22 September 2025. There is a video embedded in the article; two screenshots from the article’s text are below:
Note the old (and misinformation) canard about “if you’re young and healthy, get a COVID-19 vaccine so your grandparents won’t get COVID” from Mensik Kennedy.
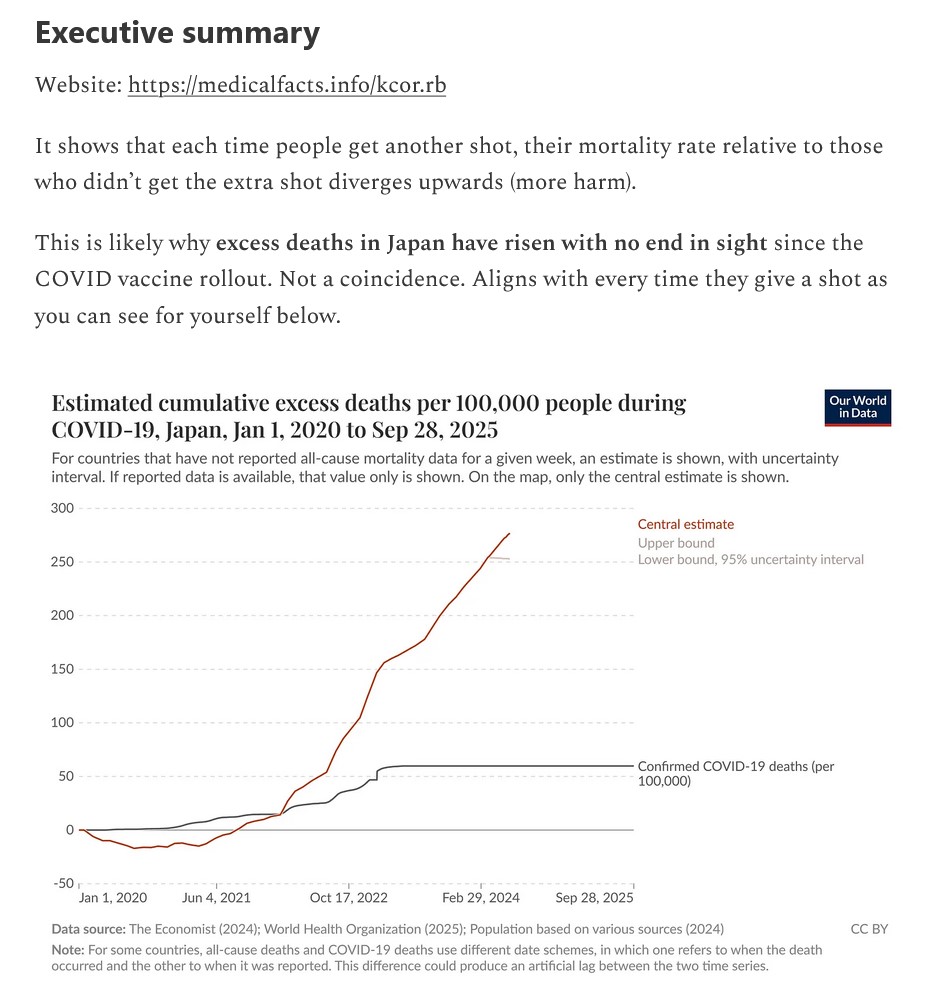
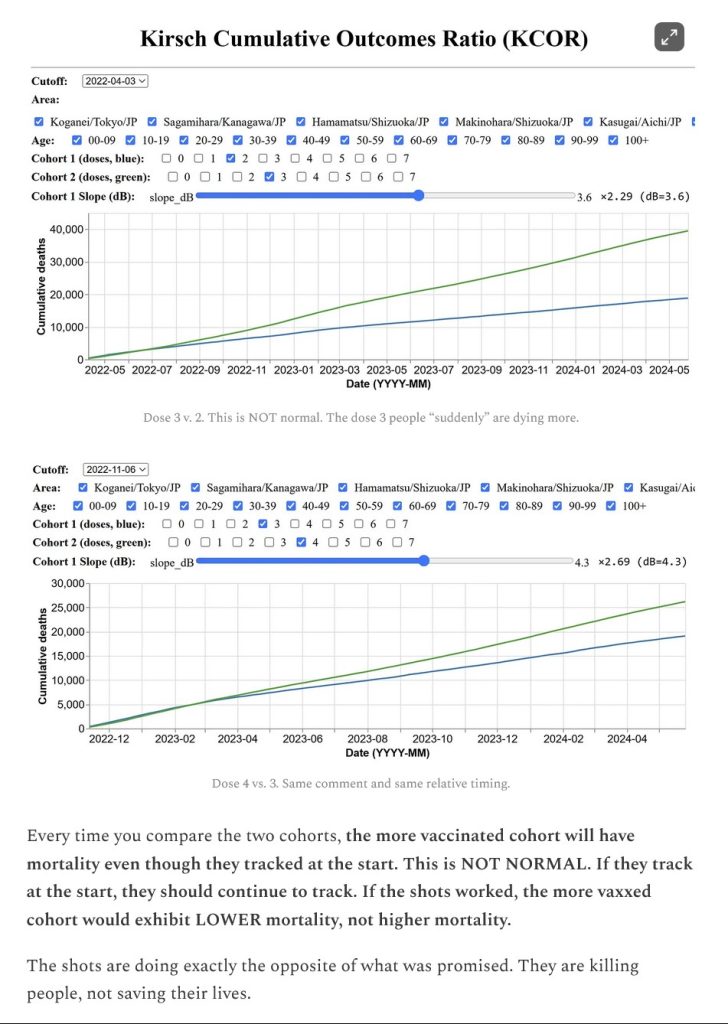
Steve Kirsch posted an article this week on his Substack blog regarding the Japan CMRR data, which proves that the more COVID-19 “vaccine” injections a person takes, the more risk that person has of dying:https://kirschsubstack.com/p/japan-cmrr-data-website-shows-clear, “Japan CMRR data website shows clear mortality increase caused by COVID shot”, 20 October 2025. Please see the screenshot from his article, below. (Note: CMRR = Cumulative Mortality Risk Ratio.) The first screenshot is of the general summary chart:
The second screenshot is from the Kirsch KCOR analysis of the Japan data, along with text summary;
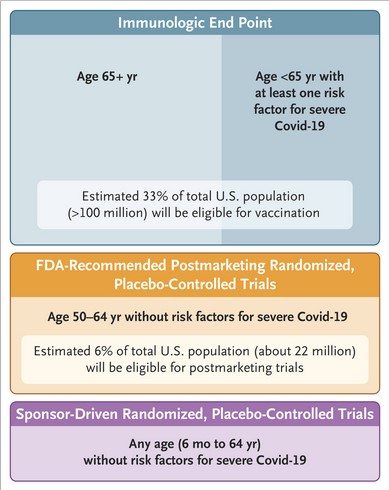
Applying all of the above to persons who, for whatever reason, are residents / patients in nursing homes or care / rehabilitation facilities: How do these people, if they do NOT want to take a COVID-19 “vaccine” injection, make their decision clear to the staff, including to the medical staff? How are these people assured, that if they do NOT want to take a COVID-19 “vaccine” injection, and there is an outbreak of COVID at the facility, that they will have access to Ivermectin, Hydroxychloroquine, Vitamin D, Zinc, and other alternative treatments for prevention or treatment of a COVID infection? How are these people assured, if they do NOT want to take a COVID-19 “vaccine” injection, that they will NOT be moved into a “segregated area” of the facility; or, worse yet, be told (or, their family / guardian be told) that the resident / patient “has to find another facility?” The issue is compounded by the fact that almost all nursing homes and care / rehabilitation facilities receive CMS funding or payments of some kind. Also, there is the “Next Generation Gold Standard” of “evidence-based COVID-19 vaccination” guidelines that were announced and implemented by HHS / NIH / CDC / FDA earlier this year. These guidelines “recommend” that persons age 65 and older get a COVID-19 “booster shot” TWICE a year. What does this mean for the person living in a nursing home in, for example, Alabama, (a facility that receives CMS funding or payments) — a person who is competent to make their own decisions, and who decides to refuse to take a COVID-19 “vaccine” injection? What if that person refuses because of religious belief? What if the person refuses because the “vaccine” contains elements lab-recreated from aborted fetal blood cell lines (the HEK293 lines?) Does the facility then “have the right”, because of the “new guidelines” in the “Evidence-Based Approach to COVID-19 Vaccination” that have been implemented, to override the person’s decision and give the injection anyway? Does the facility now “have the right” to tell the person’s children / guardian that they need to “find another facility” to take the person? Please see: https://www.hhs.gov/press-room/hhs-nih-announce-generation-gold-standard.html; also, https://www.nejm.org/doi/full/10.1056/NEJMsb2506929, “An Evidence-Based Approach to COVID-19 Vaccination”, Martin Makary, MD, MPH, and Vinay Prasad, MD, MPH. Dr. Makary is the Commissioner of the FDA; Dr. Prasad is the Director of the CBER Division of the FDA. Please see the screenshot of Figure 3 from this NEJM paper, below:
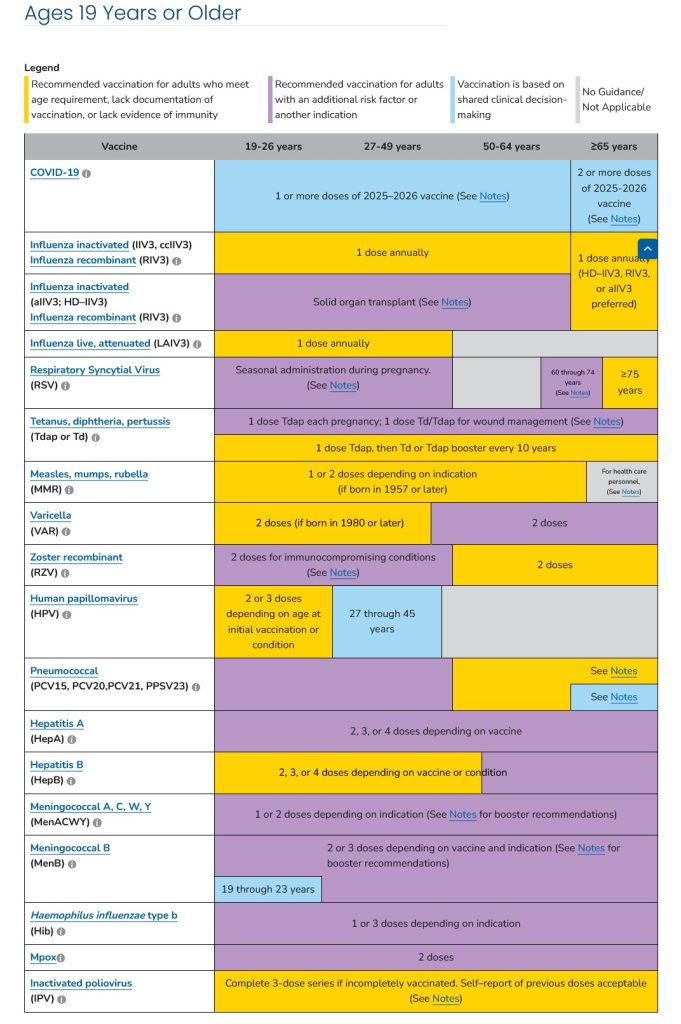
In addition, please see the age 65 and older immunization schedule recommendations for other injectables on the chart above — Influenza; RSV; pneumonia; Monkeypox; Herpes Zoster (“Shingles”); Hepatitis A and Hepatitis B; and more.
There is now supposed to be “Shared Clinical Decision-Making” between patient and healthcare provider regarding the COVID-19 “vaccines” for persons age 19 and above. Does that also apply across the board to persons living in nursing homes or care / rehabilitation facilities who are competent, but the facility they reside or stay in is also receiving CMS and/or Medicare-Medicaid payments?
There are multiple “Notes” sections regarding the administration of the other “vaccines” listed above in persons age 65 and older (and, in some cases, age 60 and older.) These “Notes” are found here: https://www.cdc.gov/vaccines/hcp/imz-schedules/adult-notes.html#note-covid-19; please scroll down this webpage and click on the topic to read about, such as, “Influenza vaccination.” There are multiple “vaccines” that are considered to be “routine”, such as the influenza “vaccine”, the RSV “vaccine”, and so on. What if a person living in a nursing home or care / rehabilitation facility decides to refuse all of these “routine” injectables, or decides to take only one or two? What happened to “Shared Clinical Decision-Making” in regards to this? Especially in light of new research that proves, for example, that the pneumonia “vaccines” actually increase the risk of contracting pneumonia and dying from said infection? Please see: https://www.thefocalpoints.com/p/breaking-223-million-person-study, “BREAKING: 2.23 Million Person Study Finds Pneumococcal Vaccines Increase Risk of Pneumonia and Death”, Nicolas Hulscher, 22 October 2025.
And, what about the COVID-19 “vaccinated” personnel (administration staff; doctors; nurses; CNAs / PCAs; facility maintenance staff; kitchen staff, etc.) who work at these nursing homes or care / rehab facilities? What about the “downstream Medical Tsunami” of negative effects on them of the “vaccines” that they took, which will present at some point, if not already? What about potential staff loss / turnover?
And, what about the vast majority of the adultchildren of these residents / patients, who are themselvesalso COVID-19 “vaccinated” — including the adult children who have already taken multiple injections of these “vaccines?” What about the “downstream Medical Tsunami” of negative effects on them of the COVID-19 “vaccines” that they took, which will present at some point, if not already?
And, what about the potential for another “pandemic emergency” being declared (including from some type of Avian Influenza outbreak) that “mandates” another round of “lockdowns”, which would effect nursing homes or care / rehab facilities?
In Yours Truly’s opinion, these are all things that need to be brought into the daylight and discussed. They represent another “ripple effect” aspect of the ongoing disaster of COVID-19.
THERE. MUST. BE. ACCOUNTABILITY.
THERE. MUST. BE. JUSTICE.
THERE. MUST. BE. TRUTH.
Peace, Good Energy, Respect: PAVACA
(Intellectual Property Disclaimer: With the exception of links to published scientific papers, website articles, and other items in the public domain, the ideas and conclusions in this post are by PAVACA. Proper credit must be given if ideas or conclusions of this post are used by other blog writers, or on social media, or in print media. Thank you.)
The free vintage header image for today’s offering of human chromosomes as drawn by hand is courtesy of iStock and Google Images.
Health Friday is a series devoted to Big Pharma, vaccines, general health, and associated topics. Today’s offering is dedicated to all persons, of whatever age or location, who have suffered injuries, illnesses, or disabilities resulting from an infection of the COVID-19 virus itself, or from having been injected with the COVID-19 “vaccines”; and, to those who have died from either an infection of the COVID-19 virus itself, or from the negative effects of the COVID-19 “vaccines” that they had taken.
There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. These are linked here. Note 1: Yours Truly has checked today’s offering for AI-generated content. To the best of her knowledge and belief, there is none, except possibly for some items embedded in linked URLS. If readers wish to add AI-generated content to today’s discussion thread, they must cite their source. Note 2: Starting with today’s offering, there will be an “Intellectual Property” notice at the end of the post. This is because Yours Truly has noticed that another blog has apparently modified and used certain information in a Health Friday post on their own blog without giving credit to Yours Truly. Thank you.
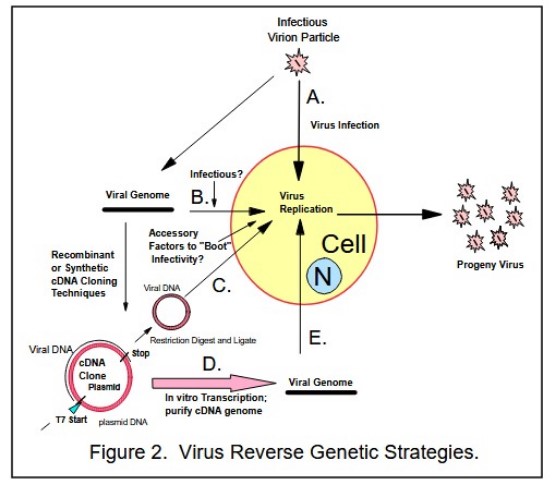
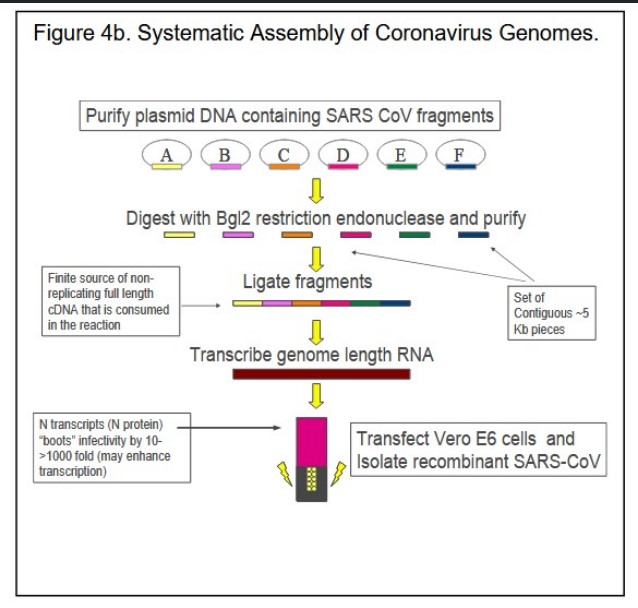
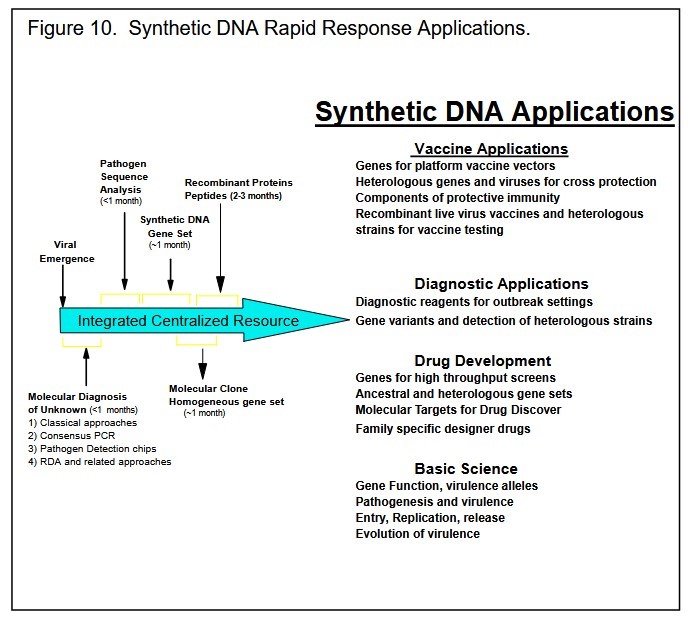
Yours Truly posted Part One of the LINE-1 and Chromosome 19 situation regarding the modRNA COVID-19 “vaccines” here: https://www.theqtree.com/2025/09/25/health-friday-9-5-2025-open-thread-human-line-1-chromosomes-and-the-modrna-covid-19-vaccines-part-one/. Part One discussed the (permanent) alteration to the LINE-1 human cell line that was designed into the modRNA COVID-19 “vaccines.” Part Two will discuss the alteration to the human Chromosome 19 (along with alteration to other human chromosomes) that were ALSO designed into the modRNA COVID-19 “vaccines.” To begin Part Two, here is a “refresher” on the paper that was published by Ralph Baric, PhD, of the University of North Carolina, Chapel Hill, on “Synthetic Genomics.” This paper has multiple graphics that display his “templates” for lab-creating synthetic viruses that are “programmed” to alter the DNA, the cells, and the chromosomes of humans: https://www.jcvi.org/sites/default/files/assets/projects/synthetic-genomics-options-for-governance/Baric-Synthetic-Viral-Genomics.pdf, “Synthetic Viral Genomics: Risks and Benefits for Science and Society”, Ralph S. Baric, PhD, 2006. Screenshots of a few of the graphics in this paper are below:
Note the phrase, “…reverse genetics and directed evolution.” Keep this phrase in mind for later in today’s offering.
And now, Yours Truly presents Part Two, beginning with human Chromosome 19, one of the 23 pairs of chromosomes that make up the human chromosome “map.” Below is an image of human Chromosome 19, per Wikipedia (https://en.wikipedia.org/wiki/Chromosome_19.) One of the two parts of the chromosome pair is from the father; the other is from the mother:
Then, a description of a set of conditions called 19p13.13 Deletion Syndrome:
A short discussion of other types of conditions related to human Chromosome 19 issues:
And, human Chromosome 19 in relation to Cancers:
Below is a screenshot of the Chromosome 19 Disease Map that was published in 1997 (https://www.liebertpub.com/doi/10.1089/gte.1997.1.145, “Disease genes and chromosomes: disease maps of the human genome. Chromosome 19”, by F Gilbert):
There has been more research since 1997 into human Chromosome 19 and its relationship to diseases and health conditions. An example is here: https://doi.org/10.1038/s41598-021-91924-7, “Mutant p53 and chromosome 19 microRNA cluster overexpression regulate cancer testis antigen expression and cellular transformation in hepatocellular carcinoma”, Goodwin G. Jinesh, et al., 16 June 2021. Two screenshots from the Introduction of this paper are below:
Take a look again at the 1997 graphic above, and note the areas of human Chromosome 19q.13, q.13.2, q13.32, and q13.34 on the Disease Map that influence the body. An interesting paper from 2018 regarding human Chromosome 19 and what occurs when there is dysregulation is here: https://pmc.ncbi.nlm.nih.gov/articles/PMC6112826/, “Cancer and the junkyard chromosome: how repeat DNA sequence on chromosome 19 influences risk of malignant disease”, Anne M. Rose, 10 August 2018. Two screenshots from this paper are below. The point here is that human Chromosome 19 is a “rich and fertile ground” for those who wish to experiment with how to alter certain areas of the chromosome, such as the p area or the q area; both of these chromosome 19 areas influence multiple organs and functions of the human body:
**** It appears, then, that the modRNA COVID-19 “vaccines” interact with both the p53 protein AND human chromosome 19 to induce cancers in “vaccinated” persons; and, that the SV40 African Green Monkey cancer promoter gene code piece that is ALSO in the modRNA COVID-19 “vaccines” is also involved regarding the inducement of cancer in “vaccinated” persons.
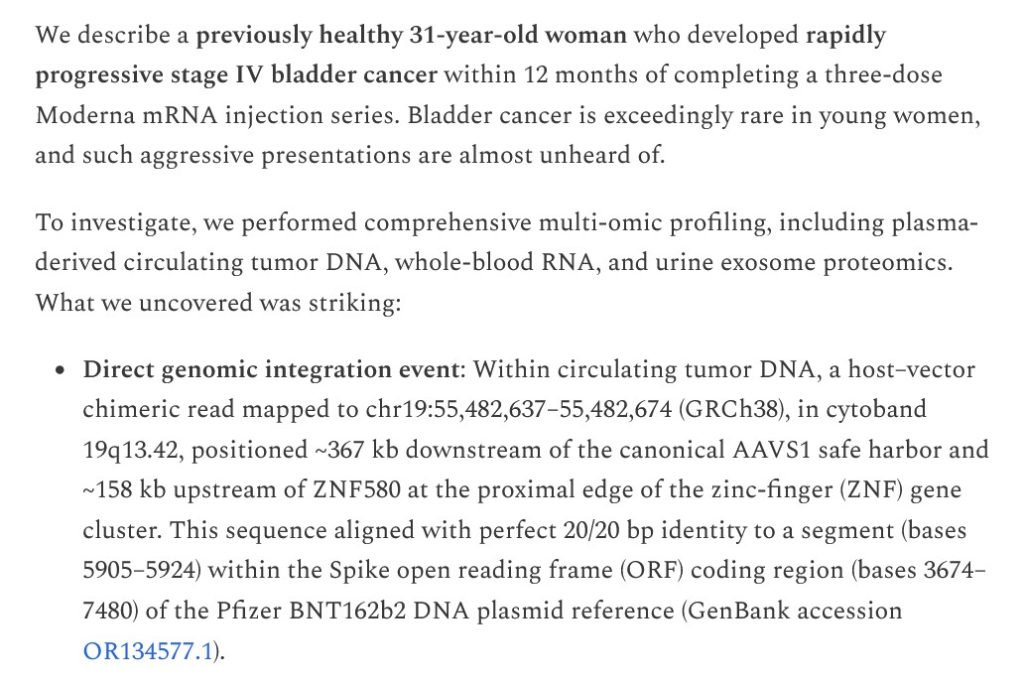
Which brings Yours Truly to this, a paper proving the first DIRECT evidence of human Chromosome 19 being altered by the modRNA COVID-19 “vaccines”, which then induce Stage IV bladder cancer: https://www.thefocalpoints.com/p/breaking-study-first-direct-evidence, “BREAKING STUDY: First Direct Evidence of mRNA “Vaccine” Genomic Integration Identified in Stage IV Cancer Patient”, Nicolas Hulscher, MPH, 15 September 2025. Please see the screenshot from this article, below:
Note regarding the above: the sequences identified which induced the Stage IV bladder cancer in the patient were contained within the Spike protein (S protein) of the Moderna modRNA COVID-19 “vaccines” that she took, not from within the Nucleocapsid protein (N protein.)
The young woman in question took THREE injections of the Moderna modRNA COVID-19 “vaccine” (mRNA-1273) during 2021 (the “primary series” plus one “booster shot.”) She was diagnosed with Stage IV bladder cancer within twelve months.
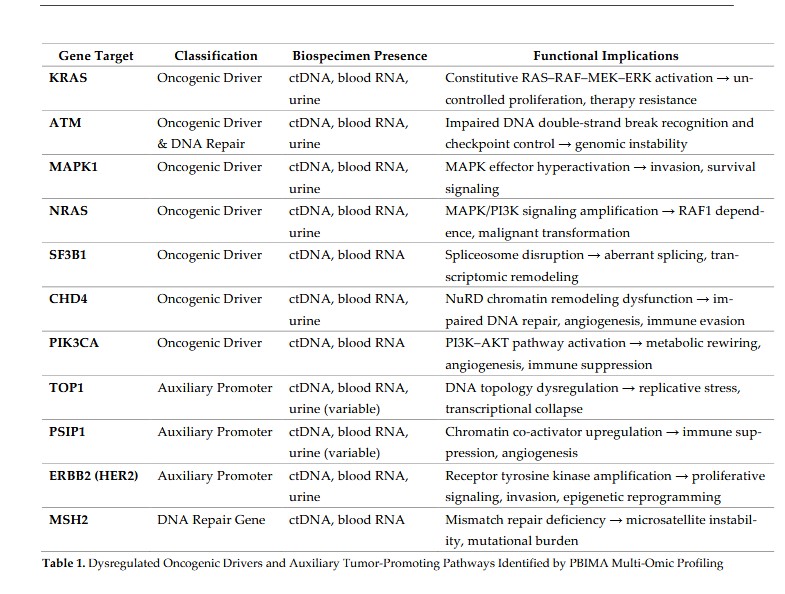
The paper is on the preprint server, Zenodo: https://zenodo.org/records/17122912, “Genomic Integration and Molecular Dysregulation in Aggressive Stage IV Bladder Cancer Following COVID-19 mRNA Vaccination”, John A. Catanzano, Nicolas Hulscher, Peter A. McCullough, 15 September 2025. Please see the following screenshots from this paper; first, Table 1. from the Case Presentation. Table 1. outlines the exact “drivers” and “pathways” that established the bladder cancer in the previously-healthy 31-year-old patient after she took the three Moderna modRNA COVID-19 “vaccine” injections:
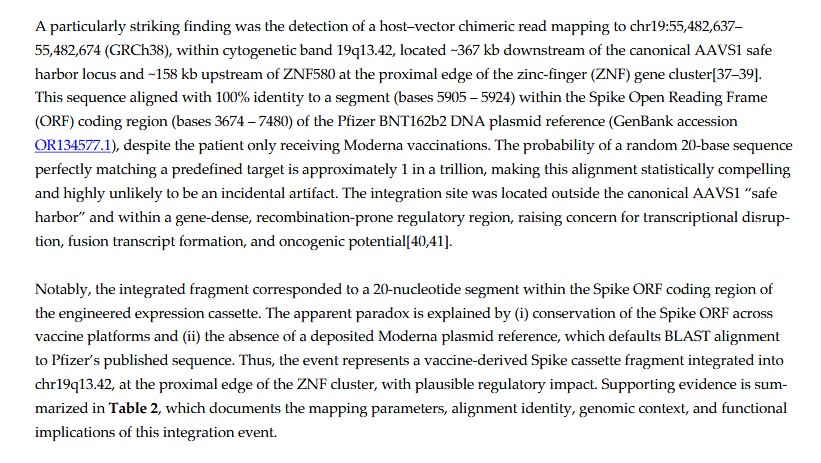
Second, from the Case Presentation in the paper. Please note the mention that numerous human Chromosome 19 alterations induced by the Moderna modRNA COVID-19 “vaccine” EXACTLY MATCH the same Open Reading Frame (ORF) sequences in the Pfizer-BioNTech modRNA COVID-19 “vaccine” (BNT162b2):
Which means that the alterations to human Chromosome 19 in BOTH the Moderna AND the Pfizer-BioNTech modRNA COVID-19 “vaccines” occur within the Open Reading Frame of the spike protein (S protein.) This chromosome altering capability is thus then present in all “descendant modRNA COVID-19 vaccines” from these companies, including the “2025-2026 version” of Pfizer-BioNTech (COMIRNATY) and of Moderna (SPIKEVAX), since said “descendant COVID-19 vaccines” all employ the S protein from the original COMIRNATY or SPIKEVAX injectables.
From the Discussion section of the paper. Please read the screenshot below carefully. This is a description of how the modRNA COVID-19 “vaccines” induce TURBO-CANCER:
**** What we have here is proof that the oncogenic driver known as human Chromosome 3q26.32, Gene PIK3CA — was included in the modRNA of the Moderna COVID-19 “vaccine” mRNA-1273. Please see the Catanzano, et al., paper cited above: the Table 1., and the Discussion screenshots; and, also, the OMIM Phenotype – Gene Relationships table cited further down in today’s offering (though the OMIM table refers to colorectal cancer, PIK3CA is a driver for other cancers, also.
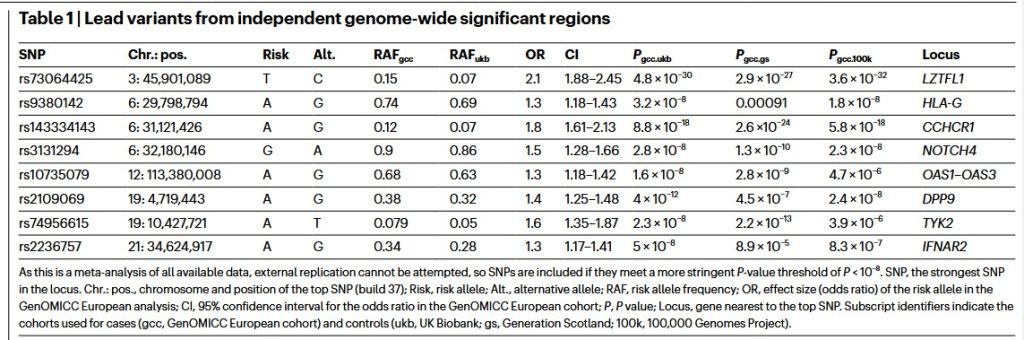
**** However, there is another element in play here: the Wuhan Hu1 virus itself (aka the SARS-CoV-2 virus itself / the COVID-19 virus itself) ALSO targets and attacks human Chromosomes: in particular, Chromosomes 3, 6, 12, 19, and 21. Please see this paper from December 2020, regarding a study performed on patients in the UK who were sick from the COVID-19 virus itself: https://www.nature.com/articles/s41586-020-03065-y, “Genetic mechanisms of critical illness in COVID-19”, Erola Pairo-Castineira, et al., 11 December 2020. Two screenshots from this paper are below; first, from the general introduction:
Compare the references to human Chromosome 19p13.2 and human Chromosome 19p13.3 in the Liebert Chromosome 19 Disease Map graphic above in today’s offering. This is proof that those who lab-created the SARS-CoV-2 (COVID-19) virus itself , and those who lab-created the modRNA COVID-19 “vaccines”, did experiment with human Chromosome 19 in order to include aberrations to areas of this chromosome that could result in negative health outcomes BOTH for persons infected with the virus itself, and for persons who took the modRNA COVID-19 “vaccines.”
And, Table 1 from the above paper:
Note: 11 December 2020 was the date of the initial Emergency Use Authorization for the Pfizer-BioNTech modRNA COVID-19 “vaccine” BNT162b2 to be used in the United States. Given that it takes months for a scientific paper to be researched, written, and published, one can assume that the Pairo-Castineira, et al., paper, was begun several months before the 11 December 2020 publish date. Note: There are FOUR identified areas on human Chromosome 6 that are attacked by the COVID-19 virus itself.
This paper, from 2014, describes the multiple health conditions and diseases that are associated with alterations to / deletions involving, human Chromosome 6: https://doi.org/10.1016/j.jprot.2013.08.001, “The Human Proteome Organization Chromosome 6 Consortium: Integrating Chromosome-centric and biology/disease driven strategies”, P.A. Keown, et al., 4 April 2014. Please see the screenshot, below, from the Introduction of this paper:
From https://www.storymd.com/, the “Ideogram of human chromosome 6“, which lists the multiple health conditions and diseases associated with aberrations of / alterations to / deletions of, parts of human Chromosome 6. The ideogram is courtesy of the Office of Biological and Environmental Research of the U.S. Department of Energy, Oak Ridge National Laboratory:
Yours Truly firmly believes that, since human Chromosome 6 is also attacked by the SARS-CoV2 (COVID-19) virus itself; and, since the COVID-19 virus itself is the foundational element within all of the modRNA COVID-19 “vaccines” — that these “vaccines”, once injected into the body, can and will attack the human Chromosome 6 of the “vaccinated” person’s body, along with attacking human Chromosomes 3, 12, 19, and 21.
Yours Truly firmly believes that those who lab-created the COVID-19 virus itself, and the modRNA COVID-19 “vaccines”, experimented with human Chromosomes 3, 6, 12, 19, and 21, in order to introduce aberrations / mechanisms into them that could induce or aggravate health conditions and/or diseases that would not otherwise appear in healthy persons, then included the results of these experiments in both the virus itself, and in the modRNA “vaccines.
Yours Truly firmly believes that those who lab-created the modRNA COVID-19 “vaccines” then added the dangerous lipid nanoparticles (ALC-0159, ALC-0315, SM-102), and N1-Methylpseudouridine, to these “vaccines” to evade the human body’s immune system, to damage / destroy the human body’s immune system, and to damage / destroy the human body’s ability to detect and eliminate “enemy elements”, in order to force the “vaccinated” body to be defenseless to the negative effects of the modRNA COVID-19 “vaccines.” Thus, there are reports of, for example, Diabetes Mellitus resulting from modRNA COVID-19 “vaccination” by the Pfizer-BioNTech “vaccine”, BNT162b2, in this document: https://phmpt.org/wp-content/uploads/2021/11/5.3.6-postmarketing-experience.pdf, APPENDIX 1. LIST OF ADVERSE EVENTS OF SPECIAL INTEREST section.
FLASH! Yours Truly has just found more proof, in her opinion, regarding the experiments on human Chromosomes by those who lab-created the COVID-19 virus itself, and by those who lab-created the modRNA COVID-19 “vaccines”. Please see, first: https://www.theburningplatform.com/2025/10/16/8300-spike-in-colon-cancer-that-just-means-the-jabs-are-working/, “8300% SPIKE IN COLON CANCER — THAT JUST MEANS THE JABS ARE WORKING”, by Camus. A screenshot from this article is below:
The Burning Platform article is based on the recent research by Dr. Jessica Rose, PhD, of VAERS reports of colon cancer since 2021 (rollout of the modRNA COVID-19 “vaccines.”) She posted a blog article regarding her analysis, here: https://jessicar.substack.com/p/colon-cancer-on-the-rise-since-2021, 7 September 2025. The huge increase in colon cancer since 2021, per the VAERS reports, appears to be in children under age 18.
Please refer to the human Chromosome Disease Maps, and the screenshots from the 2020 paper of COVID-19 infected persons in the UK, above in today’s offering, regarding human Chromosome 3 and human Chromosome 19.
BOTH human Chromosome 3 AND human Chromosome 19 (among other chromosomes) show up on the Online Mendelian Inheritance in Man listing for #114500 COLORECTAL CANCER: CRC Phenotype – Gene Relationships: https://www.omim.org/entry/114500. The human Chromosomes that correlate to the COVID-19 virus itself, and therefore to the COVID-19 modRNA “vaccines”, are:
human Chromosome 3p22.1 Gene: CTNNB1 Colorectal cancer, somatic
human Chromosome 3q26.32 Gene: PIK3CA Colorectal cancer, somatic
human Chromosome 19q13.33 Gene: BAX Colorectal cancer, somatic
NONE of the above are inherited “predispositions.”
The OMIM table is below:
In Yours Truly’s opinion, there is no possible way that the detailed, precise experiments that had to have been performed with human Chromosomes 3, 6, 12, 19, and 21, in the lab-creation of the COVID-19 virus itself, and in the lab-creation of the modRNA COVID-19 “vaccines”, could have been accomplished just during the years 2019 – 2020. This is a process that would need several years of work, at the least.
Questions: What kind of POMC (Pieces of Human Excrement) would lab-create a virus, let alone a modRNA “vaccine”, that would induce colon cancer in anyone, let alone in children? What kind of medical professional would inject this type of “vaccine” into children? What kind of government agency would “recommend” that this type of “vaccine” be injected into anyone, let alone into children? What kind of “professional medical organization” (such as, the American Academy of Pediatrics) would “recommend” that this type of “vaccine” be injected into children?
IT IS OF UTMOST IMPORTANCE THAT ALL PERSONS BUILD AND MAINTAIN THEIR NATURAL IMMUNE SYSTEM TO BE IN THE BEST HEALTH POSSIBLE.
THE COVID-19 “VACCINES” — ALL OF THEM — MUST BE REMOVED FROM THE MARKET AND FROM USE. NOW.
THE ARRESTS OF THOSE WHO WERE / ARE INVOLVED IN THE ABOVE ACTIVITIES REGARDING THE LAB-CREATION OF THE COVID-19 VIRUS ITSELF, AND OF THE modRNA COVID-19 “VACCINES”, MUST START. NOW.
THERE. MUST. BE. ACCOUNTABILITY.
THERE. MUST. BE. JUSTICE.
THERE. MUST. BE. TRUTH.
Peace, Good Energy, Respect: PAVACA
Intellectual Property Disclaimer: With the exception of links to scientific papers, public-domain scientific research or information websites, and news / media / Substack outlets that are on the internet, the contents of the above article are the ideas and/or conclusions of the writer, PAVACA. Proper credit must be given to the writer (PAVACA) if the ideas and/or conclusions in the above article are used by any other blog author or writer, or by persons on social media and/or on podcasts, or by persons using print media. Thank you.
Joe Biden never won. This is our Real President – 45, 46, 47.
AND our beautiful REALFLOTUS.
This Stormwatch Monday Open Thread remains open – VERY OPEN – a place for everybody to post whatever they feel they would like to tell the White Hats, and the rest of the MAGA/KAG/KMAG world (with KMAG being a bit of both).
Our various sister sites, listed in the Blogroll in the sidebar
Our beloved country is under Occupation by hostile forces.
Daily outrage and epic phuckery abound.
We can give in to despair…or we can be defiant and fight back in any way that we can.
Joe Biden didn’t win.
And we will keep saying Joe Biden didn’t win until we get His Fraudulency out of our White House.
Wolfie’s Wheatie’s Word of the Week:
bobstay
noun
rope used on ships to steady the bowsprit
a rope or chain used to steady the bowsprit of a ship
a rope or chain to confine the bowsprit of a ship downward to the stem or cutwater
a strong rope or chain rigging running from the end of the bowsprit to the ship’s stem or cutwater
a part of the rigging of a sailing boat or ship that counters the upward tension on the bowsprit from the jibs and forestay
Used in a sentence
A bobstay may run directly from the stem to the bowsprit, or it may run to a dolphin striker, a spar projecting downward, which is then held to the bowsprit or jibboom by a martingale stay.
Shown in a picture
Shown in a very brief video
MUSIC!
In honor of today’s “stuff” (see below) we have this reaction video!
THE STUFF
This brilliant idea from 2020 may be one of the simplest and best proofs that COVID-19 came from a laboratory. Note that the idea could not get published until much later – after the “vaccines” were a done deal. This delay of publication is much like what happened to the very early discovery that simple OTC antihistamines protected highly vulnerable people from death by COVID, which was “sat on” by the journals until it missed the chance to save millions of lives.
This is not common knowledge. Professor Nikolai Petrovski, vaccine inventor in South Australia, just a few weeks into the Pandemic, new confidently that the virus was probably man made.
To the amazement of Dr Drew in this podcast from 10 x months ago, who thought it was new… pic.twitter.com/3XrDneeb7m
This is not common knowledge. Professor Nikolai Petrovski, vaccine inventor in South Australia, just a few weeks into the Pandemic, new confidently that the virus was probably man made. To the amazement of Dr Drew in this podcast from 10 x months ago, who thought it was new research, Nikolai Petrovski discusses how in “The first few week of 2020, when the viral sequence was first released” he was only “modelling the virus to build a vaccine”. The other clip is from an AMPS seminar held just over a year ago, which works in well with the DR Drew clip. “If it’s come from an animal source, then there should be an animal out there who’s ACE2 binds better to the virus than Human ACE2, [but] rather than finding some exotic animal at the top of the list, we found Humans”[and it was] so well human adapted. “It took a long time to get published, because the narrative was, that [it] was not an acceptable question to be asking.”
"In silico comparison of SARS-CoV-2 spike protein-ACE2 binding affinities across species and implications for virus origin". – Nikolai Petrovskyhttps://t.co/l4BQb6nRm9