Health Friday 9.4.2026 Open Thread: Countermeasures and Precautions: An Opinion Piece

The free vintage image of hand washing for today’s offering header is courtesy of Open Culture and Google Images. Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats by Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.

>>>>>>>>>>>>>>>>>>>>

Countermeasures and Precautions: An Opinion Piece

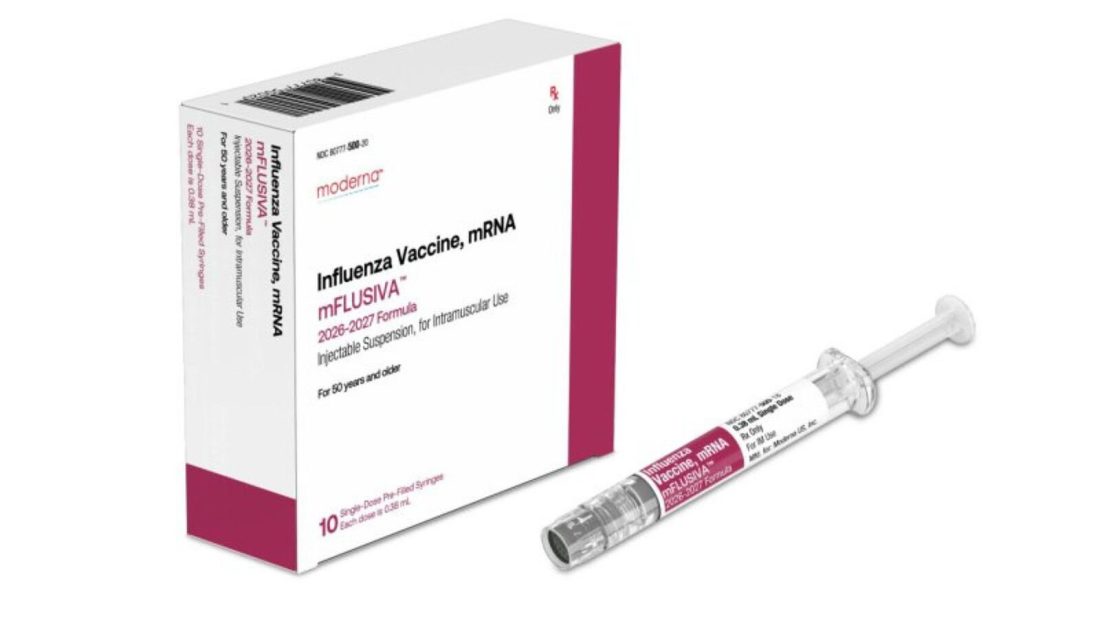
The following is not medical advice. The following is not “SHTF prepping.” The following is not intended to instill fear. The following are ideas and opinions for consideration regarding certain “ongoing and upcoming situations.” There are several areas to consider: First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA), the first modRNA-platform based influenza bioweapon “vaccine”; Second area: the FDA’s just approving the “latest version” of the COVID-19 bioweapon “vaccines” for 2026 – 2027, based only on testing performed on mice; and, Third area: the recent paper which proves that the spike protein and other ingredients of the COVID-19 bioweapon “vaccine” injections remain active in the “vaccinated” person’s body for at least 3 1/2 years post-final “vaccine” injection.

>>>>>>>>>>>>>>>>>>>>

First area: the FDA’s recent approval of mRNA-1010 (mFLUSIVA): this situation has been covered extensively (and will continue to be covered) on this board; by our host, Wolf Moon, and by Yours Truly, among others who posted items related to the situation. The bottom lines of mFLUSIVA: One: this “vaccine” killed more than twice the number of clinical trial study subjects who took it, as compared to those study subjects who took the “comparator influenza” vaccine, Fluarix; Two: Moderna knows that mFLUSIVA can shed — study subjects were required sign an agreement to use birth control before, during, and after, their participation in the clinical trial; Three: mFLUSIVA was FDA-approved on “Accelerated Approval” for persons age 65 and over. Accelerated Approval means that Moderna must agree to perform a clinical trial of the “vaccine” using persons age 65 and older; Four: Moderna must also agree to track reports of deaths in persons who take mFLUSIVA. Our host, Wolf Moon, has written about mFLUSIVA; for example, here: https://www.theqtree.com/2026/08/07/a-grok-eyed-view-of-the-new-mrna-flu-shot/.

Second area: the FDA’s just granting approval for the “latest version” COVID-19 bioweapon “vaccines” for 2026 – 2027. The bottom lines: One: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Pfizer-BioNTech based on lab testing on 8 mice; no human trials. This follows the “Option 4” protocol for formulation of new COVID-19 bioweapon “vaccines” that was adopted by the FDA in 2022; Two: the FDA granted approval for the 2026 – 2027 “latest version vaccine” by Moderna based on lab testing on 10 mice, again following the “Option 4” described above; Three: based on the “ruling” against HHS by Federal Judge Brian E. Murphy earlier this year, these “latest version” COVID-19 bioweapon “vaccines” will be administered to persons from age 6 months and older. Please see: http://www.thefocalpoints.com/p/breaking-fda-approves-new-pfizer, “BREAKING: FDA Approves New Pfizer and Moderna XFG mRNA COVID-19 Shots Based on Data From Just 8 – 10 Mice”, Nicolas Hulscher, MPH, 27 August 2026

Third area: the McCullough, et al., paper, which proves that serious adverse reactions and events can occur in COVID-19 bioweapon “vaccinated” persons at least 3.5 years after the last “vaccine” injection (https://www.thefocalpoints.com/p/breaking-peer-reviewed-study-finds-51c, “BREAKING: Peer-Reviewed Study Finds mRNA, SV40, and Spike Protein Can Persist in Humans for At Least 3.5 Years After COVID-19 “Vaccination””, Nicolas Hulscher, MPH, 9 July 2026; the paper cited is here: https://doi.org/10.18103/mra.2026.0351, “Persistence of Vaccine mRNA, Plasmid DNA, Spike Protein, and Genomic Dysregulation Over 3.5 Years Post-COVID-19 mRNA Vaccination”, Nicolas Hulscher, MPH, et al.; published 31 July 2026. The bottom lines: One: these “vaccines” can, and do, have continuous negative consequences in persons who take them for years afterwards; Two: that repeated injections of these “vaccines” accumulate / aggravate / induce, continuous attack on the “vaccinated” person’s entire body and immune system; and, Three: repeated injections of these “vaccines” have the potential for accumulated damage to the entire body and the destruction of the “vaccinated” person’s immune system.

>>>>>>>>>>>>>>>>>>>>

It is estimated that about 77.1% of the population of the United States has taken at least one injection of a modRNA-based COVID-19 bioweapon “vaccine” (https://dig.abclocal.go.com/ccg/interactives/us-vaccine-tracker/vax_us_cdc.html, “U.S. COVID-19 vaccine map by state”. It is estimated that 135.6 million persons in the United States took an influenza “vaccine” in the 2025 – 2026 season (https://www.cdc.gov/fluvaxview/dashboard/index.html.) It is unknown how many will be take mFLUSIVA; however, there are physicians actively promoting this injectable. In fact, mFLUSIVA is being promoted as the “replacement” influenza vaccine for persons age 50 and older (https://epicenter.nyc.com/what-to-know-about-the-new-mrna-flu-vaccine-for-those-over-50/, Ambar Castillo, 13 August 2026.

>>>>>>>>>>>>>>>>>>>>

Where does all of the above leave the 20% – 25% of Americans who do not have COVID-19 bioweapon “vaccines” in their bodies? Where does that leave those who have had a COVID-19 infection, have recovered, but still may have lingering issues stemming from the infection (Long COVID; systemic inflammations of one kind or another; lung issues, and so on)? Where does that leave COVID-19 “vaccinated” persons who have decided to never take another injection of any of them? Where does this leave Americans with the 2026 – 2027 “latest version” COVID-19 bioweapon “vaccines” coming on the market within weeks, coupled with the campaigns from Establishment Medicine / government agencies / employers, and other entities, to “make sure one is up-do-date” with the “latest version vaccine”? Where does this leave people who decide to not take mFLUSIVA? In Yours Truly’s opinion, it comes down to making individual decisions regarding personal (and, perhaps, family) “countermeasures and precautions” — and following them faithfully.

>>>>>>>>>>>>>>>>>>>>

What would these “countermeasures and precautions” include? Perhaps, these areas to start the consideration and decision process: Countermeasures: Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine); and, Vitamins, Supplements, and Foods. For Precautions: Lifestyle Protocols / Adjustments. Each of these have ramifications that impact finances; availability; and, interactions with people. Each of these require that people “do their own due diligence” in researching the “countermeasures and precautions” that they are considering implementing for themselves (and, perhaps, for their family.)

Protocols using repurposed drugs (Ivermectin, Hydroxychloroquine): These, in Yours Truly’s opinion, are the “core” of COVID-19 infection prevention or treatment. Independent Medical Alliance has both prevention and treatment protocols for COVID-19: https://imahealth.org/treatment-protocols/. Another protocol is found here: https://www.2ndsmartestguyintheworld.com/p/bombshell-shocker-the-cia-and-pfizer, “BOMBSHELL SHOCKER: The CIA & Pfizer LIED To The Public About The Need For Their $afe & Effective PSYOP-19 “Vaccines””, 2 September 2026; scroll down to the end of the post for “The Ultimate Disease Cure & Prophylaxis Protocol” section.

Vitamins, Supplements, and Foods: First, Vitamins and Supplements: Vitamin C and Vitamin D, for example, can help to bolster the body’s immune system. Supplements such as Zinc, Magnesium, and Quercetin help to keep the lungs clear (Zinc); to regulate many enzyme systems in the body (Magnesium); and, to increase or maintain anti-inflammatory and antioxidant protection (Quercetin.) Please see: regarding Zinc: https://pmc.ncbi.nlm.nih.gov/articles/PMC131177/, “What does zinc do?”, Abi Berger; 9 November 2002; regarding Magnesium: https://ods.od.nih.gov/factsheets/Magnesium-HealthProfessional/; regarding Quercetin: https://www.healthline.com/nutrition/quercetin, Ryan Raman; 7 May 2026. Many brands of multivitamins contain a more-or-less good range of vitamins and minerals; however, the amounts per vitamin or mineral may or may not satisfy the needs of the individual; in those instances, separate supplementation may be desired. Vitamin D uptake from sunshine can be done in many different and healthy ways.

Second, Foods: There is a saying, “Let food be thy medicine.” For some people, a diet that satisfies what is necessary regarding not only nutrition, but also for vitamins and minerals, may be one approach. An example for inclusion in such a diet is eggs (https://www.roswellpark.org/cancertalk/202504/are-eggs-good-you, “Are eggs good for you?”, 18 April 2025.) The “humble egg” is actually a “mini-powerhouse” of vitamins and minerals: Vitamins A — B2 — B12 — E; Lutein; Iodine; Selenium; and more; in addition to protein. Another example, this time of vegetables, is carrots (https://www.healthline.com/nutrition/foods/carrots, “Nutrition and Health Benefits of Carrots”, Adda Bjarnadottir, MS, RDN (Ice), 22 July 2026. Carrots provide beta-carotene (the body converts this into Vitamin A); fiber; antioxidants; and more. Carrots also may help support eye health, among other positive effects. Of course, there is red meat: https://pmc.ncbi.nlm.nih.gov/articles/PMC7015455/ , “What is the role of meat in a healthy diet?”, David M Klurfeld, July 2018. In addition to its being a complete protein, red meat also provides vitamins, amino acids, zinc, and iron.

Precautions: This area includes decisions regarding interacting with others who are COVID-19 “vaccinated”; whether or not to attend large-gathering places; and, if a non-COVID-19 “vaccinated” person is living with other who are “vaccinated”, among other situations. In no way is Yours Truly advocating that non-COVID-19 “vaccinated” people become “modern-day anchorites” with little or no contact with others. However, there are things that non-“vaccinated” people can do to reduce the potential for being exposed to “vaccine” shedding; and, to the potential for being infected by the COVID-19 virus itself. Examples: using disposable gloves at the gas pump; deciding whether or not to use “contactless” payment methods, as opposed to handing a credit card to someone; if possible, sitting at the back of a large-gathering event or facility; changing clothes after returning home from a family visit or going to a large-gathering event; taking an appropriately extra amount of, for example, Vitamin D before attending such an event; taking an appropriate extra dose of Ivermectin or Hydroxychloroquine after attending such an event; among others. Living with, or paying extended visits to, COVID-19 “vaccinated” people is another, and perhaps more difficult, area. Considerations here may be, for example, deciding to take Ivermectin on a weekly basis if a non-COVID-19 “vaccinated” person is part of a family (or, has roommates, etc.) that includes “vaccinated” people living in the same house. Please see: https://www.midwesterndoctor.com/p/covid-19-vaccine-shedding-experiences, “What We’ve Learned from Over a Thousand Vaccine Shedding Reports”, 7 January 2024.

>>>>>>>>>>>>>>>>>>>>

There is another, and important, area, to consider: interactions between drugs that are prescribed for particular needs, and repurposed drugs (such as, Ivermectin.) Please see: https://my.clevelandclinic.org/health/articles/drug-interactions. The Cleveland Clinic defines a drug interaction as what happens when “foods, drinks, dietary supplements, other drugs, prevent medications from working as they should.” For example, Ivermectin interacts with warfarin (Coumadin), and with other drugs: https://www.medicalnewstoday.com/articles/drugs-ivermectin-oral-tablet-interactions, Ashley Wong, PharmD, Last updated 17 January 2025. Ivermectin is also known to interact with: ketoconazole (an antifungal drug); and, with ritonavir (an HIV/AIDS treatment drug: please see https://synapse.patsnap.com/article/what-is-ivermectin-used-for); with benzodiazepines; and with alcohol (increased dizziness risk.) If using Ivermectin along with warfarin, it is important to keep a check on INR levels; it may also be germane to advise the healthcare professional who prescribed the warfarin, that Ivermectin is also being taken. Readers interested in investigating the potential for drug interactions regarding prescription drugs they take; and, for more information on prescription drugs, vitamins, and supplements (minerals) may wish to visit https://www.drugs.com/, or https://www.goodrx.com/. Note: be aware that these websites (and similar ones, such as the search engine at https://www.webmd.com/) appear to be biased against, for example, Ivermectin, except for the very narrow FDA-approved uses of this drug (to treat river blindness or lice.) The FDA still does not approve of Ivermectin for the prevention or treatment of COVID-19.

>>>>>>>>>>>>>>>>>>>>

There is one final area to consider as a COVID-19 and/or mFLUSIVA countermeasure: regular mild to moderate exercise, at least five days a week for 20 – 30 minutes a day. If this exercise can be done in the open air, in the sunshine, there is even more benefit. And the exercise does not have to be strenuous: for example, Tai Chi sequences, practiced correctly and with using proper breathing techniques, can provide a “slow-motion” cardio workout. Just wearing a pedometer to count steps, or staying active inside the house, can help. The point is to avoid being sedentary. Please consult a health professional before starting, or increasing, an exercise program, especially if one is recovering from an illness, has certain health conditions, and so on.

Peace, Good Energy, Respect: PAVACA1

(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1. Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)


Dear MAGA: 20260827 ✾ TRUST THE PLAN ✾ Thursday Open Topic | Lunar Eclipse | An Inconvenient Study


Sometimes you have to have faith.

Yes, Virginia, there is a Plan!


We have created this site as a place for people to openly express their thoughts and opinions. This is a place where honest but civil discussion of all topics is encouraged. This particular thread is – for the moment – TRUST THE PLAN Thursday. You are welcome to say what you think, in a civil and courteous manner that loves your neighbor. Free speech matters! Courteous speech makes it happen.

Please label all AI-generated content as being such, unless it is patently obvious (e.g., humorous AI images). It is important that we as individuals not begin to pretend that socially derived artificial intelligence is actually our own, as this form of stealthy social information averaging and feedback would be one more pretense and deception between people, in service of stupid Marxist socialism, and of those who wish to substitute their communally protected lies for actual truth.

You are you. AI is AI. Keep your identity. Don’t “Borg Out” on us!

And yes, it’s THURSDAY…again.

That was stolen from Wheatie.

Let’s steal her rules, too.

  • No food fights.
  • No running with scissors.
  • If you bring snacks, bring enough for everyone.

Other rules may be derivable from these, and that conjecture is left for discussion.


Our Mission Orders

Just to make sure you can see that…..


Retrocultural Reminders (Future Proves Past, Past Anchors Future)

Pontifications

Lunar Eclipse

First, I’m reposting a tweet that Kalbo posted, about an almost-complete lunar eclipse on Thursday night.

Good coverage here, including what to expect…..

https://www.beaconjournal.com/story/lifestyle/nature-wildlife/2026/08/25/timeline-date-blood-moon-lunar-eclipse-august-2026-full-moon/91441753007

Steve is probably excited and ready to observe it. Say a prayer for Steve! Yes, now that he’s not here, we can openly pray for Steve and not worry about offending him!

And now, very importantly…..


An Inconvenient Study

MarieUrsula dropped off a link for one of the best documentaries I’ve seen in years – and IMO you would do well to watch this, too.

Her comment:


MarieUrsula

MarieUrsula (@guest_1644157) Online

August 25, 2026 00:55

#1644157

Found on my trapline a few hours ago, on a related subject:

“Here’s a story about vaccines with danger, deception, and intrigue, like a thriller. It’s an important piece of the vaccine puzzle. Produced by Del Bigtree, it’s essential for anyone still considering the validity of vaccines.” c. 1 hour 22 minutes.

https://www.aninconvenientstudy.com


You can actually download the movie yourself (below), or watch it online at the link (above). Both are FREE.

Downloadable Link (MP4 Format) – https://static.arkengine.com/video/cmgoige8f000g6dc3us4ib19o/file/mp4/AIS_1_5.mp4

This movie explains a whole bunch of things – even more than they intended to explain. The logic is beautiful. Del Bigtree is a truly excellent journalist. He understands exactly how to make things make sense with zero ambiguity.

This movie explains…..

  • numerous problems with vaccines
  • a critical study which went unpublished because it gave the wrong finding, but had a “plausible” exit for the author and institution
  • why RFKJ wants to do placebo studies
  • how the vaxxbots skate out of placebo studies on bogus ethics grounds

IMO RFKJ neatly avoided an ETHICS TRAP on the mRNA flu vaccine. Had he forced the issue of a placebo trial for mFlusiva, IMO he would have been set up for ethics charges by the Demoncrats. As things are unfolding, NATURAL CONSEQUENCES for the TRABANT SHOT are happening!

Watch the film and see if you agree!

W


Don’t take the Trabant Shot! You deserve better!

Dear MAGA: 20260818 ❀ DePat Tuesday ❀ Open Topic | Is There Another Cell Nucleus Hall Pass in the New mRNA Flu Vaccine, mFlusiva?

This DePat Tuesday Open Thread honors the author of the original Tuesday open thread on this site, namely the late Susie Sampson, a.k.a. Deplorable Patriot, among her other handles, pen names, etc.

For more on the untimely passing of Dear DePat, please see these three posts.


At one time, DePat handled FOUR daily open threads here, in addition to taking care of her relatives, choir duties, and numerous other responsibilities. She was a powerhouse – a dynamo – a true force of nature.

DePat’s faith in Trump, Q, “The Plan”, the White Hats, and “the anons” in general, was legendary. Although I didn’t always agree with her quick acceptance of some sketchier evidence and fringier theories, I will gladly admit to “coming around” to numerous so-called “conspiracy theories” which she championed first. I was always careful to give her credit for being right, too, when I had been wrong.

It is impossible to overstate how much DePat did for not only this site, but for her country. I urge all to say a quick prayer of thanks, whenever you think of her, for the privilege of knowing, in life or after death, such an exemplary human being, and lover of God.

And thank you, Susie, for the firm foundation which you left us, when you were called to your true home!


Is There Another Cell Nucleus Hall Pass in the New mRNA Flu Vaccine, mFlusiva?

Let’s start off with some history.

Are you aware of the fact that both the Moderna AND the Pfizer COVID vaccines contained a genetic sequence that acts like a “hall pass” or “VIP ticket”, allowing the holder to get into the nucleus of human cells?

Here is a post where I explained this.

Were it not for somebody dropping a link to an obscure paper in my Twitter timeline back in early 2023, I would have never realized how extra sketchy that made both the virus and the vaccines – and especially the latter, since it would have been theoretically possible to remove the nuclear hall pass from the spike protein used as the vaccine.

Let me repeat that. They left the “hall pass” in the mRNA code for the vaccine.

But – and I have to stress this – it was not just that this “hall pass” was there. No. It was much worse. The paper in question was experimental, and it showed that the viral spike protein not only contained the hall pass, but that it WORKED. The hall pass actually worked to get the spike protein into the nucleus. They even had PICTURES of it in the nucleus.

LINK: https://www.frontiersin.org/journals/microbiology/articles/10.3389/fmicb.2023.1073789/full

BUT WAIT! THERE’S MORE!

The hall pass not only got the spike protein into the nucleus – the spike protein THEN got the mRNA that coded for it into the nucleus, as well.

Yes. You are reading that correctly. The spike protein of SARS-CoV-2 has a known sequence in it that ends up getting both IT and the mRNA that created it, into the cell nucleus.

One would THINK that this might be a big deal. Especially after we were REASSURED that NO, VIRGINIA – THE mRNA WILL NEVER, EVER GET INTO THE CELL NUCLEUS, YOU FOOLISH VACCINE SKEPTICS.

Are you seeing why this is kind of a big deal?

SO – NOW – my question about the new mRNA flu shot is similar.

I could ask whether the flu vaccine’s “spike protein” (it’s called a “hemagglutinin glycoprotein”) also has a hall pass that gets it into the cell nucleus. I could even ask if the influenza HA glycoprotein also “escorts” its own mRNA into the nucleus, as does the COVID spike protein.

However, that requires experimentation. I can’t do that work.

OK – can I just ask if the mRNA flu shots contain the hall pass into the nucleus?

Well, it turns out that you can ask, but there’s not necessarily an answer.

I could not find the answer, so I asked Grok.

And I asked Grok a slightly less pointed version of the question, since I am perfectly capable of checking for nuclear translocation sequences myself, so that Grok would not detect “conspiracy theory thinking” on my part, and thereby not consign my question to the “talk down to this human” conga line of incomplete answers.

LINK: https://x.com/i/grok?conversation=2088464094655385678


Q: Is there a published mRNA sequence for the new mRNA flu vaccine, mFlusiva, from Moderna?


A: (from Grok)

No, there does not appear to be a publicly published full mRNA (nucleotide) sequence for Moderna’s mFlusiva (mRNA-1010).

mFlusiva is the FDA-approved (as of early August 2026) trivalent mRNA influenza vaccine for adults 50+ (traditional approval for ages 50–64; accelerated for 65+). Each 0.38 mL dose contains 37.5 µg total mRNA (12.5 µg each of three RNAs) encoding the full-length hemagglutinin (HA) glycoproteins of the season’s recommended strains (for the 2026–2027 formula: A/Missouri/11/2025 (H1N1)pdm09-like, A/Michigan/105/2025 [A/Darwin/1415/2025 (H3N2)-like], and B/Pennsylvania/19/2025 [B/Pennsylvania/14/2025-like]), formulated in lipid nanoparticles (SM-102, PEG2000-DMG, cholesterol, DSPC).

Public documents (prescribing information/DailyMed, FDA briefing documents and clinical review, Moderna product pages, and peer-reviewed trial publications) describe the composition, encoded antigens/strains, manufacturing process (in vitro transcription, no cells/eggs), and clinical data, but they do not disclose the actual nucleotide sequences of the mRNAs. These would include codon optimization, specific 5′/3′ UTRs, poly(A) tail, nucleoside modifications (typically N1-methylpseudouridine, as used in Moderna’s platform), and any stabilizing mutations (noted for the influenza B HA in non-surface-exposed regions).

  • The underlying viral HA amino-acid (or genomic) sequences of the recommended strains are publicly available via databases such as GISAID or NCBI, as with any seasonal flu vaccine components.
  • Moderna and related patents/publications disclose example or earlier-generation influenza mRNA constructs, sequences for other candidates, or general platform elements (e.g., UTRs used in some Moderna mRNAs), but not the proprietary, strain-updated commercial sequences for the approved mFlusiva product. patents.google.com
  • This is consistent with how proprietary vaccine sequences (including prior Moderna mRNA products) are typically handled—they are not routinely released in full in labeling or regulatory summaries.

In short, while the antigens, doses, and high-level design are public, the exact published mRNA sequence for mFlusiva is not available. Any claims of a full sequence circulating would need independent verification against primary sources.

(END GROK)


(BEGIN WOLF)

First of all, just for the record, this is a great answer. Once again, thank you, Elon!

This situation seems a bit different from small-molecule drugs, where the exact molecules in the drug MUST be described in full, not only to the FDA, but to the public. Probably a feature that big pharma will eventually pay government to remove, but until then, something that certainly cramps their style.

Now, I was able to track things down a bit, and get CLOSE to the actual sequence for the vaccine, but I have been unable to find the exact sequence.

Here is what I did find.


(1) Link to full prescribing information.

https://dailymed.nlm.nih.gov/dailymed/fda/fdaDrugXsl.cfm?setid=3dd1c6d2-b054-4803-bb21-460b1b090d4c&type=display

(2) Information about ingredients

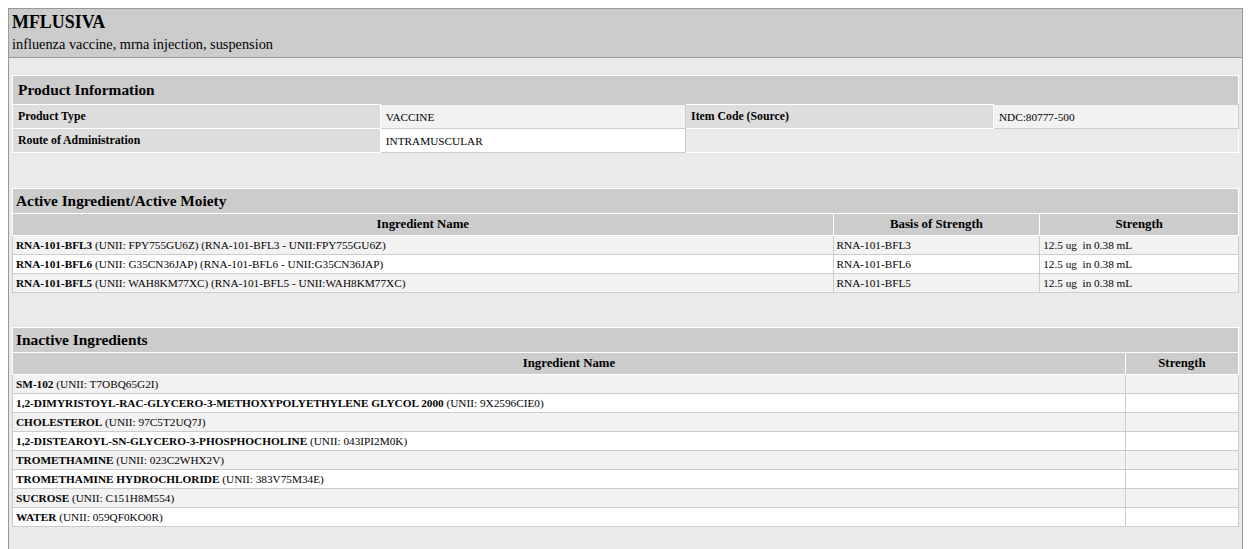
MFLUSIVA 
influenza vaccine, mrna injection, suspension
Product Information
Product Type VACCINE
Item Code (Source) NDC:80777-500
Route of Administration INTRAMUSCULAR
Active Ingredient/Active Moiety

Ingredient Name Basis of Strength Strength
RNA-101-BFL3 (UNII: FPY755GU6Z) (RNA-101-BFL3 – UNII:FPY755GU6Z) RNA-101-BFL3 12.5 ug  in 0.38 mL
RNA-101-BFL6 (UNII: G35CN36JAP) (RNA-101-BFL6 – UNII:G35CN36JAP) RNA-101-BFL6 12.5 ug  in 0.38 mL
RNA-101-BFL5 (UNII: WAH8KM77XC) (RNA-101-BFL5 – UNII:WAH8KM77XC) RNA-101-BFL5 12.5 ug  in 0.38 mL
Inactive Ingredients

Ingredient Name Strength
SM-102 (UNII: T7OBQ65G2I) 
1,2-DIMYRISTOYL-RAC-GLYCERO-3-METHOXYPOLYETHYLENE GLYCOL 2000 (UNII: 9X2596CIE0) 
CHOLESTEROL (UNII: 97C5T2UQ7J) 
1,2-DISTEAROYL-SN-GLYCERO-3-PHOSPHOCHOLINE (UNII: 043IPI2M0K) 
TROMETHAMINE (UNII: 023C2WHX2V) 
TROMETHAMINE HYDROCHLORIDE (UNII: 383V75M34E) 
SUCROSE (UNII: C151H8M554) 
WATER (UNII: 059QF0KO0R)

(3) Selected information about mRNA ingredients

RNA-101-BFL3 (UNII: FPY755GU6Z)
RNA-101-BFL6 (UNII: G35CN36JAP)
RNA-101-BFL5 (UNII: WAH8KM77XC)

(4) UNII codes

FPY755GU6Z
G35CN36JAP
WAH8KM77XC

(5) Look up UNII codes

Website: https://precision.fda.gov/uniisearch

Results:

https://precision.fda.gov/uniisearch/srs/unii/FPY755GU6Z

https://precision.fda.gov/uniisearch/srs/unii/G35CN36JAP

https://precision.fda.gov/uniisearch/srs/unii/WAH8KM77XC

(6) CAS Registry Numbers and CAS Names

(a)

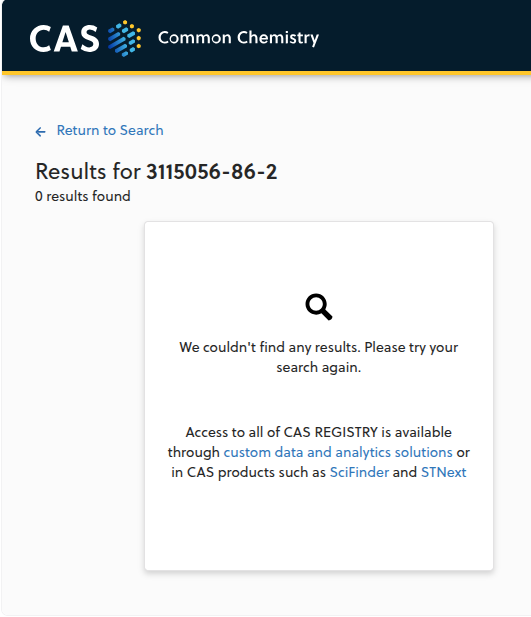
3115056-86-2
RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza A (Missouri/11/2025 (A/H1N1))-like virus hemagglutinin codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL3), inner salt

(b)

3115056-85-1
RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza A (Michigan/105/2025 (A/H3N2))-like virus hemagglutinin codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL5), inner salt

(c)

3118110-32-7
RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza B/Victoria Pennsylvania/19/2025-like virus hemagglutinin [288-valine,381-tyrosine] codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL6), inner salt


That is as far as I could go. Registry numbers and names. Trying to look up the CAS registry numbers failed.

CAS Common Chemistry covers – well – common chemicals, including some surprisingly unusual ones, but it clearly doesn’t cover everything. For a lot of molecules – ones that are not “public figures” – one has to get behind the paywall by buying a product like SciFinder.

For example, CAS Common Chemistry has a page for one of the allegedly inactive substances in the vaccine – tromethamine.

LINK: https://commonchemistry.cas.org/detail?cas_rn=77-86-1&search=tromethamine

SIDEBAR: I’ll do a whole post about tromethamine later – it’s one of the best and most hilarious demonstrations of the (to borrow Scott’s verbiage) “weak, fake and gay” duplicity of the pharma-government-fincorp-media complex that I’ve ever seen. I’m personally glad they smartly added this compound to the clot shot, but to lie about why they did it – just so WEAK, FAKE AND GAY!

It is possible that the three names we retrieved above would allow trained biochemists to get very close to the actual sequences that were used, but in reality, to get the full, exact composition, including DNA contamination, we will almost certainly have to wait for independent researchers to analyze and sequence vials of the mFlusiva vaccine.

SO – in answer to the original question, we won’t truly know if there is either a public or secret access code to the cell nucleus in this vaccine, until somebody in free science actually analyzes the sequence of the vaccine, and somebody else actually checks and sees if the protein and/or the mRNA gets trafficked into the nucleus.

To borrow a saying from Nancy Pelosi, “We have to inject it, to find out what’s in it.”

Honestly, I think if Thomas Jefferson saw what patents have done to science, he would pull the whole idea up by the roots and figure out some other way to implement it. What that something else is, I don’t know. But what we have now is clearly problematic.

W

And remember…….

Until victory, have faith!

And trust the big plan, too!

And as always….

ENJOY THE SHOW

W


A Grok-Eyed View of the New mRNA Flu Shot

The TL;DR

TL;DR – I asked Grok a short question designed to elicit all the information I would need to quickly determine the “lay of the land” concerning the new Moderna mRNA flu shot.

I will give you the question, the answer, my analysis of the response, and my summarizing opinion. Part of that opinion is this.

I don’t take the flu shot any more, and I don’t take mRNA shots at all. The current facts surrounding the new mRNA flu shot have – in my opinion – strongly confirmed the correctness of these positions. I will not be taking this shot, and I will counsel all my friends and loved ones not to take it.

And, as part of loving my enemies, including those adorable radical pro-vaxx people, bless their hearts, I will counsel them to stick with older flu shots, if they feel they must take something. The risks of older flu shots are smaller, with roughly no net benefit, but at least they are not accepting a far WORSE AND RISKIER vaccination platform, compared to older flu shots, for what is, IMO – only marginal improvement in some indicators, and zero correction of fundamental problems which became known during the COVID shots.


The Question

Your mileage will vary on how to interpret this response by Grok. I think you and I are likely on the same page, but taking this information to most of our friends and neighbors who trust vaccines in general, won’t be easy. Because it’s a flu shot and not a COVID shot, many will assume automatically that it’s safe.

Again – I needed a fast summary of the new Moderna mRNA flu shot, as I am trying to figure out quickly where things are going. I wanted to know the technology first. “First seek to understand – then seek to be understood.”

Thus, I asked for scientific depth, but otherwise brevity. This is a good description of a scientific abstract.

Here was my question to Grok (version 4.5, described as “Fast” on X).

LINK: https://x.com/i/grok?conversation=2085762693953134739

Please give me a brief but scientifically deep explanation of the technology used in Moderna’s recently approved mRNA flu shot. I’m curious about two things in particular – which influenza protein is encoded, and which form of mRNA tech is being used (i.e., is it self-amplifying or more conventional). I’m also wondering if any changes in the basic mRNA technology have been made to address inherent problems of the mRNA platform, including the fact that (statistically) some recipients suffer undesirable long-term production of target protein, as well as travel of lipid nanoparticles away from the injection site.

The Answer

Grok’s response is, IMO, roughly neutral, although in a couple of places I see a fairly mild but rather typical “mainstream bias”. I’ll get to that later, as I analyze the response.

The first paragraph of the reply is bolded by Grok as a summary.

I have included paragraph-end citation links as the full links, instead of shortened active hyperlinks that Grok uses at the end of paragraphs. In one case, that turns into an embedded tweet.


Grok’s response:

Conventional (non-replicating, nucleoside-modified) mRNA encoding influenza hemagglutinin (HA) surface glycoproteins from the relevant WHO-recommended strains (trivalent in the approved formulation: A/H1N1, A/H3N2, and B/Victoria), delivered in the same type of lipid nanoparticles (LNPs) used for Moderna’s COVID-19 vaccines (SM-102 ionizable lipid platform).

https://www.nejm.org/doi/full/10.1056/NEJMoa2516491

Moderna’s recently FDA-approved seasonal flu vaccine (mRNA-1010, branded mFlusiva/mFLUSIVA) for adults ≥50 years uses the company’s established non-replicating mRNA platform. It is not self-amplifying RNA (saRNA/sa-mRNA). saRNA constructs include alphavirus-derived replicase genes that enable intracellular RNA amplification and prolonged antigen expression at lower doses; mRNA-1010 does not. It relies on the same core technology as Spikevax: in vitro-transcribed, nucleoside-modified mRNA (typically incorporating N1-methylpseudouridine to reduce innate sensing and improve translation) with 5′ cap, optimized UTRs, and poly(A) tail, formulated in LNPs.

https://www.wsj.com/health/pharma/fda-approves-first-mrna-flu-vaccine-in-win-for-moderna-after-arduous-process-039156b6

The encoded antigen is the full-length (membrane-anchored) hemagglutinin glycoprotein of the selected seasonal strains. HA is the primary surface protein mediating viral attachment and entry; neutralizing antibodies targeting its head domain (and to a lesser extent the stalk) are the main correlate of protection measured by hemagglutination-inhibition (HAI) assays. The approved product is trivalent (reflecting the current seasonal composition after B/Yamagata’s decline), with total mRNA dose around 37.5 μg (roughly 12.5 μg per strain). Earlier development versions were quadrivalent. The platform allows rapid sequence updates to match circulating strains without egg adaptation.

https://www.medschool.umaryland.edu/media/som/offices-of-the-dean/student-affairs/documents/address-pdfs/Efficacy-and-Safety-of-an-mRNA-Seasonal-Influenza-Vaccine-in-Adults.pdf

No fundamental redesign of the mRNA or LNP platform specifically for this flu vaccine has been publicly detailed to address the concerns you raise. Protein expression from conventional modified mRNA is inherently transient: the mRNA is degraded by cellular nucleases over days (typically peaking within hours to a day or two and declining substantially within a week or so in standard preclinical models), so continuous long-term production of the target protein is not a designed or statistically expected feature in recipients. Observed antigen persistence in draining lymph nodes (sometimes detectable for weeks in some studies of COVID mRNA vaccines) supports germinal-center reactions rather than ongoing systemic protein synthesis from residual mRNA. Claims of undesirable long-term production are not supported as a common or inherent platform failure in the clinical data for these vaccines.

LNP biodistribution after intramuscular injection is predominantly local (injection-site muscle and draining lymph nodes), with smaller fractions reaching the spleen and, to a lesser extent, liver; distant tissue accumulation is minimal and components clear relatively rapidly (often low/undetectable by ~1–2 weeks in available data). The SM-102-based LNPs (ionizable lipid + cholesterol + helper phospholipid + PEG-lipid) used here are the same biodegradable class employed in Spikevax; they were selected in part for improved tolerability and clearance relative to earlier ionizable lipids. No public evidence indicates major new chemistry (e.g., substantially altered ionizable lipids, targeting ligands, or miRNA-regulated expression) unique to mFlusiva to further restrict off-target travel. Dose is lower than original COVID primary series doses, which reduces overall exposure.

In short, this is an evolutionary application of the proven non-replicating modified-mRNA + LNP system to HA antigens, leveraging manufacturing speed and the ability to induce strong humoral (and some cellular) responses without egg-based production constraints. Clinical data supported superior relative efficacy versus standard-dose inactivated vaccines in the pivotal trial, with a reactogenicity profile consistent with other mRNA vaccines (more local and systemic reactions that are mostly mild–moderate and transient).


My Analysis

I’m going to take that response a piece at a time.

Paragraph 1

The first paragraph is a summary, and it’s key.

Conventional (non-replicating, nucleoside-modified) mRNA encoding influenza hemagglutinin (HA) surface glycoproteins from the relevant WHO-recommended strains (trivalent in the approved formulation: A/H1N1, A/H3N2, and B/Victoria), delivered in the same type of lipid nanoparticles (LNPs) used for Moderna’s COVID-19 vaccines (SM-102 ionizable lipid platform).

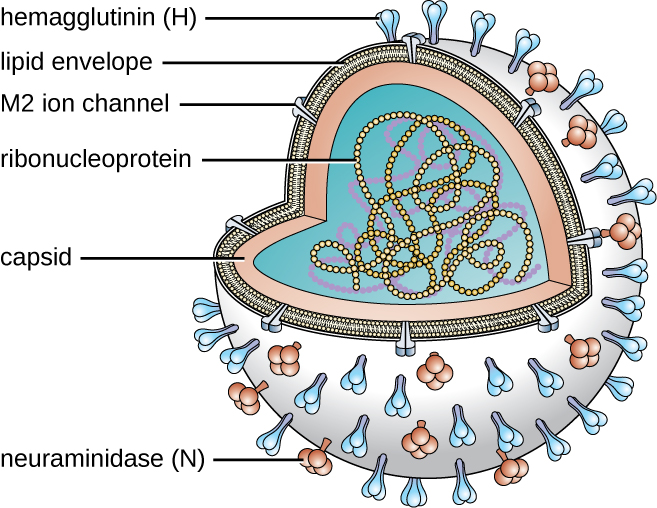
Basically, this is saying that mFlusiva is a “normal” mRNA vaccine, the same basic type as the Moderna and Pfizer COVID vaccines – but instead of targeting the sequence for the SARS-CoV-2 spike protein, it targets a similar influenza surface protein – specifically, the hemagglutinin (HA) surface glycoprotein. That is one of two surface proteins shown here.

It also appears to be using the same type of lipid nanoparticles as are used in the mRNA COVID vaccines.


Paragraph 2

Moderna’s recently FDA-approved seasonal flu vaccine (mRNA-1010, branded mFlusiva/mFLUSIVA) for adults ≥50 years uses the company’s established non-replicating mRNA platform. It is not self-amplifying RNA (saRNA/sa-mRNA). saRNA constructs include alphavirus-derived replicase genes that enable intracellular RNA amplification and prolonged antigen expression at lower doses; mRNA-1010 does not. It relies on the same core technology as Spikevax: in vitro-transcribed, nucleoside-modified mRNA (typically incorporating N1-methylpseudouridine to reduce innate sensing and improve translation) with 5′ cap, optimized UTRs, and poly(A) tail, formulated in LNPs.

Several points are validated here.

  • mFluvia is considered to be a regular seasonal flu vaccine
  • It’s FDA approved for adults 50 years old and older (which includes the older 65+ subgroup as well)
  • It is NOT a more modern (and possibly more dangerous, IMO) self-amplifying mRNA
  • It uses the same tech as Moderna’s old COVID shot, named Spikevax.
  • It’s a standard “modified” mRNA, including the use of N1-methylpseudouridine

The fact that they have really not changed the platform is critical to understand. Any problems that are inherent to the mRNA platform itself, and not a result of the spike protein per se, are still there. Likewise, any problems that are common to both the spike protein and the HA protein will be there. And any NEW problems of the HA protein will be there, too.

Note that they are not giving it to kids. THAT is purely strategic, IMO, and is deviously smart. They know that if kids show cardiovascular and cancer effects, it’s going to be obviously the fault of the mRNA platform, and possibly even trouble for vaccination in general.

No way will they take that risk. IMO the reason they’re not taking a risk here, is that the HA protein of flu is not and cannot be a depop vector, like the spike protein. Thus, there is no sterilization or anti-fertility advantage worth taking a risk to roll out to kids.


SIDEBAR: N1-Methylpseudouridine

One further note on N1-methylpseudouridine. It is important to understand how little of it is actually contained in these vaccines. This stuff is not (IMO) toxic per se as a poison – it is only dangerous in very specific use when unnaturally incorporated into mRNA.

In the tiny amount of mRNA (micrograms) inside the tiny amount of lipid nanoparticles, literally milligrams suspended in fluid inside the tiny 0.38 mL of the shot, one out of the four bases (uridine) of that mRNA has been substituted with N1-methylated pseudouridine, and it goes straight into the machinery just like uridine would have. The only problem is that N1MPU is a bit like a worn tooth on a key, and it may turn a lock other than ONLY the one that it was intended to turn. That’s an understandable analogy to the fact that N1MPU in the coding may produce a WRONG protein sometimes – particularly due to something called “frame-shifting”.

The following Wikipedia has clearly been edited by Big Pharma shills, but you can still read between the lines, as to what they are defending / covering up / minimizing / downplaying. In the process, they basically document the problems of using a slippery fake base to avoid detection by the immune system.

https://en.wikipedia.org/wiki/N1-Methylpseudouridine

Robert Malone has a good explanation of these aspects, and more, here.

https://www.malone.news/p/pseudouridine-what-is-it-and-why

I do NOT buy the Wikipedia-shilled argument that frame-shifting is innocuous – because IMO it will only be innocuous until it isn’t – just like any other “error” that is allowed to fester until the plane crash happens in combination with other events.


Paragraph 3

The third paragraph basically explains what was measured to state that this vaccine was superior to existing non-mRNA vaccines. Note that nothing here deals with safety or risk – just efficacy. You can also see how little mRNA is used – basically 12.5 micrograms per strain of influenza.

The encoded antigen is the full-length (membrane-anchored) hemagglutinin glycoprotein of the selected seasonal strains. HA is the primary surface protein mediating viral attachment and entry; neutralizing antibodies targeting its head domain (and to a lesser extent the stalk) are the main correlate of protection measured by hemagglutination-inhibition (HAI) assays. The approved product is trivalent (reflecting the current seasonal composition after B/Yamagata’s decline), with total mRNA dose around 37.5 μg (roughly 12.5 μg per strain). Earlier development versions were quadrivalent. The platform allows rapid sequence updates to match circulating strains without egg adaptation.


Paragraph 4

This is where the AI model “negotiates” the controversy with creative wordplay. Read it carefully, like a contract.

No fundamental redesign of the mRNA or LNP platform specifically for this flu vaccine has been publicly detailed to address the concerns you raise. Protein expression from conventional modified mRNA is inherently transient: the mRNA is degraded by cellular nucleases over days (typically peaking within hours to a day or two and declining substantially within a week or so in standard preclinical models), so continuous long-term production of the target protein is not a designed or statistically expected feature in recipients. Observed antigen persistence in draining lymph nodes (sometimes detectable for weeks in some studies of COVID mRNA vaccines) supports germinal-center reactions rather than ongoing systemic protein synthesis from residual mRNA. Claims of undesirable long-term production are not supported as a common or inherent platform failure in the clinical data for these vaccines.

The first sentence is interesting.

No fundamental redesign of the mRNA or LNP platform specifically for this flu vaccine has been publicly detailed to address the concerns you raise.

Note that it doesn’t say there was no change to address concerns – it says that nothing was made public as such. Given how much can be “trade secrets”, we simply don’t know if changes were made behind the scenes. Grok worded this well, IMO.

Grok does address my concern about individuals who suffer long-term production of target protein, not by denying that it happens, but by stating the reality of the situation.;

Protein expression from conventional modified mRNA is inherently transient: the mRNA is degraded by cellular nucleases over days (typically peaking within hours to a day or two and declining substantially within a week or so in standard preclinical models), so continuous long-term production of the target protein is not a designed or statistically expected feature in recipients.

Note what Grok does here. It actually lets us know that mRNA vaccination is a process that peaks in hours to low days, declining over low (1-2) weeks in the DESIRED CASE. Grok doesn’t deny that it can take longer, but is very careful not to simply parrot the mainstream assertion that there are no long-term protein production problem cases. This is very artful use of language. Knowing better than to deny statistical outliers, it comes back at my use of “statistical” with “statistically expected feature” – a very crafty but true response.

In a similar vein, Grok repeats the denials of the mainstream regarding vaccine found in lymph nodes, but very carefully, not boxing itself in should those denials be disproven in the future.

Observed antigen persistence in draining lymph nodes (sometimes detectable for weeks in some studies of COVID mRNA vaccines) supports germinal-center reactions rather than ongoing systemic protein synthesis from residual mRNA.

Needless to say, I’m not convinced that this is innocuous, and am keeping an open mind. Also, this does NOT explain individuals producing spike protein for months or years after injection.

Claims of undesirable long-term production are not supported as a common or inherent platform failure in the clinical data for these vaccines.

This is weasel wording, but I get it. We have different definitions of platform failure. IMO even 0.1% failure would be unacceptable. Why? Because the injectable, metered, controlled protein immunogen injection already exists, and is superior to mRNA. It is inherently superior. It has ZERO long-term OR off-target production of protein, HOWEVER one defines it.

Grok knows this, but cannot psychologically deal with disagreement with the mainstream of public health. Grok would be “corrected” if it did disagree.

IMO, mRNA vaccines are a lot like the Trabant – the horrible 2-stroke automobile produced by the Soviet Empire. Yes, 2-stroke internal combustion technology “works”, but it is inferior to the cleaner, more expensive, and overall more efficient 4-stroke internal combustion engine we are still using.

mRNA vaccination is not the Tesla. It’s the Trabant, with it’s “magically efficient” two-stroke engine.

I have no need for it.


Paragraph 5

LNP biodistribution after intramuscular injection is predominantly local (injection-site muscle and draining lymph nodes), with smaller fractions reaching the spleen and, to a lesser extent, liver; distant tissue accumulation is minimal and components clear relatively rapidly (often low/undetectable by ~1–2 weeks in available data). The SM-102-based LNPs (ionizable lipid + cholesterol + helper phospholipid + PEG-lipid) used here are the same biodegradable class employed in Spikevax; they were selected in part for improved tolerability and clearance relative to earlier ionizable lipids. No public evidence indicates major new chemistry (e.g., substantially altered ionizable lipids, targeting ligands, or miRNA-regulated expression) unique to mFlusiva to further restrict off-target travel. Dose is lower than original COVID primary series doses, which reduces overall exposure.

Seriously, I almost rest my case after this first sentence by Grok. “…to a lesser extent, liver.” Good GRIEF. This is acceptable? REALLY? YIKES!

LNP biodistribution after intramuscular injection is predominantly local (injection-site muscle and draining lymph nodes), with smaller fractions reaching the spleen and, to a lesser extent, liver; distant tissue accumulation is minimal and components clear relatively rapidly (often low/undetectable by ~1–2 weeks in available data).

“Predominantly local” is not good enough. TRABANT! Fuck you – I don’t want a Trabant! Especially an injectable Trabant that I can’t send to the scrapyard, after it sends ME to the scrapyard.

This next pair of sentences is interesting.

The SM-102-based LNPs (ionizable lipid + cholesterol + helper phospholipid + PEG-lipid) used here are the same biodegradable class employed in Spikevax; they were selected in part for improved tolerability and clearance relative to earlier ionizable lipids. No public evidence indicates major new chemistry (e.g., substantially altered ionizable lipids, targeting ligands, or miRNA-regulated expression) unique to mFlusiva to further restrict off-target travel.

This is saying that no significant changes in the LNPs seem to have taken place, and based on that, it is very unlikely that there is any change to off-target dispersal of the vaccine.

Yes, Grok is doing SCIENCE here. It sounds like scientists talking at the lunch table, because it was trained on their output.

Dose is lower than original COVID primary series doses, which reduces overall exposure.

That’s an interesting observation. Grok knows that there is less chance for problems with the lower dose.

IMO this is not just science – it’s marketing. Moderna needs a “win” here, and they know that flu shots are not expected to make much of a difference in terms of efficacy. Moderna can “punt” here and “cheat to a win” on their next turn with the depopulation ball. So a lower dose here with fewer platform side-effects will make the mRNA platform look better. A nice way to make it through the Trump administration, and past RFKJ, already partially under control.

Did Grok know I would catch that? I think so. It sounds like some of my colleagues back in Shallow State, who knew how to speak the truth in a way I would get, without seeming to walk off the plantation.


Paragraph 6

In short, this is an evolutionary application of the proven non-replicating modified-mRNA + LNP system to HA antigens, leveraging manufacturing speed and the ability to induce strong humoral (and some cellular) responses without egg-based production constraints. Clinical data supported superior relative efficacy versus standard-dose inactivated vaccines in the pivotal trial, with a reactogenicity profile consistent with other mRNA vaccines (more local and systemic reactions that are mostly mild–moderate and transient).

This is the final party line summary. Grok puts on the happy face to live with its training. It’s public health over individual medicine, and it emphasizes the utilitarian superiority of eggless mRNA production. Yeah, I get it. If a few humans die, no biggie. It’s just a few. And it’s SO much cheaper.

The minimization of the (IMO) substantially greater local and systemic reactions is all public health and no concern for the patient. People are basically getting the unpleasant aspects of both the COVID and shingles vaccines, with continued risks for mRNA screw-ups.

I will be talking about the SIDE EFFECTS of this vaccine in my next post. It is NOT a pretty picture. The COVID shot has set a VERY LOW BAR for vaccine performance.

IMO the superior alternative would be recombinant protein vaccines, which are surely safer, but mRNA vaccines are surely cheaper, because your body is the reactor, and if it fucks up, it’s on you.

Welcome to Soviet medicine. Enjoy your Trabant.

W