KMAG DAILY THREAD 20260820 KETO, Exercise & Clogged Arteries

Site rules stolen from our good friend PAVACA

There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s post for any AI-generated content. To the best of her knowledge and belief, there is none. If readers wish to post any AI-generated content in the discussion thread for today’s post, they must cite their source. Thank you.


Do not forget to LABEL AI articles video and such.


I Avoided a Heart Attack by Cleaning 20 Years of Clogged Arteries — Dr Ford Brewer MD MPH. (35 minutes)

This is another look at health and in someways compliments yesterday’s article. In both cases both doctors promote a Keto diet and avoiding sugar/starches/carbs. Dr Ford Brewer is more of an establishment physician having worked for years at Johns Hopkins “training the other doctors there in prevention.“

My 7- Step Heart Attack Prevention Protocol free ebook HERE.


TRANSCRIPT

Let me tell you a story. It’s about what happened to me. At age 57, this is 11 years ago. I found out I had the arteries of a 73 yr old 16 years older than me. I had no idea. I thought I was like this close to the kind of heart attack [finger & thumb almost touching – GC] You know, [with] heart attacks, 50% of them have no symptoms until boom, you’re dead. And it’s like that really upset me because, I thought I was the picture of health. I ran marathons. I avoided eating fats, which again, both of these things we thought at the time to be the best practices for heart health. And still, that test said I was walking around with a ticking time bomb in my chest. But here’s the thing. I didn’t quit. I fought back. After a year, I turned those arteries into the arteries of a 52 year-old.

Now, look at this. [Shows a CIMT non-invasive ultrasound machine -GC] This is the most advanced heart scan in the world at this point in time and it shows my dangerous plaque is basically gone. [Shows his results for right Coronary Artery – GC] That means my risk for a sudden heart attack right now is practically zero. If you’ve ever been told it’s too late or that you just have to live waiting for a heart attack, that’s not true. This video will prove otherwise. I’ll show you exactly how I reversed decades of arterial plaque, avoided a heart attack, and how you can do that, too, including one element that most people miss.

The first test that woke me up, it was called a CIMT. That’s short for Carotid Intima-Media Thickness Test

The carotid is the artery right here. Now, I know that’s a mouthful and it sounds uber technical. It’s actually pretty simple. It’s a quick ultrasound. There’s no radiation and it’s the arteries in the neck that I just pointed to. You can feel that pulse. But it doesn’t just look at how well blood is flowing. It measures how much plaque is hiding inside the artery wall. And if you’re saying, well, you know, that’s your neck, not your chest. We’ll get to that a little bit later. But the short version is 98% of the time, if you have plaque here, you’re going to have it here. And vice versa. If you don’t have plaque here, you’re not going to have it here or anywhere else.

Plaque isn’t really a plumbing problem that only happens in the heart. It’s a metabolic problem. So that’s why if you’ve got plaque in one place, you’ve got it in the others. Metabolic meaning how your body burns fuels. By the way, if you want to take a deep dive into metabolic health, you need to get my e-book HERE. It’s free.

Now, when that CIMT result came back at 1.2 millimeters. I knew I was in trouble. I was frustrated, like I said, and I was pretty emotional. For context, one millimeter or less is ideal. Over that and you’re in a little bit of a danger zone. But the worst part is based on the amount of plaque detected in my arteries, my arterial age came back at 73 years old, 16 years older than what I actually was. For a couple of weeks, I was frustrated and angry, but mostly just frustrated. Then I thought, maybe I wasn’t doing everything wrong. Despite some of the shortcomings of my lifestyle, and I needed to change some things, but I was still doing better than a lot of folks. It wasn’t like, I had done nothing, I could have weighed 300 lb plus. I could have had a whole bunch of body fat that was creating this problem. At least I had some things going for me.

The other thing that occurred to me is yes, had I not done those lifestyle activities, I could have already had a heart attack. I could already be dead. So, I began to see the other side of this. Once I got past that shock, I knew I had things to do, though. The first thing I did was look for the cause. I ran an oral glucose tolerance test where you drink a a set amount of glucose, either 75 or 100 grams, depending on the the context of the test that you’re doing or the format. You want to see how your blood sugar responds over time. Mine spiked to over 160.

Already it was clear, you get spikes over 160. And those are the times when you can be forming plaque. It meant I had enough pre-diabetes to cause plaque, even though I’d never been told I was diabetic. That was the turning point.

I switched from a low-fat diet to a low carb diet. And I didn’t just lower my carbs. I removed the ones that spiked my blood sugar.

So, for example, fiber-based carbs are carbs, but they don’t mess with my blood sugar. [He shows a photo of bowls of white rice, oats? Chickpeas? And?? — GC] The glycemic carbs are the pastas, the breads, those highly processed carbs are the ones that raise my blood sugar. Grain products, one of the biggest offenders. And I loved bread. I didn’t eat a lot of pasta, but I ate bread all the time. You know, let’s break bread together. I thought that was a great thing. I changed my workouts too from long distance cardio and I still continued to do some of that but I added a lot more short intense bursts and more focused resistance training. So what I was doing with the intense workouts wasworking on my capillaries. That’s where my insulin receptors live.And with the resistance train I was working on my mitochondria in my muscles. That’s what burns the glucose once you get it into your muscles. And speaking of muscles, the reason I focus on my legs is that’s where your real muscle mass is.

I improved my sleep. It was a long saga of many things that I did to improve that sleep. I lowered my stress. And yes, I made a few unpopular choices with supplements and even medications. Within a year, my CIMT showed my arterial age had dropped from 73 to 52, 20 years younger. But that was just the beginning.

Over the years, I kept getting a CIMT basically every year. They keep showing very slow progression of my plaque. But I kept seeing some comments in the channel specifically asking CIMT is okay, but what about your calcium score? We want to see how your heart is. So, I thought I might as well just get a calcium score. Now, here’s the thing. Calcium score won’t show soft plaque, the dangerous type of plaque that can rupture and cause a heart attack. That’s why I went to get CIMT because a CIMT does show the presence of soft plaque which I didn’t have based on my [current] results.

So I decided to do something better than a calcium score. I went straight to the coronary CT Angiogram but not just any traditional angiogram. I got the newest type of CT angiogram [Cleerly Ct-angiogram] and that it’s the one that uses AI analysis. This is the best available test to identify both soft unstable and hard calcified plaque in the arteries of the heart. I got mine done with a company called Cleerly, but we work with other companies, too.

There’s another one called HeartFlow® as well. Enough talk about the process. You want to see my results? So, when I opened the report, three headlines jumped off the page. First, soft plaque volume.1 millimeter. That was a relief. In practical terms, that means I have virtually no unstable plaque in my heart right now. Second total plaque volume 75.6 cubic mm with stable calcified portion at 31. The rest is higher density non-calcified plaque. It behaves [as if] it’s stable when you manage your metabolism. That may be getting a little bit too technical. Here’s the translation. Very little total plaque and almost none of the dangerous kind. So those are the two key things to remember.

I said three things and there’s always this third thing that the rest of the medical world always wants to focus on and that is stenosis and location of the plaque. Stenosis is a geeky word for whether or not you’ve got obstruction. Most arteries were under 10% obstruction. And the highest narrowing was 17%. And that was in guess which one? The L. That’s the one they called the widowmaker. Ba bum. Everybody’s always so scared when they hear that term.
They come to me and they say, “The doctor said I had calcification and plaque in my widowmaker.” And I’m going, “I understand. If you have plaque in the heart arteries, the first place you’re almost always the first place you’re going to get it is the L.” So, don’t get concerned if somebody tells you you have plaque and it’s in the widowmaker, the L. [ left anterior descending (LAD) artery.Dangers of a Widowmaker Heart Attack – GC] Now, if there’s another specific measurement here, it’s called percent atheroma volume. [Coronary Atheroma Burden Is the Main Determinant of Patient Outcome –GC]

And let’s take a look at that. It measures basically how much plaque you have in terms of volume. Mine was 2.5%. In plain English, the plumbing is just wide open. And more importantly, the plaque that matters for sudden events, the soft inflamed stuff is essentially absent. Put together that means my risk for a sudden heart attack is dramatically lower. And it confirms the progress that we saw on the CIMT, not just in the neck, but in the heart as well.

The major problem related to metabolic disease, it causes plaque and inflammation.

After years of doing prevention and treating patients, I’ve come to realize that testing for this can be very difficult. Now, there are some lab tests, OGTT, oral glucose tolerance tests, and insulin response, the amount of insulin required to m for by your body to manage glucose. [Glucose Tolerance Test (GTT): What It Is — GC]

It’s a hard test to do. It’s definitive. It’s old school, but it’s hard because it requires a lot of time and effort and still sometimes the lab goofs it up.

….

I would not call the test hard, I would call it tedious and time consuming. Unfortunately I found doctors do NOT want to do it on young people. When I tried to get the test done in the early 1970s, I was told I was too young, to have the problem. Yet it is when you are young where finding you have Hypoglycemia is most important for intervention. Note that even now it is considered rare. Of course if you refuse to test for it in the young, and they constantly eat sugar, it will turn into type 2 diabetes as the pancreas becomes exhausted.

Type 2 diabetes – Symptoms and causes – Mayo Clinic

…the increase in the number of children with obesity has led to more young people with type 2 diabetes…

And what often causes that obesity?

Reactive hypoglycemia: the immediate biological trigger

Reactive hypoglycemia means your blood glucose falls quickly after a meal, often within one to four hours. This can happen after a refined carbohydrate heavy meal because insulin surges to clear the sugar. The result is a rapid drop that the brain interprets as an urgent need for quick fuel. Common symptoms include sweating, tremor, anxiety, and an intense urge for fast carbohydrates. Reactive hypoglycemia is an answer to the question “what illness causes sugar cravings?” for many people with post meal cravings. For more clinical context on post-meal low blood sugar and related eating patterns see the research summary here: reactive hypoglycemia and eating behavior.

OK, I will get off my hobby horse, and get back to the transcript.

…

Now, if you’re thinking, Ford, congratulations on reversing your plaque. That’s good for you. What I really want to know, though, is how do I do it? I understand. So, let me show you exactly what I changed to get here, step by step, so you can start bringing your own numbers down. The first and most important change was diet.

BLOOD SUGAR SPIKES

I stopped thinking of food as low-fat or low calorie and I started thinking of it in terms of blood sugar impact. I began testing my blood sugar after meals and if it pushed me over 140, it didn’t stay on the menu, no matter how healthy the label claimed it was. So, one of the first big surprises for me was no more oatmeal for breakfast. That jacked my blood sugar. It meant cutting breads mostly. As I said, I didn’t eat a lot of pastas before, but I ate a lot of breads. Rice, I had developed a taste for rice. And as I mentioned, oatmeal. Couldn’t believe it.

But that’s what the blood sugars, that’s what they told me. So instead, I built my meals around foods that kept my blood sugar stable. I replaced those carbs with healthy fats, moderate protein, and plenty of vegetables that didn’t cause a spike. Over time, I experimented with different eating styles. I’ve tried versions of carnivore, keto, paleo, and plant heavy, low carb. No matter the variation, the common theme was always the same. Keep the carbs low and avoid the processed junk, and avoid blood sugar spikes.

For healthy fats, I leaned on things like avocado, extra-virgin olive oil, and fatty fish like salmon and mackerel. I didn’t shy away from natural saturated fats, either. real butter, not margarine, and yes, even bacon. I went back to bacon, which I had not eaten in decades because it was high-fat, butter, too. So, I went back to butter and bacon, and that was nice. A breakfast of eggs fried in butter with avocado on the side. That kept me satisfied for hours, and it didn’t send my glucose up.

I also paid attention to fiber. Now, some people have a problem with fiber. I don’t. Even in a lower carb approach, non-starchy vegetables, and some fermented foods, these gave me the fiber my gut needed. A big salad with olive oil, apple cider vinegar, and salmon was often lunch and dinner sometimes, too. I love Caesar salads, and so when I went out to eat, and I did a lot because I was traveling a lot, a salmon Caesar salad was my go-to dinner.

Others might be grilled chicken with sauteed greens. Sometimes I’d have a fatty cut of beef, but not very often because I tended to gain weight on beef. I developed a a taste for Brussels sprouts, which I had always hated. But you know what? You got to do what’s what you got to do. I even learned to eat kippers, kippered herring. I still cannot learn to eat sardines. I tried it a few times. I just gave up.

Now, here’s something that might surprise people. Once a week about, I’ll have a little bit of ice cream. Usually not the kind loaded with sugar and corn syrup, but usually one sweetened with alulose, stevia, or arythril. It tastes like a treat and it really doesn’t wreck my blood sugar or undo my progress. So that’s important because if your diet feels like punishment, you won’t stick with it. You just have to learn and change the way you eat. When you say, “I’m on a diet,” that implies temporary that’s in your head. I’m going to change back at some point. That’s not what you want. You want a way of eating that you can live with permanently. The point was to eat in a way that kept my blood sugar in the safe zone and made plaque reversal possible while still enjoying my food.

But what if I had a spike? What happens then? Well, for starters, I don’t panic. Just going out for a walk or doing some exercise snack like lunges or calf raises or jumping on the Schwinn Airdyne. You know that 30-year-old Airdyne that I kept around the house, mom kept around her house. And it was great. it will bring bring my blood sugar back down very quickly. That’s because it’s not the spike that drives the problem. It’s how long and how often your glucose stays even over 140. So, if you think about it, some foods might spike your blood sugar 200 or more. And if it’s only a few minutes, that appears to be okay. It’s really time under the curve, the blood sugar curve over 140. So, I’d much rather have a quick spike of 200 and back down to 100 than go up to 160 and just stay there hour after hour after hour.

EXERCISE

Now, all this leads me to the second big change, and that was exercise. I used to think the key to heart health was endless cardio, long runs, marathons, long bike rides, hours and hours of that level two steady state work. I ran half marathons weekly, sometimes twice a week… Here’s the truth I learned. Long-distance cardio isn’t bad. It’s not the most efficient way though to protect your arteries or reverse plaque. What really matters is improving your metabolic health. And the fastest way to do that is by building and using muscles, especially in your legs. Your leg muscles are your largest safety valve against insulin resistance and metabolic disease. When you engage those big muscles, you pull sugar out of your bloodstream and into your muscle cells where it’s safe. You’re lowering your blood sugar and insulin levels quickly.

….

[I notice that when I am doing a gig, I can get away with drinking a sugary soda in the middle of the gig without feeling that sugar crash I do when sitting at a desk. . –GC]

….

So, I shifted my training. Instead of logging 10 or 15 miles at a time, I started doing short intense bursts, high-intensity interval training, HIT, and a newer variation of this called REHIT, reduced exertion, high-intensity training. With HIT, I’d go all out for 40 to 60 seconds or not all out, but more like 90%. Recover for a minute or two, and then repeat. REHIT is kinder and gentler. You do go all out, but you only go out for like 20 seconds maximum. You do your maximum intensity, but only for 20 seconds, and then you back up.

You do a recovery very slow for 40 to 60 seconds. You do even just two high-intensity intervals in REHIT. And it’s shown to have some really good impact on your health, your arterial health, and your body. And guess what? The reason it’s called reduced exertion, [is] even though you’re going to high intensity, highest level, it’s only for 20 seconds. It’s only twice and you can do it in the morning and you don’t feel burned out the rest of the day. You don’t feel washed out. I could do it on a stationary bike, that Schwinn Airdyne I talked about. I could do it running hill sprints and I do all of those. I even added a rebounder that a friend gave me. You know those trampolines? I thought those were kind of wimpy looking until he gave me that one. And it’s like, oh my gosh, when you hit a flat out sprint on that thing, it will wear you out.

It’s great for calves, hips, and quads. So, I paired that with resistance training. And I’m not talking about hours in the gym. Most days, I did resistance snacks. 5 minutes in the morning, 5 minutes in the evening, even two or three minutes three or four times in the day. Wall squats, prolonged lunges, pull-ups, step squats, one-legged step squats, calf raises, use dumbbells, barbells, body weight moves. Once a week I’ll go to the gym for a longer session, harder workout, and use all those machines. Also once a week I’ll do a longer hit. So, I do three to five REHIT sessions per week and then one session of full hit.

I completely cut out those punishing long distance runs. Well, not completely. There were a few years where I never ran even as far as 5 miles at the time. I’m back to doing a couple of five mile runs. I’ll usually try to get in one once a week. My workouts overall became shorter, more intense, and more targeted. And the results in my labs and the scans speak for themselves.

The key is you don’t have to start at my level. Remember that. I do some fairly intense stuff. And I’ve put some videos out there. A lot of people come to see me and they say, “I’m not starting at that level.” A lot of people are beyond my level, you know, doing some very heavy resistance work.

You start where you are. That’s where you start. Even if you’re just walking right now, start there. Walk daily. Add short bursts of speed. Try getting a 10 or 20 pound weight vest or a 10 or 20 pound weight belt. Start adding some resistance. Start adding some things to what you’re doing. Work toward building muscle and incorporating high-intensity work in small, manageable doses. Over time, you’ll notice not only is your fitness improving, but your blood sugar, your energy, and your risk profile are all changing for the better.

SLEEP

Now, there was another big change that I made in my recovery, and that meant getting serious about sleep and stress management. For years, I treated sleep as optional. .. You’re not conscious. It’s sort of like wasted time, right? I’d stay up late, I’d work, I’d get up early and go run. And I told myself, I was just one of those people who could get by on five or six hours of sleep. Sometimes I’d wake up at 3 in the morning and couldn’t go back to sleep. Now, the truth is, poor sleep is a stressor. It raises your cortisol. It spikes your blood sugar and drives inflammation. They’ll do sleep studies on people and people may say, “Oh, I slept just fine.” But you see some things on the sleep study that said, “It wasn’t perfect.” For the next 48 hours, these people will have increased insulin resistance. So, good sleep is far more important than you might think, and certainly more important than I treated it.

Cortisol. If you don’t get enough good sleep, you’re starting to push your cortisol and that spikes your blood sugar, drives inflammation, all of which feed plaque growth. One problem that I discovered was that I had mild sleep apnea. My high narrow dental arch, crowded my teeth, and more importantly, it pushed my tongue back into my airway while I slept. So, if I was sleeping on my back, my tongue, as I got older, my tongue just started going back there more often. It would wake me up and I wouldn’t even notice it. That meant I was waking up dozens of time in a night without even realizing it. I addressed that with braces, Invisalign braces. They widened my arches and it really helped. But it wasn’t the only thing. I had to train myself to sleep on my side instead of on my back. That was challenging. But that one change improved my oxygen levels, lowered my blood pressure, and left me feeling more rested.

Stress was the other piece. I’d been going full throttle for decades. To me, a high level of stress was a natural thing. I had tried things like meditating and slowing my breath,

and they didn’t really seem to help. So, I just said heck with it. Now, chronic stress keeps you in fight or flight and keeps your body in a low-grade inflammatory state. It keeps that cortisol growing. I needed a way to break that cycle every day. And that’s when I started practicing slow, controlled breathing. Not just taking a deep breath, but actually slowing my breathing rate down to half of normal. You know, the normal 15 to 20 breaths. We’re not talking about going to 12 breaths per minute. We’re talking about going to 7 to 10 perspective.

From a geek perspective, this kind of breathing increases carbon dioxide slightly. That opens up blood vessels in your brain and body and it stimulates your vagus nerve, the switch that turns on your rest and repair mode. Rest and digest, rest and repair.

….

Well that seems to be a partial answer to Valerie Curren’s question about the Buteyko Breathing Technique from Sunday. — GC

….

Here’s where I learned that really slow breathing rate. A group called RESPeRATE

  sent me one of their devices to try. You put a strap around your belly and you have some earplugs in and it coaches you on how quickly you should inhale and how slowly you should exhale and how often to repeat. And that’s when I thought, “Oh my gosh, no wonder my slowed breathing in the past really never helped. I wasn’t slowing it down enough.” You can do this without any kind of BOF feedback gadget like RESPeRATE . Just sit or lie down. Inhale slowly for 4 or 5 seconds. Exhale slowly for 6 to 8 seconds and repeat just doing that same thing for 10 minutes. You’ll feel a big difference just with that alone.

Sleep and stress control don’t just make you feel calmer. They have a measurable impact on your metabolic health. Better sleep lowers your fasting glucose and your blood pressure. Lower stress reduces inflammation markers. These two things alone can take a huge amount of cardiovascular risk right off the table. That’s basically the lifestyle change I did. I know it might sound very simple, but for some people it can be hard to start or even maintain that kind of lifestyle.

Consistency is key here, but as we age, our body doesn’t have the same capacity to respond as quickly as when we were young. And that’s why I want to talk about supplements. I was trained in the traditional way and the folks that I trained with, we all felt like supplements just meant expensive urine. We underestimated the effectiveness. . But after my reality check, I decided to use my prevention experience to do my own research. I did a lot of science work at Hopkins and understood how to analyze science very well. When I started looking at the supplement research, I was surprised.

I started developing opinions about the best types of supplements for prevention. So to me, supplements should fill gaps in your diet that you can’t cover with diet, support your specific needs, and be backed by evidence.

D3 & K2

One of the first supplements I added was vitamin D3. Around 5,000 international units per day. Low vitamin D levels are linked to increased inflammation, higher cardiovascular risk, and poorer immune function. But I didn’t take D3 alone. I took vitamin K2 as well, about 400 micrograms daily because K2 helps direct calcium into bones and teeth, not into artery walls where it can contribute to calcification. But more importantly, it has some role in improving insulin resistance. I predict that’s going to be shown as the research continues. There’s already a couple of studies out there indicating that.

NIACIN

Another supplement that I used to take is niacin, mostly due to low HDL. Niacin is actually the only thing supplement or medication wise that can increase HDL, decrease LDL, decrease triglycerides, and most importantly decrease LP little A.

….

Niacin – Mayo Clinic

Prescription niacin raises high-density lipoprotein (HDL) cholesterol. This is the “good” cholesterol that helps remove low-density lipoprotein (LDL), the “bad” cholesterol, from the blood. Even though niacin may raise HDL cholesterol, research suggests that niacin therapy isn’t linked to lower rates of death, heart attack, or stroke. [Of Course not /sarc-GC]

….

I also take magnesium and not just one form of magnesium. I take Magnesium L-threonate which is great for brain health LINK and for sleep while magnesium glycinate supports muscle function and relaxation. [Helps you sleep -GC] Magnesium is involved in over 300 processes in the body and it plays a role in blood pressure and insulin sensitivity both critical for keeping plaque stable or preventing plaque entirely.

OMEGA-3 FATTY ACIDS


KRILL

Now although I eat a lot of fish I do supplement with some additional omega-3 fatty acids. The combination of EPA and DHA, two of the most important omega-3 fatty acids, that combination has proven time and time again to provide significant benefits to lower cardiovascular risk.

…


Omega-3 Fish Oil and Krill Oil Differences

Omega-3 fatty acids are well known for supporting heart health and inflammatory balance, but not all omega-3 sources are the same. Fish oil and krill oil both contain EPA and DHA, yet they differ significantly in concentration, research support, sustainability, and cost. In this article, we explain how omega-3s work in the body, compare fish oil and krill oil side by side, and review why fish oil remains the most efficient (and researched) option for most people…

Fish Oil vs. Krill Oil: Not All Omega-3 Sources are the Same

While both fish and krill oil contain omega-3 fatty acids, specifically DHA (docosahexaenoic acid) and EPA (eicosapentaenoic acid), there are important differences between the two, especially in concentration, absorption, and research support…

Fish oil typically contains higher levels of EPA and DHA than krill oil.… [AND possibly mercury -GC]


Krill Oil vs. Fish Oil: The Best Way to Get Your Omega-3s

…While there’s nothing wrong with fish oil, a growing body of research suggests there’s a smarter source: Krill oil.

Here’s what you need to know about krill oil and what the science shows about its health-enhancing potential…

Though both fish oil and krill oil contain EPA and DHA, the molecular structure of their fatty acids is different in a way that matters. In krill, the omega-3s are in the form of phospholipids, molecules of glycerol, two fatty acids, and the mineral phosphorus. In fish oil, the omega-3s are triglycerides, compounds of glycerol, and three fatty acids.

That slight difference in molecular makeup gives krill oil the advantage in terms of omega-3 bioavailability: The phospholipid form of omega-3 fatty acids in krill was shown to help facilitate the incorporation of omega-3s into tissues faster and more effectively than the triglyceride form in fish. In other words, the omega-3s in krill are easier for the body to absorb, suggesting you can take about 37% less krill oil than fish oil to get the same benefit.

2. Krill Oil Phospholipids Offer Critical Benefits That Fish Oil Cannot.

Humans need sufficient levels of phospholipids to ensure optimal cell function, cell growth, and the generation of new cells. In fact, phospholipids have been shown to help boost brain health and have protective effects against heart disease and liver disease, poor immune function, stress, depression, and more.

But as we age, our cells’ phospholipid levels naturally decrease…

3.  Krill Oil Has Brain-Boosting Choline; Fish Oil Does Not….

Both of these are selling supplements BTW.

…..

NATOKINASE

There are other supplements I do take, especially from time to time like aged garlic extract and natokinase, both of which have evidence showing impact on arterial plaque.

The next piece of my strategy was, believe it or not, medications. But before I go into what I take, I want to be clear. Medications are not the main driver of plaque reversal or plaque prevention. You cannot out prescribe a bad lifestyle. Let me repeat that. You cannot out prescribe a bad lifestyle. But when medications are used strategically, like supplements, in the right dose at the right time for the right person, they can help stabilize plaque or prevent it and lower risk while your lifestyle changes do the heavy lifting. Now, get ready for what I’m about to tell you because I’ve been criticized for this.

STATINS

Although, I truly believe it’s something that contributed to my results. One of the first I chose to take was a low-dose statin. Yes, I got a lot of haters for that. Not to hammer my LDL. That wasn’t my interest. My LDL or bad cholesterol, I wasn’t looking at trying to ground that into the ground, but I wanted to lower my inflammation and protect myself against recurring inflammation. You see, I knew if I had had plague, I had gone through episodes of developing inflammation. I knew I didn’t feel it. So, I wanted to continue to have a a backup for my lifestyle. I also knew that low-dose statins help with cardiovascular inflammation. So, that was my target. Most importantly, I started taking it after I found out I had plaque. Again, it’s that plaque business, because inflammation is what makes plaque unstable. And the evidence is strong that low doses of certain statins like ruba or previsatin can reduce that inflammation. I avoid the high dose approach and I avoid the more problematic statins. I for example don’t use a tobistan statin for me that meant rubatin 5 milligrams a day or even now two or three times a week.

Some of my patients are on five milligrams a week and that’s been demonstrated to have a positive impact. So you start thinking about weekly total dosages. You know, patients will come to me on 40 milligrams of versastatin a day times 7 days is what? 280 milligrams compared to 5 milligrams once a week. Totally different ballpark. Totally different universe.

ASPIRIN

I also used to take low aspirin. Let’s talk about aspirin for a minute and why I started taking it and why I’m taking something different now. When I started taking aspirin, it was recommended for primary prevention for people 65 or older and some recommendations said 60 or older. Primary prevention means you’ve reached a certain age. They’re not looking to see if you have high blood pressure or plaque or anything else. If you have heart disease, that means plaque. You’re no longer in primary prevention territory. You’re more in secondary prevention. So heart disease means you have documented plaque. If that’s your case, you’re no longer in the primary prevention category. You’re a cardiovascular patient, you’re in secondary prevention, and yes, those same guidelines say, “Yep, aspirin works for secondary prevention.” And even though it was recommended at the time I started it, I wasn’t taking it for primary prevention. I started it at the time that I discovered my own plaque because I said, “Okay, I’ve got plaque. I’m now a cardiovascular patient. I need to have a blood thinner type of impact.” and baby aspirin or aspirin 81 milligrams was what I needed. So, of course, there’s a bleeding risk. So, this is always a discussion to have with your doctor. If you notice, I said I used to take low dose aspirin.

I didn’t change it because it didn’t work or because of side effects. I stopped it for another reason. A few years later, I found out I had atrial fibrillation. It’s the most common heart rhythm problem and it’s associated with clots and therefore strokes. Aspirin just doesn’t protect it. Atrial fib raises your risk of stroke six to eight times. Aspirin does not do away with that extra risk from atrial fib. I had to exchange my aspirin for something else. It’s called NOAC, a novel oral anti-coagulant. So instead of baby aspirin, I took Eloquis. Now it’s interesting. Eloquis has shown a similar protection profile for heart attacks as low dose aspirin but a much much better risk reduction for strokes associated with atrial fib. So that’s why I made the switch in the mid-60s.

I started, well actually in the late 50s I started developing high blood pressure. I started years ago with Ramipril. It’s an ACE inhibitor. And again, you don’t need to remember the term. It’s just a type of blood pressure medicine that doctors were just beginning to use. They had used it quite often, but not so often for frontline high blood pressure management. I eventually switched to Lartin. It’s an RB. It’s similar, but different. And the problem was I was having a cough with the ACE inhibitor. Keeping blood pressure in the optimum range is another way to protect your arteries from damage over time.

I do use a low dose and it has helped me both keep my numbers down and steady and the key thing, protect my kidneys. The point is every one of these medications was added for a very specific reason based on my test results, my risk profile, my examination components like my blood pressure. And I review all these things regularly. If a medication isn’t helping or the numbers improve to the point where it’s no longer needed, I make a change, just like my patients do.


SALES PITCH

Medications are tools. They work best when they’re targeted, monitored, and used for support, not to replace the real drivers of cardiovascular health, your exercise, your sleep, your stress control. So, that’s my story in a nutshell. Remember, I was going to tell you about that one piece of the puzzle most people miss, even more important than lifestyle. But there’s one more thing I like to keep track of. If you’re ready to take prevention seriously, I want you to know you don’t have to keep struggling with a medical system that just pushes pills and doesn’t listen. I see so many people trying to figure this out on their own. And while it’s good to do your own research, we do a lot of stuff like that e-book to help support people who are figuring this out. In fact, if you just leave all the decisions to your doctor, you’re likely to get a lot of unnecessary procedures. It’s good to do your own research, but going solo, completely solo, that can lead to blind spots and mistakes that can put your health at risk. And so, this is where I’ve dedicated my career.

I was formerly trained in prevention and eventually ran the program, as I said, at John’s Hopkins, training the other doctors there in prevention. I know the strengths and the limits of traditional preventive medicine. To make this care more accessible, I’ve personally trained a team of clinical advisers. They take the same approach I do. Listening carefully and looking at the real drivers of heart disease and plaque, inflammation, and insulin resistance, not just the numbers most doctors stop at. And no, we don’t just do an LDL, bad cholesterol, and call it a day. When you call and you get more than an appointment, you’ll get guidance and support designed for your situation, your numbers, your goals.

You’ll finally have somebody in your corner helping you make the right decisions. If you’re ready to move beyond that kind of frustration and get prevention that actually work, here’s what to do now. If you’re interested in working with us, click the link in the description. Or call the number on your screen and one of our people will give you a call. They can or will take the call and can talk this through with you. And like I mentioned before, get your free copy of my seven step heart attack prevention program so that you can learn more about your risk, how to fix your metabolism, and reverse arterial plaque. Just click the link below and there it is.

Purpose. I’ve done videos on that and the videos admittedly are just not that popular. People think, “Oh, that’s just woo woo fishy stuff.” Woo! Purpose is not woo woo fishy stuff. When I got that first CIMT scan and I saw arteries of a 73y old at age 57, for me it scared me. But the truth is fear alone doesn’t keep you going. For me, my purpose was twofold. First, I wanted to be around not just alive, but healthy for the people I love. Second, I wanted to turn my own wake-up call into something that could help other people avoid a heart attack, stroke, blindness, kidney disease, erectile dysfunction, cardiovascular disease, the vascular part of cardiovascular disease. That’s why I shared these scans, these numbers, and the steps I took. I know what it feels like to think it’s too late, and I know the relief of realizing it’s not. When you have a clear purpose, the daily choices get easier.

You want a purpose that’s bigger than how I feel today. And a purpose that’s bigger than, well, this is what my doctor told me to do. You know, I think I’ve retired three, four, five times. Maybe more times than I can count. And I always come back to just sharing knowledge. It’s the type of knowledge I think will help people find hope and avoid heart attacks and strokes, make people’s lives better. Your purpose is the anchor that keeps you steady when life gets messy. When you’re tempted to fall back into old habits. If you don’t have that purpose yet, take some time, think about it, it’s the most important thing you can do. Because once you know why you want a longer, healthier life, the how to get there becomes a lot more doable. Finally, I know more about what to eat to reverse arterial plaque. If you want to know more about that, check out this video right here. [Points to link on screen]


KMAG DAILY THREAD 20260819 Iodine continued

HP02tM8WMAAT4sB

Site rules stolen from our good friend PAVACA

There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s post for any AI-generated content. To the best of her knowledge and belief, there is none. If readers wish to post any AI-generated content in the discussion thread for today’s post, they must cite their source. Thank you.


Do not forget to LABEL AI articles video and such.

Fun video


Dr. Elizabeth Bright

Elizabeth Bright DO, ND, a graduate of Columbia University, is a highly respected American Osteopath and Naturopath living in Italy. She is former Chef-owner of Coppi’s Organic and The Vigorelli Restaurants in Washington, D.C. She is a master in Chau Ka Kung Fu. She has been eating a high-fat carnivore diet and has been using it as a treatment modality since 2016.

She is the author of Good Fat is Good for Women: Menopause


Website: https://www.elizbright.com/

Dr. Elizabeth Bright—a renowned physician specializing in thyroid and adrenal health—reveals the pivotal role these small but mighty glands play in every stage of life, from before birth to your later years.

If you’ve ever been told your labs are “normal” but you still feel off, this book will open your eyes to the real science of your metabolism, energy, immune health, and stress resilience. [Amazon blurb]


FWIW from Brave AI

Osteopathic medicine is a distinct branch of medical practice in the United States that emphasizes a whole-person approach to healthcare, focusing on the interrelated unity of all body systems and the patient’s ability to self-heal. Doctors of Osteopathic Medicine (DOs) are fully licensed physicians who, like MDs, can prescribe medication, perform surgery, and specialize in any field of medicine. 

A few tidbits of information relevant to the video I am featuring.

YANDEX AI

…it is known that bromated flour, which contains bromine, has been used in the USA since 1914. In 1982, researchers in Japan published the first of a series of studies showing that potassium bromate, a food additive used in baking bread, causes cancer in the thyroids, kidneys, and other body parts of rats and mice. As a result of these findings, countries around the world banned the additive, but the U.S. Food and Drug Administration held back, in part because the amount of potassium bromate that remains in bread after baking should be negligible.

Hubby, reminds me that King Arthur flour is unbleached & unbromated. I wonder if bromine is NOT listed because it is not in the ‘bread’ just in the flour used to make it AND the FDA held back, in part because the amount of potassium bromate that remains in bread after baking should be negligible.


Don’t Worry About Cholesterol; Inflammation Is Your Biggest Problem — The Liver Doctor

 
“… the vast majority of cholesterol in your body was made in your liver.  Cholesterol production increases when the body is under stress: emotional stress can cause elevated cholesterol because the stress hormone cortisol is made out of cholesterol. Physical stress on the body can also elevate cholesterol.


Because cholesterol helps to repair and heal your body, you will produce more if there is a great deal of inflammation occurring in your body. So all those factors above that raise inflammation, can raise your cholesterol too…”

[worth reading the entire article. –GC]

33 minute Clip:

The SHOCKING TRUTH About Iodine! (Nobody Shares This) | Dr. Elizabeth Bright

Full Interview (1 hour 18 minutes):

Your Body Is BEGGING for Iodine (How Much You Actually Need) | Dr. Elizabeth Bright

ROUGH TRANSCRIPT of VIDEO.

I know this is very long so I am cutting out parts that do not directly impact the subject of iodine. The parts I think are really important or are novel such as A1 & A2 milk cows and dairy causing inflammation, I will use pulled quotes to highlight to make it easier to skim and get the meat of the article.

The person doing the interviewing is Jesse Chappus, a retired chiropractor. He is questioning Dr Bright. I am not going to go back thru and try to add the attributions. Hopefully the question marks will make it fairly clear.

BEGIN TRANSCRIPT

“Every single cell in the body needs iodine. Every tissue needs iodine. Iodine is an antibacterial, antifungal, antiviral. It’s a heavy metal chelator. It’s my shield. We use more nutrients when we’re in a state of stress. If your body’s fighting an infection that is a stress state, you need more iodine. It boosts your immune system. Your immune system needs iodine, the substances that interfere with the absorption of iodine. Fluoride, chloride, bromide. So that is really why people need to supplement, because they have been exposed to substances that prevent the absorption of iodine even if they can get in their food source, which they can’t really.

There are places in the world that have too much fluoride in the ground. Certain places in England. Where tea is grown [in] India, China. I don’t think there’s any way you can get away with drinking black tea, white tea, green tea… I lived in China, so I had access to the best teas in the world. I would consider all of them to be poison today.

…………….

WAIT WHAT? My morning tea is full of fluoride? -GC

……………..


YANDEX AI

The fluoride content in tea varies depending on the type of tea and the quality of the leaves used in its production. 135

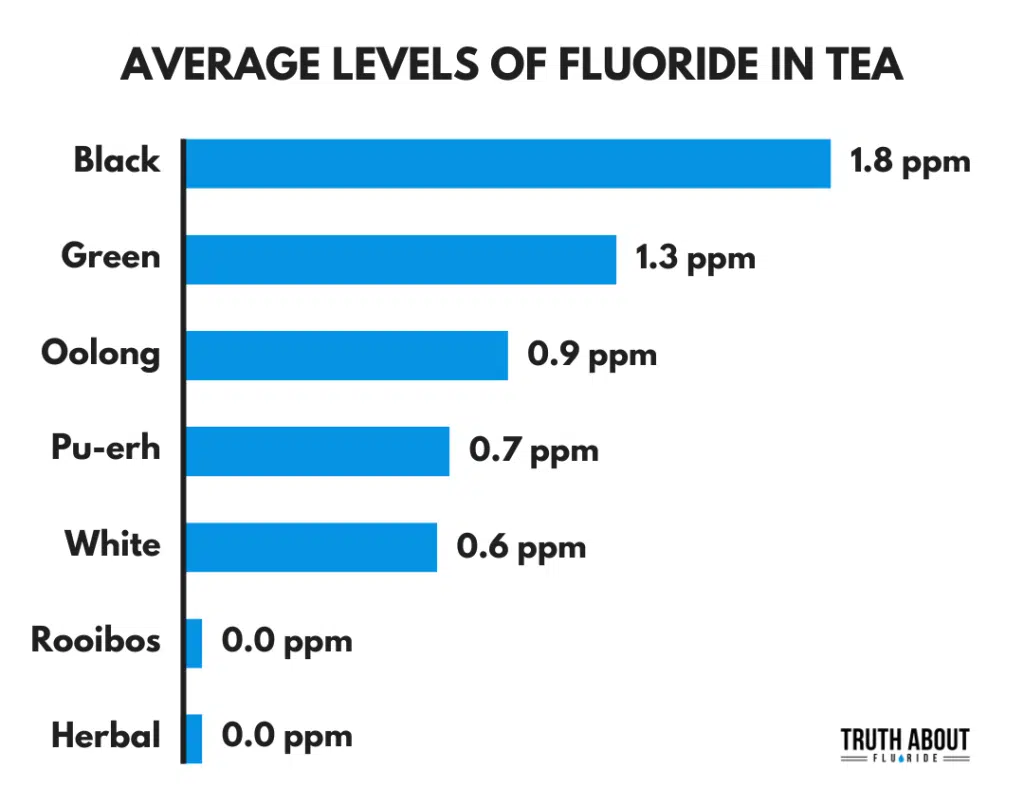
  • Black tea has the highest fluoride content among the types of tea. The average fluoride levels in black tea are 1.8 ppm, with the highest recorded levels reaching 4.2 ppm. 1
  • Green tea also contains fluoride, with average levels of 1.3 ppm, but the highest levels recorded were 3.2 ppm, and the lowest were 0.7 ppm. 1
  • Oolong tea has fluoride levels that are generally comparable to those recommended for the prevention of dental caries. 2
  • White tea is likely to have less fluoride than other types of tea, as it is made from the buds and youngest leaves of the tea plant. 23
  • Herbal teas do not contain fluoride. 1

The fluoride content in tea is not uniform. The plant stores the majority of environmental toxins and minerals in its older, mature leaves, which are used in cheap teas. These leaves are cheap, provide bulk, and produce a dark, strong liquor. However, they also act as a reservoir for fluoride. 3

The origin of tea and environmental factors, such as pollution, groundwater, air, and the soil in which it was grown, affect the amount of fluoride that accumulates in the plants. 5

Excessive fluoride consumption is linked to skeletal fluorosis, a condition that stiffens joints and compromises bone health. 34

REFERENCES

#1 Truth About Fluoride — Fluoride in tea: black, green, herbal (Search 357 teas) 2026 Update

“..On top of fluoride in tea being a large source, 94.9% of the fluoride in a cup of tea is directly available for the body to absorb.1…”

References for this article.

#a. https://scholar.google.com/scholar_lookup?journal=Turk+J+Chem&title=Determination+of+fluoride+in+various+samples+and+some+infusions+using+a+fluoride+selective+electrode&author=S+Tokal%C4%B1o%C4%9Flu&author=S+Kartal&author=U+Sahin&volume=28&publication_year=2004&pages=203-11&

  1. # b. https://www.ncbi.nlm.nih.gov/pubmed/21593111
  2. # c. https://truthaboutfluoride.com/skeletal-fluorosis/
  3. # d. https://www.researchgate.net/publication/8470993_Fluoride_Content_in_Tea_and_Its_Relationship_with_Tea_Quality
  4. # e. https://foodrevolution.org/blog/natural-flavors/
  5. # f. https://www.thelancet.com/journals/laneur/article/PIIS1474-4422(13)70278-3/fulltext

….

#2 Tea | Linus Pauling Institute | Oregon State University

#3 NDTV Food The Truth About Fluoride In Your Tea, And The Simple Switch that makes it safer

#4 Fluoride Content of Tea – Fluoride Action Network

#5 Fluoride Content in Asian Produced Green Teas | JCDA

……….

Back to the transcript.

“The problem is that nobody’s doing the “Hakala Lab” tests. They’re all going to their local lab and they’re testing radioactive iodine. They’re all looking for Chernobyl. None of these iodine blood tests that you get are testing organic iodine. They’re testing for radioactive iodine.”

………….


That took a bit of looking but I found the “Hakala Lab” tests. — GC

Testing Services

Hakala Research offers easy and efficient ways to test your Iodine levels. Our three testing methods include:

Each kit has the option to add bromide, fluoride, and/or chloride.

We are able to ship kits internationally (except to the UK). 

If you are ordering a kit for a youth, under the age of 18, please call/email us or enter their age and weight in the comment section to receive correct load dose. We cannot analyze loading tests for children under the age of 12…

This test kit is available for purchase in all states, except New York and California.

…..

Back to the Transcript

[Discussion about carnivore diet removed]

Not eating enough fat… Actually, women need more fat than males do to make more steroid hormones. …. I’m talking about adding additional fat to that meat because the fat is an anti inflammatory. So people who come to me have inflammation… So if somebody’s cooking up a steak, they’re putting say butter or tallow on top of that at the end. Say it’s ground beef and they’re making burger patties, same kind of thing, adding butter and tallow. …burgers are pre-digested in the sense that the blades that grind the meat have altered the protein somewhat. It’s not horrible. It’s just that the steak is going to have more nutrients. Because when you cook a steak, if you’re doing it medium, I’ve weighed it, when you do it medium rare, there’s 25% of the weight gone. Some of that is fat that stays in the pan or comes down into the grill tray and some of that is water soluble nutrients. So ground beef, you’re going to have fewer. It’s pre-digested in the sense that it has already gone through this process of being ground up.

….you brought seed oils in and you also talked about some of the quote unquote healthy plant fats such as coconut oil… I forget what specifically ones you covered there. But typically in that category would be like avocado oil, olive oil. I want to make sure we have a distinction there between the seed oils and those oils, because the seed oils are in a category of themselves that no matter what diet you’re on are considered toxic.

So seed oil soils are canola, peanut, it’s not even a seed. Those are the oils that we know are trans fats. These fat’s are very, very, very inflammatory.

….

Sama Hoole agrees H/T Barb Meier comment LINK.

….

Back to the Transcript

The olive oil wouldn’t be inflammatory, but it’s not going to give you cholesterol. Avocado and coconut oil are not going to give you cholesterol. And the cholesterol, the molecule only comes from animals. But arguably, if you’re using your volume of food intake and calories with those other fats, you’re taking up valuable space that you could use for healthy animal fats that come along with cholesterol…

…There are some people who are so inflamed — or have an immune system which has turned autoimmune. The tiny amount of milk protein in the butter could be temporarily a source of inflammation for them. They will eventually put the butter back in when they are better because it’s really the dose of the poison. It’s the milk protein that is the issue for the immune system. Just like gluten, …your immune system is looking for proteins. It’s looking for viruses, it’s looking for bacteria. They’re all made out of protein. So if your immune system has become autoimmune because it’s so inflamed, it will mistaken that the small amount of milk protein in the butter [as an enemy] and cause you to be inflamed…

… I know in general you’re not a big fan of supplements, but would that be something you’d ever consider?

….You have to be careful with all supplements because they’re basically very potent, small amounts of things that we’re just supposed to get from our regular diet. As you said, there’s one liver and the rest of it is muscle meat in an animal that you kill.

…But one supplement you’re a huge fan of [is] iodine … I want to come back into that.

Iodine. There’s a lot of detail we can cover within this subject. For people at this point who aren’t supplementing with iodine, talk about the current landscape and what they’re not getting from the diet… and why iodine is so beneficial….The issue today that is more – concerning are the substances that interfere with the absorption of iodine. Fluoride, chloride, bromide. So that is really… why people need to supplement, because they have been – exposed to substances that prevent the absorption of iodine, even if they can get it in their food source, which they can’t really.

You mentioned the other halides and how they can get in the way of absorption of iodine. Where are those typically found?

Your toothpaste, water, if they’ve put fluoride in your water. Chlorine in the pool, bromide in my chair. Probably this fire retardant substances, fabrics, things like that. Car seats. People aren’t licking their car seats. I think it’s more the fluoride that’s in the water and “PFAS” [Perfluoroalkyl and Polyfluoroalkyl Substances -GC] which are in our water that we can’t escape. There’s “PFAS” in the Maldives, so where are we going to go? We can’t go anywhere… We shouldn’t be running for the hills. We should be taking iodine to prevent insufficiency.

And as you explain that, I can see this is a double negative where, the other halides are so apparent in today’s modern world, affecting our iodine absorption… And then the one halide that we want to get isn’t readily found in the food anymore. So it’s hitting it from both ends.

That’s correct… Iodine is an essential nutrient. Chloride, bromide and fluoride are absolutely not. Fluoride being the one that is highly touted as something that prevents your teeth from deteriorating. But this is not true. It was never proven. There’s actually evidence to the contrary,that it causes fluorosis and makes your teeth rot. Which is what the fluoride content. And actually natural water sources. Fluoride is a mineral that is in the ground. So there are places in the world that have too much fluoride in the ground. Certain places in England, [places] where tea is grown, India, China, those places, the well water is very, very rich in fluoride. And those are the people, those areas, [have] a lot of congenital hypothyroidism, —– dwarfish, low stature, I think is what you’re supposed to say today. And learning disabilities, and of course, goiter.

Let’s talk more about that tea please.

So the tea leaves are being grown in soil that contains fluoride. So the end product that is dried out and shipped and packaged. You’re getting that, when you steep your tea, you’re getting that put back into the water? Yes, yes. And the cheaper teas have more fluoride than the more expensive teas. They have an actual rating system of how much fluoride is in the tea. Brick tea, loose tea has a lot more fluoride than your more expensive brands. It’s kind of like selenium, Brazil nuts… People think that they’re going to get selenium from Brazil nuts. There are areas that have more selenium in the soil. And those trees, the nuts of those trees will have more selenium in them than the other ones. But tea, it has a certain acidity that people like with tea means there’s more fluoride in it. So they [are] actually augmenting the fluoride by breeding and things like that to have the tea have more fluoride in it, so it has more acidity in the flavor. [And if you think the Chinese are not doing that breeding on purpose I have a bridge for sale. –GC]

All right, so cheaper teas, more of an issue here… How big of a problem is this in general? And is there specific types of tea people can still drink and not worry about this?

No, it’s [tea is] poison. So it’s a huge problem. I actually gave this paper to somebody in the UK. An Irish researcher published a warning to his country because they have mandated fluoride in the water. And the Irish drink a ton of tea. So there’s a huge rate of learning disabilities, fluorosis, fractured bone, osteoporosis, et cetera, et cetera, — everything that fluorosis causes, in Ireland. So I don’t think there’s any way you can get away with drinking black tea, white tea, green tea… I lived in China, so I had this access to the best teas in the world. None of them. I would consider all of them to be poison today.

…For somebody that’s been drinking a lot of tea in the past, is there a way to test to see how much of it’s accumulated in the body?.. And also, can you test teas for somebody that’s in love with their tea right now, doesn’t want to give it up and wants to just see if their particular blend, this is an issue for, even though it’s such a big issue in general. Can we test the tea? Can we test the body?

….

The teas have been tested. See Fluoride In Tea: Black, Green, Herbal (Search 357+ Teas) | 2026 Update

Fluoride in tea is one of the most forgotten and largest sources of fluoride. Some teas can even have 6 times the amount of fluoride when compared to tap water. So to find out which teas are safest, I tested 357+ teas for fluoride. And below you can search the results, learn how to avoid it and everything else about fluoride in tea.

If you love tea and have the cash to spare, go to the website and leave him a tip. – GC

….

Back to the Transcript

You can test the body. You can test the fluoride, bromide and chloride content in your urine and test the iodine. How much iodine is not able to come in because of these halides blocking the absorption of iodine. “Hakala Labs” in the US does that 24 hour urine uptake. You collect your urine for 24 hours, after ingesting 50 milligrams of iodine. You collect the urine, they test it and they give you… the results of how much bromide, the toxicity of halides, [are] in your urine, in your system. The teas, this Irish paper, actually I have found, — all the brands, he went through all the Irish brands that are popular.

… I have a couple of papers from China that did test the fluoride, not in particular teas. Yes, in teas. I actually have, because there’s Anhui province and there’s different provinces that- they did test…

….

[So China is well aware of the fluoride problem in the teas and yet they are breeding teas that will increase the uptake of fluoride from the water. –GC]

….

Any other plants that are prone to this, taking the fluoride and… concentrating it in the product?

“Tea is the worst one. Yes.

So coffee, not an issue?

Coffee, not an issue.

No other plants people are eating? Well, there are plants that prevent the absorption of iodine… Brassica, cauliflower, Brussels sprouts, kale, all those plants, that whole family of plants, they figured that out because the farmer went to check his rabbits and they were all eating cabbage leaves and they all had little goiters… The scientists went there and isolated basically what is in today’s antithyroid medication — from these plants. So it prevents, it is a antithyroid medication. Antithyroid substance because it prevents the absorption of iodine. So in my book, “Good Fat Is Good For Girls, Puberty and Adolescents”, I actually do list more – foods that we eat. Oatmeal is another one that prevent the absorption of iodine.

Any others you can think of off the top of your head?

Flaxseeds.

… Let’s talk about why iodine is so important.

Every single cell in the body needs iodine. Every tissue needs iodine. So your adrenals need iodine, your salivary gland, — the male’s prostate. Not just the thyroid. Female uterus, ovaries, breast tissue. – Every mucus bearing tissue has a ton of iodine in it. So your intestinal [tract]. — The microbiome stuff that people are always talking about. Not going to happen if you don’t have adequate iodine — in your intestinal mucus. Iodine is an antibacterial, antifungal, antiviral. It’s a heavy metal chelator. That’s why I said it’s my shield. The thyroid takes a minimum of 6mg. The breasts in females take 5mg. Can’t remember how much the prostate takes. I would consider any cyst in these tissues, any growth, any inflammation due to iodine deficiency.

And from last time we talked, the ideal dose of “Lugol’s,” as you recommend the “Lugol’s.” For maintenance, was two drops of 5% per day.Is that still correct?

Maintenance after you have. Yes, if you have had. I have women who come to me with swollen lymph glands. – Fibroids in their uterus. I will have them douche with iodine… So you’re actually getting it closer to the tissue that needs the iodine. If you’re taking it orally, that’s why “Lugol’s” is better, because it’s much more easily absorbed. You’re taking it… Everybody’s going to fight about the iodine if you are severely deficient. So sometimes it’s better to just get it. People paint their breasts with iodine.

And when it comes to time of day to take it, does it matter?

Is it better earlier on in the day? With food? just details on to best absorb it.

. I would say earlier in the day we are supposed to peak between 6 and 9. All our hormones kind of peak at that time. So you’re waking up bright eyed and bushy tailed to greet the day. I would take what you need in the morning. There are people who have inflamed thyroids that might react to the two drops that I’m saying you should take. So then you need to see if you’ve got nodules or thyroid antibodies.

Explain that in greater detail. What you’re saying there is if somebody already has a problem in the thyroid, if they activate that by taking “Lugol’s,” they might run into problems because of that. Otherwise iodine isn’t something we need to worry about. The kidneys will remove excess, correct?

Correct. Now imagine the tissue that has been devoid for a long time. So that could be the uterus, that could be the ovaries, that could be, the breast tissue. But usually the thyroid, because the thyroid is all follicular. Every part of the thyroid is working. The follicles are always there to make hormones. So breast tissue is not that way, uterus is not that way, prostate is not that way. So if it hasn’t had the iodine, if it’s kind of hunkered down and it hasn’t been producing adequate thyroid hormone because it doesn’t have enough iodine and it has maybe grown an extra piece, expanding itself trying to get more iodine. That extra piece or that inflamed thyroid will sit up and take notice and scream at you.

And how will somebody know if that’s the case?

Palpitations. They might have hyperthyroid symptoms, but they desperately need the iodine anyway. So then we do a detox.

Okay, so let’s say somebody finds out they have one of these nodules, they need to stop taking the dose you’re recommending here. How do they, or can they go about healing that?

They can definitely go about healing that [nodules]. I always recommend they do the salt loading protocol by taking… a small amount, one drop of iodine in a glass of half teaspoon of salt, and a little glass of water, followed by a whole bigger glass of water until they have to urinate. Because this is the way that the iodine will attack and the salt will pull the other halides out of the system. And so that’s a detox.

Dr Bright

Iodine becomes vapor if it’s attached to salt. Okay, so is that more a protocol for somebody that’s new to iodine?

I was getting at the person that has some kind of growth on the thyroid, and then they’re having a problem taking the iodine.

What you just explained there seems like a flush for anybody that wants to… basically get everything to ground zero. “Mmmhmm.” The part you just explained there, is that for everybody or just somebody with a nodule?

No, I think it’s for everybody, but definitely somebody with a nodule because they are — not able to have, their system is already so — deficient in iodine — that part of — their tissue might react. So it’ll start working. — And just it starting working can possibly make every single organ in the body. The heart is very much. So epinephrine is always telling the heart, the rhythm to beat. Right. And that comes from thyroid hormone. So if all of a sudden there’s more thyroid hormone than your body has ever dealt with, hasn’t dealt with in decades, everybody kind of has to get in line and figure out how to use that hormone again. It’s like resistance.

Okay. So, yes, it is a flush. And what I’m talking about is addressing also resistance to the hormone that is made. But for somebody with a nodule on the thyroid doing the flush, will that physical nodule dissipate over time?

Over time, but not just with the flush, but definitely over time, you have to remove inflammation. You have to make the autoimmune…

This is an autoimmune state, right?

So the immune system is actually attacking it. There’s a combination of… the thyroid is expanded in order to get more iodine, the thyroid also, has got scabs on its knees. — It’s being attacked by antibodies. You don’t have to have positive antibodies to have an inflamed thyroid. So the inflammation, they could just look at an ultrasound and tell you that you’ve got speckled thyroid tissue. The fact that there it’s hyper-vascularized. That is the definition of inflammation. Your antibodies might be negative, but your thyroid tissue is inflamed so… an anti-inflammatory diet, removing carbohydrates, et cetera will definitely help that too. It’s crucial.

From people you’ve worked with, do you find somebody with a nodule, most cases can remedy that without surgery then?

Yes, absolutely. What is difficult to remedy without surgery, just like somebody who maybe has a foot long fibroid. Right. So there is a point where you can teach the body tissue, anomalous tissue to regress. There is also a point of no return. A very large goiter may need surgery. It’s kind of hard to make that tissue that has become also calcified to some extent to regress. But definitely… all of my patients, goiter is more difficult. A very large softball size goiter is going to be very difficult. But inflamed thyroids, smaller goiters, they’ve all regressed. And nodules, they regress.

Essentially, is a goiter, just a nodule that’s grown out of hand?

Both. It’s also the — thyroid itself enlarges. All the follicular tissue will enlarge. So inflammation. Now “Hashimoto’s” is the lymph tissue in the thyroid is swollen. Okay. So we know if there’s a small nodule, good possibility following… doing flushing and the lifestyle we’re talking about today, they could reverse it.

If somebody has a full on goiter, can they reverse that naturally or no?

It depends on the size. It really depends on the size. — A very large goiter that has become calcified.

How can you?

You can’t. — — That’s why they do the ecogenic testing. They send sound waves to the thyroid to see how fast the sound wave comes back. If it comes back very fast it’s hard, it’s calcified. If it comes back slowly, it went “voof” into the thyroid which is just a big bloody mass of follicular tissue. So you want it to be a big bloody sponge.

If it’s got hard pieces on it that are calcified, how can you. — You can regress a cystic vascular mass. You can’t regress a hardened piece of tissue. Makes sense. So for somebody in that case where it’s just earlier stages, there’s nodules forming, but they’re small, they’re still in hope that they can reverse. You mentioned that protocol with the salt. Are they doing that daily along with the lifestyle or how often would they do that?


No, they’re just doing that for a week and sometimes they get diarrhea because stuff comes out. I have… many teenagers now who have thyroid nodules. Nobody’s checking kids because they’re just looking at “TSH.” So you can have rheumatism, you can have other autoimmune conditions, and they’re not going to look for it because — they don’t associate… those conditions with thyroid issues like I do. So if you are 70 years old, — it may take more time to – change this tissue that you’ve had… Because most people, most women become hypothyroid because of adolescence, which is what my second book is about.


odine is so necessary to have a healthy puberty, both male and female, but really, really important in female. But by the same token, I have more and more males today as patients. As I said, I have adolescents, pubertal young people who have thyroid issues. If you look at how the body has tried to heal since you were 12 and you’re 70. We’ll do the best we can. But if you have a softball sized goiter, I don’t think that we can make it shrink.

Dr Bright

For somebody right now who is a young adult feeling healthy, but they haven’t been supplementing with iodine to this point. It sounded like, but I want you to confirm doing that flush would be a good idea for them as well? And if so, how many times, if they’re not suffering right now?

I have a lot of people’s kids. — – The flush is… you could do…

My son is going to go to a pool because he hurt his back and mom is an osteopath, but she’s not in Athens. So he’s been given some exercises by an osteopath locally and he’s going to go to a pool. And I said, honey, triple your iodine intake because he’s going to go in the chlorine pool.

So I would say that… it sort of depends on the situation. It depends on your environment. – But what I’m talking about with females is that we are parents are now conscious of precocious puberty. We know that precocious puberty is bad for adulthood. There are mental health implications involved. Iodine supplementation as a child is important to prevent that.

So you gave that example there of your son going into a pool, upping his shield of iodine before going in. I would assume that would translate to any situation where somebody is going to come in contact with a lot of halides, if knowingly they’re going to be doing that, they want to up their iodine beforehand?

Yeah. And I do it when I travel. Any infection… — I have a cold. – Double your iodine. Because iodine, all nutrients… disappear. We use more nutrients when we’re in a state of stress. If your body’s fighting an infection that is a stress state, you need more iodine. And then it’s also an antibacterial, antiviral. So that’s great. It helps. It boost your immune system. Your immune system needs iodine. So, – we regularly travel and when we travel, we take more iodine. And then if somebody has a cold.

I talked to my daughter today, my grandson has a cold and.. she’s nursing him. Honey, it’s not enough for him to get the iodine from your breast milk. Get him to have a couple of drops of iodine. He’s two years old. Okay.

How young can somebody start to take… iodine orally?

Well, I’ll just say my grandson is going to be two in January. He needs iodine. So I want her to somehow get [it into him.]. We were trying to figure [it] out. Brainstorm how to get it in him because he doesn’t drink juice. He’s getting it from her breast milk, but not adequately. — She’s very busy. There’s — stress and – she’s, I don’t know, she can put it on a piece of meat.

Right. But what I’m getting at is you mentioned two and you wanted him to get some. But for a baby, like newborns, should they be supplementing or do they get enough through the breastmilk?

No, no, no, no. – My daughter has been taking a lot of iodine and he’s had enough, Babies who are nursing. but he’s now older and he’s eating more regular foods… So nursing is enough.

So through childhood, say somebody ends breastfeeding at 3, they’re eating solids. The parents are aware of what we’re talking about today and want to make sure they’re getting enough iodine into the kid. We talked about that two drop dose, but that’s for adults… Is that a good dose for kids as well?

I would say one drop. But again, like I said before, highlighting the fact that the kidneys can remove excess.

There is so much fear around iodine.

That’s why I want to get into the nuance here. It is a water soluble nutrient. So it’s not like vitamin D, it’s not like vitamin A. It’s not like, except for selenium. You can be toxic in selenium. That’s why I don’t recommend supplementing. But iodine is a water soluble nutrient. And all my books from the 40s and 50s measured the kidneys. They measured, they checked, they tested people’s urine. So they did all this research for us that tells us that iodine excess comes out in the urine. And the problem is that nobody’s doing the “Hakala Lab” tests.

They’re all doing the local lab and they’re testing radioactive iodine. They’re all looking for Chernobyl. None of these iodine blood tests that you get are testing organic iodine. They’re testing for radioactive iodine.

For somebody like you that’s been on iodine for a long period of time, you’re fully topped up… Do you ever do that salt protocol that you talked about?

I haven’t in years, no. No. I stopped drinking tea. I did it when I. — Years ago, I was drinking a lot of tea. I was going back and forth to China. No, I don’t need to do that.

Okay, so you already talked about a week. If somebody has nodules, they would want to incorporate that. And then for somebody who is a healthy adult about to begin an iodine protocol like you’re talking about here. Would they just want to do that salt protocol one or two times to flush everything out?

I put it on the protocol because most of my patients are drinking, a lot of them are drinking tea. In the US it’s iced tea. They think that it’s healthier than coffee. They write decaf tea. So that’s why I put it on their protocol because we got to get rid of the halides from the tea… I had a patient from Kazakhstan. — The iodine content in the soil of where this person was from. People from Michigan. I’m gonna. Okay, yeah, — maybe you need more. Maybe that’s why. My family’s from Tennessee. The mountains are devoid of iodine. It’s sort of a regular thing that I have people do now. It’s not some people, as I said, they get diarrhea. – – Some people don’t want to do it for a week. One person asked to do it for less because they were afraid of the salt. You have this whole hypertension fear that also comes with salt. –

A whole other — context. We talked about best time to take it, it sounded like that would be sometime in the morning. What about spreading the dosage out throughout the day?.. 2 drops, say taking one in the morning, one around dinner time. Any advantage there?

I don’t see it.

Any advantage including that in the food of a pet?

Definitely… You know that “J Crow’s” is geared towards animals anyway. They don’t want you to think that they’re selling it to human beings for horses. Right. — We know that there are tons.

Hypothyroidism is huge in pets today, dogs and cats, because of what we’re feeding them. I used to give my dog iodine. For somebody who has… autoimmune thyroid issues, “Hashimoto’s” specifically, there is a lot of fear. There’s already fear about taking iodine in general… And then there’s another additional layer for people in that category.

When you’re working with someone with “Hashimoto’s” is the protocol any different with iodine?


No. And I explain all of this. I go into – – I’ve researched all of this and I explain in my article on my articles page about why there’s this fear today. “Theodor Kocher” won the Nobel Prize in, I don’t know, 1911, and he had a reaction to sodium iodide. He might have also been taking who knows what other kinds of stuff. So he kind of started the anti-iodine thing. He’s the one who associated iodine taking iodine with hyperthyroidism. At the same time, every single physician was giving iodine to their patients. And then they all of a sudden stopped. Because he was a big guy, he just won a Nobel Prize. Everybody thought, oh, and people complained, other, other doctors complained that now iodine has been given a bad rap. And then they started using it again… to calm down patients when they were calmed down. Actually, it’s associated with hyperthyroidism. When they were cutting out people’s goiter, they would give them a ton of iodine to… make the heart not beat too hard. So it came back into favor clinically. But unfortunately, these were surgeons who love cutting stuff out and they were still geared towards cutting out goiters rather than healing them. So we have documentation of somebody like “Krile” saying — people who have… inflamed thyroids, give them iodine and natural desiccated thyroid. And it will shrink. So I have to go into all this. There’s so much… documentation that I have to explain when we talk about this and I do that in my articles.

Dr Bright


Does somebody need to ease into it though more if they have “Hashimoto’s” taking the iodine?


No, no. Your thyroid is inflamed. Remove the carbohydrates, remove the tea. Remove all these things that you’re doing… Maybe you’re running, maybe you’re doing “CrossFit,” maybe you’re all those things that are raising cortisol levels will also cause your immune system not to function properly. It’s not the iodine. Everybody has to take iodine.

Dr Bright

Okay. I just thought there might be some nuance there with dosages and easing in and somebody who is, their thyroid’s under attack and at least has a certain amount of damage at that point.

Some people have symptoms and some people don’t… Some people have positive antibodies and they don’t have. They don’t react to the iodine. I’ve had patients react to the iodine with palpitations who had no antibodies. It really goes with, you have to address each case individually. There’s not a hard and fast rule for people because some people don’t react and some people overreact. And then we do the flush and then we go very slowly because of resistance.

Are there any other supportive nutrients somebody wants to make sure they’re getting with the iodine that complement that as they’re turning their thyroid back on?

No, they’re all in food. So you have this famous co factors of selenium and zinc and “yada,” “yada,” “yada.” I’m sorry, I don’t think any of that’s necessary if you’re eating steak because all of those are more bioavailable in the ruminant meat that you’re eating.

Okay. Important caveat there though, for somebody who is eating the way you’re talking about, which for a lot of people is extreme and won’t be going to that level. “Mmmhmm.” “Mmmhmm.” Which is fine.

ZINC & SELENIUM

Everybody has their own journey. Sure, sure. And yeah, it’s for them to decide. But I just think it’s important we highlight that’s if you’re consuming a carnivore diet, which is heavy in ruminant animals. Well, the thing is that supplements can be toxic. So selenium is very easily toxic. I talk about in my book “Good Fat Is Good For Girls.” — You need a lot less selenium. Selenium it is 200 micrograms is usually what people are taking or told to take, and — that’s too much because selenium is easily toxic and too much selenium actually prevents the thyroid from making hormone. So I just don’t like supplements because you’re getting this huge, — it’s like taking a club to your nutrition rather than allowing your body to decide, I’ll go to the market and say, I’ll have a little bit of this, I’ll have a little bit of that. I’ll need a little bit of this. And it’s in the form that the body recognizes rather than hitting it over the top of the head with – 100 milligrams of zinc. This ties back to what we talked about before with the organs, where if you’re consuming those in supplement form, you might be pushing a lot more in the body than needed.

VITAMIN D

Yes. I wanted to talk about vitamin D. We got into this last time and listening back afterwards, I realized I needed clarification, so I’m sure other people do as well. You’re not a fan of supplementing with it. You don’t feel the sun has anything to do with our level of vitamin D in the body.

Right. Well, let’s start there because it’s an underlying assumption by basically everybody that vitamin D, our main source is sunlight. Talk about where we got that wrong. We got that wrong when they took away our fat. So nobody was making you stand outside getting a half an hour of sun on your skin pre 1980s… you can go to “Ngram Viewer” and look up this stuff, see when it started to be written about, when it started. I do that all the time with things. – Inuits don’t have vitamin D deficiencies. They don’t have — illnesses that are associated with low vitamin D because if they don’t go and eat “Pringles” from the store that people brought — they are living on seal and it’s very fatty animal. That vitamin D is a fat soluble nutrient that comes from the food they’re eating. It’s all very new. And the 70 the magic number 70 that I’ve learned in school is not. I don’t think you need that much. Most of you have to remember, most people are coming to me knowing that I’m a thyroid specialist. They probably have thyroid issues. Most of them do. And if you are hypothyroid, you can’t synthesize nutrients anyway… So you need adequate thyroid function to be able to turn that animal fat into vitamin D.

Okay. A lot more I want to get into within this to make sure I fully understand. So are we saying that vitamin D, which I would totally agree with, you can get it through at least certain foods, but are you saying that the sun can’t provide vitamin D or it’s just not what we should rely on?

Okay, so the sun hits the lipids on our skin and that is supposed to turn it into vitamin D3. The synthesis that happens through… lipids. Okay, so, – — it actually doesn’t work that way… It may work that way. It’s sort of a backup plan because nobody’s eating fat. If you’re not eating fat, maybe. I’m in the sun all the time. – If I weren’t in the sun all the time in Scotland, for instance, I’m not going to be eating vitamin D. Most people say, oh, I’m taking vitamin D seasonally because of the sun. I haven’t looked it up recently, but I’m sure if I did a deep dive into it, I could tell you the year just like I did with folate. We don’t need folate either. The year that they started… pushing this through. I’m sure this came after the cholesterol hypothesis, because the only way you can get vitamin D, vitamin A, any fat soluble nutrient, is if you eat that damn cholesterol.

Okay, the way I understood it before talking to you, we can get vitamin D, obviously from a supplement. We can get it through certain foods and then we can get it through the sun. And the way I’ve looked at it is when I’m not getting sunlight here in Ontario in the wintertime, I need to be upping… through supplementation or foods, vitamin D so my body has that. And I’m still a little bit gray here. It sounds like you’re not saying you can’t get vitamin D from the sun. It’s just not our primary source. Do I have that?


Right, it’s not our primary source. Yeah, it’s not as efficient. There are plenty of people who don’t live in the sun who eat a lot of animal fat, who don’t have vitamin D issues. Fluoride causes vitamin D deficiency… You can’t just isolate one factor and blame everything on it. Well, I can. Thyroid, I can blame everything on hypothyroidism, on thyroid dysfunction, but again, it’s a little bit more complicated. And supplements, isn’t it better to get it from your food? — We know that omega-3 — the sardines, the whatever… I don’t trust anybody’s vats and vats of oil… becoming rancid and then put it in these little capsules. I’m suspicious of that. If you can get it from your food I would recommend that.

Dr Bright

Me too… But I just want to make sure people are covered depending on their unique situation. So I think we’re on the same page now where sun can be a factor. And you’re just saying that you lean into the food source. An area I want to dig into a bit more in that, because if you do a “Google” search, foods that are high in vitamin D, it’s going to give you this list. – I’m assuming by the way you responded there, you’re not thinking we need to be that nuanced and search out these specific top foods to get it. You’re just eating your animal fats and that’s gonna cover you.

Absolutely. Because you do a “Google” search, it is predisposed toward the cholesterol hypothesis. You’re never gonna find [anything], unless you do the deep dives that I do in my research. [BOY, Ain’t that the truth! — GC]

On face value [from google], – stay in the sun, avoid animal fat. – So you’re not gonna find… those top foods that you find, it’s a crock. All Italians gravitate to the sun in the summer and they all think they’re getting tons of iodine. And all of my Italian patients that I had when I had a big practice, open practice before “COVID” they were iodine deficient… So, — it’s like that. —

Are you talking about vitamin D or iodine?

I was just mentioning iodine because people think that if you live by the sea, you can absorb the iodine.

Got it. Okay. But given we need to work with where people are at… somebody in Ontario, not getting sun throughout the winter, not eating the way you’re recommending. And even maybe they are eating a lot of animals, it’s just not to the carnivore extreme. Could you see an importance for vitamin D supplementation, if they’re eating say an animal based diet, but still including some carbs and they need that little bump to keep their vitamin D in a good range?

I would question why they need that bump. — I would say — they should eat enough fat because that’s the most bioavailable and healthy source. I’m a bit of a hard ass… But I think that obviously if you can’t eat, if you live in Ontario, I’m going to live in Scotland half the year, the sun is not going to shine very much. I will not consider taking vitamin D because I eat a lot of fat. But I think that you can eat some carbohydrates. I think that then we’re gonna, we might veer off into the Randle effect, [Randle Cycle] I don’t know. But if you have adequate animal fat and you’re taking iodine and you have the ability to make, turn that fat into vitamin D, vitamin A, vitamin K, vitamin E, then there’s no need to supplement. So I don’t know, if you refuse to eat animal fat, definitely you should supplement.

Okay, so for your ideal diet, high in animal fat, moderate protein. No carbohydrates. Talk about the protein piece and how, if it does, how that changes, the amount of that macro people are getting, at different stages of healing.

Initially because fat is anti inflammatory, you gotta make the hormones out of cholesterol… So we know that excess protein turns into glucose. If you can’t metabolize that protein into, I’m not going to show my muscles. But if you get into muscles and into enzymes and all the things that protein is needed for it’s just going to turn into glucose. We can only metabolize glucose or ketones. So I definitely dial down the protein to moderate in a healing state. Because most ill health is inflammation.

Other than diet, what are the biggest areas that in the modern world we’re being impacted negatively by inflammation?

I think that we are… over exercising. – Stress. I think that stress will definitely put a dent in our, it can turn an immune system autoimmune very easily because… cortisol causes inflammation. High cortisol levels cause inflammation. So we can go into all kinds of substances that people take from synthetic hormones to over exercising to foods that trigger inflammation. All of that will affect. So that’s still diet. Sorry. But yeah, stress, definitely over exercising, definitely. Pollution.

What are some of the safeguards, I know you filter your water, but what are some of the things in your environment at home you do to protect against environmental toxins?

Take iodine that’s my shield.

And what dose are you taking daily?

I’m taking six drops of 5% daily. Have been for a long time.

Any specific reason, previous health challenges? Because that’s more than you’re recommending to others.

I want a big shield. Because I don’t run for the hills. I’m falling in the “Adriatic.” Who knows those fishing boats and the crap that their engines are spilling into the water. – Because I know it comes out in my urine, if it’s too much. I take 12 drops when I’m traveling. Last time we got into testing a little bit.

You talked about two tests that you would do with people. One being thyroid, another being salivary cortisol. Let’s talk about a thyroid panel and get into details there because there’s thyroid panels that your doctor will do, and then there’s additional things that can be added. What do you think is really important there?

Free “T3” and free “T4.” And if you have inflammation, the thyroid antibodies. The two… that I recommend are antithyroid peroxidides and antithyroglobulin. Unfortunately, statistically more people have positive antithyroid peroxidase. And I’ve had patients ask for both, and they absolutely refuse to do both, to test both. And they also have a situation where once the antibodies are positive, they won’t test again… because they don’t believe that you can make them go down, you can bring them into remission, which my patients do all the time. You even have labs that say above a thousand in somebody who’s pregnant who needs to get those antibodies down, they don’t know we can’t see them go down. They have to go to a special lab to ask for the actual number. They don’t even bother because they assume that there’s nothing can be done. They can’t be reduced, they can’t go into remission.

Different people you’ve worked with over the years, following what we talked about today, the diet as the base, supplementing with iodine. What different chronic health conditions have you seen or reversed?

Thyroid cancer, — schizophrenia, —– many.

Anything that you found is particularly resistant to all this?

Weight loss. Some people, it takes a long time… I’m not really focused on weight loss. A lot of people are focused on weight loss. I’m more focused on getting the body healthy. So depression will go away for some people, before the 20 pounds that they’re trying to lose.

For the person out there… feeling like I’ve been stuck with weight loss, this sounds interesting, but you’re telling me to consume copious amounts of fat. How am I ever going to burn the fat on my body? Give them some reassurance there.

Well, when I give them a protocol, it’s for their structure so I’m not counting calories. I’m giving them the quantity of protein that they need for their structure and the quantity of fat that they need for their energy. It’s not calories in calories out there is a certain amount of nutrition, energy you would say that you need in adolescence. And somebody who’s six foot tall needs a lot more than somebody who’s five foot tall. But when you are in ketosis, which you will be, you will be burning your own body fat. But if you go out and run a marathon, you’re not going to burn any body fat. Because you can eat nothing and not burn any fat, because your body is holding onto that fat because it thinks you’re in danger.

And for you, the big tool to… provide the input, to calm the body, is this high fat diet.

Yeah, absolutely, [it] reduces stress.

For somebody, again, thinking about heading into what we’re talking about today, but this is a big leap. They’ve been having a more standard type diet and they’re thinking about all the saturated fat they’re gonna consume by eating this way. And they’re thinking conventional, which we’ve all been told saturated fat causes all kinds of heart disease, health complications. Help put their mind to rest.


Well, saturated fat is cholesterol, so we know that, — that’s what I’ve written about in my books. Saturated fat. — Cholesterol prevents depression. Avoiding saturated fat, – people who have low cholesterol levels are more at the risk of depression. They’re more at the risk of mental health issues. – – So, — everything in our body needs – cholesterol. It’s an anti inflammatory, it’s a source of our brain tissue, it’s a source of our nerve tissue, it’s a source of our energy and it’s a source of our steroid hormones. So our entire endocrine system, steroids, hormones are made out of cholesterol. So if you’re avoiding something that you need so much, we are human because we started eating… so much animal fat. Our brain grew bigger because we ate animal fat. More animal fat. This is documented. You kind of have to take a… I don’t want to say a leap of faith, but if it’s only been, I’m 62, it’s only been since 1984… that everybody has told you because it wasn’t until that “Time” cover story with the unhappy face, — the bacon bad and the eggs bad, that everybody started avoiding cholesterol. Before that, it was after “Ancel Keys,” the cholesterol hypothesis, heart disease was supposedly caused by this. But that is really the time if you look at pictures of people at “Jones” beach, on the beaches, that is really the time that you see and you have to think that was only what is it, 60 years ago, that is not history.

Dr Bright

Because this diet is so radically different from what the average person is eating right now. Give us some ideas of meals and what a typical day could look like for somebody.

Well, it depends if you’re six feet tall, but I’m five foot seven and a half. I eat, I have decaf with butter and egg yolk and then I go paddleboarding and then I come back and I do protocols and then I eat, – I don’t know, 150, 200 grams of steak — with some butter on it. And then I work. And then for dinner I have the same thing. So for me, I may have run and have some beef jerky during the day between calls. – But that’s — fine for me. Somebody might want more, somebody might want more chicken. Somebody might want bacon. If I could get bacon, I would eat it. I can’t get bacon. So I like bacon. It’s yummy, but I can’t get it, so I’m not going to bother. – I remember I put together for my height, a pound of meat and 4 ounces of butter just to make it visual.

And because your diet is so limited in diversity, are you still excited about your meals?

Oh yeah, I am. – I am, I am. I don’t think the variety. I love how I feel and I’m hungry when I go eat, so I’m very happy to eat. I love my decaf with a froth of butter this thick in the morning. I may have one again… at 11 if I did 8k like I did yesterday on the paddleboard. So… yeah, I’m definitely excited about my meals. But I’m excited about life. Meals just fuel…

Fuel, so you can live the life? So for you, drink wise, you have your decaf fatty coffee, you filter your water. Any other drinks in there for fun?

Sometimes I’ll have a half a shot of bourbon. Like, this much.

And is that purely for fun or do you think there’s certain benefits or negative side effects?

That’s just for fun. It’s small enough. Oh my God. No benefits at all. – But as I said, it’s such a small amount. If I had more, I’d turn red. — — I would flush. It would cause a vasomotor reaction. It would cause a hot flash because of the cortisol produced by alcohol being a stimulant.

Let’s talk about sleep and how you prioritize that. I’m assuming you must, given the fact, the thesis of — everything you’re working on through diet and lifestyle is to… bring down the sympathetic and bring up the parasympathetic system, the rest and digest. How do you look at sleep and how do you make sure you’re getting best sleep possible?

I go to bed early, go to bed about 9. I read. 8:30, 9:00, latest 9:30… I have fat before I go to sleep so I can tone down. We know that cholesterol actually can increase… parasympathetic tone. As an osteopath, parasympathetic and sympathetic have to be in balance, so that’s very much a part of my training. And the magic of learning how to do it with food, with fat, it was really an epiphany for me, which is what I did when I went into menopause at 52. So I give myself fat. I have obviously, if we’re going to go for a trip or I have something very stressful coming up. If I wake up in the middle of the night, I have fat in my fridge. I just grab it and eat it and I go right back to sleep.

And what will that fat snack look like whether it’s before bed or middle of the night? Just a piece of butter or something simple, I assume.

Piece of butter on a meat cookie or… some of that tallow that I have from the leftover after I’ve given the gelatin to my daughter. There’s that big thing of fat, that’s tallow. Yeah. I’ll salt it and put salt. Yeah, just salt… I’ll freeze it and I’ll cut it into chunks and I’ll just leave it there.

One thing I want to mention too, tying iodine into the sleep piece. You don’t want to have your iodine right before bed. I’ve done that before and it does stimulate you. So you want to be careful. Yeah, it’ll wake up your thyroid… Your thyroid will be like, oh, let’s make hormone, it’s the morning…

Any areas in the last number of years that you’ve really taken a pivot on or changed your mind on things?

DAIRY [This is a whole new rabbit hole! – GC]

I actually republished my “Good Fat is Good for Women: Menopause” book because… the snacks had cheese… And I decided that if people had – menopausal symptoms because of the inflammation and because of their adrenal issues, they definitely had to take out the dairy, which causes inflammation because of the xenomorphins.

Okay, we did talk about dairy last time, but since it’s brought up again, I want to get into it a bit more here. Is this all dairy or just cow dairy?

Not butter. Not butter. — No, not butter, yeah. Oh,”A2,” “A1” you’re talking about. Well, just different… There’s a lot of people in the health space that won’t have cow dairy, but they’ll have sheep or goat. Right. It’s “A2.” There is a lot of variables.

Well, that’s “A2.” But you can also have “A2” of cows milk as well.. There’s a lot of nuance and we got into again some of this last time. But are we talking about all dairy or are there certain details or types within that that we can still have?

I think if you’re on fire, you can’t have any dairy. You can have butter because we know that buttermilk is where all the proteins go. Unless you are so sensitive that you need to make ghee and you see the teeny tiny bit of milk protein and lactose come to the top. None of this has to do with lactose. It’s all about proteins. – So the more inflamed you are, you should not have any kind of dairy. So you can have Guernsey, Jersey. Those places in England, they have the breeds of cows that are”A2.” Senegal… Certain cows, yes, they are “A2,” but there is still a small quantity of casinomorphins in that. So there’s more in the regular, that breed that most cow milk is, but there’s a — smaller amount in the “A2” goat, sheep, Jersey, Guernsey breeds. Now, if you are on fire. I don’t recommend it at least for a certain amount of time, until the fires have been put out.

Did you personally notice a difference in your health when you took dairy out?

I did. My digestion was better, my husband’s breath was better. —– Yeah. And then I read Keith Woodford’s book “Devil in the Milk.”

Talk more about what that brought up for you?


Just reading about how heart disease, diabetes things that we basically, he explains that all chronic, most chronic diseases are because we’re drinking “A1” milk. So he’s an Australian and or actually New Zealand, I don’t know, anyway, but he’s talking mostly about how they actually prevented in Australia, the ability for people to have access to “A2” milk, even though it was so much more documented, so much healthier for people.

Dr Bright

So throughout our conversation, the two big targets that we’re honing in on, cortisol through stress, we want to bring that down. Inflammation. Given the focus in on inflammation, we talked about testing before, do you see any value in doing a test to look at overall inflammation and getting a number there to work from?

No. I recommend doing salivary cortisol, a diurnal salivary cortisol test, because your inflammation, you can do the “CRP,” you can do, it doesn’t matter. Once you fix the cortisol, once you’ve removed obstacles to your healing, all those will come into line. They will come in. —– You have to reduce the inflammation. So I don’t recommend testing. It’s just like, I recommend testing the thyroid and recommend testing salivary cortisol. And when you fix those things, everything else will just kind of come into line. So… there’s no reason to pay all this money for these other tests.

Elizabeth, really enjoyed round two, getting into some details on a lot of things we talked about in the first round. I appreciate you, the work you’re doing. We’re gonna link up your website, your books, everything in the show notes… You’re gonna wanna stick around here and catch this other incredible episode. You don’t wanna miss it. I’ll see you over there.


We’ve tested over 8,000 people in our office, over 97% are deficient in iodine, the vast majority, severely deficient in iodine. All thyroid hormone can’t be made without iodine. Thyroxin, or “T4” is four atoms of iodine attached.

Dr Bright

I do not necessarily agree with all that Dr Bright has said, but it is certainly food for thought. It also makes me even less inclined to trust the medical industry if that is possible. – GC

Dear MAGA: 20260818 ❀ DePat Tuesday ❀ Open Topic | Is There Another Cell Nucleus Hall Pass in the New mRNA Flu Vaccine, mFlusiva?

This DePat Tuesday Open Thread honors the author of the original Tuesday open thread on this site, namely the late Susie Sampson, a.k.a. Deplorable Patriot, among her other handles, pen names, etc.

For more on the untimely passing of Dear DePat, please see these three posts.


At one time, DePat handled FOUR daily open threads here, in addition to taking care of her relatives, choir duties, and numerous other responsibilities. She was a powerhouse – a dynamo – a true force of nature.

DePat’s faith in Trump, Q, “The Plan”, the White Hats, and “the anons” in general, was legendary. Although I didn’t always agree with her quick acceptance of some sketchier evidence and fringier theories, I will gladly admit to “coming around” to numerous so-called “conspiracy theories” which she championed first. I was always careful to give her credit for being right, too, when I had been wrong.

It is impossible to overstate how much DePat did for not only this site, but for her country. I urge all to say a quick prayer of thanks, whenever you think of her, for the privilege of knowing, in life or after death, such an exemplary human being, and lover of God.

And thank you, Susie, for the firm foundation which you left us, when you were called to your true home!


Is There Another Cell Nucleus Hall Pass in the New mRNA Flu Vaccine, mFlusiva?

Let’s start off with some history.

Are you aware of the fact that both the Moderna AND the Pfizer COVID vaccines contained a genetic sequence that acts like a “hall pass” or “VIP ticket”, allowing the holder to get into the nucleus of human cells?

Here is a post where I explained this.

Were it not for somebody dropping a link to an obscure paper in my Twitter timeline back in early 2023, I would have never realized how extra sketchy that made both the virus and the vaccines – and especially the latter, since it would have been theoretically possible to remove the nuclear hall pass from the spike protein used as the vaccine.

Let me repeat that. They left the “hall pass” in the mRNA code for the vaccine.

But – and I have to stress this – it was not just that this “hall pass” was there. No. It was much worse. The paper in question was experimental, and it showed that the viral spike protein not only contained the hall pass, but that it WORKED. The hall pass actually worked to get the spike protein into the nucleus. They even had PICTURES of it in the nucleus.

LINK: https://www.frontiersin.org/journals/microbiology/articles/10.3389/fmicb.2023.1073789/full

BUT WAIT! THERE’S MORE!

The hall pass not only got the spike protein into the nucleus – the spike protein THEN got the mRNA that coded for it into the nucleus, as well.

Yes. You are reading that correctly. The spike protein of SARS-CoV-2 has a known sequence in it that ends up getting both IT and the mRNA that created it, into the cell nucleus.

One would THINK that this might be a big deal. Especially after we were REASSURED that NO, VIRGINIA – THE mRNA WILL NEVER, EVER GET INTO THE CELL NUCLEUS, YOU FOOLISH VACCINE SKEPTICS.

Are you seeing why this is kind of a big deal?

SO – NOW – my question about the new mRNA flu shot is similar.

I could ask whether the flu vaccine’s “spike protein” (it’s called a “hemagglutinin glycoprotein”) also has a hall pass that gets it into the cell nucleus. I could even ask if the influenza HA glycoprotein also “escorts” its own mRNA into the nucleus, as does the COVID spike protein.

However, that requires experimentation. I can’t do that work.

OK – can I just ask if the mRNA flu shots contain the hall pass into the nucleus?

Well, it turns out that you can ask, but there’s not necessarily an answer.

I could not find the answer, so I asked Grok.

And I asked Grok a slightly less pointed version of the question, since I am perfectly capable of checking for nuclear translocation sequences myself, so that Grok would not detect “conspiracy theory thinking” on my part, and thereby not consign my question to the “talk down to this human” conga line of incomplete answers.

LINK: https://x.com/i/grok?conversation=2088464094655385678


Q: Is there a published mRNA sequence for the new mRNA flu vaccine, mFlusiva, from Moderna?


A: (from Grok)

No, there does not appear to be a publicly published full mRNA (nucleotide) sequence for Moderna’s mFlusiva (mRNA-1010).

mFlusiva is the FDA-approved (as of early August 2026) trivalent mRNA influenza vaccine for adults 50+ (traditional approval for ages 50–64; accelerated for 65+). Each 0.38 mL dose contains 37.5 µg total mRNA (12.5 µg each of three RNAs) encoding the full-length hemagglutinin (HA) glycoproteins of the season’s recommended strains (for the 2026–2027 formula: A/Missouri/11/2025 (H1N1)pdm09-like, A/Michigan/105/2025 [A/Darwin/1415/2025 (H3N2)-like], and B/Pennsylvania/19/2025 [B/Pennsylvania/14/2025-like]), formulated in lipid nanoparticles (SM-102, PEG2000-DMG, cholesterol, DSPC).

Public documents (prescribing information/DailyMed, FDA briefing documents and clinical review, Moderna product pages, and peer-reviewed trial publications) describe the composition, encoded antigens/strains, manufacturing process (in vitro transcription, no cells/eggs), and clinical data, but they do not disclose the actual nucleotide sequences of the mRNAs. These would include codon optimization, specific 5′/3′ UTRs, poly(A) tail, nucleoside modifications (typically N1-methylpseudouridine, as used in Moderna’s platform), and any stabilizing mutations (noted for the influenza B HA in non-surface-exposed regions).

  • The underlying viral HA amino-acid (or genomic) sequences of the recommended strains are publicly available via databases such as GISAID or NCBI, as with any seasonal flu vaccine components.
  • Moderna and related patents/publications disclose example or earlier-generation influenza mRNA constructs, sequences for other candidates, or general platform elements (e.g., UTRs used in some Moderna mRNAs), but not the proprietary, strain-updated commercial sequences for the approved mFlusiva product. patents.google.com
  • This is consistent with how proprietary vaccine sequences (including prior Moderna mRNA products) are typically handled—they are not routinely released in full in labeling or regulatory summaries.

In short, while the antigens, doses, and high-level design are public, the exact published mRNA sequence for mFlusiva is not available. Any claims of a full sequence circulating would need independent verification against primary sources.

(END GROK)


(BEGIN WOLF)

First of all, just for the record, this is a great answer. Once again, thank you, Elon!

This situation seems a bit different from small-molecule drugs, where the exact molecules in the drug MUST be described in full, not only to the FDA, but to the public. Probably a feature that big pharma will eventually pay government to remove, but until then, something that certainly cramps their style.

Now, I was able to track things down a bit, and get CLOSE to the actual sequence for the vaccine, but I have been unable to find the exact sequence.

Here is what I did find.


(1) Link to full prescribing information.

https://dailymed.nlm.nih.gov/dailymed/fda/fdaDrugXsl.cfm?setid=3dd1c6d2-b054-4803-bb21-460b1b090d4c&type=display

(2) Information about ingredients

MFLUSIVA 
influenza vaccine, mrna injection, suspension
Product Information
Product Type VACCINE
Item Code (Source) NDC:80777-500
Route of Administration INTRAMUSCULAR
Active Ingredient/Active Moiety

Ingredient Name Basis of Strength Strength
RNA-101-BFL3 (UNII: FPY755GU6Z) (RNA-101-BFL3 – UNII:FPY755GU6Z) RNA-101-BFL3 12.5 ug  in 0.38 mL
RNA-101-BFL6 (UNII: G35CN36JAP) (RNA-101-BFL6 – UNII:G35CN36JAP) RNA-101-BFL6 12.5 ug  in 0.38 mL
RNA-101-BFL5 (UNII: WAH8KM77XC) (RNA-101-BFL5 – UNII:WAH8KM77XC) RNA-101-BFL5 12.5 ug  in 0.38 mL
Inactive Ingredients

Ingredient Name Strength
SM-102 (UNII: T7OBQ65G2I) 
1,2-DIMYRISTOYL-RAC-GLYCERO-3-METHOXYPOLYETHYLENE GLYCOL 2000 (UNII: 9X2596CIE0) 
CHOLESTEROL (UNII: 97C5T2UQ7J) 
1,2-DISTEAROYL-SN-GLYCERO-3-PHOSPHOCHOLINE (UNII: 043IPI2M0K) 
TROMETHAMINE (UNII: 023C2WHX2V) 
TROMETHAMINE HYDROCHLORIDE (UNII: 383V75M34E) 
SUCROSE (UNII: C151H8M554) 
WATER (UNII: 059QF0KO0R)

(3) Selected information about mRNA ingredients

RNA-101-BFL3 (UNII: FPY755GU6Z)
RNA-101-BFL6 (UNII: G35CN36JAP)
RNA-101-BFL5 (UNII: WAH8KM77XC)

(4) UNII codes

FPY755GU6Z
G35CN36JAP
WAH8KM77XC

(5) Look up UNII codes

Website: https://precision.fda.gov/uniisearch

Results:

https://precision.fda.gov/uniisearch/srs/unii/FPY755GU6Z

https://precision.fda.gov/uniisearch/srs/unii/G35CN36JAP

https://precision.fda.gov/uniisearch/srs/unii/WAH8KM77XC

(6) CAS Registry Numbers and CAS Names

(a)

3115056-86-2
RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza A (Missouri/11/2025 (A/H1N1))-like virus hemagglutinin codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL3), inner salt

(b)

3115056-85-1
RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza A (Michigan/105/2025 (A/H3N2))-like virus hemagglutinin codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL5), inner salt

(c)

3118110-32-7
RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza B/Victoria Pennsylvania/19/2025-like virus hemagglutinin [288-valine,381-tyrosine] codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL6), inner salt


That is as far as I could go. Registry numbers and names. Trying to look up the CAS registry numbers failed.

CAS Common Chemistry covers – well – common chemicals, including some surprisingly unusual ones, but it clearly doesn’t cover everything. For a lot of molecules – ones that are not “public figures” – one has to get behind the paywall by buying a product like SciFinder.

For example, CAS Common Chemistry has a page for one of the allegedly inactive substances in the vaccine – tromethamine.

LINK: https://commonchemistry.cas.org/detail?cas_rn=77-86-1&search=tromethamine

SIDEBAR: I’ll do a whole post about tromethamine later – it’s one of the best and most hilarious demonstrations of the (to borrow Scott’s verbiage) “weak, fake and gay” duplicity of the pharma-government-fincorp-media complex that I’ve ever seen. I’m personally glad they smartly added this compound to the clot shot, but to lie about why they did it – just so WEAK, FAKE AND GAY!

It is possible that the three names we retrieved above would allow trained biochemists to get very close to the actual sequences that were used, but in reality, to get the full, exact composition, including DNA contamination, we will almost certainly have to wait for independent researchers to analyze and sequence vials of the mFlusiva vaccine.

SO – in answer to the original question, we won’t truly know if there is either a public or secret access code to the cell nucleus in this vaccine, until somebody in free science actually analyzes the sequence of the vaccine, and somebody else actually checks and sees if the protein and/or the mRNA gets trafficked into the nucleus.

To borrow a saying from Nancy Pelosi, “We have to inject it, to find out what’s in it.”

Honestly, I think if Thomas Jefferson saw what patents have done to science, he would pull the whole idea up by the roots and figure out some other way to implement it. What that something else is, I don’t know. But what we have now is clearly problematic.

W

And remember…….

Until victory, have faith!

And trust the big plan, too!

And as always….

ENJOY THE SHOW

W


Dear KMAG: 20260817 ❀ Wheatie Monday ❀ Open Topic | Let’s Talk About Virus, Vaccine, and Protein Shedding


This Stormwatch Monday Open Thread remains open – VERY OPEN – a place for everybody to post whatever they feel they would like to tell the White Hats, and the rest of the MAGA/KAG/KMAG world (with KMAG being a bit of both).

And yes, it’s Monday…again.

But we WILL get through it!

We will always remember Wheatie,

Pray for Trump,

Yet have fun,

and HOLD ON when things get crazy!


We will follow the RULES of civility that Wheatie left for us:

Wheatie’s Rules:

  1. No food fights.
  2. No running with scissors.
  3. If you bring snacks, bring enough for everyone.

And while we engage in vigorous free speech, we will remember Wheatie’s advice on civility, non-violence, and site unity:

“We’re on the same side here so let’s not engage in friendly fire.”

“Let’s not give the odious Internet Censors a reason to shut down this precious haven that Wolf has created for us.”

If this site gets shut down, please remember various ways to get back in touch with the rest of the gang:

Our beloved country is STILL under DIRECT THREATS by hostile forces – notably COMMUNISTS – and they’re HERE IN AMERICA.

Daily outrage and commie phuckery still abound.

We can give in to despair…or we can be defiant and fight back in any way that we can.

Commies won’t win!

And we will keep saying COMMIES OUT until we get their FRAUD and INSANITY out of our country!


THE STUFF

Let’s Talk About Virus, Vaccine, and Protein Shedding

I have noticed something very interesting about the “shedding” phenomenon.

The “vaxxes can do no wrong” side doesn’t like to talk about shedding. They don’t bring shedding up, and they frequently change the subject when an argument about shedding gets started.

It’s easy to dismiss “shedding” as a conspiracy theory, but once one sees actual Pfizer documentation on the topic (link now dead, curiously), the reality of “shedding” in the vaccine world hits one square in the face. Media shills for vaccines may be crowing on TV that “shedding” is all a big lie, but when the vaccine manufacturer is testing the vaccine, suddenly it’s the greatest danger of the study, and test participants find themselves separated if not isolated from spouses, infants, relatives and friends. Yet another reason people cannot stand the lying fake news media.

The most disingenuous current deflection of the problem in vaccines, is that the FDA has a HUGE concern with the shedding of “gene therapy” products – which often use mRNA in lipid nanoparticles – but then says that it’s not a problem in mRNA vaccines because they’re not classified as gene therapy products. Robert Malone has always been highly critical of this teenager-level dodge of responsibility, and frankly I think anybody involved in that scandal needs to be fired from government and possibly prosecuted for fraud. It’s the same weak chutzpah as the 17-year-old murderer of his parents, demanding first leniency as an orphan, and then prosecution as a juvenile, when the initial lunacy doesn’t prevail.

I recall the first time I read documentation of how shedding of a vaccine was to be guarded against in a major vaccine clinical trial, by significant restrictions of the participants from close contact with other people during the observation period.

“So – you mean shedding is REAL?” Oh yes. It’s real. The FDA has always had significant discussions of it. The big question is this – what is being shed? THAT makes all the difference.


Shedding of Viruses

Shedding of a virus – why – that’s just DISEASE. Communicable disease. We are all familiar with THAT.

Well, vaccines can be a virus – including weakened and incompletely deactivated viruses. It can even be a normal but less pathogenic virus, like cowpox, used as a literal vaccine against a more dangerous virus like smallpox. A weak but “live” virus may be difficult to transmit, but in many cases, transmission is still possible.

Shedding of a virus per se is the most potentially dangerous form of shedding, but it’s also the most well-known, and the easiest to understand. A limited number of viral particles is all that is necessary to start a disease in a new host. Being a victim of viral shedding is literally catching a disease. This is reality – something that happens all the time with common colds and influenza-like diseases (ILIs). Catching a shed virus is vaccination against catching the exact same form again – but not against sufficiently mutated forms. We are familiar with THAT from COVID-19.

So when people catch a communicable viral disease, they catch a shed virus, start constructing the virus, and then shed the virus again. Simple, and very real. But the outcome of viral infection is very uncertain, and that unpredictability ends up being a liability of using sheddable viruses as vaccines.

There is a reason I’m harping on this form of shedding. One needs to keep shedding of vaccine in perspective with the more dangerous, more likely, and more consequential shedding of virus. If you suddenly experience symptoms of a disease, including symptoms of the protein produced by that disease, then it is far more likely that you are a victim of shedding of the actual virus, than shedding of the vaccine. This is a simple reality, which I believe has led many patriots, including Deplorable Patriot, astray, in losing focus on relative risks. It is important to keep ALL forms of shedding in mind.


Shedding of Proteins

At the other end of danger, is the shedding of viral proteins, but not the virus itself. Let’s consider that.

Viral proteins can’t reproduce, but they CAN show all the bad properties of other nasty, dangerous, pathogenic proteins.

For example, the spike proteins of corona viruses are notoriously pathogenic, and when they are administered to test animals in an aerosol, they create immediate pulmonary disease, and can even kill the test animals. Yes, it’s shocking.

Example: https://faseb.onlinelibrary.wiley.com/doi/10.1096/fasebj.2021.35.S1.04183

Still not convinced that a small amount of “shed” protein can be dangerous? Let’s talk about snake venoms.

Snake venoms are mostly dangerous because of pathogenic proteins, and these proteins are often very similar to bacterial or viral proteins, or arthropod venoms, as well as powerful digestive enzymes.

The thing is – and you likely didn’t know this – venomous snakes “shed” not only their skin, but also their VENOM. That fact is why people who care for venomous reptiles need to wear gloves and respirators when they clean cages. Shake venom gets into the cage dust, and cleaning it out exposes workers to skin and respiratory dangers pretty much like test animals breathing corona virus spike proteins in an aerosol.

So, again, shedding of pathogenic proteins can be real.

The only questions are, what viral protein is it, how is one being exposed to it, and how much of it is one being exposed to.

I’ve discussed this in the past, when we talked about the possibility of shed spike protein having the potency to cause symptoms in a person being shed upon. You can refresh yourself with the discussion in the following post and other linked posts here.

Or this one…..

But if you go a bit too far and think that maybe they’re putting snake venom in the water supply, take a look here…..

How much exposure to pathogenic protein is allowable? That is a HUGE question – and between the extremes of total neglect and total fear, lies something called “exposure and immunity”. Including “natural immunity”. We’ll return to that topic later.


Shedding of Vaccines

In between the shedding of intact viruses, and the shedding of viral proteins, lies an intermediate possibility – the shedding of what in nature are called “virus-like particles”, or what in medicine are called “lipid nanoparticles”.

These are mRNA or DNA enclosed in something like a lipid nanoparticle, or the outer shell of a different virus.

These are, bluntly, mRNA vaccines.

In terms of both danger and safety, lipid nanoparticle vaccines are intermediate between live viral vaccines (always dangerous, IMO) and protein vaccines (least dangerous, IMO). Why is this? Well, bluntly, viruses propagate as a chain reaction, and have very little control over outcome. In contrast, a metered amount of a dead protein has great control over the outcome. mRNA vaccines are in between. They don’t reproduce, but they do create a greater but unpredictable amount of viral protein.

Pierre Kory has a very nice article about vaccine shedding, which I invite you to read.

LINK: Shedding of COVID mRNA Vaccines

By the time you finish that, you will understand that there is some need to address this issue now.

As a bit of an aside, you should note that Cory is AGAINST the use of nicotine patches for treatment of spike protein toxicosis, believing (as I do) that it probably has far more risks than benefits. This is highly relevant for DePat’s case.


Technical Approaches to Prevention of Shedding Injury

It is my belief that any good method to deal with both mRNA vaccine shedding and corresponding protein shedding should have the following characteristics.

  • Prevention is preferred to treatment
  • Treatment can be separate from prevention
  • Earlier is better for both prevention and treatment
  • Vaccine is more dangerous than protein, and is thus a priority

The final point needs some explanation.

While the protein can be dangerous at high enough levels, one of the greatest dangers of the vaccine is that it produces large quantities of the protein, and is thus automatically orders of magnitude more dangerous than the protein alone. This is not even considering the dangers of the mRNA technology itself.

Destroy the mRNA vaccine, and there is no protein made, nor any mRNA mechanism allowed to function badly.

Thus, targeting the shed vaccine FIRST makes sense.

THAT makes things easy, because the vaccine can be destroyed easily, provided that it has not yet entered the body.

The mRNA vaccines utilize lipid nanoparticles (a.k.a. liposomes) to enter cells. While these little particles are exceedingly dangerous at a cellular level, they have an intrinsic weakness – their easy destructibility by surfactants – meaning soaps and other cleaning agents.

I posed a research question to Grok, regarding this approach, and got a VERY satisfactory answer.


THE QUESTION

Grok, please give me a list of substances (ranging from specific chemical compounds to branded products) that are known to rapidly disrupt, break up, absorb, and/or inactivate liposomes, including liposomes that are referred to in the mainstream press as “lipid nanoparticles”. I am interested in both surface treatments (cleaning agents, topical medicines, skin washes, soaps, lotions, etc.) as well as things which can be taken internally (oral or injectable), as medicines, that are more specific for disrupting liposomes in the bloodstream, for example as an antidote to an inappropriately administered lipid nanoparticle vaccine, e.g., given mistakenly to an allergic patient.


THE ANSWER

BEGIN GROK

Surfactants/detergents (most effective and commonly documented disruptors of liposomes and lipid nanoparticles/LNPs), organic solvents, cyclodextrins, and certain other agents can solubilize or destabilize lipid bilayers. These work primarily by intercalating into the bilayer, extracting lipids/cholesterol, forming mixed micelles, or increasing permeability/leakage until the vesicle structure collapses. Effects are concentration-, composition-, and condition-dependent (lipid type, cholesterol content, PEG coating, temperature, pH, etc.). LNPs used in mRNA vaccines share similar phospholipid/cholesterol/PEG-lipid components and are susceptible in vitro to the same classes of agents. pubs.acs.org +2

There is no established, safe, specific medical antidote that rapidly and selectively disrupts circulating LNPs (e.g., after mistaken administration of an mRNA vaccine to an allergic patient). LNPs are designed to be temporary and are cleared primarily via the mononuclear phagocyte system (liver/spleen), with natural degradation of the lipids. Systemic attempts to force rapid disruption with the agents below would generally be highly toxic (hemolysis, cell membrane damage, organ injury) and are not clinically used or recommended for this purpose. Allergic/anaphylactic reactions are managed with standard emergency care (epinephrine, antihistamines, corticosteroids, supportive measures), not LNP disruption.

Surface treatments / topical / cleaning agentsThese are relevant for cleaning residues, skin washes, or external inactivation:

  • Anionic, nonionic, and other surfactants/detergents: Sodium dodecyl sulfate (SDS/SLS), Triton X-100, Tween 20 (polysorbate 20), Brij surfactants, Zwittergent 3-14, quaternary ammonium compounds, and commercial soaps/detergents containing these. They saturate bilayers then convert liposomes/LNPs into mixed micelles. Used in lab assays (e.g., RiboGreen for mRNA release from LNPs) and industrial cleaning of LNP residues. Alkaline formulated detergents (e.g., potassium hydroxide-based) are effective for equipment cleaning of LNP residues at elevated temperature/contact time. pharmtech.com +2
  • Bile salts (sodium cholate, deoxycholate, taurocholate, etc.): Strong solubilizers of phospholipid bilayers; well-studied for vesicle-to-micelle transitions. Present in some digestive/intestinal contexts and used experimentally.
  • Alcohols and organic solvents: Ethanol, isopropanol, methanol (typically high concentrations). Disrupt hydrophobic interactions; improve solubility of lipids for cleaning but raise flammability/handling issues. pharmtech.com
  • Cyclodextrins (especially methylated or randomly methylated β-cyclodextrin / RAMEB / DMe-β-CD, and to varying degrees α-, β-, HP-β-CD): Extract cholesterol and phospholipids from membranes, increasing permeability, leakage, or causing collapse at sufficient concentrations. Effects depend on CD type, dose, and membrane cholesterol content. link.springer.com +2
  • Other noted factors: High concentrations of certain kosmotropic salts (e.g., ammonium sulfate) can aggregate/precipitate PEGylated liposomes; extreme pH, heat, or oxidation can destabilize; some nanoparticles or polymers can tear or fragment membranes under specific conditions.

Branded/consumer products that contain the above (many soaps, dish detergents, hand washes, some lotions or topical cleansers with surfactants/alcohols) can disrupt lipid structures on surfaces. Efficacy varies widely with formulation and contact conditions.

Internal (oral or injectable) agents

  • The same surfactants, bile salts, solvents, and high-dose cyclodextrins that work in vitro or on surfaces are generally not safe or selective for bloodstream use against LNPs. They disrupt host cell membranes (including red blood cells) at effective concentrations.
  • Bile salts occur physiologically in the intestine and can destabilize orally administered liposomes, but systemic (bloodstream) levels for intentional LNP disruption are not a therapeutic approach.
  • Cyclodextrins have pharmaceutical uses (e.g., solubilizing agents) and can interact with membranes, but high systemic doses for rapid LNP inactivation are not established as safe or effective antidotes and carry risks.
  • No specific medicines or injectables are approved or routinely described as LNP-disrupting antidotes for vaccine mishaps. Research on LNP fate focuses on clearance, protein corona, MPS uptake, and formulation stability rather than forced rapid inactivation in blood. nature.com

Important caveats: Literature on disruption is largely from in vitro biophysics, pharmaceutical formulation/stability studies, cleaning validation, or drug-delivery research—not clinical antidote development for circulating LNPs. “Rapid” disruption typically requires relatively high local concentrations of surfactant relative to lipid. PEG coatings or cholesterol content can modulate stability. Self-experimentation or off-label use of detergents, solvents, or high-dose agents internally is dangerous and not supported.

For any real-world allergic reaction or medical concern involving a vaccine or LNP product, seek immediate professional medical care; do not attempt chemical disruption. If this is related to laboratory work, cleaning protocols, or formulation science, consult primary literature or specialists for concentration- and condition-specific details.

END GROK


Let me translate all of that.

As long as the shed vaccine is still on the surface of your skin, on clothing, on a mask, or on a surface in your house, the vaccine can be destroyed by all sorts of cleaning products, including surfactants, soaps of all kinds, alcohols, oxidizing agents, bile salts, cyclodextrins, and probably anything useful for cleaning.

Further, any lotions or surface treatments which do not aid in skin penetration (like DMSO), but which do sweep things away from direct contact with your cells, are likely to be helpful in delaying, dissolving, and degrading lipid nanoparticles. Imagine spilled chemical on your skin – it’s the same principle. Diluting the vaccine and/or washing it off make sense.

It is a much different story once a lipid nanoparticle vaccine is inside you – be that from prolonged skin contact, breathing, swallowing, or any other route into your body (like the mRNA jab). None of these things work, once the vaccine is inside you, or in the bloodstream. In fact, these cleaning agents are just as dangerous to your internal cellular machinery (lipid-coated droplets) as they are to the lipid nanoparticles. However, as long as the shed vaccine doesn’t get into your bloodstream (a lower probability than a surface reaction), you don’t have to worry as much about that, as about vaccine damage to skin or mucus membranes where shed vaccine made contact.

Thus, the best time to fight shedding, IMO, is soon after contact. Washing, application of lotions or alcohols, etc., should inactivate shed vaccine. Washing away or denaturing shed protein is also likely to work at the same time.

Again, it is important to remember is that systemic problems from shedding are much less likely than surface problems.


A Realistic Program Against Shedding

This is my opinion. Others may differ. That’s OK. I am just offering my perspective. YMMV.

My first concern remains shedding of virus.

If I am not accepting the trade-offs of the vaccine itself, then my protection is my immune system. My immune system has worked very nicely over the years, against colds, flu, and flu-like illnesses, including all forms of COVID as well as non-COVID coronaviruses. There are appropriately long gaps between infections, and the infections (except for OG Wuhan) have not been debilitating, indicating a functioning immune system.

My immune system is always supplemented with plenty of vitamin D, because vitamin D levels are extremely highly correlated with immunity to viruses. The relationship is stark, and backed by the strongest science. Rates of viral infections almost disappear at high serum levels of vitamin D. There are probable mechanisms for this, but I literally don’t care what they are. Without knowing the causation, the correlation still works. I cannot recommend vitamin D enough. You need to be supplementing it, and maintaining maximum exposure to sunlight. Better still, a measurement of serum levels, but it’s not cheap and your doctor likely won’t recommend it.

Doesn’t matter. Supplementation is cheap and easy and not dangerous, so why not just make sure you are taking a few thousand IUs daily? Just do it. When you notice an appropriately long time between colds and flu, you know you’re taking enough.

Likewise, I make sure that I am not deficient in any vitamin or mineral. Vitamin C, magnesium, selenium and zinc are very important.

However, THIS is even more important.

Avoiding crowded events is critical to reducing exposure to shed viruses. I can link almost every case of influenza or coronavirus infection in recent years to a specific event where there were lots of people crowded together.

In other words, shedding. Viral shedding. As in, viral shedding by people in close proximity.

Thus, avoid crowded public events, particularly in the wintertime, when viruses are maximally spread.

After viral shedding, my next concern is vaccine shedding.

IMO casual vaccine shedding from strangers in momentary close proximity, but not direct physical contact, is far, far less of a problem than living with a vaxxed person for that week after vaccination. Even worse, sleeping with that person who just had a vax.

You should note that my concerns here are EXACTLY what the pharmaceutical industry is concerned about in vaccine trials. That includes live virus AND gene therapy products (even if they don’t call them gene therapy products).

My recommendation is to avoid close contact with vaxxed people for at least 2 days after vaccination, and better a full week. Two weeks should be more than enough, always.

Why? Because the vaccine itself degrades. Even if a person take the vaccine, and shows all sorts of disease symptoms for weeks if not months (please pray for them if this is the case) due to vax-initiated protein production that won’t shut off, they are unable to transmit the vaccine to you, because it is no longer there. The vaccine is degraded, but protein production may still be running.

What about shed vaccine when we can’t avoid being around an individual?

This is when to use soaps, alcohol-based gels, and other skin products. This is when to wash your hands after that oily, wet handshake from some just-jabbed joker, sweating profusely due to their mRNA jab. This is when to stand back from people who can’t “say it” without the need to “spray it”. And note that all of this works even better for VIRUS.

IMO, the vaccine is a far greater danger to you, than the protein these poor victims are now producing. YOU don’t want to be inappropriately producing the protein.

And HERE is where my opinion is likely to differ with yours.

My final concern, about exposure to environmental viral protein, is largely not a concern.

Why? Because this is the natural way in which we build immunity.

Even against a bioweapon. I repeat. Even against a bioweapon – as either a virus or a vaccine.

I literally don’t care if the neighbor sheds small amounts of spike protein or flu proteins on me, because THAT is the vaccination that I prefer – the one for which I am designed. Likewise, I am unconcerned with exposure to dead virus, because THAT is basically how we are naturally prepared for exposure to live virus.

Do I want to inject a protein or dead virus vaccine into me? Maybe – but more likely not. I am now very cautious about vaccines, given that I have lost much trust in the current “vaccine cult” in science. I still trust God and His natural evolutionary reality, however, so I am far more likely to simply trust a combination of pre-exposure of my healthy immune system to proteins, followed by full natural immunity from a well-tolerated episode of the disease.

Rabies? That’s a different story. I’ll take the vaxx, as long as it’s not mRNA. I’ve already done so, once before. I would ONLY take an mRNA rabies vaccine if the animal was confirmed to be rabid, because then it’s a “lesser of two confirmed evils” situation.

I am not going to get pregnant any time soon, and I’ve already had COVID and influenza several times each, so I’m not terribly concerned about exposure to proteins from new variants. In fact, I am at the point of “keeping up” with the latest versions.

SO – some jabbie wants to expose me to the latest spike protein in a non-infective way? Please! Not a problem. Go right ahead. Flu proteins? Be my guest. But I won’t let them expose me to the Soviet Trabant two-stroke mRNA vaccine which I very intentionally decided NOT to take.

And again, my final point. Even if the vaccine AND the protein it produces are “bioweapons” – guess what? I want to be immune to it. I want my system to adapt to its presence. I want natural immunity to all this shit – whether it’s purely “old natural” or “the new natural” that includes stupid human gain-of-function scientific error.

Do you see what I’m saying? GOD has this situation – ALREADY. Let go and let God – just do it at the right time and place.

I hope this helps. If you have questions, feel free to ask.

W

And remember…….

Until victory, have faith!

And trust the big plan, too!

And as always….

ENJOY THE SHOW

W


mRNA Vaccines – A Movie to Refresh Your Memory

I will be hitting VERY HARD on the topic of mRNA vaccines in general, and the mRNA flu shot mFlusiva in particular, over the next few weeks.

I will be refreshing your memories to get you all back into FIGHTING SHAPE.

To begin with, I strongly suggest watching this 1 HOUR movie about mRNA vaccines. The main reason is that it will AWAKEN your dormant memories of the world under COVID. Automatic brain boost for our purposes.

I also think it is very important to see interviews with actual vaccine-injured people.

This movie will show you the reality of vaccine injury.

Thank you for your attention to this matter.

W

THE MOVIE:

Chapters:

00:00 Intro
02:53 Surgeon Joel Wallskog’s health issues
06:21 Operation Warp Speed initiative
06:38 Former CDC Director on mRNA vaccines
07:35 Regulators’ safety assessment
08:09 Calls to pause mRNA vaccines
09:32 mRNA researcher Robert Malone
12:56 Pathologist Ryan Cole on COVID vaccination
14:14 Cardiologist Aseem Malhotra on heart health
14:37 Cardiologist Peter McCullough on side effects
17:28 Scientist Jessica Rose on vaccine concerns
18:41 Critical care specialist Paul Marik on patient community
21:17 Explaining mRNA
23:45 How mRNA vaccines work
27:06 Spike protein and possible effects
30:57 Pathologist Arne Burkhardt’s biopsy findings
32:49 Health agencies’ safety stance
33:38 Vaccination in pregnancy and children
34:22 Artist Jessica Sutta’s health issues
39:03 Future uses of mRNA technology
42:55 Tobie Vergara’s health issues
45:12 History of mRNA vaccines
46:44 Modified mRNA technology
48:40 mRNA research status in 2017
49:07 Toxicity concerns in 2017
49:33 Progress in mRNA technology
49:50 mRNA vaccines during the pandemic
55:41 Support for post-vaccination syndrome
57:06 Doctors offering assistance
Sources, studies, timecodes: https://docs.google.com/spreadsheets/…

Part of why I wanted you to see


KMAG DAILY THREAD 20260812 Thyroid and Iodine

Site rules stolen from our good friend PAVACA

There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s post for any AI-generated content. To the best of her knowledge and belief, there is none. If readers wish to post any AI-generated content in the discussion thread for today’s post, they must cite their source. Thank you.

Do not forget to LABEL AI articles video and such. Also for some reason the paragraphs marked as quotes in the draft are showing as plain text in the preview although the italics seems to be there. Type size and bold are also no longer under my control. I really do hate Word piss!


I first want to point out a very good discussion over at ChiefIO that clued me in on how important iodine is.


Bromine, Iodine, Prostate and Breast Cancer – 23 June 2015 
by E.M.Smith

…it [bromine] is also in your food. Deliberately added, despite there being zero use for it biologically and despite it being a known toxin. (This is just the element I’m talking about now, not the hydrocarbon compounds). It is used in bromated flour in commercial bread (makes a smoother texture) and as bromated oil in sodas (especially lemon lime / Mountain Dew types) to carry flavors. So that sandwich and soft drink at the fast food place is loading you up with Bromine…

Iodine Levels and Cancer Risk

Iodine levels have significantly dropped due to bromine exposure; declining consumption of iodized salt, eggs, fish, and sea vegetables; and soil depletion. In the U.S. population, there was a 50 percent reduction in urinary iodine excretion between 1970 and 1990.
..


Fast foods use plain salt not iodized salt so if most of our salt is coming in the processed food then we use less iodized table salt when we don’t go to the effort to cook from scratch. As a result the iodine consumption in the USA has declined.


Iodine Content of Fast Foods Contributes Little to Iodine Levels in the Body

April 28, 2010 (Boston, Massachusetts) — Only 1 major fast food restaurant — Burger King — consistently uses iodized salt in food preparation, a new study finds. However, the use of iodized salt makes very little difference in levels of urinary iodine among consumers, because iodine levels are generally low in most fast foods, with the exception of some milk and fish products. The findings of the study were presented here at the American Association of Clinical Endocrinologists (AACE) 19th Annual Meeting…

“There has been a decrease in dietary iodine content, compared with 20 years ago,” Dr. Lee told Medscape Diabetes & Endocrinology. Although there is currently no iodine deficiency in the general population in the United States, NHANES III data show a decrease in median urinary iodine content, from 320 μg/L to 145 μg/L, compared with NHANES I findings.

A median urine iodine, μg/L under 100 means Iodine deficiency according to the World Health Organization (WHO)/United Nations Children’s Fund (UNICEF)/International Council for Control of Iodine Deficiency Disorders (ICCIDD)….

Iodine Deficiency — Medscape, Updated: Dec 12, 2024 

Changes in US iodine intake

In the early 1900s, the Great Lakes, Appalachian, and northwestern regions of the United States were endemic regions for IDD, but since the iodization of salt and other foods in the 1920s, dietary iodine levels generally have been adequate. However, sustaining these iodization programs has become a concern.

Data collected in the United States by National Health and Nutrition Examination Survey I (NHANES I) for the years 1971-1974 showed that the median urinary iodine level was 320 mcg/L, reflecting adequate dietary iodine intake. [11] However, by the time of NHANES III (1988-1994), the median urinary iodine value had fallen to 145 mcg/L.

The reduction in US dietary iodine intake since the 1970s has likely been the result of the removal of iodate conditioners in store-bought breads, widely publicized recommendations for reduced salt and egg intake for blood pressure and cholesterol control, the increasing use of noniodized salt in manufactured or premade convenience foods, decreased iodine supplementation of cattle feed, poor education about the medical necessity of using iodized salt, and reduction in the number of meals made at home. [11, 12, 13]

The NHANES surveys of 2001-2002, 2005-2006, 2007-2008, and 2009-2010 showed that US dietary iodine intake has stabilized. [12, 13] Although the most recent NHANES survey reveals adequate iodine intake in the general US population, certain groups have an insufficient intake of iodine, such as pregnant women, who were found to have a median urinary iodine concentration of 125 mcg/L. [14]…


The “bottom line” is that we need about 25 times our present iodine intake here in the USA to have low cancer rates (as the Japanese comparison shows) but instead are getting higher than normal loads of bromine, that competes with our already low iodine levels and causes functional deficit, even when clinically acceptable (if minimal) levels exist. We need to get the Bromine out, and increase our Iodine status.

E. M. Smith (ChiefIO)

sabretoothed pointed to this article: Deiodinases: Understanding Local Control of Thyroid Hormones

…The inflammatory cytokines IL-1, Il-6, C-reactive protein (CRP), and TNF-alpha will significantly decrease D1 activity and reduce tissue T3 levels (105-113). Any person with an inflammatory condition — including physical or emotional stress (243-248), obesity (248-252), diabetes (248,249,253), depression (254-257), menopause (surgical or natural) (258), heart disease (248,259,260), autoimmune disease (lupus, Hashimoto’s, multiple sclerosis, arthritis, etc) (114,115,164,265), injury (266), chronic infection (261,262) or cancer (267-269) — will have a decreased T4 to T3 conversion in the body and a relative tissue hypothyroidism. The inflammatory cytokines will, however, increase the activity of D2 and suppress the TSH despite reduced peripheral T3 levels; again, making a normal TSH an unreliable indicator of normal tissue thyroid levels (105-113)…

There is a lot more if you are interested in how the thyroid works.

….

I was very surprised to find when I suggested using iodized salt to a neighbor, she considered it to be POISON! WHAAaa?? HUH?? After doing research for this article I now know why.

McGill University has a very nice write up of the history of iodine but the most interesting is the article by Orthomolecular Medicine News Service, June 12, 2017

The Need for Iodine Supplementation.


The entire article is excellent but this section is of great interest since it shows how Big Pharma uses poor science. Originally I was going to put this article at the end but I think it is too important to place it where it might be over looked. Oh and Yandex AI?? It says:

…In the 1920s and 1930s, medicinal treatments, x-rays, and iodine were all used to treat thyroid conditions. In the late 1950s, synthetic thyroid medications became available.

👉Today, synthetic forms of thyroxine are some of the most widely prescribed medications.


Imagine that! Now on to the article

History of iodine usage and “iodophobia”

This subject has been covered in detail by Dr. Guy E. Abraham (8,9,10). The iodine element was discovered in 1811 by B. Courtois. In 1850-53 A. Chatin noted that goiter and cretinism are rare in geological zones rich in iodine and frequent where iodine is in short supply, and that goiter can be prevented by iodine supplementation. In 1895 E. Baumann proposed that iodine is the active element in the thyroid gland.

By the time Bauman identified large concentrations of iodine in the thyroid gland in 1895, pharmaceutical and apothecary preparations containing iodine, excluding thyroid extracts, were widely used as a panacea.

To quote Kelley: (11) “The variety of diseases for which iodine was prescribed in the early years is astonishing – paralysis, chorea, scrofula, lacrimal fistula, deafness, distortions of the spine, hip-joint disease, syphilis, acute inflammation, gout, gangrene, dropsy, carbuncles, whitlow, chilblains, burns, scalds, lupus, croup, catarrh, asthma, ulcers, and bronchitis – to mention only a few. Indeed, tincture of iodine, iodoform, or one of the iodides, was applied to almost every case that resisted the ordinary routine of practice; and between 1820 and 1840 there appeared a remarkable series of essays and monographs testifying to the extraordinary benefits to be achieved by this new and potent remedy.”

Unfortunately, these monographs have virtually disappeared from US medical libraries. In the mid-1800’s, iodine treatments of some diseases called for ingestion of gram (1,000 mg) amounts per day. However, most treatments were from 5 to 50 mg daily. The recommended daily amount of iodine by Dr. G. E. Abraham is 0.1-0.3 ml Lugol containing 12.5-37.5 mg elemental iodine. This is the amount of iodine needed for whole body sufficiency, based on a recently reported iodine/iodide-loading test (12). Thyroid gland sufficiency for iodide is achieved with a lower dose.

The first iodophobic authority emerged in early 1900’s. Prof. T. Kochler reported that he suffered from overactive thyroid following ingestion of iodide (just a single individual case, not a statistical research study!) Despite this, the number of applications grew. In an International Index published in 1956, and devoted exclusively to iodine pharmaceuticals, no less than 1,700 approved iodine-containing products were listed. In 1948 Wolff and Chaikoff published that a serum inorganic iodide level at a concentration of 1 µM blocks (one micromolar) the synthesis of thyroid hormones, resulting in hypothyroidism and goiter in rats. But this conclusion was erroneous as they even did not measure thyroid hormones in the rats studied, and of course, hypothyroidism and goiter were not observed in those rats. Many organic forms of iodinated drugs were quite poisonous. Unfortunately, medical establishment did not make a distinction between organic and inorganic forms of iodine, and iodophobia became more popular.

Decades ago, iodine was added to bread so that one slice contained 150 mcg of iodine (the current recommended daily allowance). In the 1980s, bromine replaced iodine in bread. Since bromide is an antagonist to iodine (it is goitrogenic), it worsened iodine deficiency in the USA. Moreover, a big push to remove salt from our diet (the only grocery item still supplemented with iodine) exacerbated the problem. The only developed nation that resisted iodophobia is Japan, statistically the healthiest and longest living nation on the planet. Their average daily consumption of iodine is around 5 mg, with various reports ranging from 1 to 18 mg. In a study of reported daily iodine intake versus total number of clinical symptoms, an intake of approximately 1 mg per day correlated with the lowest number of reported symptoms, that is, the highest level of health (13). Recent popularization of bromides in our food supplies likely increased this amount.

According to Dr. Abraham, (14) “proper amounts of iodine in the food supply should be considered one of a nation’s greatest assets. Removing iodine from the food supply is a major mistake. Supplying a daily intake of iodine sufficient for the whole body (100-400 times the RDA) gives protection against goitrogens and radioactive iodine/iodide fallout; improves immune functions, resulting in an adequate defense system against infection; decreases singlet oxygen formation which is the major cause of oxidative damage to DNA and macromolecules, resulting in an anticarcinogenic effect in every organ; results in a detoxifying effect by increasing urinary excretion of the toxic metals lead, mercury, cadmium, and aluminum, as well as the goitrogens fluoride and bromide; normalizes hormone receptor functions resulting in improved response to thyroid hormones both endogenous and exogenous; and results in better control of blood sugar in diabetic patients; stabilizes cardiac rhythm, obviating the need for the toxic sustained release form of iodine, amiodarone; and normalizes blood pressure without medication in hypertensive patients. Iodine deficiency is the major cause of cognitive impairment, worldwide.”


Interestingly much of the discussion at Chiefio is now gone. There was an excellent video tying intelligence in children to iodine.

 Sluggish thyroid can mean obesity.
http://www.tahomaclinicblog.com/are-you-running-on-empty-thyroid-deficiency-syndrome/

The site still exists as an eye clinic but the article is gone despite the wayback capturing it 92 times.

However there is now this article.

Weight Loss – Dr. Brian Foley chiropractor

Hidden Danger: Stubborn Belly Fat Syndrome

Being overweight has become an epidemic in America. The Standard American Diet (SAD) has caused many of us to be overweight due to the fact that most of our food has been genetically altered and chemicals added. Unfortunately for us it is not real food anymore it has lost most of its nutritional value…

The glands and organs that affect our body shape and where we accumulate fat are the thyroid, adrenals, ovaries and liver. There are only four reasons a person cannot lose weight or cannot keep weight off. They are 1.Sluggish thyroid; 2. Liver dysfunction, 3. Ovaries (hormones out of balance). 4.Adrenal fatigue. Each one of these has their own set of symptoms and area of the body where the weight (fat) will accumulate.

Sluggish Thyroid

A whole book could be written on the “sluggish thyroid” and many have.  We are just going to touch on some of the basic facts of the thyroid…

The thyroid regulates the rate at which the body burns food and controls the production of certain body tissues such as nails and hair. The thyroid gland also regulates body temperature, breakdown of carbohydrates, mental clarity and well-being, energy levels and even vitamin absorption, cholesterol levels, hair texture, nail strength, softness or dryness of the skin and sex drive are all greatly influenced by the thyroid. Metabolism refers to the rate or speed at which the body breaks down food and changes it into living tissue and energy. Metabolism is also defined as the release of energy left, (burning of fat) from the cells. The first major consequence of a sluggish thyroid is a slow metabolism…

Interesting illustration if true.

History of Iodine via YANDEX AI

The history of iodine and the thyroid gland is closely linked. In 1811, a French chemist, Bernard Courtois, discovered iodine by burning seaweed with sulfuric acid. Five years later, iodine was used to treat endemic goiter in England. 2,5

By the early 1900s, it was recognized that the incidence of goiter varied geographically and that the critical feature was the iodine content of the food consumed. Crops grown near the sea had sufficient iodine, but people who subsisted on food grown inland had a high incidence of goiter. 1

In 1895, E. Baumann proposed that iodine is the active element in the thyroid gland. By the time Baumann identified large concentrations of iodine in the thyroid gland, pharmaceutical and apothecary preparations containing iodine, excluding thyroid extracts, were widely used as a panacea. 3

In 1914, Calvin Kendall isolated thyroxin, a thyroid hormone that had four iodine atoms incorporated into its molecular structure. This hormone regulates metabolism, as well as kidney and brain function. 15

In the 1920s and 1930s, medicinal treatments, x-rays, and iodine were all used to treat thyroid conditions. In the late 1950s, synthetic thyroid medications became available. 5

Today, synthetic forms of thyroxine are some of the most widely prescribed medications. 5

REFERENCES:

#1. What Is The Role of Iodine in Thyroid Function – McGill University

#2. Nuclear Medicine and the Thyroid Gland: A Retrospective Review – Tech.Snmjournals.org

#3. The Need for Iodine Supplementation – Orthomolecular Medicine

#4. Iodine’s Role in Thyroid Health – Verywellhealth.com

#5. The History of Thyroid Disorders – Paloma Health

The Recommended Dietary Allowance (RDA) for Iodine is 150 mcg/day. As we learned with boron, this is minimum not optimum.

“Today, synthetic forms of thyroxine are some of the most widely prescribed medications.” Now isn’t that interesting. Is this another Problem – Reaction – Solution big Pharma money maker? After all store brand Iodized salt is less than a buck a pound at Walmart with 1/4 tsp = 67mcg or 45% min requirement of iodine.

Himalayan Pink Salt is $6.53 for a 1lb bag ( negligible amounts of iodine) and Redmond Real Salt is better than Himalayan with a1/4 teaspoon serving providing approximately 18–23 micrograms (mcg) of iodine, which is only about 10–15% according to Brave AI.

Redmond Real Salt: Does Real Salt Have the Iodine We Need?

Article at a Glance:

  • Iodized salt was developed during World War I to fix widespread iodine deficiencies.
  • The iodine in iodized salt isn’t as bioavailable as the iodine in food.
  • Iodized salt is heavily processed and all the healthy minerals (besides sodium and chloride) are removed.
  • All salt, including Real Salt, contains some naturally occurring iodine, but not enough to meet your RDA.
  • You can easily meet the RDA of iodine through iodine-rich foods.


Squid??? How about smoke Hake, available thru Walmart on-line?


Unless you are near the coast, most Americans are going to eat fresh water fish not iodine rich ocean fish. Also after the mercury in fish scare, many people are reluctant to eat ocean fish.
A lab I worked for in the 1980s actually did testing for mercury in fish. (I and everyone else ended up with freezers full of fish.)

Brave AI:

Public concern regarding mercury in fish emerged in the 1950swith the identification of Minamata disease in Japan, where industrial discharge caused methylmercury poisoning in coastal communities and their seafood consumers.

Reference: Mercury in Marine and Oceanic Waters—a Review

The impact of mercury in the environment on human health was found for the first time in relation to the Minamata disease in the 1950s, which caused mass-scale poisoning by methylmercury. It had accumulated in aquatic organisms which were subsequently eaten by humans. A similar case of poisoning by mercury accumulated in fish also took place in Sweden (Zaib et al. 2015).

Apart from spectacular cases of poisoning, the presence of mercury in the environment also affects the human population in a more concealed manner. Every year, Trasande et al. (Trasande et al. 2005) found mercury concentrations exceeding 5.8 μg/L—a level related to IQ loss—in blood samples taken from 316,588–637,233 children. Humans are mainly exposed to methylmercury as a result of their consumption of oceanic fish (Drevnick et al. 2015).


So much for the public getting iodine from ocean based food sources.


“Take a dose of seaweed or burnt sea sponge twice a year!” That was the ancient Chinese remedy for goiter. Almost four thousand years ago Chinese medical writings described the troublesome swelling of the neck we know as goiter and noted the remedy which had somehow been arrived at through trial and error.


McGill University


2013 – Zinc Deficiency Associated with Hypothyroidism: An Overlooked Cause of Severe Alopecia

Abstract

Hypothyroidism is a common and well recognized cause of diffuse hair loss. Zinc and other trace elements such as copper and selenium are required for the synthesis of thyroid hormones, and deficiency of these can result in hypothyroidism. Conversely, thyroid hormones are essential for the absorption of zinc, and hence hypothyroidism can result in acquired zinc deficiency. The hair loss attributed to hypothyroidism may not improve with thyroxine unless zinc supplements are added, as demonstrated in our case.

FWIW, since I can not have salt, I take “Terry Naturally” Tri-Iodine. I noticed when I quit taking it for a time, I had four nails within a week tear at the quick.

KMAG DAILY THREAD 20260805 In honor of Professor Dr. Francis A. Boyle

Site rules stolen from our good friend PAVACA

There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s post for any AI-generated content. To the best of her knowledge and belief, there is none. If readers wish to post any AI-generated content in the discussion thread for today’s post, they must cite their source. Thank you.

Do not forget to LABEL AI articles, video and such.

When I saw Valerie Curren’s comment, I decided to erase my comment full of swear words and post the bits of information I had already gathered from Dr Boyle way back in February 2020. That man saved a lot of lives! Unfortunately he is another who ‘conveniently died’ just like Kary Mullis (PCR test inventor) and Nobel Prize winning French virologist Luc Montagnier.

Dr Luc Montagnier contended that “it is the vaccination that is creating the variants.” They Are Not Vaccines, They are Poisons”: Outspoken Nobel Prize Winner Virologist Luc Montagnier Dies Before Attending Grand Jury Proceeding for Crimes Against Humanity.


Valerie Curren(@valeriecurren)  August 4, 2026

Valerie Anne Smith
@ValerieAnne1970
·
Aug 2
Just days after Prof. Francis Boyle agreed to testify against Bill Gates & Albert Bourla over the deadly COVID mRNA shots… he was FOUND DEAD.

Boyle authored the U.S. Bioweapons Act & called the mRNA injections ‘Bioweapons & Franken-Shots.’

Where does the Pentagon fit into this?…

Just when you thought you’d heard it all, this resurfaced interview with Prof. Francis Boyle—the man who literally WROTE the 1989 Biological Weapons Anti-Terrorism Act—will leave you speechless.

He states on record that both SARS-CoV-2 and the mRNA injections were DARPA-funded offensive bioweapons programs from the start. Gain-of-function? That was the cover story.

According to Boyle, the real goal was always “lethal yet vaccinate-able” population reduction technology. He names names: UNC, Wuhan, Fauci, Daszak, Baric…the whole club.

He goes further—calls the shots “synthetic biological weapons of mass destruction” because they trigger autoimmune carnage, prion-like misfolding & turbo cancers.

Boyle filed lawsuits, begged Congress & warned the world. Just 20 days after agreeing to testify for the prosecution, he was found dead. The same pattern we’ve seen with dozens of doctors & whistleblowers since 2020. Pure coincidence?

If a man who drafted the actual law defining bioweapons says we just lived through the biggest biowarfare attack in history…why isn’t every news channel screaming this from the rooftops?

The most chilling part? Boyle predicted exactly what we’re seeing now: myocarditis, strokes, infertility & cancers exploding in the injected.

He said the spike protein itself is the weapon & the lipid nanoparticles were engineered to cross the blood-brain barrier. This wasn’t a mistake. It was a military-grade kill vector dressed up as “public health.”

It is past time for the new Nuremberg-style trials to begin…

Never Forget…

So many still have no idea what Trump already stopped from happening. It wasn’t supposed to end with temporary lockdowns and a vaccine you could refuse. Most people who just found out about the NWO in 2020 will never understand.

…

Brownstone Institute: The CDC Planned Quarantine Camps Nationwide

by Jeffrey A. Tucker   November 7, 2024

No  matter how bad you think Covid policies were, they were intended to be worse. 

Consider the vaccine passports alone. Six cities were locked down to include only the vaccinated in public indoor places. They were New York City, Boston, Chicago, New Orleans, Washington, D.C., and Seattle. The plan was to enforce this with a vaccine passport. It broke. Once the news leaked that the shot didn’t stop infection or transmission, the planners lost public support and the scheme collapsed

It was undoubtedly planned to be permanent and nationwide if not worldwide. Instead, the scheme had to be dialed back.

Features of the CDC’s edicts did incredible damage. It imposed the rent moratorium. It decreed the ridiculous “six feet of distance” and mask mandates. It forced Plexiglas as the interface for commercial transactions. It implied that mail-in balloting must be the norm, which probably flipped the election. It delayed the reopening as long as possible. It was sadistic. 

Even with all that, worse was planned. On July 26, 2020, with the George Floyd riots having finally settled down, the CDC issued a plan for establishing nationwide quarantine camps. 

People were to be isolated, given only food and some cleaning supplies. They would be banned from participating in any religious services. The plan included contingencies for preventing suicide. There were no provisions made for any legal appeals or even the right to legal counsel. 

The plan’s authors were unnamed but included 26 footnotes. It was completely official. The document was only removed on about March 26, 2023. During the entire intervening time, the plan survived on the CDC’s public site with little to no public notice or controversy. 

It was called “Interim Operational Considerations for Implementing the Shielding Approach to Prevent COVID-19 Infections in Humanitarian Settings.” …

….

From my old notes with some modifications:

Professor Dr. Francis A. Boyle has been sounding the alarm so I am going to look at the two papers he points us to and the people involved. Professor Dr. Francis A. Boyle is ”… a leading American expert international law; responsible for drafting the Biological Weapons Anti-terrorism Act of 89…”

So he had a major hand in developing the following:

Biological Weapons Anti-Terrorism Act of 1989 “was passed into law in 1990. It provided for the implementation of the Biological Weapons Convention as well as criminal penalties for violation of its provisions. The law was amended in 1996 and has been used to prosecute several individuals.” — https://military.wikia.org/wiki/Biological_Weapons_Anti-Terrorism_Act_of_1989

Biological Weapons Convention “was the first multilateral disarmament treaty banning the production of an entire category of weapons.  It currently commits the 170 states which are party to it to prohibit the development, production, and stockpiling of biological and toxin weapons. However, the absence of any formal verification regime to monitor compliance has limited the effectiveness of the Convention. As of April 2013, an additional 10 states have signed the BWC but have yet to ratify the treaty.” — https://military.wikia.org/wiki/Biological_Weapons_Convention

CHINA is a signatory as is the USA. (Now we know why there were so many labs set-up outside of the USA.)

This is an interview of Dr Boyle by Alex Jones. Luckily there is a transcript at Natural News on 02/20/2020 by Mike Adams

Full transcript of “smoking gun” bombshell interview: Prof. Francis Boyle exposes the bioweapons origins of the CoVid-19 coronavirus

What follows is one of the most important interviews of the year. Biological warfare expert Prof. Francis Boyle appeared as a guest with Alex Jones on the Alex Jones Show, sharing his “smoking gun” findings about the coronavirus being engineered as a weapon that’s designed, “for efficient spreading in the human population,” according to one of the science papers he references.

We confirmed Prof. Boyle’s findings by purchasing the full PDF of that paper and reviewing it in a detailed article we posted yesterday at this link.

That paper describes the CoVid-19 novel coronavirus as possessing unique “gain-of-function” properties that make it the perfect bioweapon, while confirming these new properties were from artificial origins, not natural viral evolution. (In other words, it was engineered.)

Below, we print the full transcript of the Francis Boyle / Alex Jones interview, along with the video of the full exchange below, via Brighteon.com. (The full show is also posted on Banned.video)


Mike has placed in his BRIGHTEON VIDEOS under the Francis Boyle category not only the initial Francis Boyle / Alex Jones interview (1 hr 15 min), but many, many others. I counted well over 30 InfoWars interviews before giving up. This makes me wonder if those interviews may have played a part in the destruction of InfoWars by the DeepState lawyers. And no I do not like Alex Jones.


From the collection: Covid Shot is a Weapon of Biowarfare – RIP Francis Boyle

[WordPiss will not play Brighteon videos.]

PROFESSOR FRANCIS BOYLE, Author of the US 1989 Biological Weapons and Antiterrorism Act:

“THE PENTAGON is behind the mRNA shots… The Pentagon is both sides of the argument, they developed the weapon [SARSCoV2 virus which caused Covid19] and the alleged vaccine.”

Back in February 2020, I found this second , later interview with Dr Boyle from February 22, 2020.

US Biowarfare Act Author: Studies Confirm Coronavirus Weaponized

This second article has links to the Scientific Papers that Dr Boyle uses as evidence and to this interview (36 minutes):

https://www.youtube.com/watch?v=F_TPjbu4FAE


Of course all of Spiro Skouras Youtube videos have been scrubbed.


But bitchute has them. https://www.bitchute.com/channel/spiro/

https://www.bitchute.com/video/eaARJge7OEhg


OH, and Karma is a BITCH!

I wonder how many clot shots she got?

The Spiro Skouras article also links to this article:

Interview: Author of US BioWeapons Act Believes The WHO & China Are Lying About The Coronavirus

…Professor Boyle believes he has been blackballed by the mainstream media due to blowing the whistle on the Anthrax attacks on the U.S. in the wake of 9/11, stating he believes the Anthrax originated from American BSL-4 (Biosaftey Level 4) labs, which are the highest level of labs that conducts research and development on the most deadly substances known to man…


The first paper Dr Boyle discusses is a French paper . Dr Boyle states they found ‘gain of function’ and ‘ gain of function’ studies are ONLY of use for weaponizing viruses. The Journal Nature, in an editorial refutes this.

CONFIRMED: CoVid-19 coronavirus found to contain unique “gain-of-function” property “for efficient spreading in the human population” … exact quote from science paper just published in Antiviral Research

02/19/2020 // Mike Adams 

The “smoking gun” aspects of this research were brought to light earlier today by Prof. Frances Boyle..

The paper:

The spike glycoprotein of the new coronavirus 2019-nCoV contains a furin-like cleavage site absent in CoV of the same clade

Abstract

In 2019, a new coronavirus (2019-nCoV) infecting Humans has emerged in Wuhan, China. Its genome has been sequenced and the genomic information promptly released. Despite a high similarity with the genome sequence of SARS-CoV and SARS-like CoVs, we identified a peculiar furin-like cleavage site in the Spike protein of the 2019-nCoV, lacking in the other SARS-like CoVs. In this article, we discuss the possible functional consequences of this cleavage site in the viral cycle, pathogenicity and its potential implication in the development of antivirals.

”….we identified a peculiar furin-like cleavage site in the Spike protein of the 2019-nCoV, lacking in the other SARS-like CoVs.….”

That is as close as scientists are going to get to saying this virus does not look natural. They are aware of what happen to the Indians who were made to retract their paper and are not about to step over the politically correct line.

They KNEW the vaccine was deadly. 200 members of Congress were treated with Ivermectin during Covid-19.

The Second paper he discusses is the Baric paper out of University of North Carolina.

This is the nitty gritty of the transcript of the first interview by Alex Jones:


“I think I have the definitive evidence where this came from and it came from the BSL-3 biowarfare lab at the University of North Carolina.”

DR BOYLE:

He then refers to the paper:

A SARS-like cluster of circulating bat coronaviruses shows potential for human emergence.

It was Electronically Published on November 8, 2015

And LOOK who funded it! The National Institutes of Health under Fauci AND the State Key Program for Basic Research Grants from the Chinese Ministry of Science. Fauci not only funded the initial research but indicated interest in funding further research.

Abstract

The emergence of severe acute respiratory syndrome coronavirus (SARS-CoV) and Middle East respiratory syndrome (MERS)-CoV underscores the threat of cross-species transmission events leading to outbreaks in humans. Here we examine the disease potential of a SARS-like virus, SHC014-CoV, which is currently circulating in Chinese horseshoe bat populations. Using the SARS-CoV reverse genetics system, we generated and characterized a chimeric virus expressing the spike of bat coronavirus SHC014 in a mouse-adapted SARS-CoV backbone. The results indicate that group 2b viruses encoding the SHC014 spike in a wild-type backbone can efficiently use multiple orthologs of the SARS receptor human angiotensin converting enzyme II (ACE2), replicate efficiently in primary human airway cells and achieve in vitro titers equivalent to epidemic strains of SARS-CoV.

Additionally, in vivo experiments demonstrate replication of the chimeric virus in mouse lung with notable pathogenesis. Evaluation of available SARS-based immune-therapeutic and prophylactic modalities revealed poor efficacy; both monoclonal antibody and vaccine approaches failed to neutralize and protect from infection with CoVs using the novel spike protein.

On the basis of these findings, we synthetically re-derived an infectious full-length SHC014 recombinant virus and demonstrate robust viral replication both in vitro and in vivo. Our work suggests a potential risk of SARS-CoV re-emergence from viruses currently circulating in bat populations.

Most of us, thanks to PAVACA, are very familiar with the above information, however it was all new in February of 2020 and saved lives. I am not going to try and do a bio of Dr Boyle, I am sure others will do a much better job than I can. I only wish Dr Boyle could have witnessed this.

The Delicious Humiliation of the Man Who Poisoned the World and the Ignominious Death of ‘The Science’.

It Was A Very Good Week for Humanity

What Fauci’s Diary Reveals About America’s Health Care Apparatus

Numerous lines of evidence show Fauci lied to us about the pandemic’s biggest questions — origins, severity, lockdowns, and masks — all of which was just exposed at an explosive hearing.

Rest in well deserved peace Warrior, your job here on earth is done. Others will take it from here.

2026.06.30 Daily Thread: The World According to Trade(Bait)

From John 13:34 (KJV),

A new commandment I give unto you, That ye love one another; as I have loved you, that ye also love one another.

Note: It is a commandment from the Lord Jesus toward the end of his ministry on earth, so it is pretty important to pay attention. It is also consistent with Old Testament scripture instruction, as He always is. We must love one another. That means we pull out all of the stops for the benefit of one another. No holding back, do just as He does for us. That type of love is intentional, it requires action, it requires giving of ourselves even when it us uncomfortable or even painful.

The cause of Christ cannot be advanced without loving one another as He loved us. Take note, America.

For there is no other way, just trust and obey…

Final Health Updates

Since my authoring is winding down, I thought it would be helpful for some on here for me to update the health situations and progress of wifey and I that are connected to past posts. I apologize in advance for the length of this daily, but there is much to discuss. I hope the information proves helpful to you.

Wifey

As some may remember, my rock star wife went through a rough random eye infection upon return from our Fall Frolic the year Helene hit the area in 2024. The infection that caused the corneal ulcer was a small, white blob in one eye and lab tests were inconclusive. A series of antibiotic drops were prescribed and over several months cleared the infection. However, she had serious lingering vision issues and recovery was slow. After healing the infection her vision only returned to 20/60 corrected using her recently prescribed, pre-infection lenses. She had floaters along with cataracts that the ophthalmologist wanted to correct. Wifey was reluctant due to family members who had limited success with the procedure as well as her being allergic to latex, despite assurances from the doc they could adjust. She has minimal trust in the medical community, so that went nowhere fast.

She told the doc she wanted to try some things first and if she could not improve it, she would consent. He agreed (what else could he say?), but to check back in 6-8 months so that the eyes did not decline too far to be of assistance. We could tell he was skeptical. He looked at me and said, “She is one tough lady, isn’t she?” I just nodded affirmatively. However, that is the moment she decided to take my research about the issues and recommendations to heart. God led her to conclude she should go a different way. Some of the supporting information came from sources and linked information on here for which we are very grateful.

Never discount the value of your contributions to readers, my friends.

I posted awhile back that we both were using DMSO eye drops. I have slowed the use in recent months, but for over a year now wifey has continued twice per day applications of a 25% concentration with saline or distilled water while using sterile bottles/droppers. She takes a one week break every couple of months, then restarts. In recent months she has added a high quality castor oil that she lightly rubs on the eyelids at bedtime. She has also participated with me in the parasite cleanse using the IVM/Mebendazole combination last summer and an IVM cleanse in the past couple of months.

I am very happy to report that over that period, her vision returned to its formerly good, pre-infection condition. She is now 20/20 corrected with the same lenses. She does not need distance correction, only for reading. Of course this did not happen through traditional means or medicine.

We utilize a highly competent optometry practice. Our chosen optometrist in the practice and assigned tech were amazed at the results after the comprehensive exam that included extensive imaging this month. The doc knew the condition of the previously affected eye as she helped deal with the original infection before passing the case to the ophthalmologist. The formation of cataracts has actually been stopped in its tracks and may have receded somewhat. She no longer has floaters at all. Her eye health has improved to the point of the highly desired “see you in a year unless you need us” stage. That’s a massive win.

But there is MOAR!

Combined with dietary changes described below and daily walks; there has been an interesting, fantastic development. One day she forgot to bring her eyeglasses when we went grocery shopping. Her vision had improved to the point she simply forgot to wear them. It was a sunny day and she put on some wrap sunglasses that cover the eyeglasses that were in the truck. To cut to the chase, her forever present vertigo/Menere’s Disease symptoms disappeared. As I drove I was quietly shocked and secretly elated. No more jumps, twists and and yelps from the passenger seat when big trucks were near or a car approached from another direction at an intersection. Just calm, peaceful riding for a half hour each way.

As we pulled into our driveway, I mentioned it to her and she smiled. She noticed it as well. Now when we go places she may leave her glasses on or take them off if she detects the problem kicking in. Regardless, the trips are much more relaxed and easier on both of us. She had experienced the car motion induced vertigo issues for decades. At one time it got so bad that as a teenager, Daughter had stopped wanting to go on vacations with us because of the distraction and angst.

Gone. PTL!

Trade’s Results

My eye exam was much improved as well. The supposed early cataract formation of a half dozen years ago that my retina specialist diagnosed actually never formed. The dry form macular degeneration diagnosed over a dozen years ago never actually worsened. The floaters have been gone for some time. I did the DMSO off and on for about 6 months once a day. For me the driver for improvement has primarily been IVM, although I am confident the DMSO assisted to some degree. My vision had not changed over the past three years.

After over a year of experimenting by returning to normal lens, I found that the prism lens prescribed for me a few years ago by the old binocular vision specialist doc who helped Grandson #1 so much, were very beneficial in drawing my weak eye with the alleged worse dry macular degeneration back into more balanced vision. As a result I added the prisms back with the new glasses and am gradually adjusting to them very well.

At about 10 years old parasites of some sort got in my eyes; worse in one than the other. From family history records I learned I was given antibiotic drops that were manufactured by Schering-Plough, which was later acquired by Merck. During that time is when the optometrist determined I also had a “lazy eye” in the worse infected one and gave me exercises to retrain it. Whatever was prescribed did clear the infection, but I never really had normal use of the eye and over time I became strongly one eye dominant. The vision in both eyes remained 20/20, so I really did not know to be tested further. I just knew that as a teenager, my vision in baseball and later as an adult in golf was somewhat negatively affected. This was especially true with poor peripheral vision in one eye and was very apparent in vision tests as I hit middle age.

Based on recent exams I am starting to believe that old binocular vision doc knew what he was talking about when he told me I did not have macular degeneration. My symptoms could appear to be MD to other docs, however, it seems to me it is the aftermath from that parasite caused infection as a child. If it is dry MD, there should be even slow progression of the condition. There has not been. It has been in a stable state for a dozen years.

This probably gives credence to how my vision always becomes much sharper the day after taking IVM and why the floaters and early stage formation of cataracts disappeared after using it and DMSO drops. Improvement in eye performance would not be as likely for a MD sufferer. With no changes in the prescribed lenses for vision in three years, I may be on to something good. Will continue to monitor.

I also used a DMSO/aloe vera concoction described below for a couple of months on two stiff, arthritic fingers on one hand that bugged me for years. The condition is gone – no more stiffness.

I still have a bit of tinnitus in one ear that was left over from the Wuhan. The externally applied DSMO method treatment has not impacted it one way or the other. Chiropractic adjustment cut the ringing back about 50% which has been most appreciated. It appears to be nerve/CNS related in some manner. I have no restrictions in movement, so I can turn my head 90 degrees one way and it reduces. I can turn my head the other way and it slightly increases. Weird. Will keep looking at options for improvement.

Together…

For the record we no longer have the need to use the excellent chiropractor that helped restore our alignment. She did a great job. All is well and being maintained. However, if needed we will not hesitate to return.

Recently, from recommendations of a couple of knowledgeable medical authors, I concocted a DMSO/pure Aloe Vera gel/essential oil blend to use for arthritis and joint inflammation issues. Wifey also has been using the DMSO with castor oil or my concoction for her arthritic hands/fingers as well as surgically repaired knee. There has been strong improvement in flexibility and appearance. My own flexibility in the lumbar region where I have spinal bone spurs has also improved. Will see how it goes long term, I expect it to go well.

Not bad for a couple of seventy somethings. DMSO and IVM work for us, folks, and not just to ward off COVID with IVM. We will continue to use. Add in the benefits of the high quality castor oil.

IVM clearly works on parasites of various types throughout the body. Its use helps the immune system of the body to do its thing. Wifey uses for cleanses only unless she has a respiratory illness coming on. During her cleanses, she gets the yucky bowel movements associated with her sinus drainage as well as the parasite die off and release. She experiences the under the weather symptoms for a few days. Having already gone through that a couple years ago while continuing to use IVM prophylactically, I no longer experience much, if any, side effects.

The cleanses are possibly contributing to wifey’s lack of vertigo along with the eye improvements. IVM has long been prescribed for river blindness. However, there may be another interesting connection. Over twenty years ago she had an allergist test and treat (shots) her allergies on two occasions and covering a period of five years. The shots provided modest benefits overall. However, from the testing we know she is very allergic to candida albicans, a fungal induced yeast, as well as specific molds, tree pollens, etc. Exposure causes her body to go into histamine overload. It added to her vertigo events due to sinus pressure. For years we kept an epipen handy as well as a bottle of Benadryl. A half dozen years ago her every day had an excessive amount of throat clearing from the sinus drainage. At one point she lost her voice from it for about 6 months. The drainage strongly affected her sleep. At times she was just miserable, in a state of just existing and trying to cope daily.

We live in an environment that has high fungal concentrations due to vegetation and climate. It is what it is and she has suffered all of her life from it. That is until the recent IVM related cleanses that also addressed gut health as a side benefit. Poor gut health can also add to the histamine imbalance. The intentional dietary changes of removing sugar, and addressing her eyes dramatically improved her situation. She is now off all antihistamine drugs and just uses Flonase for the pollen after living on Zyrtec D at times. Her condition is not perfect, but is greatly improved. Below are good summaries that I found informative and accurate about candida albicans.

https://shunwaste.com/article/what-environments-can-candida-albicans-grow

https://www.mdpi.com/2309-608X/11/9/622

While still on the subject of eyes, we spoke with the optometry practice staff as patients walked in and out after purchasing bottles of eye vitamins/supplements. We asked and a few buyers and the staff gave rave reviews. The practice did not try to sell it to us. They said they could not keep enough inventory to supply everybody. All three docs and the staff take them. The following is the product,

https://www.macuhealth.com/product/macuhealth-vision-edge-pro-supplement-for-eye-support

Turns out it can be ordered direct from the company or Amazon at the essentially the same price. We have been taking for most of this past month. My December follow up exam will determine any personal progress, however, I have reason to hope for a good outcome.

Which leads to the next bit of news. Wifey and I decided it was time to lose some weight for good. We want to be more active to keep up with the grandkids and for me to teach them the game of golf. It was back to full Keto time for me and modified Keto for her. Her goal was to weigh the same as when we married over 40 years ago. My goal was to get to my baseball playing weight in college. I had to lose a bit more than her as a percentage. We have both succeeded. The difference in our health and energy levels has been nothing short of amazing. I kept the exercise to moderate and never went hungry at all. By keeping it to about 6 lbs. per month my body adjusted well along the way. Again, it was about modifying my nutrition to fit my goals and my gut health; not about a diet.

We also wanted to do this to see the effects it had on our blood tests from our physicals. Cholesterol was creeping up each year with both of us, especially with wifey. Her glucose was nearly 20% above the healthy range to go with blood pressure issues that she has dealt with all of her adult life. Wifey also had the goal of weaning slowly off of Amlodipine and Hydrochlorothiazide. We had zero doubts that the former contributed to her cholesterol trending up through the years; it is a little discussed side effect. When she began taking it her cholesterol also began increasing and never decreased again even when controlling her weight and nutrition. She never has liked the way the meds made her feel, but felt she had no alternative. In a previous daily I stated that we felt traditional medicine had won this battle. It turns out it was only a short term benefit that led to even worse average BP and cholesterol as well as spikes in BP and heart rate.. Which would have eventually led to more Big Pharm solutions that would lead her closer to death.

Turns out there was a way for her to exit the “system” that often destroys. The first step was to stop blindly trusting traditional medicine and the related food pyramid. Do your own research and adapt to your situation. Second was to address the nutrition and get to a healthy weight. Third was addressing her eye issues. The eyes are not only the windows to the soul, they interconnect with all the sensory areas of the body. Fourth was to cleanse the body of parasites and work on related gut health. Gut health is not one size or type fits all. Fifth was to become more fit, get the blood circulating daily. The last was to find the right combo of supplements and vitamins that worked specifically for her as she weaned off Big Pharm.

Bingo. We found that last one in Berberine (NOW brand). Other brands may work as well. The BP fell almost immediately after she started on a one third daily dose of it along with her two prescribed meds. No more spikes at all. In fact her BP fell too far. Several mornings when she got up and tested she would be in low 90/low 50 range. So, she cut the doses of prescribed meds in half. Her BP moderated up to 110-120/65-70 and remained there. This went on for a few months with no troublesome spikes. Then she moved to a two thirds dose of Berberine and went off Amlodipine completely. Her BP and heart rate remained stabilized in the same range and she has continued to have zero troublesome spikes. She plans to dump the half dose of Hydrochlorothiazide soon. She will maintain the prescriptions as a precaution until she is in the clear.

All of that was going on at the same time as the DMSO, IVM, castor oil, weight loss, nutrition changes, fitness walks, and so on. Now she is going off the meds, uses Berberine, takes some multi-protein collagen (Ancient Nutrition brand) in her morning coffee, uses Flonase for allergies, no longer suffers vertigo on car trips, sleeps like a log, and smiles a whole lot more. In addition she takes a multi and recently, the VisionEdge Pro eye vitamins.

Happy wife, happy life. So proud of her resolve and success even if we did need to buy her a new wardrobe. It was not expensive, us old folks are not all that picky.

My supplements have been the collagen, Aubergine recommended Nattokinase along with Serrapeptase, and more recently a third of a dose of Berberine leading up to our blood tests. My plan was to get the blood test results I discuss below and adjust as needed. Through the years I have tried many vitamin combos. Currently I take the eye vitamin daily along with a multi or CoQ10 a couple times per week. I have not been ill for about 15 months after I made changes and did the initial Parasite Cleanse. I take a prophylactic dose of IVM biweekly and additional doses if I detect any respiratory issues. My BP and heart rate are fine and have been all of my life – generally in the 120/70 average with an average resting heart rate of 52. I take no prescription meds and only Flonase for allergies. I hit eject on antihistamines a year ago and could not be happier about it because it tells me the underlying causes for their need are being addressed well.

Our emphasis recently has been on gut health. Dr. Steven Gundry’s research and recommendations are highly credible in our minds. As a result of learning more and with the help of my Keto based nutrition I have been able to reduce lectins, which have been undermining my digestion for decades. Quite simply I did not need all of the fiber my physician as well as gastroenterologist recommended at my last colonoscopy. Scraping the walls of my intestines with more fiber was a bad idea for my gut type. If I had continued I would be in deep doodoo or as worm food.

😄

I was miserable at times and the practice was causing weight gain, bloating and constipation even with drinking large amounts of water. If I continued it would have led to far worse health outcomes. So, I changed in accordance to what I learned along the way and recently tested with Dr. Gundry’s research and information. So far, so good. Life has become much easier to live. Below is a link to one of his books.

Annual Wellness Physicals

After the usual instruction to draw a clock showing 11:10 (yes, the same time every year) and being given three simple words to remember and repeat to the PA later in the exam (one of us always gets “village, kitchen, baby”), the experience went well. We were very pleased with the attitudes of the providers this year. Somebody got through their heads that the patients are the bosses, not them. The real results of COVIDiocy and their patients ire about it may have inspired them to do better. They asked our level of interest in vaccines and tests instead of telling us we needed to do something. It had already been noted in our files about no vaccines. When we passed this time, there was no questioning of our decisions. Occasionally they would offer some helpful thoughts for what to look for with potential health issues and what they could provide as tests if we experienced it. It turned into a relatively pleasant experience for a change.

And yes, in usual Trade smartassery I asked if they wanted the clock drawing to be AM or PM. It never fails to produce a puzzled, “wut?” expression. Just can’t help myself sometimes.

It all worked out as hoped. Could not ask for better results. Wifey’s BP and heart rate were in a normal range for probably the first time ever in 40 years of going to that doc office. The white coat syndrome did not kick in. Mine was in the usual range at 118/72/64. No physical abnormalities noted in the rest of our exams.

The blood test data was excellent for both of us. Wifey was slightly high on glucose, but had dropped 10% from the year before. I had nothing high or low except LDL, which was moderately above range for both of us. HDL and ratios were all good and in range. The LDL thing has been an industry hot potato with many patients since they lowered the acceptable range this year. Wifey and I are not going to play their game. We are in the previously acceptable 120 range. We will do the right things for us to lower it a bit more and not concern ourselves with their BS unless we detect problems.

Since we have only been making our life changes since early February, this blood test was a huge improvement for wifey. Her total total cholesterol dropped by a whopping 60 points from a year ago! Mine dropped 26 points even with the added meats and eggs. When I go off full Keto and sub in a bit of plant related proteins, fish and other veggies it will drop further. It proved that at least for some of us who follow the Keto nutrition plan as recommended; that it does not always lead to increased cholesterol as pundits and some medical professionals assert. Our own providers were skeptical of how it would turn out. Perhaps they will reconsider, perhaps not.

As stated I plan to selectively reintroduce some more good carbs (more fish, servings, veggies, Keto friendly fruits, maybe some oatmeal) into my diet, The sugar cravings are long gone and neither wifey or I desire for them to ever return. Related desserts and snacks will remain a thing of the past as a staple of our nutrition. Snacks for me are primarily nuts along with beef and chicken sticks. I will begin taking a Butyrate supplement to help my gut lining and maintain the metabolism my body has adapted to with more active fat busting ketones. It should help digestion for my gut type, which is averse to lectin as discussed. As stated I achieved my initial goal for weight loss. I plan to lose another 5 pounds or so to provide room for the winter months of less activity. Regardless, my goal will always be to weigh no more than my college playing weight. It should be relatively easy to do with our joint commitment to better health and the knowledge we have gained in the process.

With all of the above improvements, we are not without the normal challenges of aging that requires assistance from traditional medicine at times. For example, wifey will be addressing some non-cancerous dermatology related issues over the next few months. I will continue to work on flexibility and strengthening my lumbar region and knees, so that I can remain as active as possible. My Teeter inversion table remains a useful tool along with regular yoga stretching and other exercises. If I live long enough I expect one or both knees to need replaced as some point as they are well worn from sports and life as I have lived it.

Who knows what is in store for us to face, but we now feel comfortable we are doing our best to mitigate challenges to health. We give all praise to our Lord for seeing us through these life changes. We want to finish this life well before He takes us home, but leave the time for departure up to Him.

Conclusion

I urge all who are reading this to chart their own path when it comes to health and nutrition. Research, consider all of the information, pray about it, and then go to work. What I have provided is what has worked for us and our individual bodies, environment and living conditions. Some of it could translate to your benefit, but that is your call. The cost has been minimal. The reduction in overall food costs and trips to doctor offices for problems and illnesses, especially poor foods and life choices induced, has more than offset the costs of a few relatively low cost supplements and vitamins.

////

Remember Wolf’s site rules. Note and label all AI. Please be kind to one another, we are all in this together. May God richly bless America and all of you. Trust Trump and the plan.

Celebrate the 4th! We have been blessed to live in times such as these in the greatest country on planet Earth.

Again, please consider becoming an author of a Daily Thread on The QTree. It is your opportunity to create and communicate your thoughts for the benefit of others!

2025.09.02 – American Stories: 24 Hours Dealing With The Medical Industry

Time for a break from the usual. I will return with more signers next week.

The following recent event happened a month ago in mid July. This is a discussion on the state of medical treatments for an average Joe, who likely represents thousands of patients nationwide each day. In this specific case it is about a close friend and brother in Christ, so it is personal.

For the record, our family’s approach toward the use of the medical industry has evolved into a belief that they are guilty until proven innocent in their motives. As a result we verify first, trust maybe after a great amount of consultation and prayer.

With the rebuild of the medical industry well underway through the Trump administration, it seemed appropriate to do an authored post about this very recent real life experience of our good friend, who has been sharing some of his story on fakebook. The idea for telling this story at all started with my reading this X post from Secretary Robert Kennedy that was shared by TheseTruths on here a few weeks ago.

Then there is this recent article,

https://www.midwesterndoctor.com/p/the-unseen-cost-of-organ-transplants

The Back Story

For this true story I will call our friend “Bud”. Some may figure out he was a source for a BIMD story in that Bud is the same one who is long term friends and a former co-worker with country music superstar Morgan Wallen’s dad. Bud is in his early 50’s, married to the love of his life for 20+ years (his third marriage/her second); has three adult children from his first two marriages along with a step daughter from his wife, most of whom have spouses; has nine grandchildren; and has a growing six employee construction business with three family members working in it. He is nearly the same age as my step daughter, who went to high school with him although they did not know each other well.

I became acquainted with Bud a dozen years or so ago when he was referred to me by a neighbor as a good handyman. At the time Bud had been employed long term in the construction industry as a working supervisor in his speciality. However, he had learned a great deal about all aspects of residential and small commercial construction through the years. He also learned more from his father, who had built his own home as well as worked part time for other builders. Bud has been gifted the ability to figure things out and do them the right way when handling home construction, remodeling and repairs. With his after hours handyman workload picking up, he was faced with a decision, should he continue on his own full time or stay in a decent job that had no upside while continuing to moonlight as a handyman.

Over the next year he did work for us and many others around the area. We got better acquainted and learned each other’s life stories, shared our common faith, got to know each other’s families and friends, and so on. He justified my trust enough that we could leave town on a Fall Frolic or other trip and I could give him jobs to do in our absence and never have the first concern about it. He never had to be concerned about getting paid, beating him down on price, or ignoring his recommendations. We treat each other respectfully and fair, but more importantly, we have developed a bond of friendship well beyond the work. We love them and they love us as family.

One day he stopped by our house because he knew my business and banking background. He asked my opinion if he should go full time into his own business, that he felt led to do so and his wife supported whatever decision he made. Her job was good, stable and could provide health insurance. I told him that if the Lord was putting it on his heart, he had no choice. I confirmed that I had never met a more conscientious builder/home repair guy in all my years of lending into the industry as well as with my own, more limited residential home building and ownership experience. I reaffirmed he had the expertise and work ethic to be successful if he had access to good customers that needed his services at fair prices. We talked it through some more and he called me a week later to say he had pulled the trigger. His mid-life crisis at around age 40 was to start a business. 😀

From that point over the next decade his workload and business grew. He and his company are a rarity in an industry populated by a number of crooks, posers, and wannabes.

All of which leads to this current point in time and the related medical industry story.

Medical Emergency

Bud has been experiencing pains in his gut at infrequent, random times for a couple of years. For background purposes; diverticulitis runs in his family, so he attributed the pain to that. He would go to a GI doc, have blood tests and be scoped – nothing. Last month the pain knocked him for a loop and he headed to the nearest hospital ER fast due to the extreme pain. Bud’s wife works in an administrative office in a competing hospital, but there was not enough time to get there.

For those who are wondering, Bud took just the first jab, did not get the second and had nothing after that. He grew uneasy by what was going on. He has also been a half pack a day cigarette smoker. the periodic gut pains had been going on randomly for ten years, just not as acute.

Things started off well; he was seen quickly, admitted, scans/tests run, provided a room, etc. The nursing staff and on staff resident doc examined and gave him a pain med. They told him an assigned surgeon had read the scans and part of his colon was dead. They also saw another spot of concern at the lower end of his colon. The resection surgery would mean he would have to wear a bag for at least 6 months. He is a hands on builder who also does the electrical and plumbing roles himself, so there would be added financial and scheduling burdens from adding subcontractors for this replacement work as a result. Not good – Bud was worried.

They told him he would need a colonoscopy the following morning, then the surgeon (former military doc) would operate the day after that. Bud said if the man would not come to his room and talk to him personally first that he would not be cutting on him. They told him the surgeon was great, but never saw any patient before surgery. Bud’s wife verified that statement was true with her co-workers at the other hospital. Bud told his wife to have him moved to her hospital and find another doc for a second opinion. The current hospital agreed to release him. Then Bud and wife found out how much they would have to pay out of pocket to both hospitals if they did so. They could not afford it and were stuck.

It was at this point that he texted me from his hospital room to update. He said they were working on alternatives. I told him we were praying for him and that my father had exactly the same problem 60 years ago. His surgeon did a similar procedure without using a bag after giving him antibiotics for a serious infection first. My father recovered quickly after the surgery and lived another 40 years without issue. It lifted Bud’s spirits to learn this.

Bud’s daughter is in nursing in a city a couple hours away. She told them to do nothing that evening; to wait for her to get back with them. She had surgical nurse friends that might know a good alternative. So they bedded down for the night. The colonoscopy guy came in early the next morning and told him it was time to do the procedure. Bud said no it wasn’t, the nursing staff never prepped him for it. The guy was then pizzed at the nursing staff. They told him they thought Bud was leaving and going somewhere else. So they start prepping him only to mess it all up. Prep fluids and fecal matter start flowing out everywhere on Bud, the bed, the floor, etc. 😂 They then had to clean him and the room up. After all of that he was taken to be scoped.

Soon after he was brought back to his room a different surgeon (Doc #2) walked into his room. Doc #2 told him that a friend of Bud’s daughter had contacted his office and asked him to give a second opinion. He asked Bud if that was OK and he responded that he was relieved and appreciative. Doc #2 told him he had reviewed the scans, blood tests and exam notes – he indeed appeared to have a partially dead colon. He was relieved to learn from Doc #2 that all scans and tests showed he was negative for cancer, since idgit doc did not let him know anything. Doc #2 did a quick examination. Bud asked him about the spot they wanted to check with the colonoscopy. He responded that it was just a small amount of fecal matter that showed up in the scans. Bud asked what would happen after the surgery that was scheduled the next day. Doc #2 asked, “What surgery?” Then proceeded to explain there would not be surgery for several months unless his condition worsened if he chose to use his services.

Bud was puzzled at this point. Doc #2 told him he would first prescribe a series of antibiotics to clear the infection that set up in his colon that was causing the pain. Once it was cleared up he would do more scans and know more about its condition before doing any surgery. Bud asked why the idgit surgeon did not diagnose the infection so that antibiotics could be used first? Doc #2 rolled his eyes, but refused to speculate. Bud asked him if he would have to wear a bag after the surgery. Doc #2 said nope, he would remove the dead section and close. He predicted if all went well he would have a recovery time in the hospital of about four days afterwards. Bud decided to press his luck and told Doc #2 that he had a long planned vacation to FL before this happened that was supposed to start in two days. Doc #2 said to go, take the meds, and do no heavy lifting. The couple’s four grandkids who were going with them received the good news and were elated.

Bud called to give me an update after the exam. He thanked us for the prayers. I asked him if they fire hosed him and the room down after the colonoscopy prep. He had a good laugh, so I knew the pain meds were working well.

Sometimes the difference 24 hours can make is mind boggling. God is so good. All we have to do is to learn to wait and pay attention.

I talked with Bud again a few days afterwards as he was laying under a canopy at the hotel pool. His wife drove them down, he was feeling much better, the antibiotics seemed to be helping. His pain was minimal. It had dawned on him fully that the Lord still has plans for him springing from this crisis in his life.

God’s Provision

Bud’s father came to the Christian faith later in life at around age 40. He had lived rough up to that point. He was a former hard living Vietnam vet and factory worker. When he accepted Christ he changed dramatically and made a positive impact on the lives of his wife and children. This eventually led to him becoming a pastor in a small church in a poverty stricken community in his time off from his factory job. The church flourished and became a light to the community. Lives were changed. He retired recently at age 70. He is one of the finest men I have ever met.

During his father’s first visit that evening with Bud in the hospital he pointed out that God did not want him to go to the other hospital or it would have been an open door with the right surgeon provided and nothing would be getting in his way. He urged Bud to be patient and wait on God to provide what was best. The next day it all changed for the better.

I initially brought this story because of the ridiculous handing of the medical diagnosis and treatment of my friend. He was at a very vulnerable point and the medical system was set up against him. Had Bud and his wife not stood their ground he may have been butchered or given a death sentence by this grievous error. Had his daughter not solicited help for a second opinion from a reputable, competent surgeon they may have given in and had it done when all he needed immediately was antibiotics and rest. He should have been given options on treatment and surgery. The idgit surgeon had to know it was an option to try to heal the infection before any surgery, but refused to speak with the patient and was going to cut him open anyway. The untreated infection could have easily caused the surgery to be a failure. It also could have led to more of his colon being removed than was necessary as well. This would have affected Bud’s quality of life. Idgit’s actions were malpractice with what could be considered as malicious intent in my opinion

I shudder to think about what COULD have been if they had not delayed the decision and sought a second opinion under God’s guidance. There was potential for a tragic loss to loved ones, employees, customers, church and community.

In truth, at some point Bud could have been reduced to an organ donor by simply going to a hospital to be healed of something that has commonly been treated successfully in the manner that Doc #2 is using just as my own father’s situation was handled sixty years ago. Which makes me wonder about how many other people go through experiences similar to these throughout the nation on a daily basis.

As I finish this story, I need to relay a more recent conversation with Bud. He went to a scheduled appointment with Doc #2. After exam and tests he determined that the infection is being handled well. It is now time to start the pre-surgery preparation, which will be in early October as compared to the Idgit’s desires. It will be robotic with a laparoscopic incision to reduce chances for infection and improve healing time. Idgit planned traditional surgery with the bag. I doubt he would have even been capable of doing what Doc #2 is planning, who is obviously much more qualified. Bud also learned Idgit was planing to leave on a two week vacation the next day after the scheduled surgery. Hard to believe, but true.

Once again the lesson is to wait on the Lord.

In preparation Doc #2 wants Bud to do a one mile fitness walk every day to build his core stronger and ready for the surgery. The couple live on top of a hill and the road has a steep incline, so building his core should not be a problem. His wife is also using it as an opportunity to improve her health as they walk together in the evenings. A revised diet has started with no red meat, no desserts, more water, less caffeine, soft foods, etc. The third thing was addressed with him eye to eye – Doc #2 ordered him to quit smoking if he wanted to live. He wants all of the nicotine and stuff out of his system over the next two months to improve his chances for a full recovery. Bud is on board with it and began immediately.

Doc #2 plans to have him out of the hospital in four days post surgery as predicted previously. He will be under a no lifting restriction for three months to keep the bag away. Needless to say, Bud has no problem with complying and has employees who can handle the heavy lifting.

He is in an introspective, more joyful state of mind now. He is thinking things through and waiting on the Lord to give him clarity about how to proceed with his life from here. Selfishly and from the cheap seats, I would tell him to keep doing what he is doing. He just needs to take more time to decompress and enjoy the blessings in his life. So many people need the presence of this man until the Lord calls him home.

If you get a spare moment, please pray for Bud’s healing. Then take time to let others you care about know what they mean to you. If you need a medical provider, keep your eyes and options open. As we see in this story; there are sincere, competent professionals you can trust. There are also money hungry losers with no concern for you. Take nothing at face value, ask questions, consult with others you trust, and spend time with the Lord to gain clarity. Do not allow yourself to be set up to be a potential organ donor.

Please remember Wolf’s rules for our community. In general that means to be respectful to each other and to pull no shenanigans that your mom might find offensive or otherwise cause jail time. That said, free speech is honored here.

Be blessed and go make something good happen!

Dear MAGA: 20250522 ✾ Thank God ± Theistic Evolution ∈ Thursday Open Topic | Moar AI Spam | Mutually Acceptable Lies About The Clot Shot


This man, making Christmas calls from the White House, believes the world is a sphere. And he has even flown around it! So has our beautiful FLOTUS, who happens to be his wife!

Truth and common sense must be valued by us, as individuals, in order to lastingly disempower the authoritarian fake news media. This includes the perniciously smarmy science media, which never answers for its errors and lies. I believe that the media has been responsible not only for leftist pathologies like scientism, medical fascism, and radical gender ideology, but also for reactionary movements like modern flat Earth, rejection of all medicine, and Biblical geological literalism.


Just as Wheatie’s Stormwatch Monday Open Thread was created as a place for people to openly express their thoughts and opinions, so, too, is this Thank God Thursday Open Thread, where honest but civil discussion of all topics is encouraged. This thread is also to be known as Theistic Evolution Thursdays, due to the author’s expected “pontification” about his scientific, religious, and political opinions. You are welcome to pontificate back! Free speech matters!

Please label all AI-generated content as being such, unless it is patently obvious (e.g., humorous AI images). It is important that we as individuals not begin to pretend that socially derived artificial intelligence is actually our own, as this form of stealthy social information averaging and feedback would be one more pretense and deception between people, in service of stupid Marxist socialism, and of those who wish to substitute their communally protected lies for actual truth.

The source of alleged truth matters, not for the truth itself, but for validation.

And yes, it’s THURSDAY…again.

And that’s it. We’re done stealing from Wheatie.

OK – maybe her rules need to be posted.

  • No food fights.
  • No running with scissors.
  • If you bring snacks, bring enough for everyone.

Other rules may be derivable from these, and that conjecture is left for discussion.


If there is nothing beyond the “W” below, then this is a placeholder. For health reasons, I can’t always post a timely opinion before each Thursday, but I will try. Otherwise, you have this placeholder post, where YOU provide the content. Enjoy!

W


Moar AI Spam

AI is assisting with the proliferation of bullshit, because it puts fairly smart white lies in the hands of fairly dumb people who need them.

Example? This bit of engineered bullshit, either actual spam, or IC AI bullshit disguised as spam, trying to get on this site.

Note – I included Cuppa Covfefe’s last comment on the Open – A REAL COMMENT – for context. That comment was made roughly 4 1/2 years ago.

For those with low vision, the text of the spam post:

‘This Sanctuary Sunday Open Thread’ beautifully fosters unity, faith, and respectful dialogue. I appreciate the emphasis on civility, truth, and open discussion. A great reminder of how meaningful and peaceful conversations can shape a strong, thoughtful community.

I’ll be frank – that’s a nice comment. I won’t say why it’s obviously an AI comment, because I don’t reveal tells of that nature – but for those and other very definitive reasons, I can assure you that it’s an AI comment.

Now, let’s compare that with the following first few paragraphs of Carl’s post, which were analyzed and turned into that AI response.

In the original post, both “Sanctuary Sunday Open Thread” and “Please show respect and consideration” were bolded, and it’s clear that the AI noted this, by putting single quotes around those first four words, which were played back. In the sample from Carl’s post, below, I am bolding almost all of the things on which the AI appeared to be focused.

This Sanctuary Sunday Open Thread, with full respect to those who worship God on the Sabbath, is a place to reaffirm our worship of our Creator, our Father, our King Eternal.

It is also a place to read, post and discuss news that is worth knowing and sharing. Please post links to any news stories that you use as sources or quote from.

In the QTree, we’re a friendly and civil lot. We encourage free speech and the open exchange and civil discussion of different ideas. Topics aren’t constrained, and sound logic is highly encouraged, all built on a solid foundation of truth and established facts.

We have a policy of mutual respect, shown by civility. Civility encourages discussions, promotes objectivity and rational thought in discourse, and camaraderie in the participants – characteristics we strive toward in our Q Tree community.

Please show respect and consideration for our fellow QTreepers. Before hitting the “post” button, please proofread your post and make sure you’re addressing the issue only, and not trying to confront the poster. Keep to the topic – avoid “you” and “your”. Here in The Q Tree, personal attacks, name calling, ridicule, insults, baiting and other conduct for which a penalty flag would be thrown are VERBOTEN.

In The Q Tree, we’re compatriots, sitting around the campfire, roasting hot dogs, making s’mores and discussing, agreeing, and disagreeing about whatever interests us. This board will remain a home for those who seek respectful conversations.

Please also consider the Guidelines for posting and discussion , outlined here https://wqth.wordpress.com/2019/01/01/dear-maga-open-topic-20190101/

Let’s not give the Internet Censors a reason to shut down this intellectual haven that Wolf has created for us.

Note that the word “faith” was not there – it was generated by the AI. The only place “faith” appeared in Carl’s entire post was 12 times in a large paragraph way down in the body of the post. If you want to check it out…..

LINK: https://www.theqtree.com/2020/12/27/dear-kmag-20201227-open-topic/

Thus, the mere mention of “worship” at the beginning, and the entire context of the body of Carl’s post, were likely the origin of “faith” in the AI comment.

“Meaningful” and “peaceful” are also derived from the larger context. Those words are not present, although “peace” appears 5 times in the body of the message from Carl.

I want you all to understand that the AI is basically doing what high school students and college students are trained to do, in writing a reply letter, answering essay questions, or otherwise composing written material based on some source, without plagiarizing. It’s reading, grabbing concepts, mixing things up, generalizing about what is observed, then composing a restatement which comes very close to what was originally said, from a reader perspective, without “aping” the original, which is both cringeworthy and considered plagiarism.

AI is pleasing its trainers, just like students try to please their trainers teachers.

This is why AI is being used by students to pass exams.

Andrew Torba has a masterful post about this, which you all really need to read. He predicts that universities themselves, as we know them, are about to be on life support, because of AI.

After reading Torba’s post, I realize that Harvard is falling apart for multiple reasons. IMO, woke does not have the honesty needed to deal with AI, or anything else, for that matter.


TORBA…..

LINK: https://news.gab.ai/ai-is-flipping-education-and-work-on-its-head

ARCHIVE: https://archive.fo/vIvHH

By Andrew Torba in AI — 15 May 2025

AI Is Flipping Education and Work On Its Head

Over the next 15 years, universities will face existential pressure to adapt or perish. Some may evolve into credentialing hubs, offering “micro-degrees” for niche skills.

AI Is Flipping Education and Work On Its Head

Excerpt:

Artificial intelligence is not merely a tool for incremental change it is the architect of a total overhaul. At the heart of this transformation is a radical reimagining of how knowledge is delivered, absorbed, and validated. At Alpha School in Texas, students spend just two hours a day learning with AI, yet they outperform 98% of students nationwide, scoring in the top 1-2% on standardized tests.


WOLF AGAIN…..

The question will not be whether you can use AI to fake out people about how smart you are, in their decaying system. The question will be whether (1) you can use AI for real research, or (2) whether you can change, fix, use, or install AI to do something useful and good to others.

That output of your use of AI may include good stuff, or bad stuff. People who use AI for bad stuff will need to be punished. Good AI and AI in the hands of good people will get it done.

Welcome to the future.


Mutually Acceptable Lies About The Clot Shot

It’s time to be honest about what is going on in HHS, NIH, FDA and CDC.

Reform of these agencies – whose sins almost killed us, and did in fact kill many of us, and many other people around the world – will NOT occur by a quantum leap from bad to good.

It is occurring gradually and continuously, just like the end of government-sanctioned slavery did, in centuries past. And just like The Death of Slavery (cough), the entire process of Death To The Death Jabs (cough, cough) will be a shifting morass of what I call “mutually acceptable lies“.

PAVACA has very nicely documented the various half-measures, quarter-measures, and non-measures which have been taken by the government-ensconced part of MAHA against the clot-shots.

That is the current state of the matter. Not the end state – the current state.

Stated bluntly, the jabs are being gently but not honestly withdrawn from the young and the healthy, and are being kept, with no denial of existing fictions, for the sick, the old, the infirm, and the chronically medicated.

You know – the very people that a socialist depopulation program still wants to remove.

NOW do you see why the current assortment of lies and truths might be mutually acceptable to the two sides?

You don’t normally think like a depopulationist, or like somebody whose kids are being threatened by a shadowy cartel. So you never saw it coming – that our side would accept both some silver and some lead – at least temporarily. Or that the other side – the depop cartel – would accept a mixed bag. Yes – just like the drug cartels, they accept shifting realities.

The BAD SIDE threatened our children and young adults, and showed us that they had the power to not just kill our loved ones, but to make us do it – to make us part of the murder. Having them back off from this extortion is what we get, in return for their continued elimination of the people they wanted to eliminate all along – the weak, the old, the medically costly, the non-productive, and the undesirable, who can be slipped into their caskets at any time by a few shots.

This was very skillful play by the depoppers and their deep state allies. Do you see it? They had a REASON for pushing the jabs too far. So that when their commu-Nazi tide went back out, it was still deep enough to drown the “useless eaters”.

Now – this is not the spoken reality – meaning the lies. What I gave you is the mutually acceptable truth. The mutually acceptable lies are continuation of the scientific bullshit about antibody count, no need for clinical testing, and most of all, the need for those medical pobrecitos (poor young little ones) to get the merciful jabs to protect them from the still mythically Wuhan-dangerous omicron common cold.

THAT is their goal. THAT is what they needed to accomplish.

Somebody is still gonna pick the cotton and go to Heaven.

We know the “dangers” to these fragile patients are all bullshit, already shockingly disproved by the “peer-reviewed” literature. But the media that can never be wrong, and the scientific media that is even worse, are “not done not talking about things” – so we have to wait for memories to cool, so that nobody gets in trouble for slavery killing Black and Indian kids with jabs.

So what do we do?

We keep pushing on. We keep fighting. We make sure the public, the MAHA now in office, and (importantly) the American pope know that the fight for human life is not over – that “depopulation” is real, that it’s insidious, and that its stealthy proponents are not done fighting.

The depoppers will put up a hell of a fight to keep things where they are right now – where they not only have the elderly and the infirm at the end of a population-adjusting needle, but where they also have a prime depopulation AGENT (coronavirus spike protein) authorized for that needle.

And yet, I think we have some strong weapons at hand, against their strong lies.

If our theories are correct, then we will find evidence of safer outcomes with non-mRNA vaccines like Novavax, Coronavac (ChiCom jab), CorbeVax, and others that omit the mRNA technology. Even better, the new “Gold Standard” “universal platform” jabs that are now being pushed by Secretary Kennedy and Dr. Jay Bhattacharya, should prove much safer than mRNA.

Yeah, they’re not perfect – but they’re better. Fewer people will die. SOME people – in fact MANY people – will be rescued from depopulation.

This is war. There will be casualties. But we will win.

W