Our mission, as God-fearing and God-loving patriots, is to defend this Constitutional Republic and to increase its greatness, in all good things and ways, by using our voices in free but courteous speech, by discussing the happenings of the world and coming to a profound understanding of those things, and by sharing and promulgating these Truths on both this platform and others.
The free vintage image for today’s offering header of Scène de la pestede 1720 by Michel Serre, of the Great Plague of Marseille, is courtesy of Google Images. For more information about the Great Plague of Marseille, please see: https://www.sciendirect.com/science/article/pii/S0755498222000318, “History of the plague of 1720 – 1722, in Marseille”, Michel Signoli, et al.; September 2022. For more information about the Black Death (Black Plague) in Europe, 1347 – 1351, please see: https://www.britannica.com/event/Black-Death. Note that the article on the Britannica website mentions the fact that the strain of Yersinia pestis (Y. pestis) that caused the Black Death plague in Europe is the ancestral strain of all other plague events since then.
The word “plague” generate images of the Black Death (Black Plague, the Bubonic Plague) that swept through Europe in the mid-1300s. Of thousands of dead people on the streets. Of entire families wiped out in a few days. Of the cries of “Bring out your dead.” And the Black Death is only one example of how devastating the plague can be. There have been numerous other incidents of plague attack, such as the 1720 – 1722 event that struck Marseille, France. Today’s offering discusses a “new aspect” of the plague — of a certain element of it being used as a “vaccine” ingredient. For purposes of today’s offering, Yersinia pestis and Y. pestis are used interchangeably.
>>>>>>>>>>>>>>>>>>>>
Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
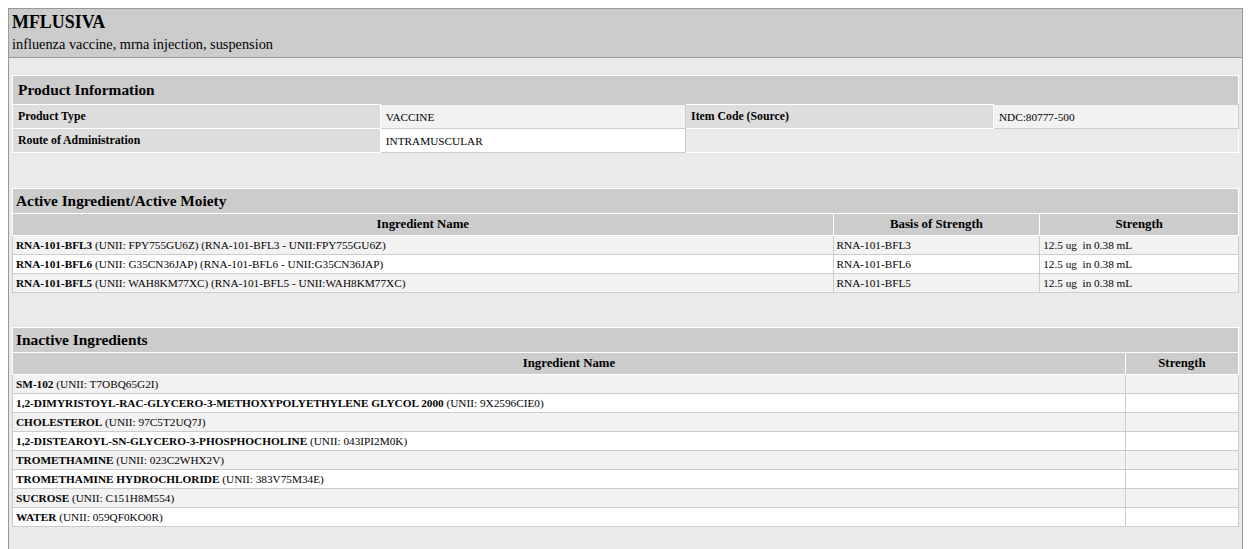
However, there are other types of adjuvants that are either now in use, or are being studied for use, in injectable drugs. One such use being studied is the subject of today’s offering: an Avian Influenza “vaccine” adjuvant derived from the Yersinia pestis bacterium (the Black Death, the Black Plague, and also known as the Bubonic Plague.) To repeat: an Avian Influenza “vaccine” adjuvant derived from the Yersinia pestis bacterium (the Black Death, the Black Plague, and also known as the the Bubonic Plague.) Yours Truly begins here, with an article by Jon Fleetwood: https://jonfleetwood.substack.com/p/hhs-funds-chimeric-bird-flu-pandemic, “HHS Funds Chimeric Pandemic Bird Flu Vaccine Made With Engineered Plague Derivative BECC470s: Journal ‘mSphere'”, 13 August 2026. Please see the screenshots from this article, below:
The paper referred to in the Fleetwood article is here: https://journals.asm.org/doi/10.1126/msphere.00171-26, “Optimizing an avian influenza vaccine using a novel Bacterial Enzymatic Combinatorial Chemistry (BECC) TLR4 adjuvant”, Robert K. Ernst, et al.; 10 July 2026. The research was funded primarily via HHS-NIH-NIAID-BAA2017/HHSN272201800043C; via other HHS-NIH-NIAID grants; and, the Center for Vaccine Development and Global Health (University of Maryland School of Medicine.) The work of one co-author, Devon Riley, was funded via the United States Army Long-Term Health and Education Training Program.
>>>>>>>>>>>>>>>>>>>>
What is BECC470? Please see: https://www.fromtiersin.org/journals/immunology/articles/10.3389/fimmu.2026.187218/full, “Licensed and investigational TLR4 agonists as vaccine adjuvants: Structural basis, clinical progress, and future directions”; Jiasheng Zhou, et al.; 16 July 2026. Note that, except for one co-author of this paper (who is associated with the Communist Chinese version of the CDC), all other co-authors are associated with research institutes in Wuhan, Communist China. A screenshot of section 3.2 of this paper, which describes BECC (Bacterial Enzymatic Combinatorial Chemistry) is below. There are two versions of BECC470: BECC470b (the biological form of the Y. pestis element in the adjuvant); and, BECC470s (the lab-created synthetic form of the Y. pestis element in the adjuvant):
BECC438, BECC470b, and BECC470s are all derived from the lipid A in Y. pestis.
It appears that there are three separate publications of the Robert K. Ernst, et al., paper: the 10 July 2026 paper in the ASM Journals, cited above; another publication, a day later in July 2026, in journal Vaccines (https://www.sciencedirect.com/science/article/pii/S02644-10X26005839), “BECC-adjuvanted hemagglutinin influenza vaccine promotes enhanced immunogenicity and protective efficacy”, Robert K. Ernst, et al.; 11 July 2026; and, a Biorxiv preprint version, published in March 2026 (https://www.biorxiv.org/content/early/2026/03/05/2026.03.03.709477.full.pdf, “Optimizing an avian influenza vaccine using a novel Bacterial Enzymatic Combinatorial Chemistry (BECC) TLR4 adjuvant”, Robert K. Ernst, et al.; 5 March 2026. All three of these publications appear to have same parameters: One, that Gain-of-Function experiments were performed with multiple strains of Avian Influenza and then injected into the lab mice; Two, there is no direct mention that BECC438, or BECC470b, or BECC470s, are derived from the lipid A of Y. pestis; and, Three, that BECC adjuvants are “superior” to the other types of adjuvants currently in influenza “vaccines.”
>>>>>>>>>>>>>>>>>>>>
Back to the article by Jon Fleetwood. Something caught Yours Truly’s eye: It appears that the lipid A portion of a certain strain of Y. pestis, called KIM6+, is the one that was chosen to lab-create BECC470b, which was then chemically engineered to create BECC470s. Please see below:
Yours Truly did some digging into KIM6+. The 2023 paper, which also has Robert K. Ernst as co-author, is here: https://www.cell.com/action/showPdf?pii=S2405-8440(23)05327-6, “Physiochemical characterization of biological and synthetic forms of two lipid A-based TLR4 agonists”, Robert K. Ernst, et al.; available online 8 July 2023. Another paper, from 2021, by Bland, et al., discusses the KIM6+ strain of Y. pestis and its infectivity: https://journals.plos.org/plospathogens/article?id=10.1371/journal.ppat.1009995, “Acquisition of Yersinia murine toxin enabled Yersinia pestis to expand the range of mammalian hosts that sustain flea-borne plague”, David M. Bland, et al.; 14 Octocer 2021. Please see below, from the Results section of this paper:
It appears that the KIM6+ strain of Y. pestis is one that has about 50% more capability to infect. And it is the KIM6+ strain that was chosen to lab-create BECC470b; and then to have that chemically engineered to lab-synthesize BECC470s — both of which can be used as vaccine adjuvants.
>>>>>>>>>>>>>>>>>>>>
Robert K. Ernst holds at least two US Patents related to the use of KIM6+-derived Y. pestis lipid A constructs that can be used as adjuvants in vaccines: US10358667B2, 7 January 2016, “Adjusted expiration” of 19 March 2034: and, US11124815B2, 21 September 2021, “Adjusted expiration” of 7 March 2034. Both Patents have the same Title (“Immunotherapeutic Potential of Modified Lipooligosacchardies/Lipid A”); the same Inventors (Robert K. Ernst, et al.); and the same Licenses and Options (Licensed to TollereBio Corporation [Robert K. Ernst], Optioned to Virtici, LLC.)
Reading through US10358667B2, one finds, for example, that a BSL-2 biosafety laboratory level is, apparently, sufficient to work with the KIM6+ lipid A of Y. pestis, and to lab-create BECC470 adjuvants from this bacterium; that BOTH the “biological version” of BECC470 (BECC470b) and the “synthetic version” of BECC470 (BECC470s) can be used as vaccine adjuvants; and, that the BECC470 vaccine adjuvants, per the Patent, section VIII. Use of ExemplaryLipooligosaccharide/Lipid A-based Mimetic Compositions: “…is [sic] useful for…” the following vaccines, among others, listed in the Patent:
measles, mumps, rubella (think MMR);
polio;
plague;
chickenpox;
HPV;
Hepatitis B (think newborn “vaccination” with this one);
pertussis;
tetanus;
and, shigella (Shingles)
And, in fact, Dr. Ernst is at work creating a shigella “vaccine” that includes BECC-engineered adjuvants: https://www.sciencedirect.com/science/pii/S0264410X25000763, “BECC-engineered live-attenuated Shigella vaccine candidates display reduced endotoxicity with robust immunogenicity in mice”, Robert K. Ernst, et al.; 19 March 2025. This paper appears, in Yours Truly’s opinion, to “dance around” actually mentioning the apparent use of Y. pestis-derived elements in the Gain-of-Function shigella “vaccine” that was administered to lab mice (administered using various methods, including intramuscular injection and gastric injection.) The paper does list various Patents that are “related” to the paper, including both US10358667B2 and US11124815B2 (discussed above in today’s offering.) The paper also lists the 2018 Ernst, et al., paper regarding the use of Y. pestis-derived BECC438 in a vaccine administered to mice: https://www.sciencedirect.com/science/article/abs/pii/S0264410X18307680, “A lipid A-based TLR4 mimetic effectively adjuvants a Yersinia pestis rF-V1 subunit vaccine in a murine challenge model”, Robert K. Ernst, et al.; 27 June 2018.
In Yours Truly’s opinion, this entire situation raises important questions, among them: One: Why is the United States government (via HHS / NIH / NIAID), and the United States Army, funding research into using any element of the plague bacterium in a drug of any type, let alone a drug that can be injected? Two: How is it possible that a BSL-2 level laboratory can be considered to have sufficient biosafety to work with any element of the plague bacterium? Three: Why was KIM6+, apparently one of the most deadly and infective lipid A elements of Y. pestis, used to lab-create BECC470b and BECC470s? And, Four: Is it possible to completely “de-nature” the deadly effects of any element of Y. pestis sufficiently for such element to be used as an adjuvant in vaccines?
Peace, Good Energy, Respect: PAVACA1
(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA1 (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA1 if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s post for any AI-generated content. To the best of her knowledge and belief, there is none. If readers wish to post any AI-generated content in the discussion thread for today’s post, they must cite their source. Thank you.
Do not forget to LABEL AI articles video and such.
I Avoided a Heart Attack by Cleaning 20 Years of Clogged Arteries — Dr Ford Brewer MD MPH. (35 minutes)
This is another look at health and in someways compliments yesterday’s article. In both cases both doctors promote a Keto diet and avoiding sugar/starches/carbs. Dr Ford Brewer is more of an establishment physician having worked for years at Johns Hopkins “training the other doctors there in prevention.“
My 7- Step Heart Attack Prevention Protocol free ebook HERE.
TRANSCRIPT
Let me tell you a story. It’s about what happened to me. At age 57, this is 11 years ago. I found out I had the arteries of a 73 yr old 16 years older than me. I had no idea. I thought I was like this close to the kind of heart attack [finger & thumb almost touching – GC] You know, [with] heart attacks, 50% of them have no symptoms until boom, you’re dead. And it’s like that really upset me because, I thought I was the picture of health. I ran marathons. I avoided eating fats, which again, both of these things we thought at the time to be the best practices for heart health. And still, that test said I was walking around with a ticking time bomb in my chest. But here’s the thing. I didn’t quit. I fought back. After a year, I turned those arteries into the arteries of a 52 year-old.
Now, look at this. [Shows a CIMT non-invasive ultrasound machine -GC] This is the most advanced heart scan in the world at this point in time and it shows my dangerous plaque is basically gone. [Shows his results for right Coronary Artery – GC] That means my risk for a sudden heart attack right now is practically zero. If you’ve ever been told it’s too late or that you just have to live waiting for a heart attack, that’s not true. This video will prove otherwise. I’ll show you exactly how I reversed decades of arterial plaque, avoided a heart attack, and how you can do that, too, including one element that most people miss.
The carotid is the artery right here. Now, I know that’s a mouthful and it sounds uber technical. It’s actually pretty simple. It’s a quick ultrasound. There’s no radiation and it’s the arteries in the neck that I just pointed to. You can feel that pulse. But it doesn’t just look at how well blood is flowing. It measures how much plaque is hiding inside the artery wall. And if you’re saying, well, you know, that’s your neck, not your chest. We’ll get to that a little bit later. But the short version is 98% of the time, if you have plaque here, you’re going to have it here. And vice versa. If you don’t have plaque here, you’renot going to have it here or anywhere else.
Plaque isn’t really a plumbing problem that only happens in the heart. It’s a metabolic problem. So that’s why if you’ve got plaque in one place, you’ve got it in the others. Metabolic meaning how your body burns fuels. By the way, if you want to take a deep dive into metabolic health, you need to get my e-bookHERE. It’s free.
Now, when that CIMT result came back at 1.2 millimeters. I knew I was in trouble. I was frustrated, like I said, and I was pretty emotional. For context, one millimeter or less is ideal. Over that and you’re in a little bit of a danger zone. But the worst part is based on the amount of plaque detected in my arteries, my arterial age came back at 73 years old, 16 years older than what I actually was. For a couple of weeks, I was frustrated and angry, but mostly just frustrated. Then I thought, maybe I wasn’t doing everything wrong. Despite some of the shortcomings of my lifestyle, and I needed to change some things, but I was still doing better than a lot of folks. It wasn’t like, I had done nothing, I could have weighed 300 lb plus. I could have had a whole bunch of body fat that was creating this problem. At least I had some things going for me.
The other thing that occurred to me is yes, had I not done those lifestyle activities, I could have already had a heart attack. I could already be dead. So, I began to see the other side of this. Once I got past that shock, I knew I had things to do, though. The first thing I did was look for the cause. I ran an oral glucose tolerance test where you drink a a set amount of glucose, either 75 or 100 grams, depending on the the context of the test that you’re doing or the format. You want to see how your blood sugar responds over time. Mine spiked to over 160.
Already it was clear, you get spikes over 160. And those are the times when you can be forming plaque. It meant I had enough pre-diabetes to cause plaque, even though I’d never been told I was diabetic. That was the turning point.
I switched from a low-fat diet to a low carb diet. And I didn’t just lower my carbs. I removed the ones that spiked my blood sugar.
So, for example, fiber-based carbs are carbs, but they don’t mess with my blood sugar. [He shows a photo of bowls of white rice, oats? Chickpeas? And?? — GC] The glycemic carbs are the pastas, the breads, those highly processed carbs are the ones that raise my blood sugar. Grain products, one of the biggest offenders. And I loved bread. I didn’t eat a lot of pasta, but I ate bread all the time. You know, let’s break bread together. I thought that was a great thing. I changed my workouts too from long distance cardio and I still continued to do some of that but I added a lot more short intense bursts and more focused resistance training. So what I was doing with the intense workouts wasworking on my capillaries. That’s where my insulin receptors live.And with the resistance train I was working on my mitochondria in my muscles. That’s what burns the glucose once you get it into your muscles. And speaking of muscles, the reason I focus on my legs is that’s where your real muscle mass is.
I improved my sleep. It was a long saga of many things that I did to improve that sleep. I lowered my stress. And yes, I made a few unpopular choices with supplements and even medications. Within a year, my CIMT showed my arterial age had dropped from 73 to 52, 20 years younger. But that was just the beginning.
Over the years, I kept getting a CIMT basically every year. They keep showing very slow progression of my plaque. But I kept seeing some comments in the channel specifically asking CIMT is okay, but what about your calcium score? We want to see how your heart is. So, I thought I might as well just get a calcium score. Now, here’s the thing. Calcium score won’t show soft plaque, the dangerous type of plaque that can rupture and cause a heart attack. That’s why I went to get CIMT because a CIMT does show the presence of soft plaque which I didn’t have based on my [current] results.
So I decided to do something better than a calcium score. I went straight to the coronary CT Angiogrambut not just any traditional angiogram. I got the newest type of CT angiogram [Cleerly Ct-angiogram] and that it’s the one that uses AI analysis. This is the best available test to identify both soft unstable and hard calcified plaque in the arteries of the heart. I got mine done with a company called Cleerly, but we work with other companies, too.
There’s another one called HeartFlow®as well. Enough talk about the process. You want to see my results? So, when I opened the report, three headlines jumped off the page. First, soft plaque volume.1 millimeter. That was a relief. In practical terms, that means I have virtually no unstable plaque in my heart right now. Second total plaque volume 75.6 cubic mm with stable calcified portion at 31. The rest is higher density non-calcified plaque. It behaves [as if] it’s stable when you manage your metabolism. That may be getting a little bit too technical. Here’s the translation. Very little total plaque and almost none of the dangerous kind. So those are the two key things to remember.
I said three things and there’s always this third thing that the rest of the medical world always wants to focus on and that is stenosis and location of the plaque. Stenosis is a geeky word for whether or not you’ve got obstruction. Most arteries were under 10% obstruction. And the highest narrowing was 17%. And that was in guess which one? The L. That’s the one they called the widowmaker. Ba bum. Everybody’s always so scared when they hear that term.
They come to me and they say, “The doctor said I had calcification and plaque in my widowmaker.” And I’m going, “I understand. If you have plaque in the heart arteries, the first place you’re almost always the first place you’re going to get it is the L.” So, don’t get concerned if somebody tells you you have plaque and it’s in the widowmaker, the L. [left anterior descending (LAD) artery.Dangers of a Widowmaker Heart Attack – GC] Now, if there’s another specific measurement here, it’s called percent atheroma volume. [Coronary Atheroma Burden Is the Main Determinant of Patient Outcome –GC]
And let’s take a look at that. It measures basically how much plaque you have in terms of volume. Mine was 2.5%. In plain English, the plumbing is just wide open. And more importantly, the plaque that matters for sudden events, the soft inflamed stuff is essentially absent. Put together that means my risk for a sudden heart attack is dramatically lower. And it confirms the progress that we saw on the CIMT, not just in the neck, but in the heart as well.
The major problem related to metabolic disease, it causes plaque and inflammation.
After years of doing prevention and treating patients, I’ve come to realize that testing for this can be very difficult. Now, there are some lab tests, OGTT, oral glucose tolerance tests, and insulin response, the amount of insulin required to m for by your body to manage glucose. [Glucose Tolerance Test (GTT): What It Is — GC]
It’s a hard test to do. It’s definitive. It’s old school, but it’s hard because it requires a lot of time and effort and still sometimes the lab goofs it up.
….
I would not call the test hard, I would call it tedious and time consuming. Unfortunately I found doctors do NOT want to do it on young people. When I tried to get the test done in the early 1970s, I was told I was too young, to have the problem. Yet it is when you are young where finding you have Hypoglycemia is most important for intervention. Note that even now it is considered rare.Of course if you refuse to test for it in the young, and they constantly eat sugar, it will turn into type 2 diabetes as the pancreas becomes exhausted.
Reactive hypoglycemia means your blood glucose falls quickly after a meal, often within one to four hours. This can happen after a refined carbohydrate heavy meal because insulin surges to clear the sugar.The result is a rapid drop that the brain interprets as an urgent need for quick fuel. Common symptoms include sweating, tremor, anxiety, and an intense urge for fast carbohydrates. Reactive hypoglycemia is an answer to the question “what illness causes sugar cravings?” for many people with post meal cravings. For more clinical context on post-meal low blood sugar and related eating patterns see the research summary here: reactive hypoglycemia and eating behavior.
OK, I will get off my hobby horse, and get back to the transcript.
…
Now, if you’re thinking, Ford, congratulations on reversing your plaque. That’s good for you. What I really want to know, though, is how do I do it? I understand. So, let me show you exactly what I changed to get here, step by step, so you can start bringing your own numbers down. The first and most important change was diet.
BLOOD SUGAR SPIKES
I stopped thinking of food as low-fat or low calorie and I started thinking of it in terms of blood sugar impact. I began testing my blood sugar after meals and if it pushed me over 140, it didn’t stay on the menu, no matter how healthy the label claimed it was. So, one of the first big surprises for me was no more oatmeal for breakfast. That jacked my blood sugar. It meant cutting breads mostly. As I said, I didn’t eat a lot of pastas before, but I ate a lot of breads. Rice, I had developed a taste for rice. And as I mentioned, oatmeal. Couldn’t believe it.
But that’s what the blood sugars, that’s what they told me. So instead, I built my meals around foods that kept my blood sugar stable. I replaced those carbs with healthy fats, moderate protein, and plenty of vegetables that didn’t cause a spike.Over time, I experimented with different eating styles. I’ve tried versions of carnivore, keto, paleo, and plant heavy, low carb. No matter the variation, the common theme was always the same. Keep the carbs low and avoid the processed junk, and avoid blood sugar spikes.
For healthy fats, I leaned on things like avocado, extra-virgin olive oil, and fatty fish like salmon and mackerel. I didn’t shy away from natural saturated fats, either. real butter, not margarine, and yes, even bacon. I went back to bacon, which I had not eaten in decades because it was high-fat, butter, too. So, I went back to butter and bacon, and that was nice. A breakfast of eggs fried in butter with avocado on the side. That kept me satisfied for hours, and it didn’t send my glucose up.
I also paid attention to fiber. Now, some people have a problem with fiber. I don’t. Even in a lower carb approach, non-starchy vegetables, and some fermented foods, these gave me the fiber my gut needed. A big salad with olive oil, apple cider vinegar, and salmon was often lunch and dinner sometimes, too. I love Caesar salads, and so when I went out to eat, and I did a lot because I was traveling a lot, a salmon Caesar salad was my go-to dinner.
Others might be grilled chicken with sauteed greens. Sometimes I’d have a fatty cut of beef, but not very often because I tended to gain weight on beef. I developed a a taste for Brussels sprouts, which I had always hated. But you know what? You got to do what’s what you got to do. I even learned to eat kippers, kippered herring. I still cannot learn to eat sardines. I tried it a few times. I just gave up.
Now, here’s something that might surprise people. Once a week about, I’ll have a little bit of ice cream. Usually not the kind loaded with sugar and corn syrup, but usually one sweetened with alulose, stevia, or arythril. It tastes like a treat and it really doesn’t wreck my blood sugar or undo my progress. So that’s important because if your diet feels like punishment, you won’t stick with it. You just have to learn and change the way you eat. When you say, “I’m on a diet,” that implies temporary that’s in your head. I’m going to change back at some point. That’s not what you want. You want a way of eating that you can live with permanently. The point was to eat in a way that kept my blood sugar in the safe zone and made plaque reversal possible while still enjoying my food.
But what if I had a spike? What happens then? Well, for starters, I don’t panic. Just going out for a walk or doing some exercise snack like lunges or calf raises or jumping on the Schwinn Airdyne. You know that 30-year-old Airdyne that I kept around the house, mom kept around her house. And it was great. it will bring bring my blood sugar back down very quickly. That’s because it’s not the spike that drives the problem. It’s how long and how often your glucose stays even over 140. So, if you think about it, some foods might spike your blood sugar 200 or more. And if it’s only a few minutes, that appears to be okay. It’s really time under the curve, the blood sugar curve over 140. So, I’d much rather have a quick spike of 200 and back down to 100 than go up to 160 and just stay there hour after hour after hour.
EXERCISE
Now, all this leads me to the second big change, and that was exercise. I used to think the key to heart health was endless cardio, long runs, marathons, long bike rides, hours and hours of that level two steady state work. I ran half marathons weekly, sometimes twice a week… Here’s the truth I learned. Long-distance cardio isn’t bad. It’s not the most efficient way though to protect your arteries or reverse plaque. What really matters is improving your metabolic health. And the fastest way to do that is by building and using muscles, especially in your legs. Your leg muscles are your largest safety valve against insulin resistance and metabolic disease. When you engage those big muscles, you pull sugar out of your bloodstream and into your muscle cells where it’s safe. You’re lowering your blood sugar and insulin levels quickly.
….
[I notice that when I am doing a gig, I can get away with drinking a sugary soda in the middle of the gig without feeling that sugar crash I do when sitting at a desk. . –GC]
….
So, I shifted my training. Instead of logging 10 or 15 miles at a time, I started doing short intense bursts, high-intensity interval training, HIT, and a newer variation of this called REHIT, reduced exertion, high-intensity training. With HIT, I’d go all out for 40 to 60 seconds or not all out, but more like 90%. Recover for a minute or two, and then repeat. REHIT is kinder and gentler. You do go all out, but you only go out for like 20 seconds maximum. You do your maximum intensity, but only for 20 seconds, and then you back up.
You do a recovery very slow for 40 to 60 seconds. You do even just two high-intensity intervals in REHIT. And it’s shown to have some really good impact on your health, your arterial health, and your body. And guess what? The reason it’s called reduced exertion, [is] even though you’re going to high intensity, highest level, it’s only for 20 seconds. It’s only twice and you can do it in the morning and you don’t feel burned out the rest of the day. You don’t feel washed out. I could do it on a stationary bike, that Schwinn Airdyne I talked about. I could do it running hill sprints and I do all of those. I even added a rebounder that a friend gave me. You know those trampolines? I thought those were kind of wimpy looking until he gave me that one. And it’s like, oh my gosh, when you hit a flat out sprint on that thing, it will wear you out.
It’s great for calves, hips, and quads. So, I paired that with resistance training. And I’m not talking about hours in the gym. Most days, I did resistance snacks. 5 minutes in the morning, 5 minutes in the evening, even two or three minutes three or four times in the day. Wall squats, prolonged lunges, pull-ups, step squats, one-legged step squats, calf raises, use dumbbells, barbells, body weight moves. Once a week I’ll go to the gym for a longer session, harder workout, and use all those machines. Also once a week I’ll do a longer hit. So, I do three to five REHIT sessions per week and then one session of full hit.
I completely cut out those punishing long distance runs. Well, not completely. There were a few years where I never ran even as far as 5 miles at the time. I’m back to doing a couple of five mile runs. I’ll usually try to get in one once a week. My workouts overall became shorter, more intense, and more targeted. And the results in my labs and the scans speak for themselves.
The key is you don’t have to start at my level. Remember that. I do some fairly intense stuff. And I’ve put some videos out there. A lot of people come to see me and they say, “I’m not starting at that level.” A lot of people are beyond my level, you know, doing some very heavy resistance work.
You start where you are. That’s where you start. Even if you’re just walking right now, start there. Walk daily. Add short bursts of speed. Try getting a 10 or 20 pound weight vest or a 10 or 20 pound weight belt. Start adding some resistance. Start adding some things to what you’re doing. Work toward building muscle and incorporating high-intensity work in small, manageable doses. Over time, you’ll notice not only is your fitness improving, but your blood sugar, your energy, and your risk profile are all changing for the better.
SLEEP
Now, there was another big change that I made in my recovery, and that meant getting serious about sleep and stress management. For years, I treated sleep as optional. .. You’re not conscious. It’s sort of like wasted time, right? I’d stay up late, I’d work, I’d get up early and go run. And I told myself, I was just one of those people who could get by on five or six hours of sleep. Sometimes I’d wake up at 3 in the morning and couldn’t go back to sleep. Now, the truth is, poor sleep is a stressor. It raises your cortisol. It spikes your blood sugar and drives inflammation. They’ll do sleep studies on people and people may say, “Oh, I slept just fine.” But you see some things on the sleep study that said, “It wasn’t perfect.” For the next 48 hours, these people will have increased insulin resistance. So, good sleep is far more important than you might think, and certainly more important than I treated it.
Cortisol. If you don’t get enough good sleep, you’re starting to push your cortisol and that spikes your blood sugar, drives inflammation, all of which feed plaque growth. One problem that I discovered was that I had mild sleep apnea. My high narrow dental arch, crowded my teeth, and more importantly, it pushed my tongue back into my airway while I slept. So, if I was sleeping on my back, my tongue, as I got older, my tongue just started going back there more often. It would wake me up and I wouldn’t even notice it. That meant I was waking up dozens of time in a night without even realizing it. I addressed that with braces, Invisalign braces. They widened my arches and it really helped. But it wasn’t the only thing. I had to train myself to sleep on my side instead of on my back. That was challenging. But that one change improved my oxygen levels, lowered my blood pressure, and left me feeling more rested.
Stress was the other piece. I’d been going full throttle for decades. To me, a high level of stress was a natural thing. I had tried things like meditating and slowing my breath,
and they didn’t really seem to help. So, I just said heck with it. Now, chronic stress keeps you in fight or flight and keeps your body in a low-grade inflammatory state. It keeps that cortisol growing. I needed a way to break that cycle every day. And that’s when I started practicing slow, controlled breathing. Not just taking a deep breath, but actually slowing my breathing rate down to half of normal. You know, the normal 15 to 20 breaths. We’re not talking about going to 12 breaths per minute. We’re talking about going to 7 to 10 perspective.
From a geek perspective, this kind of breathing increases carbon dioxide slightly. That opens up blood vessels in your brain and body and it stimulates your vagus nerve, the switch that turns on your rest and repair mode. Rest and digest, rest and repair.
….
Well that seems to be a partial answer to Valerie Curren’s question about the Buteyko Breathing Technique from Sunday. — GC
….
Here’s where I learned that really slow breathing rate. A group called RESPeRATE
sent me one of their devices to try. You put a strap around your belly and you have some earplugs in and it coaches you on how quickly you should inhale and how slowly you should exhale and how often to repeat. And that’s when I thought, “Oh my gosh, no wonder my slowed breathing in the past really never helped. I wasn’t slowing it down enough.” You can do this without any kind of BOF feedback gadget like RESPeRATE . Just sit or lie down. Inhale slowly for 4 or 5 seconds. Exhale slowly for 6 to 8 seconds and repeat just doing that same thing for 10 minutes. You’ll feel a big difference just with that alone.
Sleep and stress control don’t just make you feel calmer. They have a measurable impact on your metabolic health. Better sleep lowers your fasting glucose and your blood pressure. Lower stress reduces inflammation markers. These two things alone can take a huge amount of cardiovascular risk right off the table. That’s basically the lifestyle change I did. I know it might sound very simple, but for some people it can be hard to start or even maintain that kind of lifestyle.
Consistency is key here, but as we age, our body doesn’t have the same capacity to respond as quickly as when we were young. And that’s why I want to talk about supplements. I was trained in the traditional way and the folks that I trained with, we all felt like supplements just meant expensive urine. We underestimated the effectiveness. . But after my reality check, I decided to use my prevention experience to do my own research. I did a lot of science work at Hopkins and understood how to analyze science very well. When I started looking at the supplement research, I was surprised.
I started developing opinions about the best types of supplements for prevention. So to me, supplements should fill gaps in your diet that you can’t cover with diet, support your specific needs, and be backed by evidence.
D3 & K2
One of the first supplements I added was vitamin D3. Around 5,000 international units per day. Low vitamin D levels are linked to increased inflammation, higher cardiovascular risk, and poorer immune function. But I didn’t take D3 alone. I took vitamin K2 as well, about 400 micrograms daily because K2 helps direct calcium into bones and teeth, not into artery walls where it can contribute to calcification. But more importantly, it has some role in improving insulin resistance. I predict that’s going to be shown as the research continues. There’s already a couple of studies out there indicating that.
NIACIN
Another supplement that I used to take is niacin, mostly due to low HDL. Niacin is actually the only thing supplement or medication wise that can increase HDL, decrease LDL, decrease triglycerides, and most importantly decrease LP little A.
Prescription niacin raises high-density lipoprotein (HDL) cholesterol. This is the “good” cholesterol that helps remove low-density lipoprotein (LDL), the “bad” cholesterol, from the blood. Even though niacin may raise HDL cholesterol, research suggests that niacin therapy isn’t linked to lower rates of death, heart attack, or stroke. [Of Course not /sarc-GC]
….
I also take magnesium and not just one form of magnesium. I take Magnesium L-threonatewhich is great for brain health LINK and for sleep while magnesium glycinate supports muscle function and relaxation. [Helps you sleep -GC] Magnesium is involved in over 300 processes in the body and it plays a role in blood pressure and insulin sensitivity both critical for keeping plaque stable or preventing plaque entirely.
OMEGA-3 FATTY ACIDS
KRILL
Now although I eat a lot of fish I do supplement with some additional omega-3 fatty acids. The combination of EPA and DHA, two of the most important omega-3 fatty acids, that combination has proven time and time again to provide significant benefits to lower cardiovascular risk.
Omega-3 fatty acids are well known for supporting heart health and inflammatory balance, but not all omega-3 sources are the same. Fish oil and krill oil both contain EPA and DHA, yet they differ significantly in concentration, research support, sustainability, and cost. In this article, we explain how omega-3s work in the body, compare fish oil and krill oil side by side, and review why fish oil remains the most efficient (and researched) option for most people…
Fish Oil vs. Krill Oil: Not All Omega-3 Sources are the Same
While both fish and krill oil contain omega-3 fatty acids, specifically DHA (docosahexaenoic acid) and EPA (eicosapentaenoic acid), there are important differences between the two, especially in concentration, absorption, and research support…
Fish oil typically contains higher levels of EPA and DHA than krill oil.… [AND possibly mercury -GC]
…While there’s nothing wrong with fish oil, a growing body of research suggests there’s a smarter source: Krill oil.
Here’s what you need to know about krill oil and what the science shows about its health-enhancing potential…
Though both fish oil and krill oil contain EPA and DHA, the molecular structure of their fatty acids is different in a way that matters. In krill, the omega-3s are in the form of phospholipids, molecules of glycerol, two fatty acids, and the mineral phosphorus. In fish oil, the omega-3s are triglycerides, compounds of glycerol, and three fatty acids.
That slight difference in molecular makeup gives krill oil the advantage in terms of omega-3 bioavailability: The phospholipid form of omega-3 fatty acids in krill was shown to help facilitate the incorporation of omega-3s into tissues faster and more effectively than the triglyceride form in fish. In other words, the omega-3s in krill are easier for the body to absorb, suggesting you can take about 37% lesskrill oil than fish oil to get the same benefit.
2. Krill Oil Phospholipids Offer Critical Benefits That Fish Oil Cannot.
But as we age, our cells’ phospholipid levels naturally decrease…
3. Krill Oil Has Brain-Boosting Choline; Fish Oil Does Not….
Both of these are selling supplements BTW.
…..
NATOKINASE
There are other supplements I do take, especially from time to time like aged garlic extract and natokinase, both of which have evidence showing impact on arterial plaque.
The next piece of my strategy was, believe it or not, medications. But before I go into what I take, I want to be clear. Medications are not the main driver of plaque reversal or plaque prevention. You cannot out prescribe a bad lifestyle. Let me repeat that. You cannot out prescribe a bad lifestyle. But when medications are used strategically, like supplements, in the right dose at the right time for the right person, they can help stabilize plaque or prevent it and lower risk while your lifestyle changes do the heavy lifting. Now, get ready for what I’m about to tell you because I’ve been criticized for this.
STATINS
Although, I truly believe it’s something that contributed to my results. One of the first I chose to take was a low-dose statin. Yes, I got a lot of haters for that. Not to hammer my LDL. That wasn’t my interest. My LDL or bad cholesterol, I wasn’t looking at trying to ground that into the ground, but I wanted to lower my inflammation and protect myself against recurring inflammation. You see, I knew if I had had plague, I had gone through episodes of developing inflammation. I knew I didn’t feel it. So, I wanted to continue to have a a backup for my lifestyle. I also knew that low-dose statins help with cardiovascular inflammation. So, that was my target. Most importantly, I started taking it after I found out I had plaque. Again, it’s that plaque business, because inflammation is what makes plaque unstable. And the evidence is strong that low doses of certain statins like ruba or previsatin can reduce that inflammation. I avoid the high dose approach and I avoid the more problematic statins. I for example don’t use a tobistan statin for me that meant rubatin 5 milligrams a day or even now two or three times a week.
Some of my patients are on five milligrams a week and that’s been demonstrated to have a positive impact. So you start thinking about weekly total dosages. You know, patients will come to me on 40 milligrams of versastatin a day times 7 days is what? 280 milligrams compared to 5 milligrams once a week. Totally different ballpark. Totally different universe.
ASPIRIN
I also used to take low aspirin. Let’s talk about aspirin for a minute and why I started taking it and why I’m taking something different now. When I started taking aspirin, it was recommended for primary prevention for people 65 or older and some recommendations said 60 or older. Primary prevention means you’ve reached a certain age. They’re not looking to see if you have high blood pressure or plaque or anything else. If you have heart disease, that means plaque. You’re no longer in primary prevention territory. You’re more in secondary prevention. So heart disease means you have documented plaque. If that’s your case, you’re no longer in the primary prevention category. You’re a cardiovascular patient, you’re in secondary prevention, and yes, those same guidelines say, “Yep, aspirin works for secondary prevention.” And even though it was recommended at the time I started it, I wasn’t taking it for primary prevention. I started it at the time that I discovered my own plaque because I said, “Okay, I’ve got plaque. I’m now a cardiovascular patient. I need to have a blood thinner type of impact.” and baby aspirin or aspirin 81 milligrams was what I needed. So, of course, there’s a bleeding risk. So, this is always a discussion to have with your doctor. If you notice, I said I used to take low dose aspirin.
I didn’t change it because it didn’t work or because of side effects. I stopped it for another reason. A few years later, I found out I had atrial fibrillation. It’s the most common heart rhythm problem and it’s associated with clots and therefore strokes. Aspirin just doesn’t protect it. Atrial fib raises your risk of stroke six to eight times. Aspirin does not do away with that extra risk from atrial fib. I had to exchange my aspirin for something else. It’s called NOAC, a novel oral anti-coagulant. So instead of baby aspirin, I took Eloquis. Now it’s interesting. Eloquis has shown a similar protection profile for heart attacks as low dose aspirin but a much much better risk reduction for strokes associated with atrial fib. So that’s why I made the switch in the mid-60s.
I started, well actually in the late 50s I started developing high blood pressure. I started years ago with Ramipril. It’s an ACE inhibitor. And again, you don’t need to remember the term. It’s just a type of blood pressure medicine that doctors were just beginning to use. They had used it quite often, but not so often for frontline high blood pressure management. I eventually switched to Lartin. It’s an RB. It’s similar, but different. And the problem was I was having a cough with the ACE inhibitor. Keeping blood pressure in the optimum range is another way to protect your arteries from damage over time.
I do use a low dose and it has helped me both keep my numbers down and steady and the key thing, protect my kidneys. The point is every one of these medications was added for a very specific reason based on my test results, my risk profile, my examination components like my blood pressure. And I review all these things regularly. If a medication isn’t helping or the numbers improve to the point where it’s no longer needed, I make a change, just like my patients do.
SALES PITCH
Medications are tools. They work best when they’re targeted, monitored, and used for support, not to replace the real drivers of cardiovascular health, your exercise, your sleep, your stress control. So, that’s my story in a nutshell. Remember, I was going to tell you about that one piece of the puzzle most people miss, even more important than lifestyle. But there’s one more thing I like to keep track of. If you’re ready to take prevention seriously, I want you to know you don’t have to keep struggling with a medical system that just pushes pills and doesn’t listen. I see so many people trying to figure this out on their own. And while it’s good to do your own research, we do a lot of stuff like that e-book to help support people who are figuring this out. In fact, if you just leave all the decisions to your doctor, you’re likely to get a lot of unnecessary procedures. It’s good to do your own research, but going solo, completely solo, that can lead to blind spots and mistakes that can put your health at risk. And so, this is where I’ve dedicated my career.
I was formerly trained in prevention and eventually ran the program, as I said, at John’s Hopkins, training the other doctors there in prevention. I know the strengths and the limits of traditional preventive medicine. To make this care more accessible, I’ve personally trained a team of clinical advisers. They take the same approach I do. Listening carefully and looking at the real drivers of heart disease and plaque, inflammation, and insulin resistance, not just the numbers most doctors stop at. And no, we don’t just do an LDL, bad cholesterol, and call it a day. When you call and you get more than an appointment, you’ll get guidance and support designed for your situation, your numbers, your goals.
You’ll finally have somebody in your corner helping you make the right decisions. If you’re ready to move beyond that kind of frustration and get prevention that actually work, here’s what to do now. If you’re interested in working with us, click the link in the description. Or call the number on your screen and one of our people will give you a call. They can or will take the call and can talk this through with you. And like I mentioned before, get your free copy of my seven step heart attack prevention program so that you can learn more about your risk, how to fix your metabolism, and reverse arterial plaque. Just click the link below and there it is.
Purpose. I’ve done videos on that and the videos admittedly are just not that popular. People think, “Oh, that’s just woo woo fishy stuff.” Woo! Purpose is not woo woo fishy stuff. When I got that first CIMT scan and I saw arteries of a 73y old at age 57, for me it scared me. But the truth is fear alone doesn’t keep you going. For me, my purpose was twofold. First, I wanted to be around not just alive, but healthy for the people I love. Second, I wanted to turn my own wake-up call into something that could help other people avoid a heart attack, stroke, blindness, kidney disease, erectile dysfunction, cardiovascular disease, the vascular part of cardiovascular disease. That’s why I shared these scans, these numbers, and the steps I took. I know what it feels like to think it’s too late, and I know the relief of realizing it’s not. When you have a clear purpose, the daily choices get easier.
You want a purpose that’s bigger than how I feel today. And a purpose that’s bigger than, well, this is what my doctor told me to do. You know, I think I’ve retired three, four, five times. Maybe more times than I can count. And I always come back to just sharing knowledge. It’s the type of knowledge I think will help people find hope and avoid heart attacks and strokes, make people’s lives better. Your purpose is the anchor that keeps you steady when life gets messy. When you’re tempted to fall back into old habits. If you don’t have that purpose yet, take some time, think about it, it’s the most important thing you can do. Because once you know why you want a longer, healthier life, the how to get there becomes a lot more doable. Finally, I know more about what to eat to reverse arterial plaque. If you want to know more about that, check out this video right here. [Points to link on screen]
There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: Yours Truly has checked today’s post for any AI-generated content. To the best of her knowledge and belief, there is none. If readers wish to post any AI-generated content in the discussion thread for today’s post, they must cite their source. Thank you.
Do not forget to LABEL AI articles video and such.
Elizabeth Bright DO, ND, a graduate of Columbia University, is a highly respected American Osteopath and Naturopath living in Italy. She is former Chef-owner of Coppi’s Organic and The Vigorelli Restaurants in Washington, D.C. She is a master in Chau Ka Kung Fu. She has been eating a high-fat carnivore diet and has been using it as a treatment modality since 2016.
She is the author of Good Fat is Good for Women: Menopause
Website: https://www.elizbright.com/
Dr. Elizabeth Bright—a renowned physician specializing in thyroid and adrenal health—reveals the pivotal role these small but mighty glands play in every stage of life, from before birth to your later years.
If you’ve ever been told your labs are “normal” but you still feel off, this book will open your eyes to the real science of your metabolism, energy, immune health, and stress resilience. [Amazon blurb]
FWIW from Brave AI
Osteopathic medicine is a distinct branch of medical practice in the United States that emphasizes a whole-person approach to healthcare, focusing on the interrelated unity of all body systems and the patient’s ability to self-heal.Doctors of Osteopathic Medicine (DOs)are fully licensed physicians who, like MDs, can prescribe medication, perform surgery, and specialize in any field of medicine.
A few tidbits of information relevant to the video I am featuring.
…it is known that bromated flour, which contains bromine, has been used in the USA since 1914. In 1982, researchers in Japan published the first of a series of studies showing that potassium bromate, a food additive used in baking bread, causes cancer in the thyroids, kidneys, and other body parts of rats and mice. As a result of these findings, countries around the world banned the additive, but the U.S. Food and Drug Administration held back, in part because the amount of potassium bromate that remains in bread after baking should be negligible.
Hubby, reminds me that King Arthur flour is unbleached & unbromated. I wonder if bromine is NOT listed because it is not in the ‘bread’ just in the flour used to make it AND the FDA held back, in part because the amount of potassium bromate that remains in bread after baking should be negligible.
“…the vast majority of cholesterol in your body was made in your liver. Cholesterol production increases when the body is under stress: emotional stress can cause elevated cholesterol because the stress hormone cortisol is made out of cholesterol. Physical stress on the body can also elevate cholesterol.
Because cholesterol helps to repair and heal your body, you will produce more if there is a great deal of inflammation occurring in your body.So all those factors above that raise inflammation, can raise your cholesterol too…”
[worth reading the entire article. –GC]
33 minute Clip:
The SHOCKING TRUTH About Iodine! (Nobody Shares This) | Dr. Elizabeth Bright
Full Interview (1 hour 18 minutes):
Your Body Is BEGGING for Iodine (How Much You Actually Need) | Dr. Elizabeth Bright
ROUGH TRANSCRIPT of VIDEO.
I know this is very long so I am cutting out parts that do not directly impact the subject of iodine. The parts I think are really important or are novel such as A1 & A2 milk cows and dairy causing inflammation, I will use pulled quotes to highlight to make it easier to skim and get the meat of the article.
The person doing the interviewing is Jesse Chappus, a retired chiropractor. He is questioning Dr Bright. I am not going to go back thru and try to add the attributions. Hopefully the question marks will make it fairly clear.
BEGIN TRANSCRIPT
“Every single cell in the body needs iodine. Every tissue needs iodine. Iodine is an antibacterial, antifungal, antiviral. It’s a heavy metal chelator. It’s my shield. We use more nutrients when we’re in a state of stress. If your body’s fighting an infection that is a stress state, you need more iodine. It boosts your immune system. Your immune system needs iodine, the substances that interfere with the absorption of iodine. Fluoride, chloride, bromide. So that is really why people need to supplement, because they have been exposed to substances that prevent the absorption of iodine even if they can get in their food source, which they can’t really.
There are places in the world that have too much fluoride in the ground. Certain places in England. Where tea is grown [in] India, China. I don’t think there’s any way you can get away with drinking black tea, white tea, green tea… I lived in China, so I had access to the best teas in the world. I would consider all of them to be poison today.
…………….
WAIT WHAT? My morning tea is full of fluoride? -GC
The fluoride content in tea varies depending on the type of tea and the quality of the leaves used in its production. 135
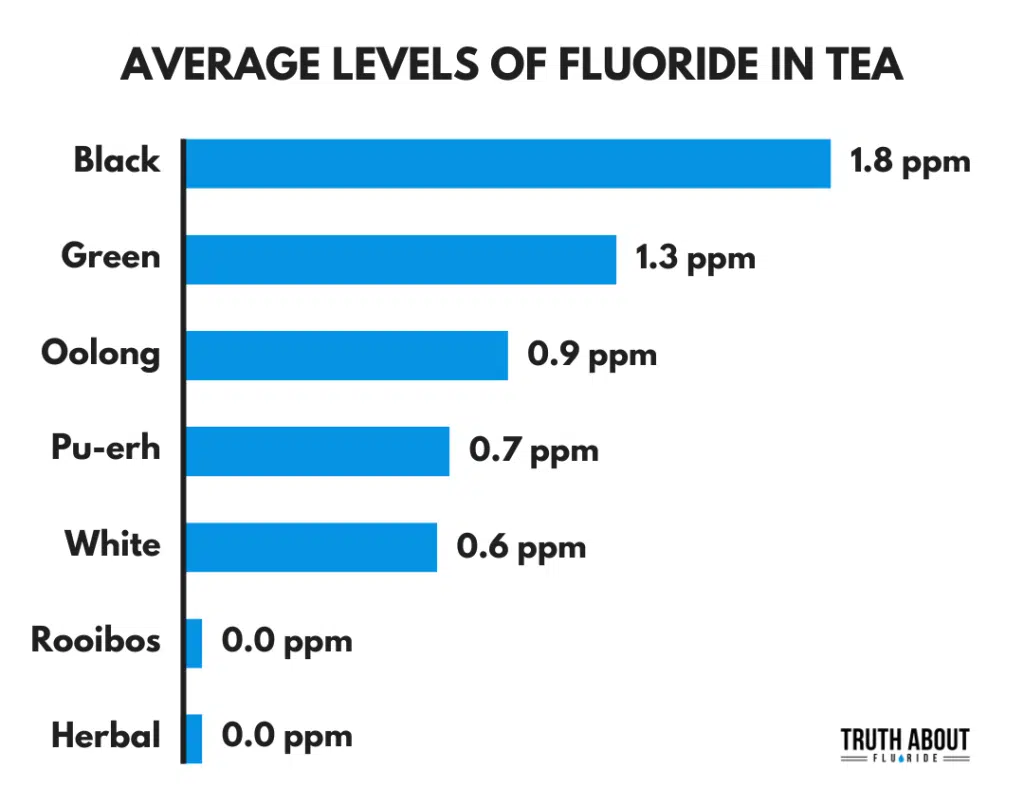
Black tea has the highest fluoride content among the types of tea. The average fluoride levels in black tea are 1.8 ppm, with the highest recorded levels reaching 4.2 ppm. 1
Green tea also contains fluoride, with average levels of 1.3 ppm, but the highest levels recorded were 3.2 ppm, and the lowest were 0.7 ppm. 1
Oolong tea has fluoride levels that are generally comparable to those recommended for the prevention of dental caries. 2
White tea is likely to have less fluoride than other types of tea, as it is made from the buds and youngest leaves of the tea plant. 23
The fluoride content in tea is not uniform. The plant stores the majority of environmental toxins and minerals in its older, mature leaves, which are used in cheap teas. These leaves are cheap, provide bulk, and produce a dark, strong liquor. However, they also act as a reservoir for fluoride. 3
The origin of tea and environmental factors, such as pollution, groundwater, air, and the soil in which it was grown, affect the amount of fluoride that accumulates in the plants. 5
Excessive fluoride consumption is linked to skeletal fluorosis, a condition that stiffens joints and compromises bone health. 34
“The problem is that nobody’s doing the “Hakala Lab” tests. They’re all going to their local lab and they’re testing radioactive iodine. They’re all looking for Chernobyl. None of these iodine blood tests that you get are testing organic iodine. They’re testing for radioactive iodine.”
Each kit has the option to add bromide, fluoride, and/or chloride.
We are able to ship kits internationally (except to the UK).
If you are ordering a kit for a youth, under the age of 18, please call/email us or enter their age and weight in the comment section to receive correct load dose. We cannot analyze loading tests for children under the age of 12…
This test kit is available for purchase in all states, except New York and California.
…..
Back to the Transcript
[Discussion about carnivore diet removed]
Not eating enough fat… Actually, women need more fat than males do to make more steroid hormones. …. I’m talking about adding additional fat to that meat because the fat is an anti inflammatory. So people who come to me have inflammation… So if somebody’s cooking up a steak, they’re putting say butter or tallow on top of that at the end. Say it’s ground beef and they’re making burger patties, same kind of thing, adding butter and tallow. …burgers are pre-digested in the sense that the blades that grind the meat have altered the protein somewhat. It’s not horrible. It’s just that the steak is going to have more nutrients. Because when you cook a steak, if you’re doing it medium, I’ve weighed it, when you do it medium rare, there’s 25% of the weight gone. Some of that is fat that stays in the pan or comes down into the grill tray and some of that is water soluble nutrients. So ground beef, you’re going to have fewer. It’s pre-digested in the sense that it has already gone through this process of being ground up.
….you brought seed oils in and you also talked about some of the quote unquote healthy plant fats such as coconut oil… I forget what specifically ones you covered there. But typically in that category would be like avocado oil, olive oil. I want to make sure we have a distinction there between the seed oils and those oils, because the seed oils are in a category of themselves that no matter what diet you’re on are considered toxic.
So seed oil soils are canola, peanut, it’s not even a seed. Those are the oils that we know are trans fats. These fat’s are very, very, very inflammatory.
The olive oil wouldn’t be inflammatory, but it’s not going to give you cholesterol. Avocado and coconut oil are not going to give you cholesterol. And the cholesterol, the molecule only comes from animals. But arguably, if you’re using your volume of food intake and calories with those other fats, you’re taking up valuable space that you could use for healthy animal fats that come along with cholesterol…
…There are some people who are so inflamed — or have an immune system which has turned autoimmune. The tiny amount of milk protein in the butter could be temporarily a source of inflammation for them. They will eventually put the butter back in when they are better because it’s really the dose of the poison. It’s the milk protein that is the issue for the immune system. Just like gluten, …your immune system is looking for proteins. It’s looking for viruses, it’s looking for bacteria. They’re all made out of protein. So if your immune system has become autoimmune because it’s so inflamed, it will mistaken that the small amount of milk protein in the butter [as an enemy] and cause you to be inflamed…
… I know in general you’re not a big fan of supplements, but would that be something you’d ever consider?
….You have to be careful with all supplements because they’re basically very potent, small amounts of things that we’re just supposed to get from our regular diet. As you said, there’s one liver and the rest of it is muscle meat in an animal that you kill.
…But one supplement you’re a huge fan of [is] iodine … I want to come back into that.
Iodine. There’s a lot of detail we can cover within this subject. For people at this point who aren’t supplementing with iodine, talk about the current landscape and what they’re not getting from the diet… and why iodine is so beneficial….The issue today that is more – concerning are the substances that interfere with the absorption of iodine. Fluoride, chloride, bromide. So that is really… why people need to supplement, because they have been – exposed to substances that prevent the absorption of iodine, even if they can get it in their food source, which they can’t really.
You mentioned the other halides and how they can get in the way of absorption of iodine. Where are those typically found?
Your toothpaste, water, if they’ve put fluoride in your water. Chlorine in the pool, bromide in my chair. Probably this fire retardant substances, fabrics, things like that. Car seats. People aren’t licking their car seats. I think it’s more the fluoride that’s in the water and “PFAS” [Perfluoroalkyl and Polyfluoroalkyl Substances -GC] which are in our water that we can’t escape. There’s “PFAS” in the Maldives, so where are we going to go? We can’t go anywhere… We shouldn’t be running for the hills. We should be taking iodine to prevent insufficiency.
And as you explain that, I can see this is a double negative where, the other halides are so apparent in today’s modern world, affecting our iodine absorption… And then the one halide that we want to get isn’t readily found in the food anymore. So it’s hitting it from both ends.
That’s correct… Iodine is an essential nutrient. Chloride, bromide and fluoride are absolutely not. Fluoride being the one that is highly touted as something that prevents your teeth from deteriorating. But this is not true. It was never proven. There’s actually evidence to the contrary,that it causes fluorosis and makes your teeth rot. Which is what the fluoride content. And actually natural water sources. Fluoride is a mineral that is in the ground. So there are places in the world that have too much fluoride in the ground. Certain places in England, [places] where tea is grown, India, China, those places, the well water is very, very rich in fluoride. And those are the people, those areas, [have] a lot of congenital hypothyroidism, —– dwarfish, low stature, I think is what you’re supposed to say today. And learning disabilities, and of course, goiter.
Let’s talk more about that tea please.
So the tea leaves are being grown in soil that contains fluoride. So the end product that is dried out and shipped and packaged. You’re getting that, when you steep your tea, you’re getting that put back into the water? Yes, yes. And the cheaper teas have more fluoride than the more expensive teas. They have an actual rating system of how much fluoride is in the tea. Brick tea, loose tea has a lot more fluoride than your more expensive brands. It’s kind of like selenium, Brazil nuts… People think that they’re going to get selenium from Brazil nuts. There are areas that have more selenium in the soil. And those trees, the nuts of those trees will have more selenium in them than the other ones. But tea, it has a certain acidity that people like with tea means there’s more fluoride in it. So they [are] actually augmenting the fluoride by breeding and things like that to have the tea have more fluoride in it, so it has more acidity in the flavor. [And if you think the Chinese are not doing that breeding on purpose I have a bridge for sale. –GC]
All right, so cheaper teas, more of an issue here… How big of a problem is this in general? And is there specific types of tea people can still drink and not worry about this?
No, it’s [tea is] poison. So it’s a huge problem. I actually gave this paper to somebody in the UK. An Irish researcher published a warning to his country because they have mandated fluoride in the water. And the Irish drink a ton of tea. So there’s a huge rate of learning disabilities, fluorosis, fractured bone, osteoporosis, et cetera, et cetera, — everything that fluorosis causes, in Ireland. So I don’t think there’s any way you can get away with drinking black tea, white tea, green tea… I lived in China, so I had this access to the best teas in the world. None of them. I would consider all of them to be poison today.
…For somebody that’s been drinking a lot of tea in the past, is there a way to test to see how much of it’s accumulated in the body?.. And also, can you test teas for somebody that’s in love with their tea right now, doesn’t want to give it up and wants to just see if their particular blend, this is an issue for, even though it’s such a big issue in general. Can we test the tea? Can we test the body?
Fluoride in tea is one of the most forgotten and largest sources of fluoride. Some teas can even have 6 times the amount of fluoride when compared to tap water. So to find out which teas are safest, I tested 357+ teas for fluoride. And below you can search the results, learn how to avoid it and everything else about fluoride in tea.
If you love tea and have the cash to spare, go to the website and leave him a tip. – GC
….
Back to the Transcript
You can test the body. You can test the fluoride, bromide and chloride content in your urine and test the iodine. How much iodine is not able to come in because of these halides blocking the absorption of iodine. “Hakala Labs” in the US does that 24 hour urine uptake. You collect your urine for 24 hours, after ingesting 50 milligrams of iodine. You collect the urine, they test it and they give you… the results of how much bromide, the toxicity of halides, [are] in your urine, in your system. The teas, this Irish paper, actually I have found, — all the brands, he went through all the Irish brands that are popular.
… I have a couple of papers from China that did test the fluoride, not in particular teas. Yes, in teas. I actually have, because there’s Anhui province and there’s different provinces that- they did test…
….
[So China is well aware of the fluoride problem in the teas and yet they are breeding teas that will increase the uptake of fluoride from the water. –GC]
….
Any other plants that are prone to this, taking the fluoride and… concentrating it in the product?
“Tea is the worst one. Yes.
So coffee, not an issue?
Coffee, not an issue.
No other plants people are eating? Well, there are plants that prevent the absorption of iodine… Brassica, cauliflower, Brussels sprouts, kale, all those plants, that whole family of plants, they figured that out because the farmer went to check his rabbits and they were all eating cabbage leaves and they all had little goiters… The scientists went there and isolated basically what is in today’s antithyroid medication — from these plants. So it prevents, it is a antithyroid medication. Antithyroid substance because it prevents the absorption of iodine. So in my book, “Good Fat Is Good For Girls, Puberty and Adolescents”, I actually do list more – foods that we eat. Oatmeal is another one that prevent the absorption of iodine.
Any others you can think of off the top of your head?
Flaxseeds.
… Let’s talk about why iodine is so important.
Every single cell in the body needs iodine. Every tissue needs iodine. So your adrenals need iodine, your salivary gland, — the male’s prostate. Not just the thyroid. Female uterus, ovaries, breast tissue. – Every mucus bearing tissue has a ton of iodine in it. So your intestinal [tract]. — The microbiome stuff that people are always talking about. Not going to happen if you don’t have adequate iodine — in your intestinal mucus. Iodine is an antibacterial, antifungal, antiviral. It’s a heavy metal chelator. That’s why I said it’s my shield. The thyroid takes a minimum of 6mg. The breasts in females take 5mg. Can’t remember how much the prostate takes. I would consider any cyst in these tissues, any growth, any inflammation due to iodine deficiency.
And from last time we talked, the ideal dose of “Lugol’s,” as you recommend the “Lugol’s.” For maintenance, was two drops of 5% per day.Is that still correct?
Maintenance after you have. Yes, if you have had. I have women who come to me with swollen lymph glands. – Fibroids in their uterus. I will have them douche with iodine… So you’re actually getting it closer to the tissue that needs the iodine. If you’re taking it orally, that’s why “Lugol’s” is better, because it’s much more easily absorbed. You’re taking it… Everybody’s going to fight about the iodine if you are severely deficient. So sometimes it’s better to just get it. People paint their breasts with iodine.
And when it comes to time of day to take it, does it matter?
Is it better earlier on in the day? With food? just details on to best absorb it.
. I would say earlier in the day we are supposed to peak between 6 and 9. All our hormones kind of peak at that time. So you’re waking up bright eyed and bushy tailed to greet the day. I would take what you need in the morning. There are people who have inflamed thyroids that might react to the two drops that I’m saying you should take. So then you need to see if you’ve got nodules or thyroid antibodies.
Explain that in greater detail. What you’re saying there is if somebody already has a problem in the thyroid, if they activate that by taking “Lugol’s,” they might run into problems because of that. Otherwise iodine isn’t something we need to worry about. The kidneys will remove excess, correct?
Correct. Now imagine the tissue that has been devoid for a long time. So that could be the uterus, that could be the ovaries, that could be, the breast tissue. But usually the thyroid, because the thyroid is all follicular. Every part of the thyroid is working. The follicles are always there to make hormones. So breast tissue is not that way, uterus is not that way, prostate is not that way. So if it hasn’t had the iodine, if it’s kind of hunkered down and it hasn’t been producing adequate thyroid hormone because it doesn’t have enough iodine and it has maybe grown an extra piece, expanding itself trying to get more iodine. That extra piece or that inflamed thyroid will sit up and take notice and scream at you.
And how will somebody know if that’s the case?
Palpitations. They might have hyperthyroid symptoms, but they desperately need the iodine anyway. So then we do a detox.
Okay, so let’s say somebody finds out they have one of these nodules, they need to stop taking the dose you’re recommending here. How do they, or can they go about healing that?
They can definitely go about healing that [nodules]. I always recommend they do the salt loading protocol by taking… a small amount, one drop of iodine in a glass of half teaspoon of salt, and a little glass of water, followed by a whole bigger glass of water until they have to urinate. Because this is the way that the iodine will attack and the salt will pull the other halides out of the system. And so that’s a detox.
Dr Bright
Iodine becomes vapor if it’s attached to salt. Okay, so is that more a protocol for somebody that’s new to iodine?
I was getting at the person that has some kind of growth on the thyroid, and then they’re having a problem taking the iodine.
What you just explained there seems like a flush for anybody that wants to… basically get everything to ground zero. “Mmmhmm.” The part you just explained there, is that for everybody or just somebody with a nodule?
No, I think it’s for everybody, but definitely somebody with a nodule because they are — not able to have, their system is already so — deficient in iodine — that part of — their tissue might react. So it’ll start working. — And just it starting working can possibly make every single organ in the body. The heart is very much. So epinephrine is always telling the heart, the rhythm to beat. Right. And that comes from thyroid hormone. So if all of a sudden there’s more thyroid hormone than your body has ever dealt with, hasn’t dealt with in decades, everybody kind of has to get in line and figure out how to use that hormone again. It’s like resistance.
Okay. So, yes, it is a flush. And what I’m talking about isaddressing also resistance to the hormone that is made. But for somebody with a nodule on the thyroid doing the flush, will that physical nodule dissipate over time?
Over time, but not just with the flush, but definitely over time, you have to remove inflammation. You have to make the autoimmune…
This is an autoimmune state, right?
So the immune system is actually attacking it. There’s a combination of… the thyroid is expanded in order to get more iodine, the thyroid also, has got scabs on its knees. — It’s being attacked by antibodies. You don’t have to have positive antibodies to have an inflamed thyroid. So the inflammation, they could just look at an ultrasound and tell you that you’ve got speckled thyroid tissue. The fact that there it’s hyper-vascularized. That is the definition of inflammation. Your antibodies might be negative, but your thyroid tissue is inflamed so… an anti-inflammatory diet, removing carbohydrates, et cetera will definitely help that too. It’s crucial.
From people you’ve worked with, do you find somebody with a nodule, most cases can remedy that without surgery then?
Yes, absolutely. What is difficult to remedy without surgery, just like somebody who maybe has a foot long fibroid. Right. So there is a point where you can teach the body tissue, anomalous tissue to regress. There is also a point of no return. A very large goiter may need surgery. It’s kind of hard to make that tissue that has become also calcified to some extent to regress. But definitely… all of my patients, goiter is more difficult. A very large softball size goiter is going to be very difficult. But inflamed thyroids, smaller goiters, they’ve all regressed. And nodules, they regress.
Essentially, is a goiter, just a nodule that’s grown out of hand?
Both. It’s also the — thyroid itself enlarges. All the follicular tissue will enlarge. So inflammation. Now “Hashimoto’s” is the lymph tissue in the thyroid is swollen. Okay. So we know if there’s a small nodule, good possibility following… doing flushing and the lifestyle we’re talking about today, they couldreverse it.
If somebody has a full on goiter, can they reverse that naturally or no?
It depends on the size. It really depends on the size. — A very large goiter that has become calcified.
How can you?
You can’t. — — That’s why they do the ecogenic testing. They send sound waves to the thyroid to see how fast the sound wave comes back. If it comes back very fast it’s hard, it’s calcified. If it comes back slowly, it went “voof” into the thyroid which is just a big bloody mass of follicular tissue. So you want it to be a big bloody sponge.
If it’s got hard pieces on it that are calcified, how can you. — You can regress a cystic vascular mass. You can’t regress a hardened piece of tissue. Makes sense. So for somebody in that case where it’s just earlier stages, there’s nodules forming, but they’re small, they’re still in hope that they can reverse. You mentioned that protocol with the salt. Are they doing that daily along with the lifestyle or how often would they do that?
No, they’re just doing that for a week and sometimes they get diarrhea because stuff comes out. I have… many teenagers now who have thyroid nodules. Nobody’s checking kids because they’re just looking at “TSH.” So you can have rheumatism, you can have other autoimmune conditions, and they’re not going to look for it because — they don’t associate… those conditions with thyroid issues like I do. So if you are 70 years old, — it may take more time to – change this tissue that you’ve had… Because most people, most women become hypothyroid because of adolescence, which is what my second book is about.
odine is so necessary to have a healthy puberty, both male and female, but really, really important in female. But by the same token, I have more and more males today as patients. As I said, I have adolescents, pubertal young people who have thyroid issues. If you look at how the body has tried to heal since you were 12 and you’re 70. We’ll do the best we can. But if you have a softball sized goiter, I don’t think that we can make it shrink.
Dr Bright
For somebody right now who is a young adult feeling healthy, but they haven’t been supplementing with iodine to this point. It sounded like, but I want you to confirm doing that flush would be a good idea for them as well? And if so, how many times, if they’re not suffering right now?
I have a lot of people’s kids. — – The flush is… you could do…
My son is going to go to a pool because he hurt his back and mom is an osteopath, but she’s not in Athens. So he’s been given some exercises by an osteopath locally and he’s going to go to a pool. And I said, honey, triple your iodine intake because he’s going to go in the chlorine pool.
So I would say that… it sort of depends on the situation. It depends on your environment. – But what I’m talking about with females is that we are parents are now conscious of precocious puberty. We know that precocious puberty is bad for adulthood. There are mental health implications involved. Iodine supplementation as a child is important to prevent that.
So you gave that example there of your son going into a pool, upping his shield of iodine before going in. I would assume that would translate to any situation where somebody is going to come in contact with a lot of halides, if knowingly they’re going to be doing that, they want to up their iodine beforehand?
Yeah. And I do it when I travel. Any infection… — I have a cold. – Double your iodine. Because iodine, all nutrients… disappear. We use more nutrients when we’re in a state of stress. If your body’s fighting an infection that is a stress state, you need more iodine. And then it’s also an antibacterial, antiviral. So that’s great. It helps. It boost your immune system. Your immune system needs iodine. So, – we regularly travel and when we travel, we take more iodine. And then if somebody has a cold.
I talked to my daughter today, my grandson has a cold and.. she’s nursing him. Honey, it’s not enough for him to get the iodine from your breast milk. Get him to have a couple of drops of iodine. He’s two years old. Okay.
How young can somebody start to take… iodine orally?
Well, I’ll just say my grandson is going to be two in January. He needs iodine. So I want her to somehow get [it into him.]. We were trying to figure [it] out. Brainstorm how to get it in him because he doesn’t drink juice. He’s getting it from her breast milk, but not adequately. — She’s very busy. There’s — stress and – she’s, I don’t know, she can put it on a piece of meat.
Right. But what I’m getting at is you mentioned two and you wanted him to get some. But for a baby, like newborns, should they be supplementing or do they get enough through the breastmilk?
No, no, no, no. – My daughter has been taking a lot of iodine and he’s had enough, Babies who are nursing. but he’s now older and he’s eating more regular foods… So nursing is enough.
So through childhood, say somebody ends breastfeeding at 3, they’re eating solids. The parents are aware of what we’re talking about today and want to make sure they’re getting enough iodine into the kid. We talked about that two drop dose, but that’s for adults… Is that a good dose for kids as well?
I would say one drop. But again, like I said before, highlighting the fact that the kidneys can remove excess.
There is so much fear around iodine.
That’s why I want to get into the nuance here. It is a water soluble nutrient. So it’s not like vitamin D, it’s not like vitamin A. It’s not like, except for selenium. You can be toxic in selenium. That’s why I don’t recommend supplementing. But iodine is a water soluble nutrient. And all my books from the 40s and 50s measured the kidneys. They measured, they checked, they tested people’s urine. So they did all this research for us that tells us that iodine excess comes out in the urine. And the problem is that nobody’s doing the “Hakala Lab” tests.
They’re all doing the local lab and they’re testing radioactive iodine. They’re all looking for Chernobyl. None of these iodine blood tests that you get are testing organic iodine. They’re testing for radioactive iodine.
For somebody like you that’s been on iodine for a long period of time, you’re fully topped up… Do you ever do that salt protocol that you talked about?
I haven’t in years, no. No. I stopped drinking tea. I did it when I. — Years ago, I was drinking a lot of tea. I was going back and forth to China. No, I don’t need to do that.
Okay, so you already talked about a week. If somebody has nodules, they would want to incorporate that. And then for somebody who is a healthy adult about to begin an iodine protocol like you’re talking about here. Would they just want to do that salt protocol one or two times to flush everything out?
I put it on the protocol because most of my patients are drinking, a lot of them are drinking tea. In the US it’s iced tea. They think that it’s healthier than coffee. They write decaf tea. So that’s why I put it on their protocol because we got to get rid of the halides from the tea… I had a patient from Kazakhstan. — The iodine content in the soil of where this person was from. People from Michigan. I’m gonna. Okay, yeah, — maybe you need more. Maybe that’s why. My family’s from Tennessee. The mountains are devoid of iodine. It’s sort of a regular thing that I have people do now. It’s not some people, as I said, they get diarrhea. – – Some people don’t want to do it for a week. One person asked to do it for less because theywere afraid of the salt. You have this whole hypertension fear that also comes with salt. –
A whole other — context. We talked about best time to take it, it sounded like that would be sometime in the morning. What about spreading the dosage out throughout the day?.. 2 drops, say taking one in the morning, one around dinner time. Any advantage there?
I don’t see it.
Any advantage including that in the food of a pet?
Definitely… You know that “J Crow’s” is geared towards animals anyway. They don’t want you to think that they’re selling it to human beings for horses. Right. — We know that there are tons.
Hypothyroidism is huge in pets today, dogs and cats, because of what we’re feeding them. I used to give my dog iodine. For somebody who has… autoimmune thyroid issues, “Hashimoto’s” specifically, there is a lot of fear. There’s already fear about taking iodine in general… And then there’s another additional layer for people in that category.
When you’re working with someone with “Hashimoto’s” is the protocol any different with iodine?
No. And I explain all of this. I go into – – I’ve researched all of this and I explain in my article on my articles page about why there’s this fear today. “Theodor Kocher” won the Nobel Prize in, I don’t know, 1911, and he had a reaction to sodium iodide. He might have also been taking who knows what other kinds of stuff. So he kind of started the anti-iodine thing. He’s the one who associated iodine taking iodine with hyperthyroidism. At the same time, every single physician was giving iodine to their patients. And then they all of a sudden stopped. Because he was a big guy, he just won a Nobel Prize. Everybody thought, oh, and people complained, other, other doctors complained that now iodine has been given a bad rap. And then they started using it again… to calm down patients when they were calmed down. Actually, it’s associated with hyperthyroidism. When they were cutting out people’s goiter, they would give them a ton of iodine to… make the heart not beat too hard. So it came back into favor clinically. But unfortunately, these were surgeons who love cutting stuff out and they were still geared towards cutting out goiters rather than healing them. So we have documentation of somebody like “Krile” saying — people who have… inflamed thyroids, give them iodine and natural desiccated thyroid. And it will shrink. So I have to go into all this. There’s so much… documentation that I have to explain when we talk about this and I do that in my articles.
Dr Bright
Does somebody need to ease into it though more if they have “Hashimoto’s” taking the iodine?
No, no. Your thyroid is inflamed. Remove the carbohydrates, remove the tea. Remove all these things that you’re doing… Maybe you’re running, maybe you’re doing “CrossFit,” maybe you’re all those things that are raising cortisol levels will also cause your immune system not to function properly. It’s not the iodine. Everybody has to take iodine.
Dr Bright
Okay. I just thought there might be some nuance there with dosages and easing in and somebody who is, their thyroid’s under attack and at least has a certain amount of damage at that point.
Some people have symptoms and some people don’t… Some people have positive antibodies and they don’t have. They don’t react to the iodine. I’ve had patients react to the iodine with palpitations who had no antibodies. It really goes with, you have to address each case individually. There’s not a hard and fast rule for people because some people don’t react and some people overreact. And then we do the flush and then we go very slowly because of resistance.
Are there any other supportive nutrients somebody wants to make sure they’re getting with the iodine that complement that as they’re turning their thyroid back on?
No, they’re all in food. So you have this famous co factors of selenium and zinc and “yada,” “yada,” “yada.” I’m sorry, I don’t think any of that’s necessary if you’re eating steak because all of those are more bioavailable in the ruminant meat that you’re eating.
Okay. Important caveat there though, for somebody who is eating the way you’re talking about, which for a lot of people is extreme and won’t be going to that level. “Mmmhmm.” “Mmmhmm.” Which is fine.
ZINC & SELENIUM
Everybody has their own journey. Sure, sure. And yeah, it’s for them to decide. But I just think it’s important we highlight that’s if you’re consuming a carnivore diet, which is heavy in ruminant animals. Well, the thing is that supplements can be toxic. So selenium is very easily toxic. I talk about in my book “Good Fat Is Good For Girls.” — You need a lot less selenium. Selenium it is 200 micrograms is usually what people are taking or told to take, and — that’s too much because selenium is easily toxic and too much selenium actually prevents the thyroid from making hormone. So I just don’t like supplements because you’re getting this huge, — it’s like taking a club to your nutrition rather than allowing your body to decide, I’ll go to the market and say, I’ll have a little bit of this, I’ll have a little bit of that. I’ll need a little bit of this. And it’s in the form that the body recognizes rather than hitting it over the top of the head with – 100 milligrams of zinc. This ties back to what we talked about before with the organs, where if you’re consuming those in supplement form, you might be pushing a lot more in the body than needed.
VITAMIN D
Yes. I wanted to talk about vitamin D. We got into this last time and listening back afterwards, I realized I needed clarification, so I’m sure other people do as well. You’re not a fan of supplementing with it. You don’t feel the sun has anything to do with our level of vitamin D in the body.
Right. Well, let’s start there because it’s an underlying assumption by basically everybody that vitamin D, our main source is sunlight. Talk about where we got that wrong. We got that wrong when they took away our fat. So nobody was making you stand outside getting a half an hour of sun on your skin pre1980s… you can go to “Ngram Viewer” and look up this stuff, see when it started to be written about, when it started. I do that all the time with things. – Inuits don’t have vitamin D deficiencies. They don’t have — illnesses that are associated with low vitamin D because if they don’t go and eat “Pringles” from the store that people brought — they are living on seal and it’s very fatty animal. That vitamin D is a fat soluble nutrient that comes from the food they’re eating. It’s all very new. And the 70 the magic number 70 that I’ve learned in school is not. I don’t think you need that much. Most of you have to remember, most people are coming to me knowing that I’m a thyroid specialist. They probably have thyroid issues. Most of them do. And if you are hypothyroid, you can’t synthesize nutrients anyway… So you need adequate thyroid function to be able to turn that animal fat into vitamin D.
Okay. A lot more I want to get into within this to make sure I fully understand. So are we saying that vitamin D, which I would totally agree with, you can get it through at least certain foods, but are you saying that the sun can’t provide vitamin D or it’s just not what we should rely on?
Okay, so the sun hits the lipids on our skin and that is supposed to turn it into vitamin D3. The synthesis that happens through… lipids. Okay, so, – — it actually doesn’t work that way… It may work that way. It’s sort of a backup plan because nobody’s eating fat. If you’re not eating fat, maybe. I’m in the sun all the time. – If I weren’t in the sun all the time in Scotland, for instance, I’m not going to be eating vitamin D. Most people say, oh, I’m taking vitamin D seasonally because of the sun. I haven’t looked it up recently, but I’m sure if I did a deep dive into it, I could tell you the year just like I did with folate. We don’t need folate either. The year that they started… pushing this through. I’m sure this came after the cholesterol hypothesis, because the only way you can get vitamin D, vitamin A, any fat soluble nutrient, is if you eat that damn cholesterol.
Okay, the way I understood it before talking to you, we can get vitamin D, obviously from a supplement. We can get it through certain foods and then we can get it through the sun. And the way I’ve looked at it is when I’m not getting sunlight here in Ontario in the wintertime, I need to be upping… through supplementation or foods, vitamin D so my body has that. And I’m still a little bit gray here. It sounds like you’re not saying you can’t get vitamin D from the sun. It’s just not our primary source. Do I have that?
Right, it’s not our primary source. Yeah, it’s not as efficient. There are plenty of people who don’t live in the sun who eat a lot of animal fat, who don’t have vitamin D issues. Fluoride causes vitamin D deficiency… You can’t just isolate one factor and blame everything on it. Well, I can. Thyroid, I can blame everything on hypothyroidism, on thyroid dysfunction, but again, it’s a little bit more complicated. And supplements, isn’t it better to get it from your food? — We know that omega-3 — the sardines, the whatever… I don’t trust anybody’s vats and vats of oil… becoming rancid and then put it in these little capsules. I’m suspicious of that. If you can get it from your food I would recommend that.
Dr Bright
Me too… But I just want to make sure people are covered depending on their unique situation. So I think we’re on the same page now where sun can be a factor. And you’re just saying that you lean into the food source. An area I want to dig into a bit more in that, because if you do a “Google” search, foods that are high in vitamin D, it’s going to give you this list. – I’m assuming by the way you responded there, you’re not thinking we need to be that nuanced and search out these specific top foods to get it. You’re just eating your animal fats and that’s gonna cover you.
Absolutely. Because you do a “Google” search, it is predisposed toward the cholesterol hypothesis. You’re never gonna find [anything], unless you do the deep dives that I do in my research. [BOY, Ain’t that the truth! — GC]
On face value [from google], – stay in the sun, avoid animal fat. – So you’re not gonna find… those top foods that you find, it’s a crock. All Italians gravitate to the sun in the summer and they all think they’re getting tons of iodine. And all of my Italian patients that I had when I had a big practice, open practice before “COVID” they were iodine deficient… So, — it’s like that. —
Are you talking about vitamin D or iodine?
I was just mentioning iodine because people think that if you live by the sea, you can absorb the iodine.
Got it. Okay. But given we need to work with where people are at… somebody in Ontario, not getting sun throughout the winter, not eating the way you’re recommending. And even maybe they are eating a lot of animals, it’s just not to the carnivore extreme. Could you see an importance for vitamin D supplementation, if they’re eating say an animal based diet, but still including some carbs and they need that little bump to keep their vitamin D in a good range?
I would question why they need that bump. — I would say — they should eat enough fat because that’s the most bioavailable and healthy source. I’m a bit of a hard ass… But I think that obviously if you can’t eat, if you live in Ontario, I’m going to live in Scotland half the year, the sun is not going to shine very much. I will not consider taking vitamin D because I eat a lot of fat. But I think that you can eat some carbohydrates. I think that then we’re gonna, we might veer off into the Randle effect, [Randle Cycle] I don’t know. But if you have adequate animal fat and you’re taking iodine and you have the ability to make, turn that fat into vitamin D, vitamin A, vitamin K, vitamin E, then there’s no need to supplement. So I don’t know, if you refuse to eat animal fat, definitely you should supplement.
Okay, so for your ideal diet, high in animal fat, moderate protein. No carbohydrates.Talk about the protein piece and how, if it does, how that changes, the amount of that macro people are getting, at different stages of healing.
Initially because fat is anti inflammatory, you gotta make the hormones out of cholesterol… So we know that excess protein turns into glucose. If you can’t metabolize that protein into, I’m not going to show my muscles. But if you get into muscles and into enzymes and all the things that protein is needed for it’s just going to turn into glucose. We can only metabolize glucose or ketones. So I definitely dial down the protein to moderate in a healing state. Because most ill health is inflammation.
Other than diet, what are the biggest areas that in the modern world we’re being impacted negatively by inflammation?
I think that we are… over exercising. – Stress. I think that stress will definitely put a dent in our, it can turn an immune system autoimmune very easily because… cortisol causes inflammation. High cortisol levels cause inflammation. So we can go into all kinds of substances that people take from synthetic hormones to over exercising to foods that trigger inflammation. All of that will affect. So that’s still diet. Sorry. But yeah, stress, definitely over exercising, definitely. Pollution.
What are some of the safeguards, I know you filter your water, but what are some of the things in your environment at home you do to protect against environmental toxins?
Take iodine that’s my shield.
And what dose are you taking daily?
I’m taking six drops of 5% daily. Have been for a long time.
Any specific reason, previous health challenges? Because that’s more than you’re recommending to others.
I want a big shield. Because I don’t run for the hills. I’m falling in the “Adriatic.” Who knows those fishing boats and the crap that their engines are spilling into the water. – Because I know it comes out in my urine, if it’s too much. I take 12 drops when I’m traveling. Last time we got into testing a little bit.
You talked about two tests that you would do with people. One being thyroid, another being salivary cortisol. Let’s talk about a thyroid panel and get into details there because there’s thyroid panels that your doctor will do, and then there’s additional things that can be added. What do you think is really important there?
Free “T3” and free “T4.” And if you have inflammation, the thyroid antibodies. The two… that I recommend are antithyroid peroxidides and antithyroglobulin. Unfortunately, statistically more people have positive antithyroid peroxidase. And I’ve had patients ask for both, and they absolutely refuse to do both, to test both. And they also have a situation where once the antibodies are positive, they won’t test again… because they don’t believe that you can make them go down, you can bring them into remission, which my patients do all the time. You even have labs that say above a thousand in somebody who’s pregnant who needs to get those antibodies down, they don’t know we can’t see them go down. They have to go to a special lab to ask for the actual number. They don’t even bother because they assume that there’s nothing can be done. They can’t be reduced, they can’t go into remission.
Different people you’ve worked with over the years, following what we talked about today, the diet as the base, supplementing with iodine. What different chronic health conditions have you seen or reversed?
Thyroid cancer, — schizophrenia, —– many.
Anything that you found is particularly resistant to all this?
Weight loss. Some people, it takes a long time… I’m not really focused on weight loss. A lot of people are focused on weight loss. I’m more focused on getting the body healthy. So depression will go away for some people, before the 20 pounds that they’re trying to lose.
For the person out there… feeling like I’ve been stuck with weight loss, this sounds interesting, but you’re telling me to consume copious amounts of fat. How am I ever going to burn the fat on my body? Give them some reassurance there.
Well, when I give them a protocol, it’s for their structure so I’m not counting calories. I’m giving them the quantity of protein that they need for their structure and the quantity of fat that they need for their energy. It’s not calories in calories out there is a certain amount of nutrition, energy you would say that you need in adolescence. And somebody who’s six foot tall needs a lot more than somebody who’s five foot tall. But when you are in ketosis, which you will be, you will be burning your own body fat. But if you go out and run a marathon, you’re not going to burn any body fat. Because you can eat nothing and not burn any fat, because your body is holding onto that fat because it thinks you’re in danger.
And for you, the big tool to… provide the input, to calm the body, is this high fat diet.
Yeah, absolutely, [it] reduces stress.
For somebody, again, thinking about heading into what we’re talking about today, but this is a big leap. They’ve been having a more standard type diet and they’re thinking about all the saturated fat they’re gonna consume by eating this way. And they’re thinking conventional, which we’ve all been told saturated fat causes all kinds of heart disease, health complications. Help put their mind to rest.
Well, saturated fat is cholesterol, so we know that, — that’s what I’ve written about in my books. Saturated fat. — Cholesterol prevents depression. Avoiding saturated fat, – people who have low cholesterol levels are more at the risk of depression. They’re more at the risk of mental health issues. – – So, — everything in our body needs – cholesterol. It’s an anti inflammatory, it’s a source of our brain tissue, it’s a source of our nerve tissue, it’s a source of our energy and it’s a source of our steroid hormones. So our entire endocrine system, steroids, hormones are made out of cholesterol. So if you’re avoiding something that you need so much, we are human because we started eating… so much animal fat. Our brain grew bigger because we ate animal fat. More animal fat. This is documented. You kind of have to take a… I don’t want to say a leap of faith, but if it’s only been, I’m 62, it’s only been since 1984… that everybody has told you because it wasn’t until that “Time” cover story with the unhappy face, — the bacon bad and the eggs bad, that everybody started avoiding cholesterol. Before that, it was after “Ancel Keys,” the cholesterol hypothesis, heart disease was supposedly caused by this. But that is really the time if you look at pictures of people at “Jones” beach, on the beaches, that is really the time that you see and you have to think that was only what is it, 60 years ago, that is not history.
Dr Bright
Because this diet is so radically different from what the average person is eating right now. Give us some ideas of meals and what a typical day could look like for somebody.
Well, it depends if you’re six feet tall, but I’m five foot seven and a half. I eat, I have decaf with butter and egg yolk and then I go paddleboarding and then I come back and I do protocols and then I eat, – I don’t know, 150, 200 grams of steak — with some butter on it. And then I work. And then for dinner I have the same thing. So for me, I may have run and have some beef jerky during the day between calls. – But that’s — fine for me. Somebody might want more, somebody might want more chicken. Somebody might want bacon. If I could get bacon, I would eat it. I can’t get bacon. So I like bacon. It’s yummy, but I can’t get it, so I’m not going to bother. – I remember I put together for my height, a pound of meat and 4 ounces of butter just to make it visual.
And because your diet is so limited in diversity, are you still excited about your meals?
Oh yeah, I am. – I am, I am. I don’t think the variety. I love how I feel and I’m hungry when I go eat, so I’m very happy to eat. I love my decaf with a froth of butter this thick in the morning. I may have one again… at 11 if I did 8k like I did yesterday on the paddleboard. So… yeah, I’m definitely excited about my meals. But I’m excited about life. Meals just fuel…
Fuel, so you can live the life? So for you, drink wise, you have your decaf fatty coffee, you filter your water. Any other drinks in there for fun?
Sometimes I’ll have a half a shot of bourbon. Like, this much.
And is that purely for fun or do you think there’s certain benefits or negative side effects?
That’s just for fun. It’s small enough. Oh my God. No benefits at all. – But as I said, it’s such a small amount. If I had more, I’d turn red. — — I would flush. It would cause a vasomotor reaction. It would cause a hot flash because of the cortisol produced by alcohol being a stimulant.
Let’s talk about sleep and how you prioritize that. I’m assuming you must, given the fact, the thesis of — everything you’re working on through diet and lifestyle is to… bring down the sympathetic and bring up the parasympathetic system, the rest and digest. How do you look at sleep and how do you make sure you’re getting best sleep possible?
I go to bed early, go to bed about 9. I read. 8:30, 9:00, latest 9:30… I have fat before I go to sleep so I can tone down. We know that cholesterol actually can increase… parasympathetic tone. As an osteopath, parasympathetic and sympathetic have to be in balance, so that’s very much a part of my training. And the magic of learning how to do it with food, with fat, it was really an epiphany for me, which is what I did when I went into menopause at 52. So I give myself fat. I have obviously, if we’re going to go for a trip or I have something very stressful coming up. If I wake up in the middle of the night, I have fat in my fridge. I just grab it and eat it and I go right back to sleep.
And what will that fat snack look like whether it’s before bed or middle of the night? Just a piece of butter or something simple, I assume.
Piece of butter on a meat cookie or… some of that tallow that I have from the leftover after I’ve given the gelatin to my daughter. There’s that big thing of fat, that’s tallow. Yeah. I’ll salt it and put salt. Yeah, just salt… I’ll freeze it and I’ll cut it into chunks and I’ll just leave it there.
One thing I want to mention too, tying iodine into the sleep piece. You don’t want to have your iodine right before bed. I’ve done that before and it does stimulate you. So you want to be careful. Yeah, it’ll wake up your thyroid… Your thyroid will be like, oh, let’s make hormone, it’s the morning…
Any areas in the last number of years that you’ve really taken a pivot on or changed your mind on things?
DAIRY [This is a whole new rabbit hole! – GC]
I actually republished my “Good Fat is Good for Women: Menopause” book because… the snacks had cheese… And I decided that if people had – menopausal symptoms because of the inflammation and because of their adrenal issues, they definitely had to take out the dairy, which causes inflammation because of the xenomorphins.
Okay, we did talk about dairy last time, but since it’s brought up again, I want to get into it a bit more here. Is this all dairy or just cow dairy?
Not butter. Not butter. — No, not butter, yeah. Oh,”A2,” “A1” you’re talking about. Well, just different… There’s a lot of people in the health space that won’t have cow dairy, but they’ll have sheep or goat. Right. It’s “A2.” There is a lot of variables.
Well, that’s “A2.” But you can also have “A2” of cows milk as well.. There’s a lot of nuance and we got into again some of this last time. But are we talking about all dairy or are there certain details or types within that that we can still have?
I think if you’re on fire, you can’t have any dairy. You can have butter because we know that buttermilk is where all the proteins go. Unless you are so sensitive that you need to make ghee and you see the teeny tiny bit of milk protein and lactose come to the top. None of this has to do with lactose. It’s all about proteins. – So the more inflamed you are,you should not have any kind of dairy. So you can have Guernsey, Jersey. Those places in England, they have the breeds of cows that are”A2.” Senegal… Certain cows, yes, they are “A2,” but there is still a small quantity of casinomorphins in that. So there’s more in the regular, that breed that most cow milk is, but there’s a — smaller amount in the “A2” goat, sheep, Jersey, Guernsey breeds. Now, if you are on fire. I don’t recommend it at least for a certain amount of time, until the fires have been put out.
Did you personally notice a difference in your health when you took dairy out?
I did. My digestion was better, my husband’s breath was better. —– Yeah. And then I read Keith Woodford’s book “Devil in the Milk.”
Talk more about what that brought up for you?
Just reading about how heart disease, diabetes things that we basically, he explains that all chronic, most chronic diseases are because we’re drinking “A1” milk. So he’s an Australian and or actually New Zealand, I don’t know, anyway, but he’s talking mostly about how they actually prevented in Australia, the ability for people to have access to “A2” milk, even though it was so much more documented, so much healthier for people.
Dr Bright
So throughout our conversation, the two big targets that we’re honing in on, cortisol through stress, we want to bring that down. Inflammation. Given the focus in on inflammation, we talked about testing before, do you see any value in doing a test to look at overall inflammation and getting a number there to work from?
No. I recommend doing salivary cortisol, a diurnal salivary cortisol test, because your inflammation, you can do the “CRP,” you can do, it doesn’t matter. Once you fix the cortisol, once you’ve removed obstacles to your healing, all those will come into line. They will come in. —– You have to reduce the inflammation. So I don’t recommend testing. It’s just like, I recommend testing the thyroid and recommend testing salivary cortisol. And when you fix those things, everything else will just kind of come into line. So… there’s no reason to pay all this money for these other tests.
Elizabeth, really enjoyed round two, getting into some details on a lot of things we talked about in the first round. I appreciate you, the work you’re doing. We’re gonna link up your website, your books, everything in the show notes… You’re gonna wanna stick around here and catch this other incredible episode. You don’t wanna miss it. I’ll see you over there.
We’ve tested over 8,000 people in our office, over 97% are deficient in iodine, the vast majority, severely deficient in iodine. All thyroid hormone can’t be made without iodine. Thyroxin, or “T4” is four atoms of iodine attached.
Dr Bright
I do not necessarily agree with all that Dr Bright has said, but it is certainly food for thought. It also makes me even less inclined to trust the medical industry if that is possible. – GC
This DePat Tuesday Open Thread honors the author of the original Tuesday open thread on this site, namely the late Susie Sampson, a.k.a. Deplorable Patriot, among her other handles, pen names, etc.
For more on the untimely passing of Dear DePat, please see these three posts.
At one time, DePat handled FOUR daily open threads here, in addition to taking care of her relatives, choir duties, and numerous other responsibilities. She was a powerhouse – a dynamo – a true force of nature.
DePat’s faith in Trump, Q, “The Plan”, the White Hats, and “the anons” in general, was legendary. Although I didn’t always agree with her quick acceptance of some sketchier evidence and fringier theories, I will gladly admit to “coming around” to numerous so-called “conspiracy theories” which she championed first. I was always careful to give her credit for being right, too, when I had been wrong.
It is impossible to overstate how much DePat did for not only this site, but for her country. I urge all to say a quick prayer of thanks, whenever you think of her, for the privilege of knowing, in life or after death, such an exemplary human being, and lover of God.
And thank you, Susie, for the firm foundation which you left us, when you were called to your true home!
Is There Another Cell Nucleus Hall Pass in the New mRNA Flu Vaccine, mFlusiva?
Let’s start off with some history.
Are you aware of the fact that both the Moderna AND the Pfizer COVID vaccines contained a genetic sequence that acts like a “hall pass” or “VIP ticket”, allowing the holder to get into the nucleus of human cells?
Were it not for somebody dropping a link to an obscure paper in my Twitter timeline back in early 2023, I would have never realized how extra sketchy that made both the virus and the vaccines – and especially the latter, since it would have been theoretically possible to remove the nuclear hall pass from the spike protein used as the vaccine.
Let me repeat that. They left the “hall pass” in the mRNA code for the vaccine.
But – and I have to stress this – it was not just that this “hall pass” was there. No. It was much worse. The paper in question was experimental, and it showed that the viral spike protein not only contained the hall pass, but that it WORKED. The hall pass actually worked to get the spike protein into the nucleus. They even had PICTURES of it in the nucleus.
The hall pass not only got the spike protein into the nucleus – the spike protein THEN got the mRNA that coded for it into the nucleus, as well.
Yes. You are reading that correctly. The spike protein of SARS-CoV-2 has a known sequence in it that ends up getting both IT and the mRNA that created it, into the cell nucleus.
One would THINK that this might be a big deal. Especially after we were REASSURED that NO, VIRGINIA – THE mRNA WILL NEVER, EVER GET INTO THE CELL NUCLEUS, YOU FOOLISH VACCINE SKEPTICS.
Are you seeing why this is kind of a big deal?
SO – NOW – my question about the new mRNA flu shot is similar.
I could ask whether the flu vaccine’s “spike protein” (it’s called a “hemagglutinin glycoprotein”) also has a hall pass that gets it into the cell nucleus. I could even ask if the influenza HA glycoprotein also “escorts” its own mRNA into the nucleus, as does the COVID spike protein.
However, that requires experimentation. I can’t do that work.
OK – can I just ask if the mRNA flu shots contain the hall pass into the nucleus?
Well, it turns out that you can ask, but there’s not necessarily an answer.
I could not find the answer, so I asked Grok.
And I asked Grok a slightly less pointed version of the question, since I am perfectly capable of checking for nuclear translocation sequences myself, so that Grok would not detect “conspiracy theory thinking” on my part, and thereby not consign my question to the “talk down to this human” conga line of incomplete answers.
Q: Is there a published mRNA sequence for the new mRNA flu vaccine, mFlusiva, from Moderna?
A: (from Grok)
No, there does not appear to be a publicly published full mRNA (nucleotide) sequence for Moderna’s mFlusiva (mRNA-1010).
mFlusiva is the FDA-approved (as of early August 2026) trivalent mRNA influenza vaccine for adults 50+ (traditional approval for ages 50–64; accelerated for 65+). Each 0.38 mL dose contains 37.5 µg total mRNA (12.5 µg each of three RNAs) encoding the full-length hemagglutinin (HA) glycoproteins of the season’s recommended strains (for the 2026–2027 formula: A/Missouri/11/2025 (H1N1)pdm09-like, A/Michigan/105/2025 [A/Darwin/1415/2025 (H3N2)-like], and B/Pennsylvania/19/2025 [B/Pennsylvania/14/2025-like]), formulated in lipid nanoparticles (SM-102, PEG2000-DMG, cholesterol, DSPC).
Public documents (prescribing information/DailyMed, FDA briefing documents and clinical review, Moderna product pages, and peer-reviewed trial publications) describe the composition, encoded antigens/strains, manufacturing process (in vitro transcription, no cells/eggs), and clinical data, but they do not disclose the actual nucleotide sequences of the mRNAs. These would include codon optimization, specific 5′/3′ UTRs, poly(A) tail, nucleoside modifications (typically N1-methylpseudouridine, as used in Moderna’s platform), and any stabilizing mutations (noted for the influenza B HA in non-surface-exposed regions).
The underlying viral HA amino-acid (or genomic) sequences of the recommended strains are publicly available via databases such as GISAID or NCBI, as with any seasonal flu vaccine components.
Moderna and related patents/publications disclose example or earlier-generation influenza mRNA constructs, sequences for other candidates, or general platform elements (e.g., UTRs used in some Moderna mRNAs), but not the proprietary, strain-updated commercial sequences for the approved mFlusiva product. patents.google.com
This is consistent with how proprietary vaccine sequences (including prior Moderna mRNA products) are typically handled—they are not routinely released in full in labeling or regulatory summaries.
In short, while the antigens, doses, and high-level design are public, the exact published mRNA sequence for mFlusiva is not available. Any claims of a full sequence circulating would need independent verification against primary sources.
(END GROK)
(BEGIN WOLF)
First of all, just for the record, this is a great answer. Once again, thank you, Elon!
This situation seems a bit different from small-molecule drugs, where the exact molecules in the drug MUST be described in full, not only to the FDA, but to the public. Probably a feature that big pharma will eventually pay government to remove, but until then, something that certainly cramps their style.
Now, I was able to track things down a bit, and get CLOSE to the actual sequence for the vaccine, but I have been unable to find the exact sequence.
Product Information Product Type VACCINE Item Code (Source) NDC:80777-500 Route of Administration INTRAMUSCULAR
Active Ingredient/Active Moiety
Ingredient Name Basis of Strength Strength RNA-101-BFL3 (UNII: FPY755GU6Z) (RNA-101-BFL3 – UNII:FPY755GU6Z) RNA-101-BFL3 12.5 ug in 0.38 mL RNA-101-BFL6 (UNII: G35CN36JAP) (RNA-101-BFL6 – UNII:G35CN36JAP) RNA-101-BFL6 12.5 ug in 0.38 mL RNA-101-BFL5 (UNII: WAH8KM77XC) (RNA-101-BFL5 – UNII:WAH8KM77XC) RNA-101-BFL5 12.5 ug in 0.38 mL
3115056-86-2 RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza A (Missouri/11/2025 (A/H1N1))-like virus hemagglutinin codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL3), inner salt
(b)
3115056-85-1 RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza A (Michigan/105/2025 (A/H3N2))-like virus hemagglutinin codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL5), inner salt
(c)
3118110-32-7 RNA (recombinant 5′-(m7G-(5′→5′)-ppp-Gm)-capped all uridine→N1-methylpseudouridine-substituted influenza B/Victoria Pennsylvania/19/2025-like virus hemagglutinin [288-valine,381-tyrosine] codon-optimized transgene plus 5′- and 3′-untranslated flanking region-containing poly(A)-tailed messenger RNA-101-BFL6), inner salt
That is as far as I could go. Registry numbers and names. Trying to look up the CAS registry numbers failed.
CAS Common Chemistry covers – well – common chemicals, including some surprisingly unusual ones, but it clearly doesn’t cover everything. For a lot of molecules – ones that are not “public figures” – one has to get behind the paywall by buying a product like SciFinder.
For example, CAS Common Chemistry has a page for one of the allegedly inactive substances in the vaccine – tromethamine.
SIDEBAR: I’ll do a whole post about tromethamine later – it’s one of the best and most hilarious demonstrations of the (to borrow Scott’s verbiage) “weak, fake and gay” duplicity of the pharma-government-fincorp-media complex that I’ve ever seen. I’m personally glad they smartly added this compound to the clot shot, but to lie about why they did it – just so WEAK, FAKE AND GAY!
It is possible that the three names we retrieved above would allow trained biochemists to get very close to the actual sequences that were used, but in reality, to get the full, exact composition, including DNA contamination, we will almost certainly have to wait for independent researchers to analyze and sequence vials of the mFlusiva vaccine.
SO – in answer to the original question, we won’t truly know if there is either a public or secret access code to the cell nucleus in this vaccine, until somebody in free science actually analyzes the sequence of the vaccine, and somebody else actually checks and sees if the protein and/or the mRNA gets trafficked into the nucleus.
To borrow a saying from Nancy Pelosi, “We have to inject it, to find out what’s in it.”
Honestly, I think if Thomas Jefferson saw what patents have done to science, he would pull the whole idea up by the roots and figure out some other way to implement it. What that something else is, I don’t know. But what we have now is clearly problematic.
This Stormwatch Monday Open Thread remains open – VERY OPEN – a place for everybody to post whatever they feel they would like to tell the White Hats, and the rest of the MAGA/KAG/KMAG world (with KMAG being a bit of both).
Our various sister sites, listed in the Blogroll in the sidebar
Our beloved country is STILL under DIRECT THREATS by hostile forces – notably COMMUNISTS – and they’re HERE IN AMERICA.
Daily outrage and commie phuckery still abound.
We can give in to despair…or we can be defiant and fight back in any way that we can.
Commies won’t win!
And we will keep saying COMMIES OUT until we get their FRAUD and INSANITY out of our country!
THE STUFF
Let’s Talk About Virus, Vaccine, and Protein Shedding
I have noticed something very interesting about the “shedding” phenomenon.
The “vaxxes can do no wrong” side doesn’t like to talk about shedding. They don’t bring shedding up, and they frequently change the subject when an argument about shedding gets started.
It’s easy to dismiss “shedding” as a conspiracy theory, but once one sees actual Pfizer documentation on the topic (link now dead, curiously), the reality of “shedding” in the vaccine world hits one square in the face. Media shills for vaccines may be crowing on TV that “shedding” is all a big lie, but when the vaccine manufacturer is testing the vaccine, suddenly it’s the greatest danger of the study, and test participants find themselves separated if not isolated from spouses, infants, relatives and friends. Yet another reason people cannot stand the lying fake news media.
The most disingenuous current deflection of the problem in vaccines, is that the FDA has a HUGE concern with the shedding of “gene therapy” products – which often use mRNA in lipid nanoparticles – but then says that it’s not a problem in mRNA vaccines because they’re not classified as gene therapy products. Robert Malone has always been highly critical of this teenager-level dodge of responsibility, and frankly I think anybody involved in that scandal needs to be fired from government and possibly prosecuted for fraud. It’s the same weak chutzpah as the 17-year-old murderer of his parents, demanding first leniency as an orphan, and then prosecution as a juvenile, when the initial lunacy doesn’t prevail.
I recall the first time I read documentation of how shedding of a vaccine was to be guarded against in a major vaccine clinical trial, by significant restrictions of the participants from close contact with other people during the observation period.
Shedding of a virus – why – that’s just DISEASE. Communicable disease. We are all familiar with THAT.
Well, vaccines can be a virus – including weakened and incompletely deactivated viruses. It can even be a normal but less pathogenic virus, like cowpox, used as a literal vaccine against a more dangerous virus like smallpox. A weak but “live” virus may be difficult to transmit, but in many cases, transmission is still possible.
Shedding of a virus per se is the most potentially dangerous form of shedding, but it’s also the most well-known, and the easiest to understand. A limited number of viral particles is all that is necessary to start a disease in a new host. Being a victim of viral shedding is literally catching a disease. This is reality – something that happens all the time with common colds and influenza-like diseases (ILIs). Catching a shed virus is vaccination against catching the exact same form again – but not against sufficiently mutated forms. We are familiar with THAT from COVID-19.
So when people catch a communicable viral disease, they catch a shed virus, start constructing the virus, and then shed the virus again. Simple, and very real. But the outcome of viral infection is very uncertain, and that unpredictability ends up being a liability of using sheddable viruses as vaccines.
There is a reason I’m harping on this form of shedding. One needs to keep shedding of vaccine in perspective with the more dangerous, more likely, and more consequential shedding of virus. If you suddenly experience symptoms of a disease, including symptoms of the protein produced by that disease, then it is far more likely that you are a victim of shedding of the actual virus, than shedding of the vaccine. This is a simple reality, which I believe has led many patriots, including Deplorable Patriot, astray, in losing focus on relative risks. It is important to keep ALL forms of shedding in mind.
Shedding of Proteins
At the other end of danger, is the shedding of viral proteins, but not the virus itself. Let’s consider that.
Viral proteins can’t reproduce, but they CAN show all the bad properties of other nasty, dangerous, pathogenic proteins.
For example, the spike proteins of corona viruses are notoriously pathogenic, and when they are administered to test animals in an aerosol, they create immediate pulmonary disease, and can even kill the test animals. Yes, it’s shocking.
Still not convinced that a small amount of “shed” protein can be dangerous? Let’s talk about snake venoms.
Snake venoms are mostly dangerous because of pathogenic proteins, and these proteins are often very similar to bacterial or viral proteins, or arthropod venoms, as well as powerful digestive enzymes.
The thing is – and you likely didn’t know this – venomous snakes “shed” not only their skin, but also their VENOM. That fact is why people who care for venomous reptiles need to wear gloves and respirators when they clean cages. Shake venom gets into the cage dust, and cleaning it out exposes workers to skin and respiratory dangers pretty much like test animals breathing corona virus spike proteins in an aerosol.
So, again, shedding of pathogenic proteins can be real.
The only questions are, what viral protein is it, how is one being exposed to it, and how much of it is one being exposed to.
I’ve discussed this in the past, when we talked about the possibility of shed spike protein having the potency to cause symptoms in a person being shed upon. You can refresh yourself with the discussion in the following post and other linked posts here.
How much exposure to pathogenic protein is allowable? That is a HUGE question – and between the extremes of total neglect and total fear, lies something called “exposure and immunity”. Including “natural immunity”. We’ll return to that topic later.
Shedding of Vaccines
In between the shedding of intact viruses, and the shedding of viral proteins, lies an intermediate possibility – the shedding of what in nature are called “virus-like particles”, or what in medicine are called “lipid nanoparticles”.
These are mRNA or DNA enclosed in something like a lipid nanoparticle, or the outer shell of a different virus.
These are, bluntly, mRNA vaccines.
In terms of both danger and safety, lipid nanoparticle vaccines are intermediate between live viral vaccines (always dangerous, IMO) and protein vaccines (least dangerous, IMO). Why is this? Well, bluntly, viruses propagate as a chain reaction, and have very little control over outcome. In contrast, a metered amount of a dead protein has great control over the outcome. mRNA vaccines are in between. They don’t reproduce, but they do create a greater but unpredictable amount of viral protein.
Pierre Kory has a very nice article about vaccine shedding, which I invite you to read.
By the time you finish that, you will understand that there is some need to address this issue now.
As a bit of an aside, you should note that Cory is AGAINST the use of nicotine patches for treatment of spike protein toxicosis, believing (as I do) that it probably has far more risks than benefits. This is highly relevant for DePat’s case.
Technical Approaches to Prevention of Shedding Injury
It is my belief that any good method to deal with both mRNA vaccine shedding and corresponding protein shedding should have the following characteristics.
Prevention is preferred to treatment
Treatment can be separate from prevention
Earlier is better for both prevention and treatment
Vaccine is more dangerous than protein, and is thus a priority
The final point needs some explanation.
While the protein can be dangerous at high enough levels, one of the greatest dangers of the vaccine is that it produces large quantities of the protein, and is thus automatically orders of magnitude more dangerous than the protein alone. This is not even considering the dangers of the mRNA technology itself.
Destroy the mRNA vaccine, and there is no protein made, nor any mRNA mechanism allowed to function badly.
Thus, targeting the shed vaccine FIRST makes sense.
THAT makes things easy, because the vaccine can be destroyed easily, provided that it has not yet entered the body.
The mRNA vaccines utilize lipid nanoparticles (a.k.a. liposomes) to enter cells. While these little particles are exceedingly dangerous at a cellular level, they have an intrinsic weakness – their easy destructibility by surfactants – meaning soaps and other cleaning agents.
I posed a research question to Grok, regarding this approach, and got a VERY satisfactory answer.
THE QUESTION
Grok, please give me a list of substances (ranging from specific chemical compounds to branded products) that are known to rapidly disrupt, break up, absorb, and/or inactivate liposomes, including liposomes that are referred to in the mainstream press as “lipid nanoparticles”. I am interested in both surface treatments (cleaning agents, topical medicines, skin washes, soaps, lotions, etc.) as well as things which can be taken internally (oral or injectable), as medicines, that are more specific for disrupting liposomes in the bloodstream, for example as an antidote to an inappropriately administered lipid nanoparticle vaccine, e.g., given mistakenly to an allergic patient.
THE ANSWER
BEGIN GROK
Surfactants/detergents (most effective and commonly documented disruptors of liposomes and lipid nanoparticles/LNPs), organic solvents, cyclodextrins, and certain other agents can solubilize or destabilize lipid bilayers. These work primarily by intercalating into the bilayer, extracting lipids/cholesterol, forming mixed micelles, or increasing permeability/leakage until the vesicle structure collapses. Effects are concentration-, composition-, and condition-dependent (lipid type, cholesterol content, PEG coating, temperature, pH, etc.). LNPs used in mRNA vaccines share similar phospholipid/cholesterol/PEG-lipid components and are susceptible in vitro to the same classes of agents. pubs.acs.org +2
There is no established, safe, specific medical antidote that rapidly and selectively disrupts circulating LNPs (e.g., after mistaken administration of an mRNA vaccine to an allergic patient). LNPs are designed to be temporary and are cleared primarily via the mononuclear phagocyte system (liver/spleen), with natural degradation of the lipids. Systemic attempts to force rapid disruption with the agents below would generally be highly toxic (hemolysis, cell membrane damage, organ injury) and are not clinically used or recommended for this purpose. Allergic/anaphylactic reactions are managed with standard emergency care (epinephrine, antihistamines, corticosteroids, supportive measures), not LNP disruption.
Surface treatments / topical / cleaning agentsThese are relevant for cleaning residues, skin washes, or external inactivation:
Anionic, nonionic, and other surfactants/detergents: Sodium dodecyl sulfate (SDS/SLS), Triton X-100, Tween 20 (polysorbate 20), Brij surfactants, Zwittergent 3-14, quaternary ammonium compounds, and commercial soaps/detergents containing these. They saturate bilayers then convert liposomes/LNPs into mixed micelles. Used in lab assays (e.g., RiboGreen for mRNA release from LNPs) and industrial cleaning of LNP residues. Alkaline formulated detergents (e.g., potassium hydroxide-based) are effective for equipment cleaning of LNP residues at elevated temperature/contact time. pharmtech.com +2
Bile salts (sodium cholate, deoxycholate, taurocholate, etc.): Strong solubilizers of phospholipid bilayers; well-studied for vesicle-to-micelle transitions. Present in some digestive/intestinal contexts and used experimentally.
Alcohols and organic solvents: Ethanol, isopropanol, methanol (typically high concentrations). Disrupt hydrophobic interactions; improve solubility of lipids for cleaning but raise flammability/handling issues. pharmtech.com
Cyclodextrins (especially methylated or randomly methylated β-cyclodextrin / RAMEB / DMe-β-CD, and to varying degrees α-, β-, HP-β-CD): Extract cholesterol and phospholipids from membranes, increasing permeability, leakage, or causing collapse at sufficient concentrations. Effects depend on CD type, dose, and membrane cholesterol content. link.springer.com +2
Other noted factors: High concentrations of certain kosmotropic salts (e.g., ammonium sulfate) can aggregate/precipitate PEGylated liposomes; extreme pH, heat, or oxidation can destabilize; some nanoparticles or polymers can tear or fragment membranes under specific conditions.
Branded/consumer products that contain the above (many soaps, dish detergents, hand washes, some lotions or topical cleansers with surfactants/alcohols) can disrupt lipid structures on surfaces. Efficacy varies widely with formulation and contact conditions.
Internal (oral or injectable) agents
The same surfactants, bile salts, solvents, and high-dose cyclodextrins that work in vitro or on surfaces are generally not safe or selective for bloodstream use against LNPs. They disrupt host cell membranes (including red blood cells) at effective concentrations.
Bile salts occur physiologically in the intestine and can destabilize orally administered liposomes, but systemic (bloodstream) levels for intentional LNP disruption are not a therapeutic approach.
Cyclodextrins have pharmaceutical uses (e.g., solubilizing agents) and can interact with membranes, but high systemic doses for rapid LNP inactivation are not established as safe or effective antidotes and carry risks.
No specific medicines or injectables are approved or routinely described as LNP-disrupting antidotes for vaccine mishaps. Research on LNP fate focuses on clearance, protein corona, MPS uptake, and formulation stability rather than forced rapid inactivation in blood. nature.com
Important caveats: Literature on disruption is largely from in vitro biophysics, pharmaceutical formulation/stability studies, cleaning validation, or drug-delivery research—not clinical antidote development for circulating LNPs. “Rapid” disruption typically requires relatively high local concentrations of surfactant relative to lipid. PEG coatings or cholesterol content can modulate stability. Self-experimentation or off-label use of detergents, solvents, or high-dose agents internally is dangerous and not supported.
For any real-world allergic reaction or medical concern involving a vaccine or LNP product, seek immediate professional medical care; do not attempt chemical disruption. If this is related to laboratory work, cleaning protocols, or formulation science, consult primary literature or specialists for concentration- and condition-specific details.
END GROK
Let me translate all of that.
As long as the shed vaccine is still on the surface of your skin, on clothing, on a mask, or on a surface in your house, the vaccine can be destroyed by all sorts of cleaning products, including surfactants, soaps of all kinds, alcohols, oxidizing agents, bile salts, cyclodextrins, and probably anything useful for cleaning.
Further, any lotions or surface treatments which do not aid in skin penetration (like DMSO), but which do sweep things away from direct contact with your cells, are likely to be helpful in delaying, dissolving, and degrading lipid nanoparticles. Imagine spilled chemical on your skin – it’s the same principle. Diluting the vaccine and/or washing it off make sense.
It is a much different story once a lipid nanoparticle vaccine is inside you – be that from prolonged skin contact, breathing, swallowing, or any other route into your body (like the mRNA jab). None of these things work, once the vaccine is inside you, or in the bloodstream. In fact, these cleaning agents are just as dangerous to your internal cellular machinery (lipid-coated droplets) as they are to the lipid nanoparticles. However, as long as the shed vaccine doesn’t get into your bloodstream (a lower probability than a surface reaction), you don’t have to worry as much about that, as about vaccine damage to skin or mucus membranes where shed vaccine made contact.
Thus, the best time to fight shedding, IMO, is soon after contact. Washing, application of lotions or alcohols, etc., should inactivate shed vaccine. Washing away or denaturing shed protein is also likely to work at the same time.
Again, it is important to remember is that systemic problems from shedding are much less likely than surface problems.
A Realistic Program Against Shedding
This is my opinion. Others may differ. That’s OK. I am just offering my perspective. YMMV.
My first concern remains shedding of virus.
If I am not accepting the trade-offs of the vaccine itself, then my protection is my immune system. My immune system has worked very nicely over the years, against colds, flu, and flu-like illnesses, including all forms of COVID as well as non-COVID coronaviruses. There are appropriately long gaps between infections, and the infections (except for OG Wuhan) have not been debilitating, indicating a functioning immune system.
My immune system is always supplemented with plenty of vitamin D, because vitamin D levels are extremely highly correlated with immunity to viruses. The relationship is stark, and backed by the strongest science. Rates of viral infections almost disappear at high serum levels of vitamin D. There are probable mechanisms for this, but I literally don’t care what they are. Without knowing the causation, the correlation still works. I cannot recommend vitamin D enough. You need to be supplementing it, and maintaining maximum exposure to sunlight. Better still, a measurement of serum levels, but it’s not cheap and your doctor likely won’t recommend it.
Doesn’t matter. Supplementation is cheap and easy and not dangerous, so why not just make sure you are taking a few thousand IUs daily? Just do it. When you notice an appropriately long time between colds and flu, you know you’re taking enough.
Likewise, I make sure that I am not deficient in any vitamin or mineral. Vitamin C, magnesium, selenium and zinc are very important.
However, THIS is even more important.
Avoiding crowded events is critical to reducing exposure to shed viruses. I can link almost every case of influenza or coronavirus infection in recent years to a specific event where there were lots of people crowded together.
In other words, shedding. Viral shedding. As in, viral shedding by people in close proximity.
Thus, avoid crowded public events, particularly in the wintertime, when viruses are maximally spread.
After viral shedding, my next concern is vaccine shedding.
IMO casual vaccine shedding from strangers in momentary close proximity, but not direct physical contact, is far, far less of a problem than living with a vaxxed person for that week after vaccination. Even worse, sleeping with that person who just had a vax.
You should note that my concerns here are EXACTLY what the pharmaceutical industry is concerned about in vaccine trials. That includes live virus AND gene therapy products (even if they don’t call them gene therapy products).
My recommendation is to avoid close contact with vaxxed people for at least 2 days after vaccination, and better a full week. Two weeks should be more than enough, always.
Why? Because the vaccine itself degrades. Even if a person take the vaccine, and shows all sorts of disease symptoms for weeks if not months (please pray for them if this is the case) due to vax-initiated protein production that won’t shut off, they are unable to transmit the vaccine to you, because it is no longer there. The vaccine is degraded, but protein production may still be running.
What about shed vaccine when we can’t avoid being around an individual?
This is when to use soaps, alcohol-based gels, and other skin products. This is when to wash your hands after that oily, wet handshake from some just-jabbed joker, sweating profusely due to their mRNA jab. This is when to stand back from people who can’t “say it” without the need to “spray it”. And note that all of this works even better for VIRUS.
IMO, the vaccine is a far greater danger to you, than the protein these poor victims are now producing. YOU don’t want to be inappropriately producing the protein.
And HERE is where my opinion is likely to differ with yours.
My final concern, about exposure to environmental viral protein, is largely not a concern.
Why? Because this is the natural way in which we build immunity.
Even against a bioweapon. I repeat. Even against a bioweapon – as either a virus or a vaccine.
I literally don’t care if the neighbor sheds small amounts of spike protein or flu proteins on me, because THAT is the vaccination that I prefer – the one for which I am designed. Likewise, I am unconcerned with exposure to dead virus, because THAT is basically how we are naturally prepared for exposure to live virus.
Do I want to inject a protein or dead virus vaccine into me? Maybe – but more likely not. I am now very cautious about vaccines, given that I have lost much trust in the current “vaccine cult” in science. I still trust God and His natural evolutionary reality, however, so I am far more likely to simply trust a combination of pre-exposure of my healthy immune system to proteins, followed by full natural immunity from a well-tolerated episode of the disease.
Rabies? That’s a different story. I’ll take the vaxx, as long as it’s not mRNA. I’ve already done so, once before. I would ONLY take an mRNA rabies vaccine if the animal was confirmed to be rabid, because then it’s a “lesser of two confirmed evils” situation.
I am not going to get pregnant any time soon, and I’ve already had COVID and influenza several times each, so I’m not terribly concerned about exposure to proteins from new variants. In fact, I am at the point of “keeping up” with the latest versions.
SO – some jabbie wants to expose me to the latest spike protein in a non-infective way? Please! Not a problem. Go right ahead. Flu proteins? Be my guest. But I won’t let them expose me to the Soviet Trabant two-stroke mRNA vaccine which I very intentionally decided NOT to take.
And again, my final point. Even if the vaccine AND the protein it produces are “bioweapons” – guess what? I want to be immune to it. I want my system to adapt to its presence. I want natural immunity to all this shit – whether it’s purely “old natural” or “the new natural” that includes stupid human gain-of-function scientific error.
Do you see what I’m saying? GOD has this situation – ALREADY. Let go and let God – just do it at the right time and place.
I hope this helps. If you have questions, feel free to ask.
Homeschooling is going great! #1 is turning into a rock star. Almost literally, as his music voice lessons are also paying off. He’s got talent and loves to sing for the Lord. We just need him to finish puberty and the voice change. At his annual physical his pediatrician decided it was time to be tested for food allergies, celiac disease, etc. to learn more about what we need to do to increase his weight. He is super skinny and not even on the weight chart for a 13 year old. What we learned was enlightening and reassuring.
Since handling all of his other issues including spinal alignment, vision, dyspraxia, schooling, etc.; we have been making marginal progress on his remaining two issues – weight/strength and sensory. The tests revealed he has zero food allergy issues, no evidence of celiac, and so on. As a baby and toddler he was somewhat lactose intolerant, but grew out of it. Fit as a fiddle. So being extremely underweight has not harmed his overall health and has led us back to what we have suspected and claimed as his primary health issue since birth – sensory. His finicky eating and food choices are directly related to sensory issues, which creates great anxiety. The anxiety causes the eye focal issues that resemble short term absence seizures, that are now making even him annoyed (good sign). No more guesswork, no more what ifs, no more sleepless nights trying to figure it all out.
It is time to focus entirely on what it is and how to remedy to the best extent possible. This process starts and ends with prayer and lifting him up to the Great Physician to help him be his best self to glorify Him. By our submission to His answers and will, #1 will be made whole in the image God wants him. Our role is to simply pay attention and do our parts as He leads us. Psalm 146:5, 6 tells us,
“Blessed is he whose help is the God of Jacob, whose hope is in the Lord his God,who made heaven and earth, the sea, and all that is in them, who keeps faith forever;“
Practically speaking we have noted that when he starts having excessive sensory related episodes he is in need of a spinal adjustment from the chiro, in particular in the cervical spine area of the neck. The chiro works him in quickly every time and his stress goes down immediately afterwards.
This discussion leads to our church breaking ground this week on its long planned Next Generation (Youth) Center that will provide a community center type place for children, youth and young adults to come and enjoy fellowship and training together. This will include long sought homeschooling group support. It will provide another much needed Pre-K/Parents Day Out school and program for our community. It will also serve as critically needed Sunday School and small group meeting space for our congregation.
This project was supposed to break ground in 2020. Then COVID hit. Then costs spiraled out of sight under Chyna Joe. Finally the ship was righted and we have arrived – the Lord provides within His timing, which is perfect. It all fits the needs of both #1 and #2 along with granddaughter. But not only them, it meets the need to use the gifts of teaching and service of Daughter to develop and love on children as well as my own recently discovered calling relating to homeschooling activities. Thank you, Jesus!
Now, For The Rest Of The Story
Don’t worry, the following is not just about geoengineering. However, it is a good place to start as you will learn. As a short reminder…
To beat an old horse, not a dead one, I have a simple question.
Who authorized these wannabe environmental terrorists to screw with nature and all life on this planet? Probably some of the same demons who executed the great COVID caper that is killing million worldwide. I am quite sure the God of Creation is not amused.
The first glaring evidence that geoengineering is a real concern is that the usual subjects dismiss consideration and relegate it to conspiracy status. This attitude occurs within the related scientific academia, media, research, application, manufacturing, distribution and environmental restoration of the various industries making money off of it; from which the elected and unelected authorities gain power and influence. That creates major red flags!
🚩🚩🚩
You always see defenses, rationalizations, and excuses instead of challenges to the related narratives of the day. The activities are represented as “settled science” and soft pedaled by media lackeys; that is until the truth is revealed. We also know why they do what they do – money and power. Jeff Childers had a good recent article on the six step process associated with the liars of science doing what they do as the process works its eventual way toward revealed truth.
Since chemtrails and such were banned in Tennessee a couple of years ago interesting things have happened. It was like walking up to a big switch and flipping it. For the past couple of years we have become much more predictable on temps and precipitation; less radical fluctuations. The blue skies and clouds are back to normal and can be quite magnificent to observe at times during out daily fitness walks. It is like the environment has exhaled a giant sigh of relief.
Animal life abounds again. We are back to seeing deer wander about as well as watching out for bear in our strolls in our rural community. Have not seen them in this manner for a couple of decades. The wild turkey have become obnoxious along the backroads. Flocks of various birds have returned big time while nesting for longer periods well into the summer, not just for a brief period in early spring. This has helped keep the insect population under control. During our walks it can get quite amusing as the birds dive bomb us in their attempts to “steer” us away from their nests.
Most importantly and a great indicator of the before and after effects of geoengineering; the feared demise of the honey bees population has disappeared. They were greatly impacted by the spraying. Now, anything that has flowers has bees everywhere you go. There is a crescendo of bee buzzing sounds in every patch. More and more area residents are taking up beekeeping as a hobby. The local senior center has a program with brood boxes for the hives and is teaching seniors how to do it on their properties while sharing the product with seniors at the center. In general, I have not seen grass, shrubbery and trees this green this time of year for 30+ years. The farmers markets have been booming with great local produce.
Despite the explosion of pollen related allergens that come with the improvements, wifey and I no longer experience miserable reactions that forced us inside during this time of year. Improved gut health may be part of the reason, however, there is no question that living in a cleaner, more natural environment is contributing greatly.
Post Helene
For those traveling Interstate 40 at the TN/NC border through “the gorge”, there is a planned late 2027 reopening of the fully rebuilt section destroyed by the flooding effects of Helene. According to federal highway officials it is the largest in scope and most expensive project of its type in our nation’s history. Picture in your mind a 12 mile long dam being constructed to endure whatever gets thrown at it short of a nuke or direct meteor hit.
😄
Presently one side is still used as a lower speed, two lane road with larger sized tractor trailer rigs being prohibited and rerouted. It will be a few more years before all of the Helene related road infrastructure in the area will be rebuilt.
Now where were those large lithium deposits located again? Who purchased the related properties and rights?
Which properties did the leftist controlled City of Asheville file imminent domain to take or acquire by other means at depressed prices to do repairs and long desired infrastructure while using federal grants and FEMA funding? Have doubts? It is in the City’s minutes. Even AI discusses the property acquisitions. An example is below,
Nah, the Dem crims would have no reasons or ability to enhance a lower Gulf of America tropical depression less than two months before a strongly contested general election for POTUS and Congressional seats by negatively impacting two southern states that could swing said elections through mail-in ballots and conservative voter suppression. sarc/
I am sure it is just a coincidence that the massive number of recon flights in the southern Caribbean before the tropical disturbance even became a tropical storm included not only NOAA Hurricane Hunter planes, but also the Air Force Reserves. sarc/
Go to Figure 6 a little over halfway into the report below to see for yourselves.
Trust me, that amount and related patterns of flights do not appear or discussed in other archived reports anything like Helene’s. Ask yourselves why the NOAA Hurricane Hunters and Air Force Reserves would be flying that close to the Mexican, Honduran, and Guatemalan coasts for an undeveloped, routine tropical depression? That is not something that is typically done. Not only did the flights cross into the airspace of those nations, they also crossed over communist enemy Cuba and its airspace. These flights happen to be around and over the same countries that were sending their drug cartel crud, trafficked kids, thugs, and other assorted deadbeats across our southern border by the millions. All of it being authorized by Dem controlled government actors to supposedly recon a tropical depression a thousand miles away from our coastline a crazy number of times, a storm that grew and made its way to landfall at the Big Bend in FL.
Now which related military and federal agency leaders have been terminated or forced into retirement in the past 18 months?
But nah, move on, nothing to see here. Yeah, ok.
You gotta keep digging and asking questions long after the fake media and general public interest is gone to find the truth. We learned that up front and personal locally with the Great Smoky Mountains Fire a decade ago, whose effects are still felt. But let’s take it a step farther. Some of us were around for the Vietnam War days. We know much of what our military did to the environment there to root out the enemy- the burnouts, Agent Orange, etc. If you do not know, simply use your search engine. The methods have likely been used here as well. It is not a conspiracy theory to be explained away as the facts are the methods have been used before over 50 years ago. Here is just one exposé from a declassified document from 1970.
Rather sobering to consider, don’t you think? Now, about all those western U. S. wildfires…
Ground Report
Shifting gears, I like to give an east TN ground report this time of year. Average Americans, mostly MAGA types, come here in droves to the land of Dolly, mountains, lakes, and bears. So far the total visitation is down slightly due primarily to fuel and food costs. Tourists have been coming as usual, just staying for shorter visits due to higher costs. As a result it has been somewhat easier to travel around the area than usual for this time of year. Add in the obvious decrease in hispanic population. Subject to the Iran War ending, the rebound of empty nesters and leafers visiting will be really strong this fall.
As stated the hispanic population has been greatly reduced in the public eye. Don’t know if they are still in hiding or have left. The Honduran vape and smoke shop center of drug trafficking and FedEx delivery fame from my previous dailies is still closed. Local law enforcement has gone silent over the incidents, however, our family friend is elated that there have been no surprise pallets of “products” from Honduras being delivered to her driveway lately. We can only surmise that the misdirects accomplished the intended purposes of the federal authorities, such as ATF and ICE, that may have been arranged to corral the traffickers. We do note the questionable contract FedEx delivery person from the last event is no longer making deliveries in the area. Funny, that.
Employment is still strong with rising wages. Less people working in stores and restaurants, yet, generally well trained and better performers to offset. Many more older workers than in the past. It appears there are many who “retired” to this area are picking up some income being employed at least part-time. Industrial and residential construction is everywhere. The residential projects are primarily the national D. R. Horton spec plain box type – basically – tract housing. Grab some land, get the approvals, send in the excavation and road building crews, slap up 50-150 houses as quickly as possible and move on. Some better built apartment and condo complexes are underway or recently completed in the area as well. Other than automotive related, most of the industrial growth is tied to the federal facilities and related contractors in Oak Ridge. The new nuclear power plant there is under construction. When complete it will easily be enough to supplement the growth for the federal reservation and essential operations along with an AI expansion.
Marsha and team got it done in the primary for governor despite not having much time to campaign due to her Senator duties. She will win the general easily, probably by around 30 points. She will also keep the conservative train rolling smoothly down the tracks in TN as she has been a noted GOP operator behind the scenes for decades. Based on recent interviews, all will be well under her watch and may actually be improved from a conservative wish list perspective.
The GOP will have her replacement at Senator lined up ready to go, but ultimately it will be Marsha’s choice. Tim Burchett is a solid contender and if selected the “dadgum” Club Senate will never be the same once he gets done with it. Marsha and Tim go back a lot of years to their state senator days and are good friends. There are some solid MAGA House replacement options to replace Tim if she does pick him. TN would then have the polished, internationally experienced Bill Hagerty to go with a man of the people as our Trump endorsed Senators. Tim is the same former small business owner hillbilly, who as County Mayor ran the state’s third most populated county’s government better than it ever had for eight years with zero tax increases and balanced budgets annually during the period. Hope it happens.
For what it is worth, Trump supporting House Rep Andy Ogles lost because he is a bit too brash for some folks in his district, the GOP machine trotted out well respected Charlie Hatcher as his opponent, and because TN has open primaries. The Dems showed up to vote against Andy to push Charlie over the top. So, Charlie Hatcher it is and he will win the general. He had the endorsement of current Governor Lee (MAGA lite). The good news is he has been the state Dept. Of Agriculture Commissioner for 6 years under Lee, so he knows how government works. He is a dairy farmer who can help USDA with practical experience. He is strongly pro Trump, pro guns, pro life. He will vote how the Speaker tells him to vote. No worries, just not a change agent.
In closing: John 8:32 – “And you will know the truth, and the truth will set you free.” (ESV)
This Rejoice & Praise God Sunday Open Thread, with full respect to those who worship God on the Sabbath, is a place to reaffirm our worship of our Creator, our Father, our King Eternal.
It’s also a place to read, post, and discuss news that is worth knowing and sharing. Please post links to any news stories that you use as sources or quote from.
In the QTree, we’re a friendly and civil lot. We encourage free speech and the open exchange and civil discussion of different ideas. Topics aren’t constrained, and sound logic is highly encouraged, all built on a solid foundation of truth and established facts, and not by agenda-driven accusations and pronouncements.
We have a policy of mutual respect, shown by civility. Civility encourages discussions, promotes objectivity and rational thought in discourse, and camaraderie in the participants – characteristics we strive toward in our Q Tree community.
Please show respect and consideration for our fellow QTreepers. Before hitting the “post” button, please proofread your post and make sure your opinion addresses the issue only, and does not confront or denigrate the poster. Keep to the topic – avoid “you” and “your”. Here in The Q Tree, personal attacks, name-calling, ridicule, insults, baiting, and other conduct for which a penalty flag would be thrown are VERBOTEN.
In The Q Tree, we’re compatriots, sitting around the campfire, roasting hot dogs, making s’mores, and discussing, agreeing, and disagreeing about whatever interests us. This board will remain a home for those who seek respectful conversations.
God is in Control . . . and His Grace is Sufficient, so . . . Keep Looking Up
Hopefully, every Sunday, we can find something here that will build us up a little . . . give us a smile . . . and add some joy or peace, very much needed in all our lives.
“This day is holy to the Lord your God; do not mourn nor weep.” . . . “Go your way, eat the fat, drink the sweet, and send portions to those for whom nothing is prepared; for this day is holy to our Lord. Do not sorrow, for the joy of the Lord is your strength.”
One Nation . . . Blessed
In Western nations, America especially, we can see the Bible’s influence on many aspects of society. Everything from our laws to our work ethic to our view of marriage has been molded by a Judeo-Christian worldview. It has always been the case that the Word of God makes a difference in cultures where it is introduced. In first-century Thessalonica, a mob dragged some Christians through the streets shouting, “These men who have turned the world upside down have come here also” (Acts 17:6, ESV). It is only right that the Bible should have an influence on society, as it has an influence on the individuals within society.
God is the Creator of the world and the humans who inhabit it (Genesis 1). From the very beginning, God designed the world and people to “function” a certain way. When society doesn’t follow the principles that God gives us in the Bible, life simply doesn’t work as well. God’s the only One with the insight into how life functions to our best benefit, and He shares that wisdom with us in His Word. The Bible is described in Hebrews 4:12 as “alive and active.” This means, in part, that the Bible is as applicable and relevant today as it was when it was first written.
Looking back at the early stages of America, it is impossible not to see the influence the Bible had. Our government structure, laws, morality, education, and family values were all founded on principles that came directly from the Bible. The Founding Fathers, Presidents, and foreigners visiting a young America identified the key to the nation’s success as the biblical influence embraced by its society. When a nation honors God, it develops a respect for all of God’s creation. Where there is no honor of God, a society will fail to respect His creation, and people will suffer as a result.
From the beginning, people have had a choice whether to follow God’s way. But choices always carry consequences. The Old Testament history of Israel documents the societal laws and precepts God gave them. When Israel lived by God’s laws, their society functioned well, but when they deviated from God’s design, their society always went downhill. Attempts today to remove the Bible’s influence from society or to marginalize a biblical worldview reveal the pride of mankind that says, “We know better than the One who created us.”
None of this is to say that we should establish a theocracy such as ancient Israel had. God’s purposes in that system of government were for a certain time and place. However, when the Bible is properly understood, its influence on society can only lead to less crime, less divorce, less sloth, and more charity. As John Adams, the second President of the United States, wrote, “Suppose a nation in some distant Region should take the Bible for their only law Book, and every member should regulate his conduct by the precepts there exhibited! Every member would be obliged in conscience, to temperance, frugality, and industry; to justice, kindness, and charity towards his fellow men; and to piety, love, and reverence toward Almighty God . . . What a Eutopia, what a Paradise would this region be” (Diary and Autobiography of John Adams, Vol. III, p. 9). Scripture says it best: “Blessed is the nation whose God is the Lord” (Psalm 33:12).
At all times, remember.
THIS [The QTree] is a House of the Lord.
NEVER be afraid to speak His name.
Post about God – comments or articles – whenever and wherever you desire. FEAR NOT. God is with us, because we make sure He is WELCOME.
Wheatie Wisdom. If you bring snacks, bring enough for everyone. No running with scissors. No food fights. AI stuff posted, requires a link. Please use spoiler, for longer posts. Wolf Speak. No obnoxious behavior towards fellow QTreeper(s). Freedom of Speech is honored here QTree. But Do Know, every poster, IS personally responsible for what they post.
February 2021 marks the clear inflection. The rate of increase shifted to a new, steeper trajectory, a 3-to-4 sigma departure from the prior trend. In the years since, the survey has added seven million people. Growth of that magnitude in a mature population is not normal aging, not “long COVID” in isolation, and not some gradual sociological shift. It was sudden. It has persisted. And it continues to be treated as background noise by the same public health authorities who spent years obsessed with every other metric.
Let me address the predictable objections, because they surface every time these numbers are posted. First: “It’s just fraud. People are gaming disability benefits.” That claim collapses under basic scrutiny of the data source. This is not Social Security Disability Insurance claims. It is not SSDI awards, which lag, require medical determinations, and are subject to administrative backlogs and incentive effects. This is the Current Population Survey, the same monthly household survey that produces the unemployment rate and labor-force participation numbers. Roughly 60,000 households are contacted each month. Six simple questions are asked about serious difficulty hearing, seeing, concentrating/remembering/making decisions, walking or climbing stairs, dressing or bathing, and doing errands alone. Any “yes” classifies the person as having a disability for statistical purposes.
I laid this out in detail years ago in threads that are still easy to find. The series is real-time, not claims-driven, and has nothing to do with benefit eligibility. The questions have been consistent since 2008. Response patterns do not suddenly invent millions of new disabled respondents because the political winds shifted. When the same survey that markets, banks, and the Federal Reserve rely upon for labor-market signals produces a multi-year, multi-sigma break in disability prevalence, the responsible reaction is investigation, not dismissal.
Second: “It’s illegal aliens flooding the numbers.” This one is equally weak. Undocumented immigrants have long been known to under-respond or avoid government surveys altogether out of fear of detection, deportation risk, or general distrust of authorities. They are not lining up to answer detailed questions about household members’ health limitations over the phone or in person. If anything, the survey systematically undercounts this population relative to reality. The sharp, sustained rise in reported disability began in February 2021, well before the largest recent surges in border encounters, and has continued in a manner inconsistent with simple demographic inflows. The data do not support the claim that the disability spike is an artifact of illegal immigration.
Public health agencies and the media have largely ignored the signal. There has been no serious, transparent inquiry into why the disability rate changed slope so sharply in early 2021 and has remained elevated. Temporary explanations such as COVID itself, lockdowns, mental-health effects of isolation all fail the timing and magnitude tests. The virus was already circulating in 2020 without producing this sustained break. The sharpest acceleration aligned with the mass rollout and subsequent workplace mandates. Correlation is not causation; we are constantly reminded. Fair enough, but when a novel medical intervention is administered to hundreds of millions of working-age adults on an accelerated timeline, and the independent, high-frequency survey of population health then records a multi-sigma regime change precisely then, the burden of proof shifts. Authorities who spent years demanding every other correlation be investigated suddenly lose interest.
The economic implications are not abstract. More than 37 million people reporting disability means a permanently larger share of the population facing barriers to full participation. Labor-force participation among the disabled remains far lower than among those without disability. Employers face higher absence rates and higher costs. Insurance pools absorb elevated claims. The fiscal pressure on entitlement programs grows even if this particular survey is not the claims pipeline. All of it is occurring against a backdrop of demographic aging that was already expected to raise disability prevalence gradually but not at the abrupt rate observed since early 2021.
I have posted the charts for years: total population 16+, the civilian labor force subset, men, women, employed versus not. The pattern is consistent. Rate-of-change moderation appears occasionally, then another leg higher. The February 2021 inflection remains the defining feature. A 3-to-4 sigma shift in trend is not something serious analysts discard. It is the kind of signal that, in any other domain…markets, epidemiology, engineering…would trigger immediate forensic review.
Health authorities have chosen another path. The data continues to accumulate. The total population survey keeps printing higher numbers. The questions asked of households have not changed. The methodology is the same one used for the official employment statistics that move markets every month. Yet the disability series is treated as an inconvenience rather than a red flag.
The conclusion from the data is straightforward. The timing, the magnitude, the concentration among the previously healthy working age population, and the failure of alternative explanations all point to the COVID vaccine campaign as one of the primary driver of the excess disability. That is the assessment I have maintained as the numbers have updated. Ignoring a sustained, multi-sigma break in a core government survey does not make the break disappear. It only guarantees that the consequences continue to compound while institutions look the other way.
The July 2026 print at 37 million is simply the latest confirmation. The trend that began in February 2021 has not been explained by health authorities, has not been investigated with appropriate rigor, and has not been reversed. Until that changes, the data will keep speaking whether anyone in authority cares to listen or not.
Through my piss poor administrative skills, Slow Guy lost the link. Good news, Google will have it via basic search.
—
ht Wolf.
A few days back, Wolf posted this video. To REFRESH our memories, of the Covidiot nightmare we lived through.
100% well worth revisiting The J A B S.
Inside mRNA Vaccines – The Movie
The Bastards Have Doubled Down.
14 of 15 Must Go.
R E S I S T We Must!
—
Trump sparing lives on all sides… (Bonus. Conserving high tech ordnance.)
Trump is Using “Siege Tactics” on Iran
POTUS is perfectly content in our current position. He is utilizing a modern day version of siege tactics.
Rather than utilizing ground troops and mass casualties, he neutralized Iran from range, surrounded them, cut off their imports/exports, and is squeezing them economically.
So for those saying nothing is happening, or that Trump needs to hurry up, that we need a full-scale invasion, etc., you need to understand the approach. Trump is saving countless lives, while restructuring the global flow of energy, and waiting for Iran to collapse economically.
The only thing Iran have going for them, is that their handlers also control the US/Global media. Iran and global media, are both assets of the transnational criminal organization, known as the Deep State.
As Trump highlights below, “all they have is FAKE NEWS”. This is the only arrow left in their quiver, so to speak. Their only way to fight back is on the information battlefield, because they have already been destroyed on the kinetic battlefield. All they can do is try to convince the American People that Trump is a failure, the US MIL are losing, Iran is awesome, yada yada yada.
Health Friday is a series devoted to information about Big Pharma, vaccines, general health, and associated topics. There are Important Notifications from our host, Wolf Moon; the Rules of our late, good Wheatie; and, certain caveats from Yours Truly, of which readers should be aware. They are linked here. Note: AI-generated items in today’s offering will be cited as such. If readers wish to post AI-generated items in today’s discussion thread, they must cite their source. Thank you.
In Yours Truly’s opinion: Dr. Anthony Fauci; Dr. Rochelle Walensky; and, Dr. Vivek Murthy — all knew what they were doing in privately recognizing to each other that the modRNA COVID-19 bioweapon “vaccines” were dangerous to pregnant women; to the child they were carrying; and, that these “vaccines” could cause the death of the fetus in a “vaccinated” pregnant woman: while, at the same time, each of them were stating that these same “vaccines” were “safe and effective”, and that they would not pose harm to a pregnant woman or to her unborn child. There is no excuse for, no “qualifying explanation” for, no running away from, the fact that the lies these three physicians spread resulted in the miscarriage — the stillbirth — the death inside the womb, of thousands of babies due to the their expectant mothers getting COVID-19 “vaccinated.” The miscarriages — stillbirths — deaths of these children are on their hands.
The Shimabukuro, et al., paper of April 2021, attempted to gloss over the dangers of the COVID-19 bioweapon “vaccines” to pregnant women (https://nejm.org/doi/full/10.1056/NEJMoa2104983, “Preliminary Findings of mRNA Covid-19 Vaccine Safety in Pregnant Persons”, Tom Shimabukuro, et al; April 2021. At the time this paper was published, Dr. Shimabukuro was the director of the Immunization Safety Office of the CDC. Please see the screenshot of the “Results” section of the Abstract from the original April 2021 paper; followed by the screenshot of the “Correction” version of the same “Results” that was published on 8 September 2021:
However, neither the original Shimabukuro, et al., paper, nor the “corrected” paper, apparently mention the fact that, of the 3958 reported pregnancies in COVID-19 bioweapon “vaccinated” women (“pregnant persons”), only 827 pregnancies were “completed.” Which leaves 3,131 reported pregnancies that were NOT “completed” in these “vaccinated” women; in other words, about a 79.2% non-completed pregnancy rate in these “vaccinated” women — not the 12.6% negative pregnancy outcomes rate stated in the paper.
Yours Truly now turns to US9884859B2, the Patent granted in October 2015 to Dr. Ralph Baric, PhD, of the University of North Carolina, Chapel Hill, for his “invention” of the “template virus” for SARS-CoV-2. The following screenshots, below, are from this Patent: the Title and Dates Summary; the Figure 1; the paragraph from the Detailed Description of the Invention regarding the use of subgroup 1a-type viruses in the “invention”; the citations from the Patent for viruses used in the subgroup 1a section on the Figure 1 “virus tree chart”
Look at the phrase from the paragraph regarding subgroup 1a viruses that can be used in Dr. Baric’s “invention”: “…, as well as any other subgroup 1a coronavirus now known (e.g., as can be found in the GenBank (R) Database or later identified, and any combination thereof.” This means that ANY subgroup 1a-type of coronavirus can be used in the SARS-CoV-2 “template virus” that Dr. Baric “invented.” How does this tie into the miscarriages, the stillbirths, the live births of infants who are weak / low weight, and so on, to expectant mothers who were “vaccinated” with a COVID-19 bioweapon “vaccine”? First: Yours Truly believes that Dr. Ralph Baric shared information contained in US9884895B2 with Dr. Zheng-li Shi of the Wuhan Institute of Virology (as she was working on various coronaviruses, including SARS-CoV); and/or, he shared samples of certain subgroup 1a viruses with Dr. Shi. Second: Yours Truly believes that US9884895B2 was the “template virus” for SARS-CoV-2 “foundation” that ultimately became the “modRNA” (aka “mRNA”) used in the COVID-19 bioweapon “vaccines.” Regarding the citation in the Patent above, about Porcine Respiratory and Reproductive Virus (also called Porcine Reproductive and Respiratory Syndrome), please see the following screenshot from this website: https://www.merckvetmanual.com/generalized-conditions/porcine-reproductive-and-respiratory-sundrome/porcine-reproductive-and-respiratory-syndrome:
Regarding the Figure 1 of the Patent, please refer to the “1a” portion of the “virus tree.” There are three viruses listed: FCoV (Feline coronavirus); TGEV (Transmissible Gastroenteritis virus [swine]);, and, PRV (Pseudorabies virus [swine].) Please see the screenshot about PRV, below, from this website: https://merckvetmanual.com/nervous-system/pseudorabies/pseudorabies-in-pigs:
Why was Dr. Baric including at least two viruses that cause reproductive failure in swine in his Patented “template virus” for SARS-CoV-2 “invention” — Porcine Reproductive and Respiratory Virus (PRRV, aka PRRS); and, Pseudorabies virus (PRV)? Why was Pseudorabies virus (PRV) the only one listed on Fig. 1 from the Patent US9884895B2, unless this entire “virus tree” graphic is only listing examples of the various subgroup viruses that could be utilized in Dr. Baric’s Patent “template virus” for SARS-CoV-2 “invention”?
Yours Truly turns to one final item: Page 8 of the Pharmacokinetics Tabulated Summary report on BNT162b2 (COMIRNATY) given to the FDA by Pfizer-BioNTech in 2021 (https://icandecide.org/wp-content/uploads/2022/03/125742_S1_M2_26_pharmkin-tabulated-summary.pdf. Look at the BNT162b2 accumulations (assisted by the ALC-0159 and ALC-0315 lipid nanoparticles in this “vaccine”) in the Ovaries (12.3) and in the Uterus (0.456) in the Wistar lab rats.) [Note: this is aside from the fact that the COVID-19 bioweapon virus itself, as “invented” by Dr. Baric, has these two female fertility and pregnancy killers included in it — meaning that a female of childbearing age could, in theory, become infected with the virus itself, recover, but potentially have problems in terms of conception, carrying the fetus through pregnancy, and delivering a healthy child. The difference here, in Yours Truly’s opinion, is that if the female is non-COVID-19 bioweapon “vaccinated”, that person still has a relatively intact natural immune system to help fight off the virus itself and its negative effects. A “vaccinated” female’s natural immune system is damaged or destroyed by the COVID-19 bioweapon “vaccines” that she took. The mechanism of these “vaccines” is to induce a constant state of “fake COVID-19 virus infection” in the “vaccinated” persons’ body. In addition, the lipid nanoparticles ALC-0159 and ALC-0315 (in the Pfizer-BioNTech “vaccines”); and, the SM-102 (in the Moderna “vaccines”) move the ingredients of these injectables into every cell in the “vaccinated” person’s body.)] Page 8 is below:
Now, tie these accumulations in with the information above regarding the inclusion of at least two types of swine virus that cause reproductive failure (PRRV, aka PRRS; and, PRV) into Dr. Baric’s “template virus” Patent for SARS-CoV-2, US9884895B2. To Yours Truly, the combination of these inclusions; plus, the documented accumulations in the ovaries and the uteruses of the Wistar lab rats injected with BNT162b2 (COMIRNATY); and which version, by the way, was the same version for which the FDA granted the initial EUA for use in the United States on 11 December 2020, and which version is still the “foundational version” still used in all “descendant versions” of COMIRNATY since then; plus, the documented reports of miscarriages — stillbirths — live births with weak and/or low weight infants, involving pregnant females who were injected with modRNA COVID-19 bioweapon “vaccines”: all add to up something that is not a “coincidence.” It is, instead, a situation that cannot be ignored or minimized. It is, instead, a situation that must be fully investigated by the highest levels of government. In Yours Truly’s opinion: Pfizer-BioNTech; Moderna; and, Novavax, MUST be compelled to disclose the EXACT ingredients of the modRNA in their respective COVID-19 bioweapon “vaccines”, the AMOUNTS of these ingredients, and the EXACT formulations of their respective COVID-19 bioweapon “vaccines.” In addition, the above manufacturers MUST be compelled to disclose any and all communications with Dr. Baric regarding US9884895B2, and the use of any of the information in that Patent in their respective COVID-19 bioweapon “vaccines” formulations and manufacture.
THE USE OF ANY COVID-19 BIOWEAPON “VACCINE” ON PREGNANT FEMALES, AND ON FEMALES OF CHILDBEARING AGE, MUST STOP IMMEDIATELY.
Peace, Good Energy, Respect: PAVACA
(Intellectual Property Disclaimer and Notice: Except for the linked URLs and other items available on the Internet, the ideas and/or opinions in today’s offering are by PAVACA (M.E. Forbes, aka M.E.C. Forbes.) Credit must be given to PAVACA if ideas and/or opinions in today’s offering are used by other blog writers; by podcasters; or in print or social media.)
We have created this site as a place for people to openly express their thoughts and opinions. This is a place where honest but civil discussion of all topics is encouraged. This particular thread is – for the moment – TRUST THE PLAN Thursday. You are welcome to say what you think, in a civil and courteous manner that loves your neighbor. Free speech matters! Courteous speech makes it happen.
Please label all AI-generated content as being such, unless it is patently obvious (e.g., humorous AI images). It is important that we as individuals not begin to pretend that socially derived artificial intelligence is actually our own, as this form of stealthy social information averaging and feedback would be one more pretense and deception between people, in service of stupid Marxist socialism, and of those who wish to substitute their communally protected lies for actual truth.
You are you. AI is AI. Keep your identity. Don’t “Borg Out” on us!
And yes, it’s THURSDAY…again.
That was stolen from Wheatie.
Let’s steal her rules, too.
No food fights.
No running with scissors.
If you bring snacks, bring enough for everyone.
Other rules may be derivable from these, and that conjecture is left for discussion.
I decided that I would dump a dozen of my tabs once again. It’s cathartic. A few thoughts go out with each one.
(1) An old Wheatie post, from September 14, 2019, when this site was just shy of 1 year old. We were still on WordPress, and COVID had probably just been leaked from the Wuhan lab.
(2) An old Steve post, from the Qth of July, 2021, in the midst of COVID vaccination, when Steve covered Einstein’s early, revolutionary papers, laying foundations in both relativity and quantum mechanics.
(3) My 250th Anniversary thank you post, featuring Q = Quantum and a salute to our fallen patriots, in case you want to bookmark it. Also the finale on the Thursday posts with the Genesis stained glass artwork.
(4) A great video on Trump’s Main Street / Golden Age / reindustrialization strategy. Thanks to Duchess for bringing this to my attention.
(5) One of the best explanations of the Schroedinger equation – an intuitive physical and mathematical rationalization of how quantum mechanics arises out of classical physics.
(6) AI slop and eye-roll clickbait about Pluto is very interesting nonetheless. Much of this stuff is worth knowing. If you make it past the first repetitive, yawn-inducing, “delay of story” filler nonsense, it gets better!
(7) These two tabs go together. Think long and hard before you get an mRNA vaccine.
I wanted to let everyone know that my husband @DanVanAckeren1 took his own life on Friday, July 24, 2026. He was suffering for 5 years after the COVID-19 Pfizer vax gave him Multiple System Atrophy & other conditions. His was the 3rd suicide this week. My fight isn’t over. pic.twitter.com/iDGPNNKQo9
When you read about his case, you’ll understand that his life was a living hell. Please don’t roll the dice. Don’t trust these demons! They won’t have the mercy to just kill you – they will torment you until you kill yourself.
(8) Here’s an interesting argument leaning on the First Amendment – that restrictions on drug advertising would enable restrictions on energy advertising.
STEVE MILLOY: Banning Drug Ads Today Could Muzzle Energy Tomorrow
(9) Good habits are effective in helping people to NOT GET a nasty parasite in Hawaii, and those habits will serve you well here in the Great 48. Read about how to prevent rat lungworm brain infections, because that information will help keep you from getting other diseases here in REAL AMERICA.
(10) Horrible clickbait about fire ants is really an interesting ecology study about “horny toads” in Texas. Go ahead and click. Yeah, it’s AI slop, but it’s not terrible.